🔥🔥Wow. Our article is published! @BradSpellberg 🎉🔥🔥
A journey that started with a simple question: What’s in a name?
Today, I’m incredibly grateful to see our article published in @CMIComms :
“What’s in a Name? The Rise of Klebsiella pneumoniae: From Friedländer to Klebs”
This is my first publication as first author, and having this journey with my mentor, co-author, and friend, Dr. Spellberg, makes this milestone even more special.
K. pneumoniae is an organism I deal with almost every day—often as a notorious MDR pathogen. Writing this article gave me the opportunity to step back from the daily clinical challenge and explore the fascinating story behind its name.
From Friedländer → Klebs → K.pneumoniae.
Alhamdulillah. 🤲🏻
EnJoy!
#IDXposts
https://t.co/uDB9UsL53S
Well, in the era of ceftaz avi and other BLBIs, I'm not sure whether Chloramphenicol has a role to play. Maybe folks in CA disagree! @DrToddLee@sebpoule
🆕️⚡️LTE Chloramphenicol activity against carbapenemase producing Enterobacterales #IDXposts
https://t.co/ZdFGCIytvA
🆕💥🟢External validation of the PACTO risk score for infective endocarditis in patients with coagulase-negative staphylococcal bacteremia: a multicenter cohort study #idxposts#IEWiki https://t.co/m9bJxnkQ6A
@JulienPrvost5@DiorIzzy@JulianVentres@ABsteward@DrToddLee I almost never discharge on IV. Almost all patients can be switched to oral. Every now and then you find a patient who doesn’t meet the five criteria for oral switch (eg, gut doesn’t work, resistant to all oral options, etc).
@JulienPrvost5@DiorIzzy@JulianVentres@ABsteward@DrToddLee The clock starts in 2019 with OVIVA/POET. So we're only 7 years in. 10 more years until the battleship has fully turned. Ive been doing oral for osteo and bacteremia since 2006. For endocarditis later. But, I do think 10 years is realistic. Until then, Just...Keep...Swimming.
@JulianVentres@ABsteward@DrToddLee First, clunk their heads together like Mo to Curley and Shemp. Second, no IV lead-in for the Heldman S. aureus endocarditis RCT. Third, 12 RCTs of bacteremia show oral effective. Fourth, the bug doesn't know if you give the drug IV or po. Only that enough gets there to kill it.
SSC is a repeat offender of bad guidelines. we should collectively all just stop following them
but too bad CMS adopted SEP1. lousy process measures rebranded as "quality improvement" which is not supported by evidence. lactate is a really bad biomarker of perfusion. never been established that giving fluids to lower it helps. in fact it is worse when compared to a perfusion focused strategy
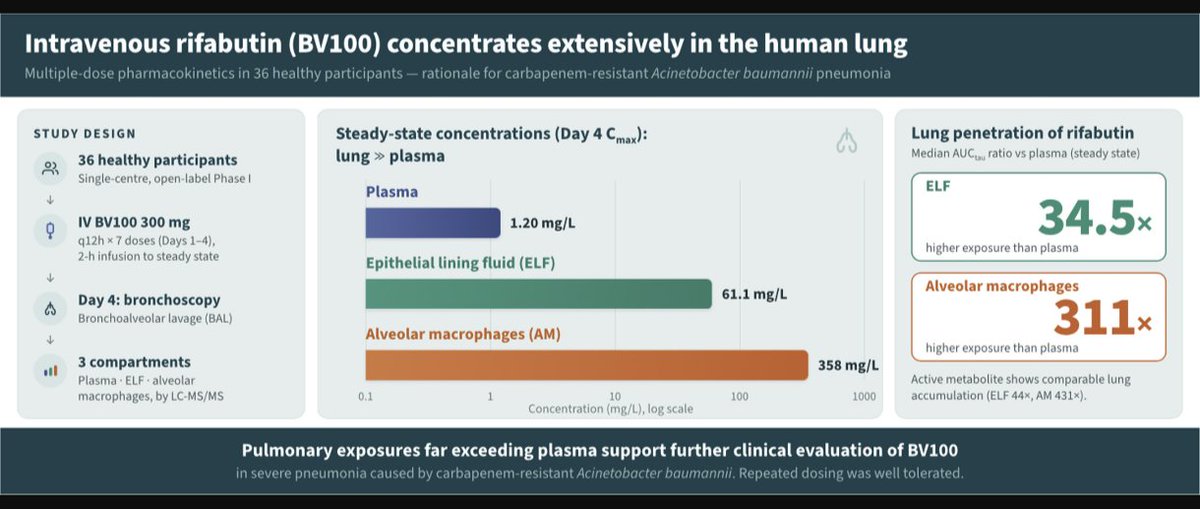
CRAB causes severe respiratory infections with limited therapeutic options and high mortality. Although rifabutin exhibits potent activity against A. baumannii, oral administration results in low bioavailability and variable exposure. An intravenous formulation (BV100) was developed to overcome these limitations. #IDXposts
💥Very interesting!!👀
An exiting option for CRAB!
Intravenous rifabutin (BV100) achieves pulmonary exposures substantially exceeding plasma concentrations, providing a strong pharmacological rationale for further clinical evaluation of BV100 in severe CRAB pneumonia
💥First human data on lung penetration of IV rifabutin (BV100).
•Lung exposures exceed plasma 35-fold (ELF) and 311-fold (alveolar macrophages).
•Active metabolite25-O-deacetyl-rifabutin shows similar lung accumulation #idxposts
https://t.co/Qjv7K6Kpot
💥Very interesting!!👀
An exiting option for CRAB!
Intravenous rifabutin (BV100) achieves pulmonary exposures substantially exceeding plasma concentrations, providing a strong pharmacological rationale for further clinical evaluation of BV100 in severe CRAB pneumonia
💥First human data on lung penetration of IV rifabutin (BV100).
•Lung exposures exceed plasma 35-fold (ELF) and 311-fold (alveolar macrophages).
•Active metabolite25-O-deacetyl-rifabutin shows similar lung accumulation #idxposts
https://t.co/Qjv7K6Kpot
Important to note this. “Bilateral lower extremity cellulitis” - very commonly said. Also Cellulitis not responding to antibiotics unlikely to be infectious unless other issues (ie peripheral vascular disease etc) .
Misdiagnosis of cellulitis is common! Approximately one-third of hospitalized patients diagnosed with cellulitis may have a non-infectious diagnosis.
🆕💥🔴Mimics of Lower Extremity Cellulitis: An Approach to the Red Leg #idxposts
https://t.co/bwNTNhwtYw
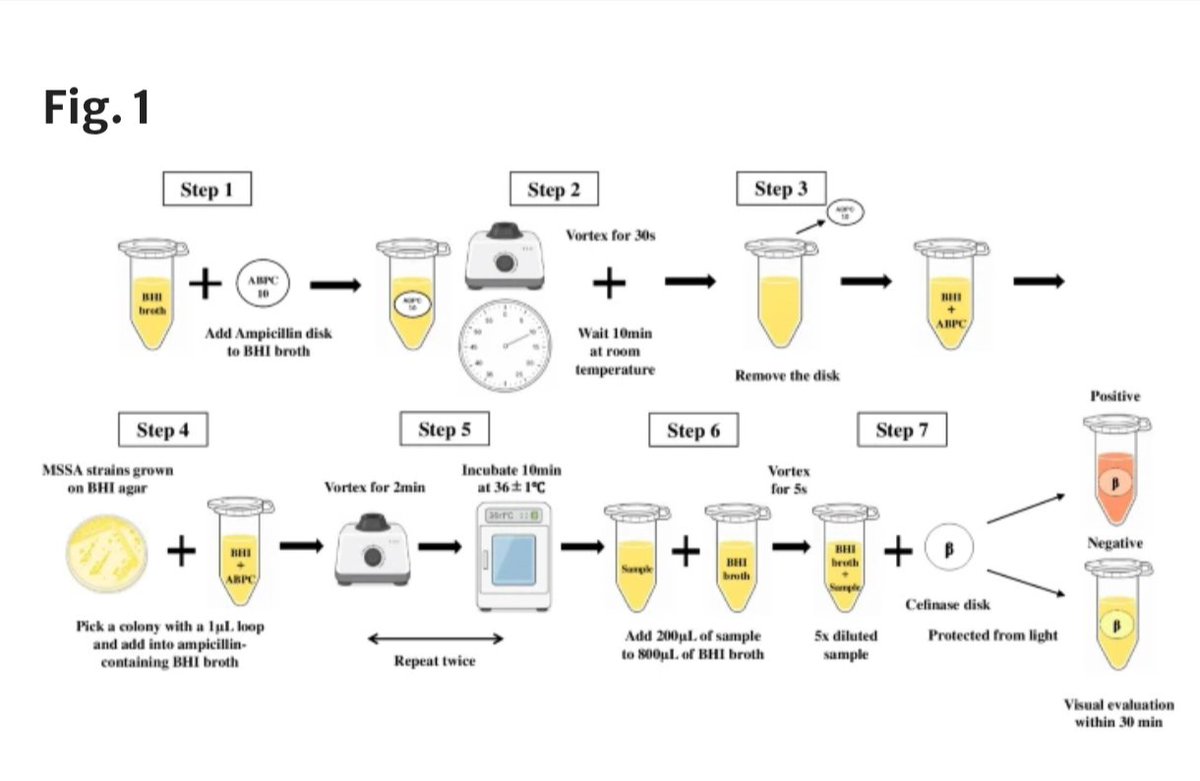
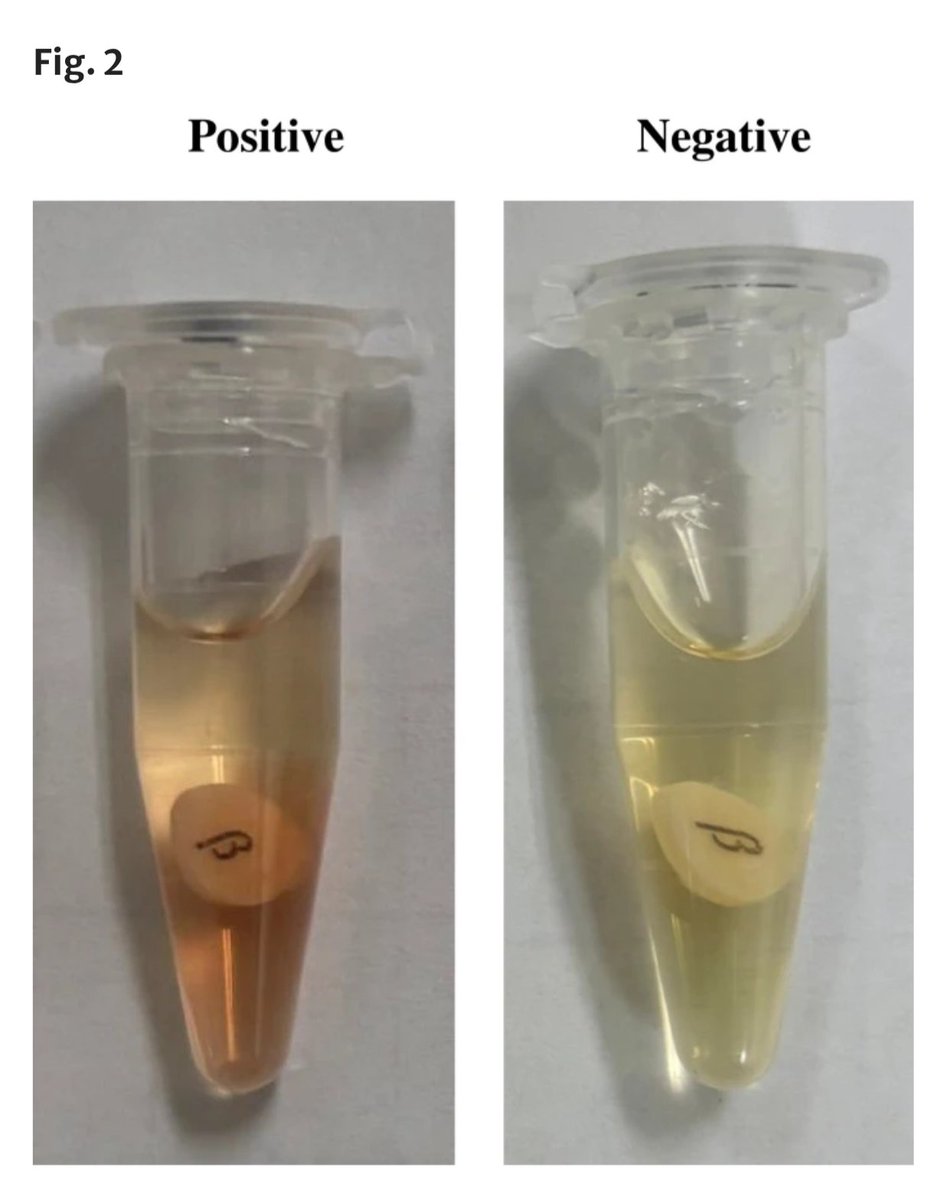
🆕💥🟢 Development of a rapid diagnostic test for the cefazolin inoculum effect in methicillin-susceptible Staphylococcus aureus: Cefinase disk direct (CDD) test
The proposed CDD test demonstrated satisfactory diagnostic performance for the detection of blaZ type A-harboring MSSA isolates #idxposts
https://t.co/5WQJfGalsI
🆕💥🔴Phase III clinical trial evaluated Silevimig, a bispecific anti-rabies monoclonal antibody targeting antigenic sites I and III, as a substitute for human rabies immunoglobulin (HRIG) in post-exposure prophylaxis. Silevimig is safe and effective alternative for passive rabies post-exposure prophylaxis #idxposts https://t.co/EeCvXGoJc6
🔥🔥Back online🔥🔥
IDSA/ESCMID 2026 Guidelines on Staphylococcus aureus Bacteremia: Risk Stratification, Diagnostic Evaluation, and Management of Adults and Children Part-1
#IDXposts
https://t.co/X1kOKsrVfg