A massive unexplained INR in a patient not taking warfarin, with relatively normal liver tests and platelets, should raise concern for SUPERWARFARIN. Do not delay treatment while awaiting specialized confirmatory testing.
Superwarfarin reversal is a long game. Vitamin K may be required for months.
Discharge only when bleeding is controlled and the oral regimen is stable; taper under lab guidance to avoid rebound INR elevation and recurrent bleeding.
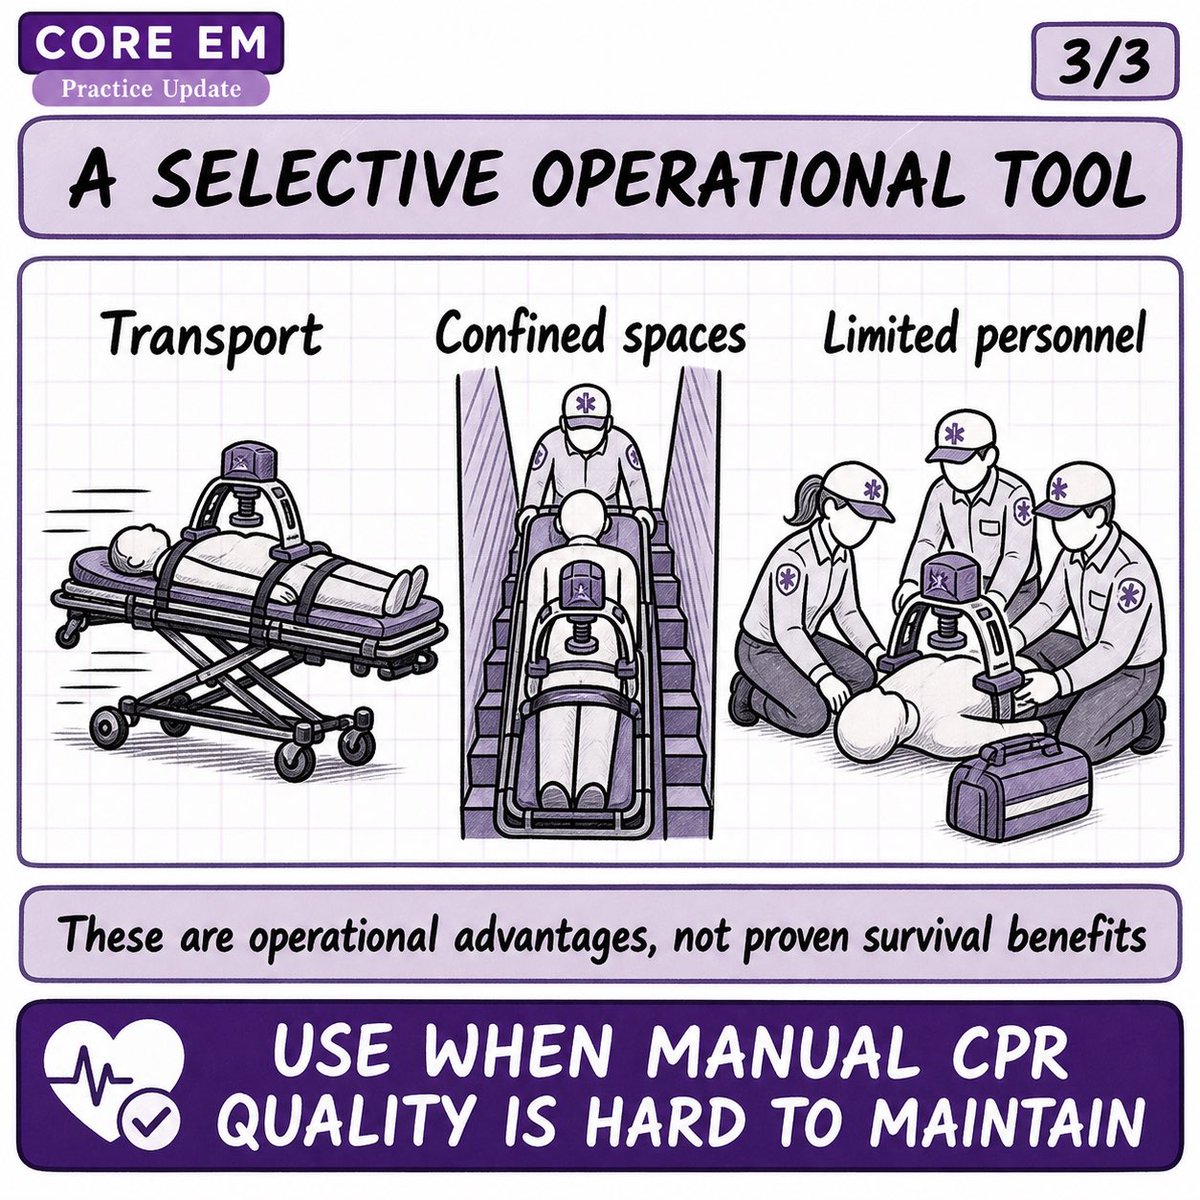
Mechanical CPR may help when manual compression quality is difficult to maintain, such as transport, prolonged extrication, confined spaces, or limited personnel.
That is an operational rationale, not proven survival benefit. Keep this in mind during your next resuscitation 🧠
🚨Btw, routine mechanical CPR has NOT improved survival or neurologic outcomes versus manual CPR in OHCA..
High-quality manual CPR remains the default rather than reflexive device deployment.. 🧵👇
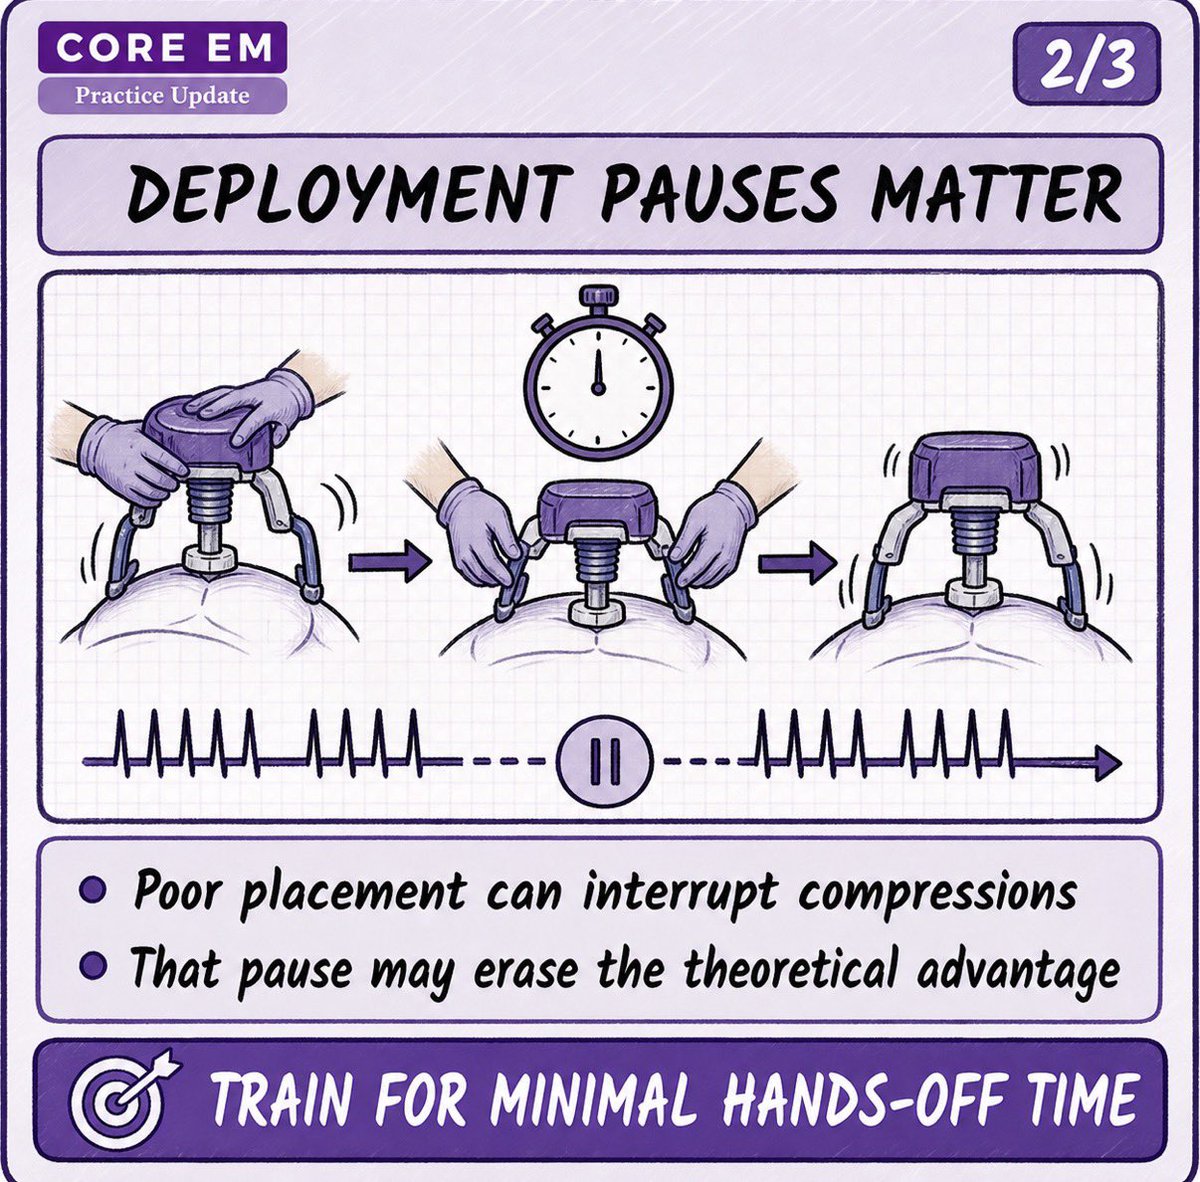
Mechanical CPR placement can interrupt compressions and erase its theoretical advantage.
Treat the use of these devices as a rehearsed procedure, with teams training specifically to minimize hands-off time ⏳
Mechanical CPR may help when manual compression quality is difficult to maintain, such as transport, prolonged extrication, confined spaces, or limited personnel.
That is an operational rationale, not proven survival benefit. Keep this in mind 🧠
Mechanical CPR placement can interrupt compressions and erase its theoretical advantage.
Treat the use of these devices as a rehearsed procedure, with teams training specifically to minimize hands-off time ⏳
Is ketamine really the safer choice for hypotensive patients before intubation? This RCT challenges this commonly held assumption. Etomidate's adrenal suppression may be more theoretical than we thought.
Full breakdown on our website: https://t.co/0B23XQJxaP
🚨 Post-ROSC Pearl:
Code-dose epi (1mg IV) wears off in ~3 minutes.
That’s your rearrest window.
Have push-dose pressors at the bedside BEFORE the crash comes.
Don’t wait for the monitor to tell you what you already know.
Have a listen for more pearls:
https://t.co/CS3raPATLk
💉 Naloxone Tips:
Titrate to respiratory effort, NOT full consciousness.
Start low 👇 (0.04-0.1 mg IV) and repeat.
Slamming a full 2mg can trigger acute withdrawal, vomiting, aspiration, pulmonary edema, and a combative patient.
Less is more. Titrate up 👆.
Full article (oldie but goodie): https://t.co/QivYK4kk2H