"When the hospital gets busy, immediate reaction from the people with managerial roles is to post a message in a large group asking clinicians to discharge patients. These can be sent at any hour, blurring the lines between professional and personal time." https://t.co/lGXg2llj9V
Dr. Brittany Rance discusses Ten Palliative Care Pointers for acute medicine at #HR24
So important for anyone caring for acutely ill patients!
Some that I admittedly don't think of but definitely will now! 👇
#1: Early palliative care for all
- improves Quality of Life
- decreases LOS in hospital
- decreases death in hospital
- potentially prevents inappropraite interventions at end of life
#2: Opioids Around the Clock
Goal is to stay in therapeutic window
Do not skip the overnight medication
#3: Choose short acting opioid for acute situations
Eventually, can transfer to a long acting.
When pt. on long acting agent comes into hospital consider transitioning to short acting which is more titratable and safe (especially if worried for adverse effects)
#4: What else works? Don't forget adjuvants
Sometimes side effects of opiates limit treatment.
Lots of other agents: NSAIDs, Dexmethasone, Anti-spasmodic, Anti-convulsive for neuropathic.
Consider topical medications: Not another pill with some moderate evidence.
Topical agents:
E.g. Methadone (wound/fungating mass) Amitriptyline-ketamine (neuropathic / malignant)
Diclofenac (MSK)
Camphor-menthol-hydrocortisone (itchiness)
#5: Medication Not Working? Consider changing route!
Oral medications might not be absorbed well. Consider alternate routes (IV, subQ, rectal, SL, topical etc.)
Consider SubQ: Rapid action, no IV access required, slower peak plasma levels, can be transitioned to hospice, minimizes extra fluids.
#6: Choose antiemetics by etiology
Often nauseas is multifactorial - choose based on the most likely etiologies as this will treat the symptoms better.
Good first line:
1. Metoclopramide
2. Haldol
3. Zofran
Gravol common but might not always be the most effective
#7: Constipation is prevalent and should be treated!
Be prophylactic with a REGULAR Bowel protocol
Docusate is ineffective --> just get rid of it!
Good regime: PEG daily and/or Sennosides QHS to start.
#8: When there's been a change, recognize dying.
Imminent death within 3 days suggested by:
Absent radial pulse
Respirations with mandibular movements
Inability to close eyelids
One common scenario is opioids being withheld in this population because of concerns of drowsiness, but really, the drowsiness is due to the dying process. Keep opioids going!
#9: Anticipate Terminal Delirium
Very prevalent. Hypoactive or hyperactive . Hyperactive delirium can cause a lot of distress --> hallucinations, picking, disrupted sleep cycles.
Anticipate this and treat --> Methotrimeprazine, Loxapine, Midazolam etc.
Consider modifiable factors --> urinary retention that needs foley, untreated pain, unnecessary vitals.
AVOID restraints! Use pharmacologic agents.
#10: Checklists for Medications at End of Life Care
Domains to address
Pain
Secretions
Dyspnea
Delirium
Seizure
Bleed
Fever
Congratulations again to the Mater Misericordiae University Hospital who won the coveted Golden Hip Award for the second year in a row. Louise Brent, Irish Hip Fracture Database Audit Manager, made the trip to the hospital last Thursday to meet with some of the Hip Fracture Governance Committee and officially present them with the Golden Hip Award for 2022 data. #IHFD2023 @Marymullenmate1
just to be told payroll is closed and they will be deducting it all from my next single pay. Thanks @HSELive@ULHospitals Merry Christmas to you too 🎄☺️
So I clarified with HR/manpower whether I was on the right pay scale, they told me I wasn’t even though I was, proceeded to over pay me on a whim, instead of investigating appropriately, and then told me I was overpaid
and that someone was going to get in touch to sort out a payment plan to which I had to reach out to attempt to set up one because I received no communication until an email came in to say how much I was overpaid,
And finally, both teams had the opportunity to bring their scenarios from beginning to end using the #WICOPSIM lab. It was incredible how effective the scenarios were given such a short prep time!
As a senior resident, I thought I had a pretty strong understanding of sepsis and septic shock.
But after doing a deep dive, I realized there's so much nuance.
Here's my approach to workup and management, along with some key pearls and lessons.
- Thread -
1/26
How are SHOs expected to pay €605 on Medical Council fees, a few weeks before changeover (which means double rent for some and emergency tax for almost all)?
Oh sorry I forgot, all doctors are millionaires
Dear @SteveBarclay,
There seems to be a lot of interest on UK #MedTwitter (@RoshanaMN) in how enticing Australia is for UK docs. Here are a few examples, from a junior doctor who made the move, of the international market you're competing with.
You should be worried.🧵
It’s not hard understanding why when you almost get run over twice in a week because drivers and motorcyclists in Dublin continue to run red 🔴 lights with no repercussions.
1/ Readers on plans to cut car use: “I made the switch from car to bike 20 years ago, and haven’t looked back... Unfortunately, the sometimes hostile nature of cycling in Dublin, particularly in rush-hour traffic, is a big deterrent for a lot of people"
📢OUT NOW📢 'Joining the dots: A blueprint for preventing and managing #frailty in older people' has now been published! This report shows what good-quality age-attuned integrated care for older people looks like. Find out more here https://t.co/SRHQX40qJP #BGSBlueprint
1/THREAD
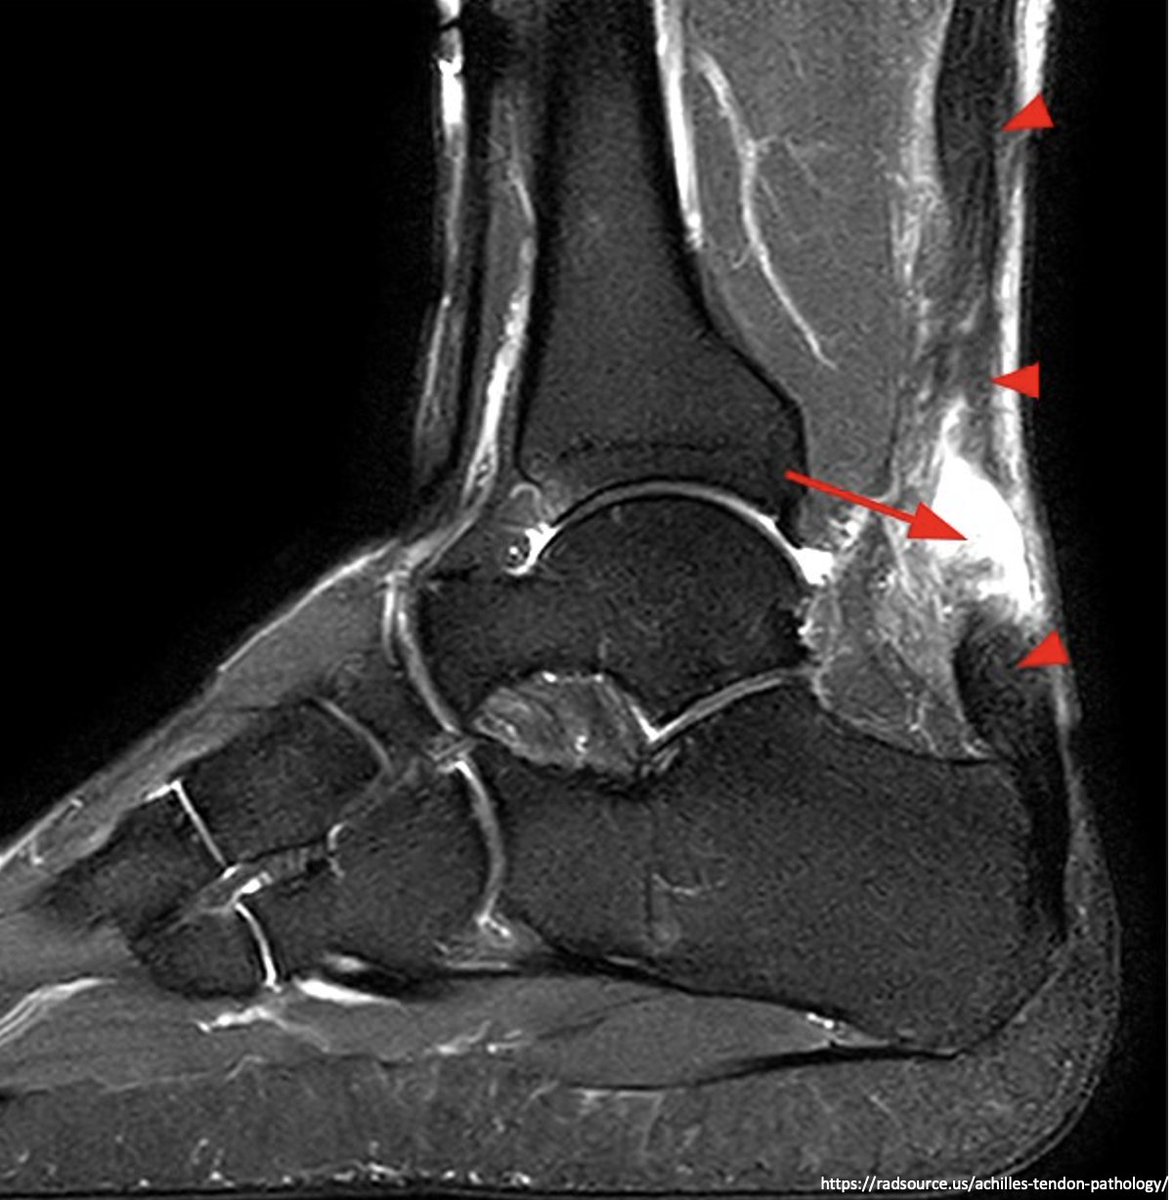
Ever wonder why fluoroquinolones increase the risk of tendon rupture?
It seems so random that a whole class of antibiotics could cause tendon injuries, but the risk is real.
#medtwitter#tweetorial