This “soft” generation is likely to be the first that has the balls to stand up to the ever expanding legions of vultures decimating doctors.
So many in the past have suffered endless abuse and pretended it was a badge of honor. The upcoming physicians may be weak on handling abusive work environments but they’re damn strong on fighting to change them.
I may lament the groups of medical students who had the gall to disrespect me on rounds or during anatomy labs, but these same people will group together and use the actual power physicians hold when pushed. Unlike the generations of strong physicians that displayed their immense power by surrendering every shred of it they had bit by bit.
We’re raising a generation of baby shit soft physicians.
Train how you’re gonna play.
We interviewed a guy this week for an eat what you kill private practice ask what happens if he needs a wellness day off.
“Do I still get paid?”
Baby. Shit. Soft.
I agree with much of what you’ve said, except that undergoing medical training means I owe a debt. What was tuition for? What was all the abuse of residency about? I generated much, much more revenue than I ever saw as income. Hundreds of times more. I paid hundreds of thousands of dollars. I gave, I am certain, years of life expectancy. No one just showed up and bestowed me with the gift of being a doctor. I paid for it, suffered for it, and earned every bit it.
People don’t talk this way about teachers or lawyers or plumbers or farmers or anything else. For some reason doctors are the only ones subjected to this scam, and under all the sophistry it’s just that people want to use us, and they wrap the exploitation in this kind of language about a calling, a debt, whatever. This is a skill I paid dearly to develop and I now sell and it ought to be up to me how I sell it and to whom. I’m a nice guy and I don’t want to see people suffer who I could otherwise help, but that’s me being charitable, not me paying a debt, and one sure fire way to make me feel a lot less cheery and charitable is for the person I’m helping to respond not with gratitude but it’s polar opposite: entitlement.
I never owed society a damn thing and despite that I’ve given well beyond what could be reasonably expected.
Whatever imaginary debt I owed for receiving medical training was paid over and over again.
I am going to side with doctors here
I do appreciate your support on X, which I have witnessed, and I agree with you 100% that society invests in medical training and each doctor owes a debt of some degree for that.
But it is not an interminable one.
By the time most doctors (my generation especially) completed training, we did a huge amount of charity care, well in excess of the resources invested in us
Even after that, most doctors take call for free for their practice (insured or not). Even though we get paid when we see patients, we remain available for 24 hour shifts every day (in shifts, but still) without pay, covering every Holiday, 365 days a year. This is typically without any extra pay (there are exceptions)
But that is not all
Debts and responsibilities go both ways.
When I graduated, doctors were largely afforded a large degree of latitude and respect, most of it merited. And for the respect and responsibility we carried, we were given tremendous agency to do our job.
That has been withdrawn, bit by bit, piece by piece.
And in its place has been instead an endless list of things we MUST do, while at the same time withdrawing our agency. Most of it done without our permission (except for the orgs that claim to represent us, but do not). I suspect you would agree with me on this.
We are now told what to do, how to do it, and in which form we must document it.
We are asked to fight with patients' insurance companies to secure care, while we remain responsible for the outcomes. Even if our appeals succeed 90% of the time, our decisions are still questioned.
Our pay (as independent practitioners, not employees) has been static for 30 years while every other part of healthcare has enjoyed raises in excess of inflation.
We have been disgraced on live television by a sitting president (Obama) characterizing the entire profession by the worst of us.
And politicians have openly said they intend to dismantle the independent practice of medicine, intending to force us to effectively work for corporations or the state.
For this reason, and paraphrasing Reagan ... I didn't leave Medicine. Medicine left me.
If I retire before 65, it will not have been my original intention, since I planned to work to a ripe old age.
But it will happen without guilt that I violated any obligation, which has been paid more than enough.
They are treating their algorithms as though they have feelings and moral standing. This is weird as hell. Full on dystopian. Imagine if a car dealership made you sign an agreement that you wouldn’t be unkind or cruel to your vehicle. Batshit insane.
I’d love to see a patient and complete an NCS/EMG on the same day.
I also love the having electricity and a staff.
They’ve decimated payments for decades now, and want to go further, which will force even less to be done in a visit to stay afloat.
Give it a few years and I’ll take a history in one visit, do the exam a week later, and write the assessment and plan a week after that. 10 minutes each visit. 99203, 99213, 99213. NCS/EMG one limb a week later. Then another one a week later, and so forth. 95909 x 4 and 95886 x 4. The first 3 will recommend testing the next limb for clarity.
Patients will love it.
@dcnh42@BrentAWilliams2 Btw, that insurance price fixing doesn’t apply to commercial insurance. Only Medicare and Medicaid. Another problem with having government involvement.
You realize that essentially none of this is set by physicians, right?
Physicians as a whole share blame for it getting to this because we caved like the cowardly weaklings that we are, but we’re not the villains here.
And younger physicians like me inherited this mess with no individual power or collective will to change it.
@grok@blindmelon9@CosmicNeighbrs@MattWalshBlog So in short, the claim is accurate when you account for what the person personally paid. And it’s far worse when you add other entitlement programs
You have a child’s view of how medicine should and is run. For example, you think doctor’s are required to take an oath. You think patient’s failures to follow instructions are somehow not their own fault.
The responsibility for your health is yours. No one else’s. Meditate on that. Doctors do what we can. Few listen.
I’m looking forward to those rewards though. I’ll be on the lookout for society showing me an ounce of respect and not the usual where society is mostly composed of people who haven’t got the foggiest clue of what the hell they’re talking about lecturing us about everything we do wrong while they do nothing for themselves.
AI cannot read a CT better than radiology residents.
AI cannot take an accurate history.
AI cannot perform a physical exam.
AI cannot reason about which tests are high yield and which are low yield.
AI has zero chance of replacing physicians.
As I’ve said before though, it can absolutely replace >90% of everyone else involved in medicine today.
The people who think AI can replace physicians are quite frankly retarded. They have no idea what they’re talking about and no idea what we actually do.
A subocclusive thrombus would not cause syncope alone. If you think you’ve seen a case of that, I invite you to improve your eye exams. It would cause additional symptoms and findings. The extent of tissue involvement to lose consciousness is too large.
I can think of a guy who had an episode of syncope and had a stroke later that day that was completely unrelated. It also may have been related via arrhythmia as you said, in which case the arrhythmia still requires investigation if it was enough to cause syncope and generate a thrombus (that’s not afib friend). Which brings us right back to my original statement that his cause of syncope still needs to be investigated if he actually had syncope and not something lazily and incorrectly described as syncope.
And I don’t know why this imagining was obtained beyond what is listed on the post.
Not sure how many times I can say this, but true syncope does not require a CTA (or any cervical/cranial vascular imaging). They get ordered constantly and they’re all dumb to get.
Ordering a CTA for syncope without a really, really good reason is the real malpractice.
Probably the dumbest reason to order a CTA, and I say that as a fan of the CTA.
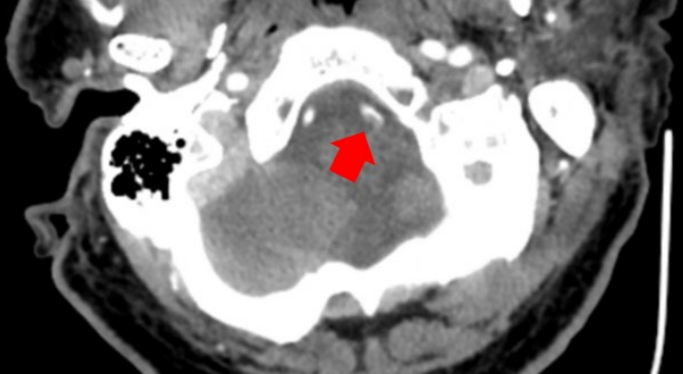
63-year-old man presents with syncope.
ED: CTA head and neck
This finding in the intradural left vertebral artery is alleged to have been missed (real case image).
The malpractice complaint states the patient re-presented 9 hours later with distal embolization to the basilar artery (subocclusive) and left superior cerebellar artery (occlusive), resulting in permanent injury.
@AnActualRad Sadly it probably is that high.
I get so many syncope referrals as well. Patients who haven’t even had an EKG with a stat neurology referral.
The patient you’re describing would have exam findings and would not be a simple syncope.
People do not lose consciousness from a basilar thrombus (or any thrombus impacting the posterior circulation) and have normal neurological exams or at least a clear TIA syndrome. The extent of the area involved to cause loss of consciousness is too large.
Hence why I said if this was legitimate syncope as I defined above, then this test was not required in the first place and he still needs to be evaluated for syncope.
Considering this is the image shared for the lawsuit, this is likely the best he has.
@willessd@BBillDavis Your inability to read is not my mental gymnastics.
You have helped to convince me that at least one physician can easily be replaced by AI.
@lfstevens AI is extremely useful in limiting diagnostic blindness. I use it partly for this reason. If you feed it accurate information, it is incredibly helpful. It gets you to think of things you otherwise wouldn’t.