Tina is 57. Competitive runner in her 30s. Then life happened — kids, loss, single parenthood. Her running stopped, and she no longer went to the gym.
When the kids left for college, she started running again. Came back too fast. Got hurt. Then hurt again. Then her knee wouldn't settle.
Her MRI showed a meniscus tear. The first surgeon said she needed surgery. Same with the second. She came to me for a third opinion.
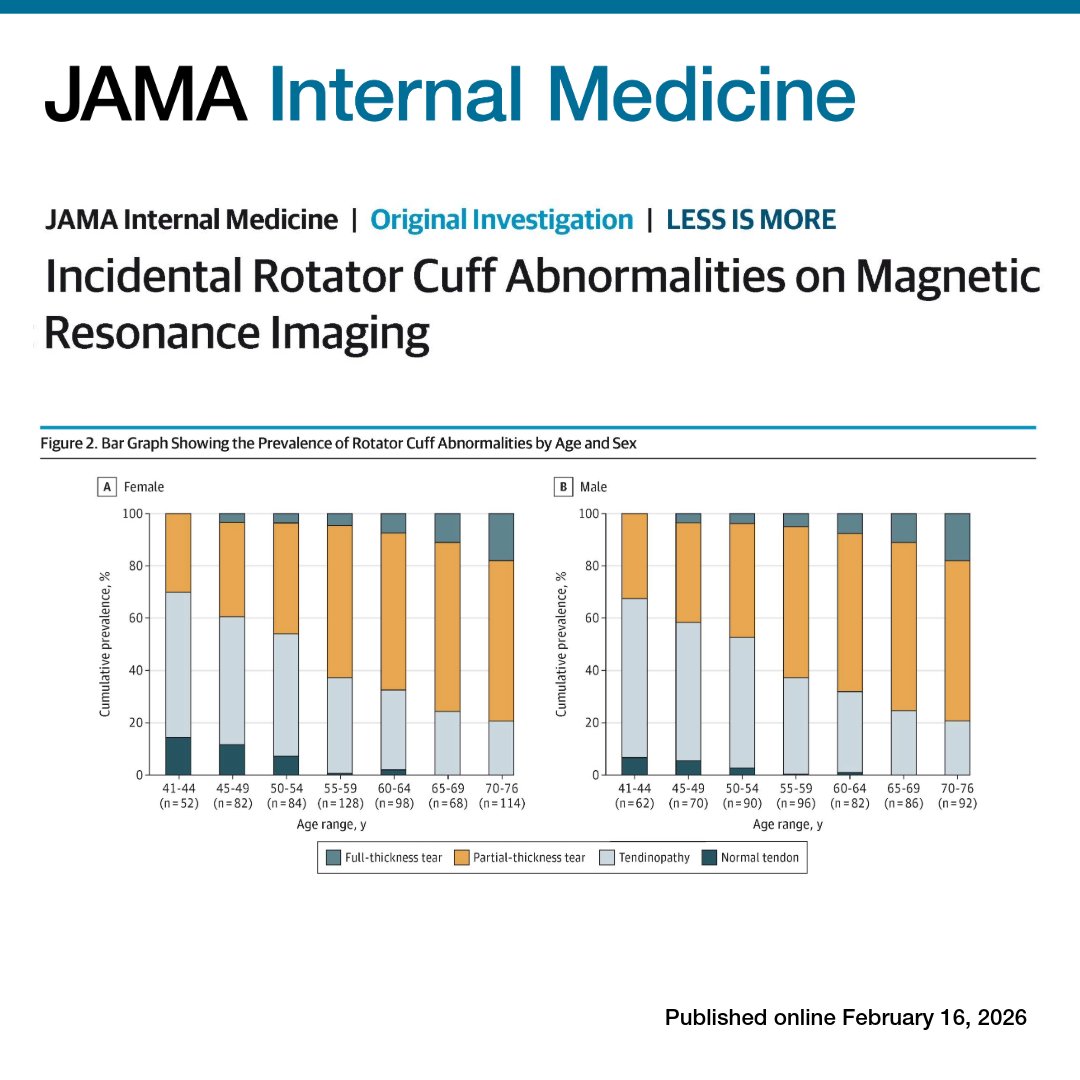
From @JAMAInternalMed: #RotatorCuff abnormalities on #MRI were found in 99% of adults aged 41 to 76, including 96% of asymptomatic shoulders, indicating most findings are age-related rather than disease.
https://t.co/f33KbhzT4z
@DrNadolsky@MichelleCardel Not only are the results impressive, but getting 77% of the particiants to stick with the program for 12 months is spectacular. Great work to you both and your team. Thanks for clarifying
@MichelleCardel I'm confused by the retention rates. The 12 month retention seems to be 8.7%. 69850 initiated treatment, yet only 6089 stayed on the program for 12 mo. Is that a correct interpretation?
@sdktri4life@hjluks Not a physician...a physical therapist. They have the time and access. They have the knowlesge to both assess and more importantly implement the treatment, including many of the associated comorbidities. Also, important to acknowledge diagnosis is not just based muscle mass 1/2
@am_dpt7 2/2 b. public speaking(C of Aging, Rec Dept, rotaries, schools), c. Host workshops and webinars d. Host free screens e. Write (free reports, blogs, email blasts). All will help demonstrate our value through sharing our message and abilities to our communities. Start locally.
@am_dpt7 A couple ideas: 1. Provide high value,high impact care beyond addressing pain, such as increased strength, general health (weight managment, disease risk modification). 2. Be better marketers to clarify our value to the community, Which means: a. Networking (BNI, COC) 1/2
"... high intensity resistance training is as effective as other treatment or other exercise to improve disability outcomes for people with chronic low back pain, and potentially more effective at reducing pain symptoms than other exercise." https://t.co/2GAiaQofg9
@norton_cfna @PaulBliton Regulatory issues often impede this, unfortunately. Ideally it would be like the mental health space... Pyschologist and LMHC/LSW working together in the same office. But it can be done with some creativity. As a result, S&C creeps into rehab, rehab creeps into S&C. Everyone wins
@norton_cfna @PaulBliton I think if more PTs moved into the fitness space, and more trainers/ S&C moved into the rehab space, patients/clients would benefit. Being territorial does more harm. Blending expertise provides more benefits.
@PaulBliton I have never seen or heard of a PT practice implementing a combination of high volume olympic lifts, calisthenics, plyometrics, and metabolic conditioning within the same workout for patients. Where do you see this happening?