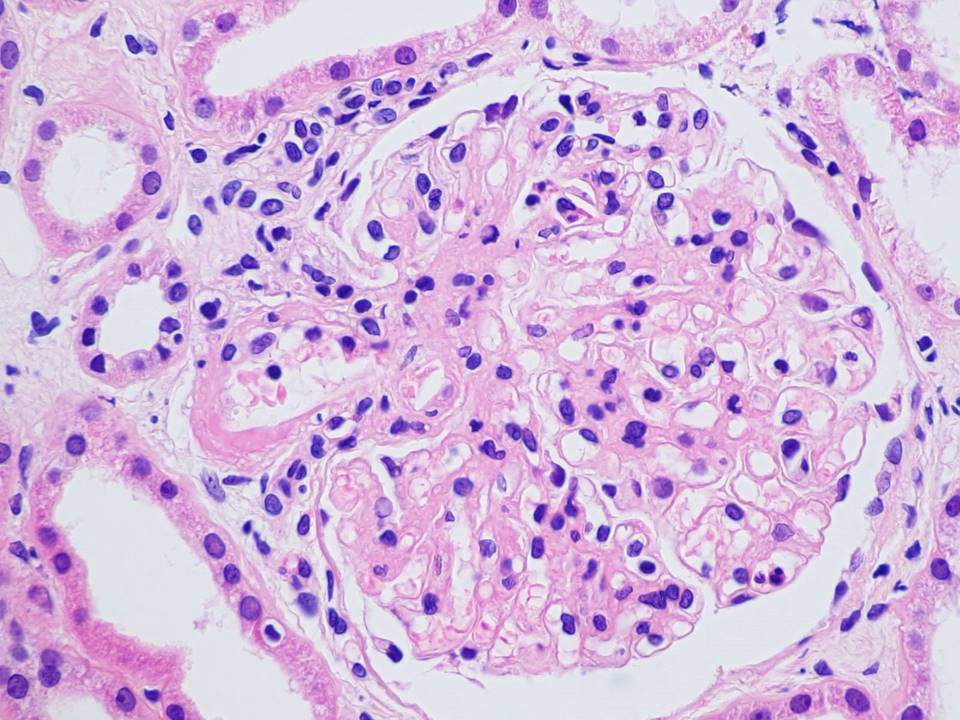
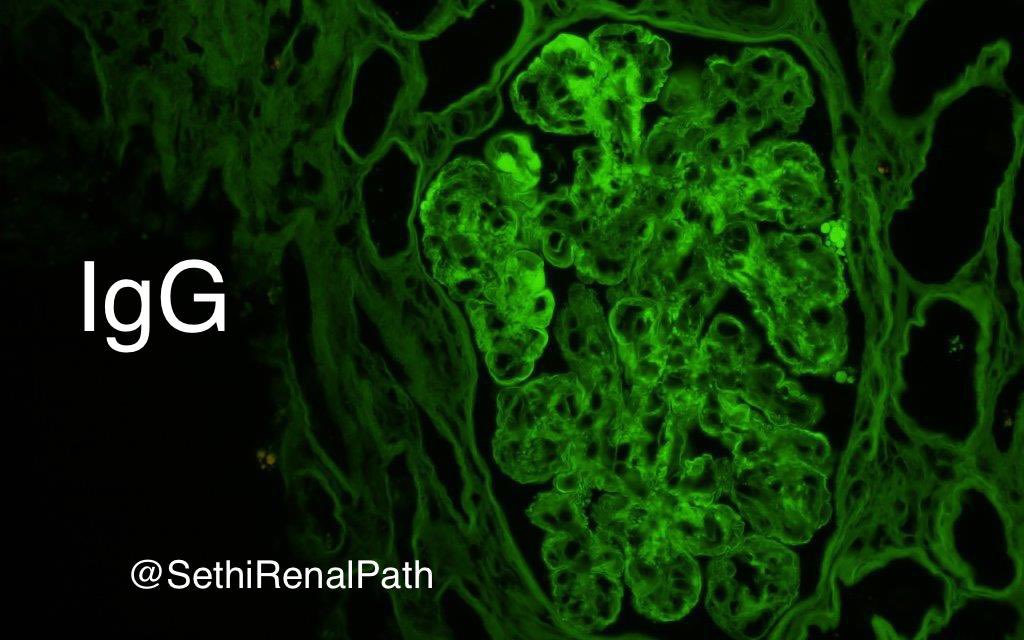
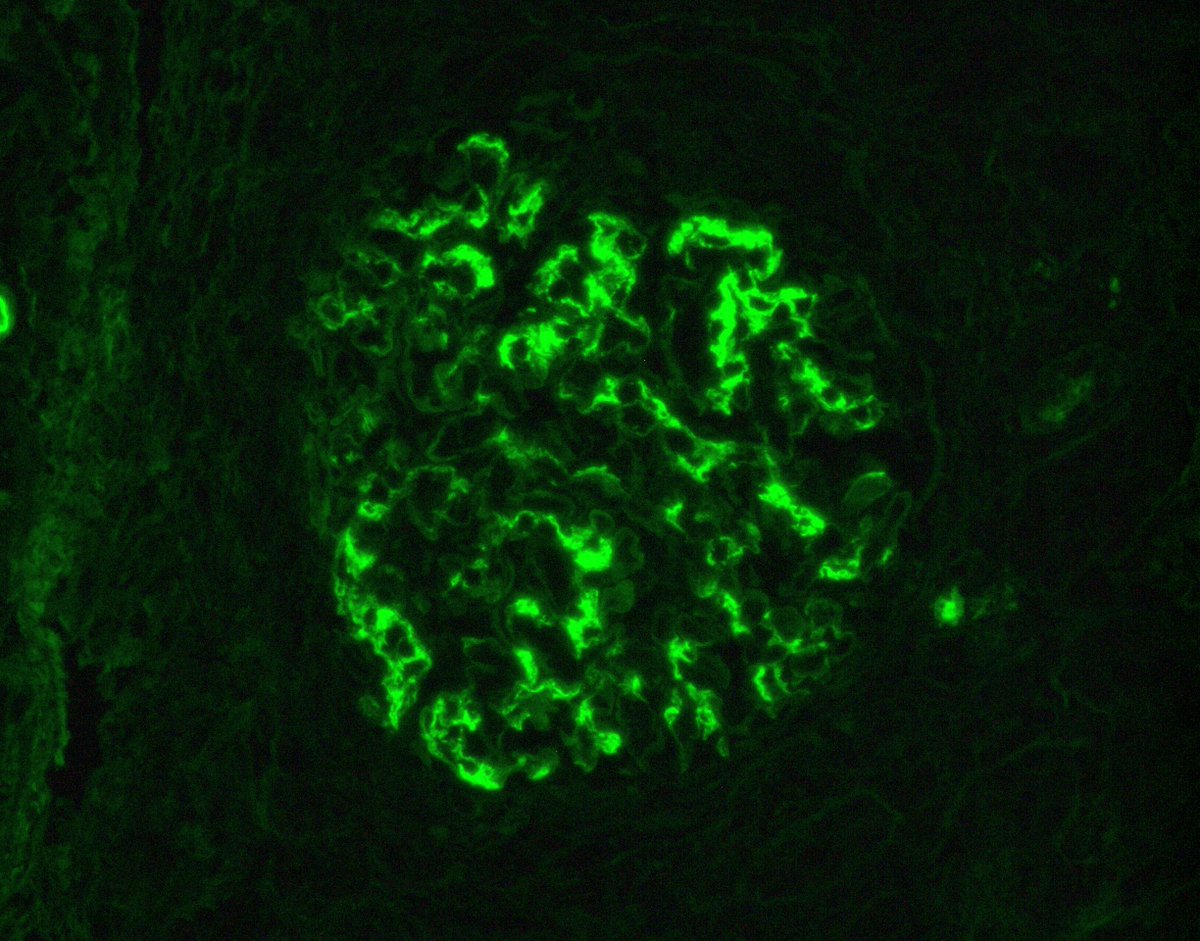
Sometimes a simple stain can make a pathologist’s day. In this case, positive NELL1 in a case of membranous nephropathy today.
Dx: NELL1-associated MN.
79 yr-old smoker with 2 grams proteinuria. Cr 1.7
Will need malignancy work up, as NELL1-MN often associated with malignancy.
Good teaching case today.
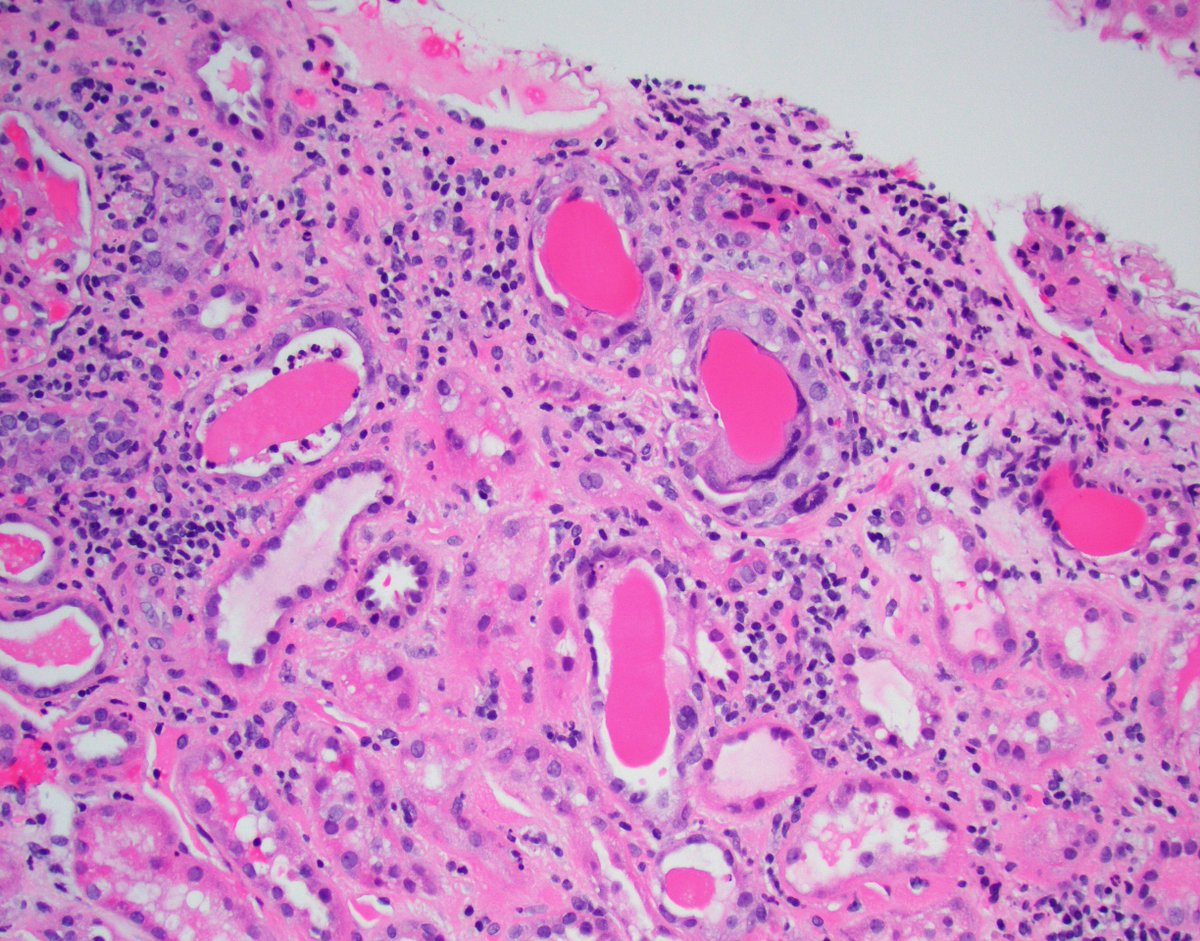
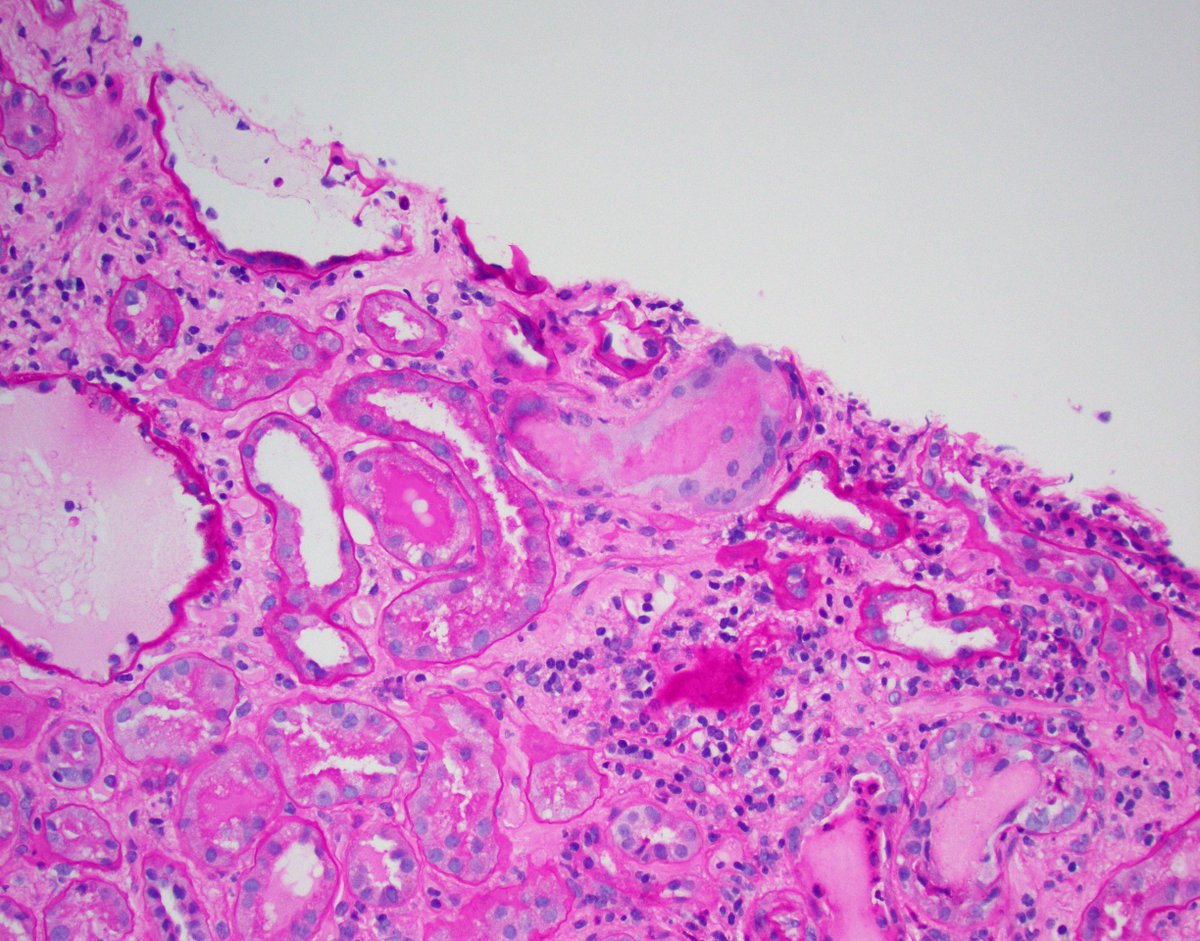
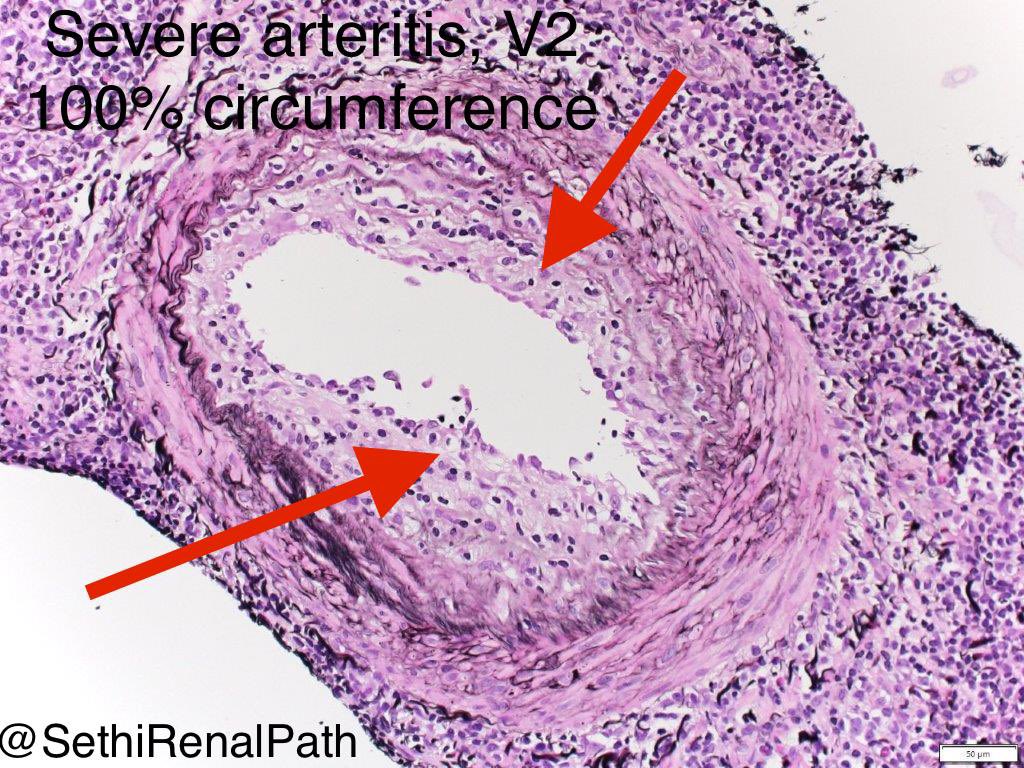
Severe arteritis, with large # lymphocytes under endothelial cells
Arteritis, involves entire 100% circumference=V2 lesion
V2=>25% per criteria
Dx:Acute cell mediated rejection, Banff 2B
C4d neg
45 yr old 1 month post transplant ⬇️immunosuppression
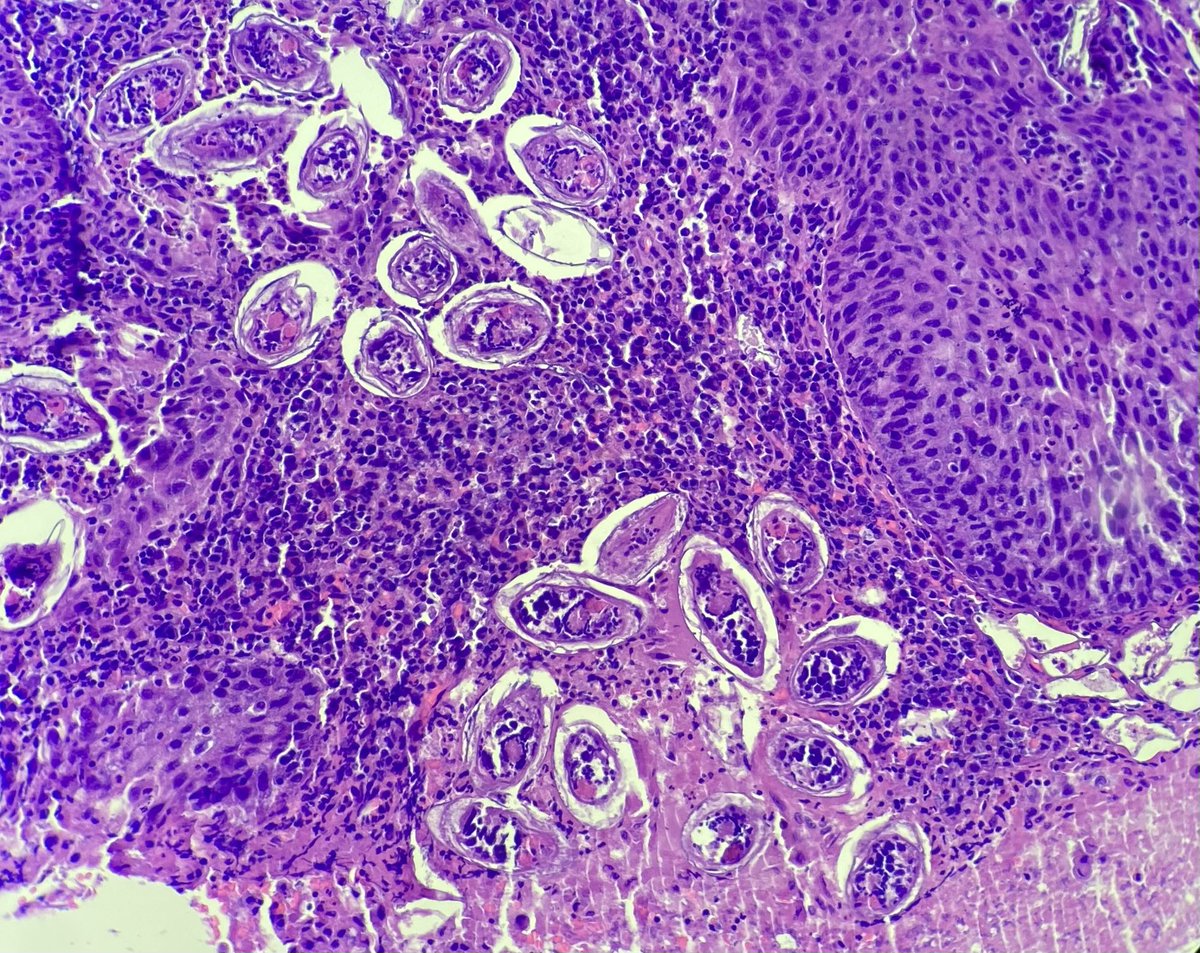
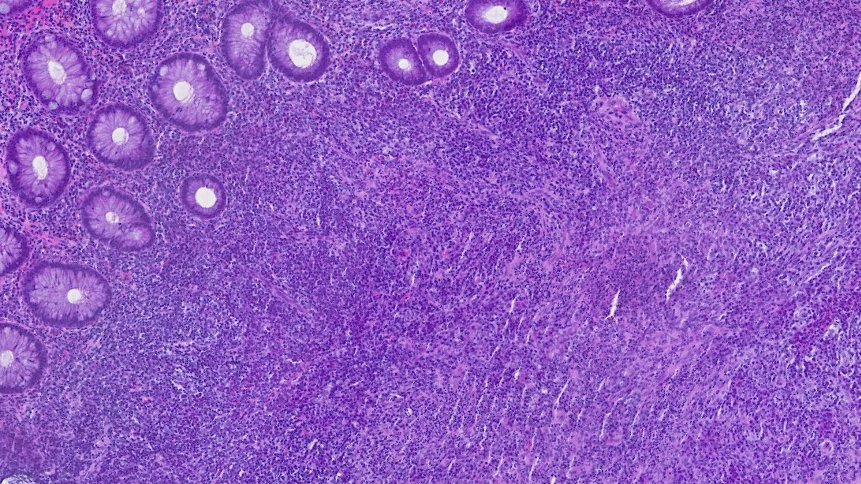
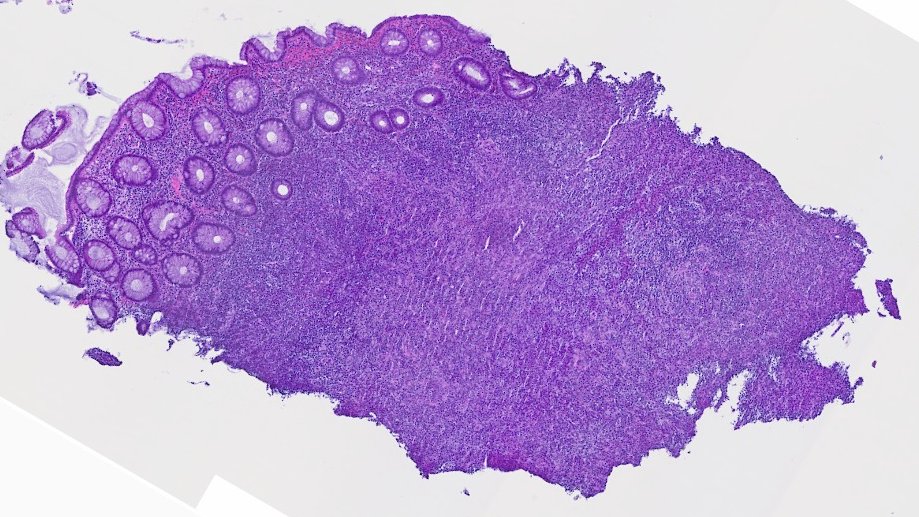
🪱SYPHILITIC PROCTITIS🪱
🚩ALWAYS advise to rule out ITS in rectal chronic active proctitis! And remember: a negative Treponema stain is not enough.
😮Can mimic CANCER or IBD but it is benign & easily treated.
📋https://t.co/mdvDHMHZY4
#GiPath#Pathology
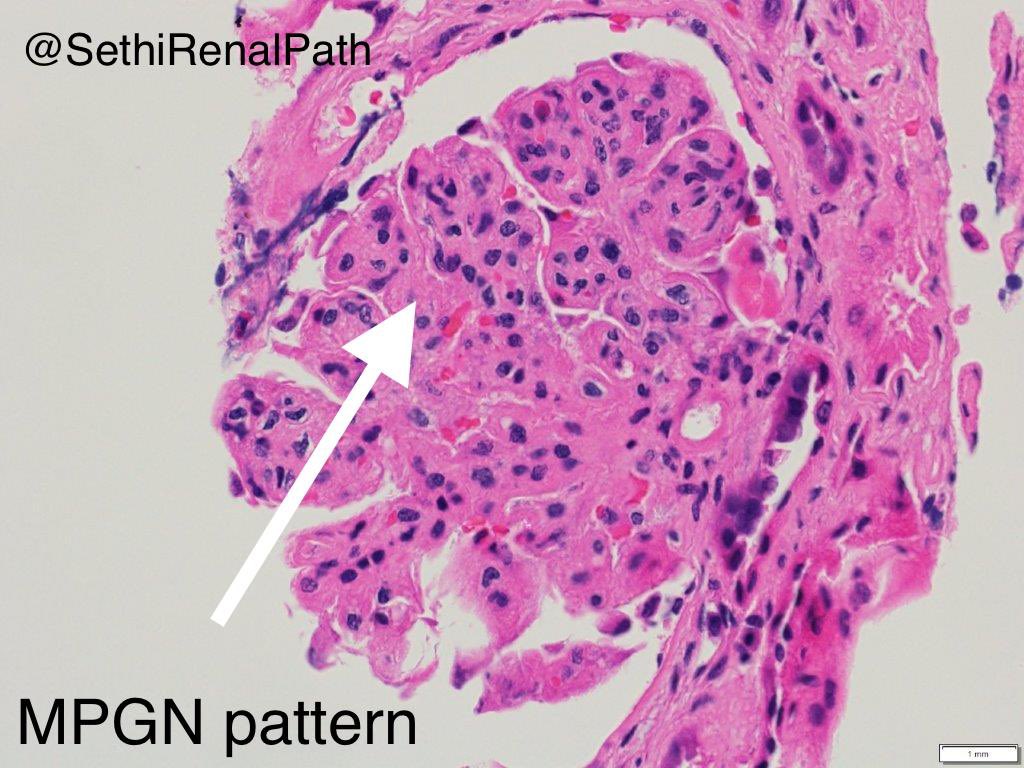
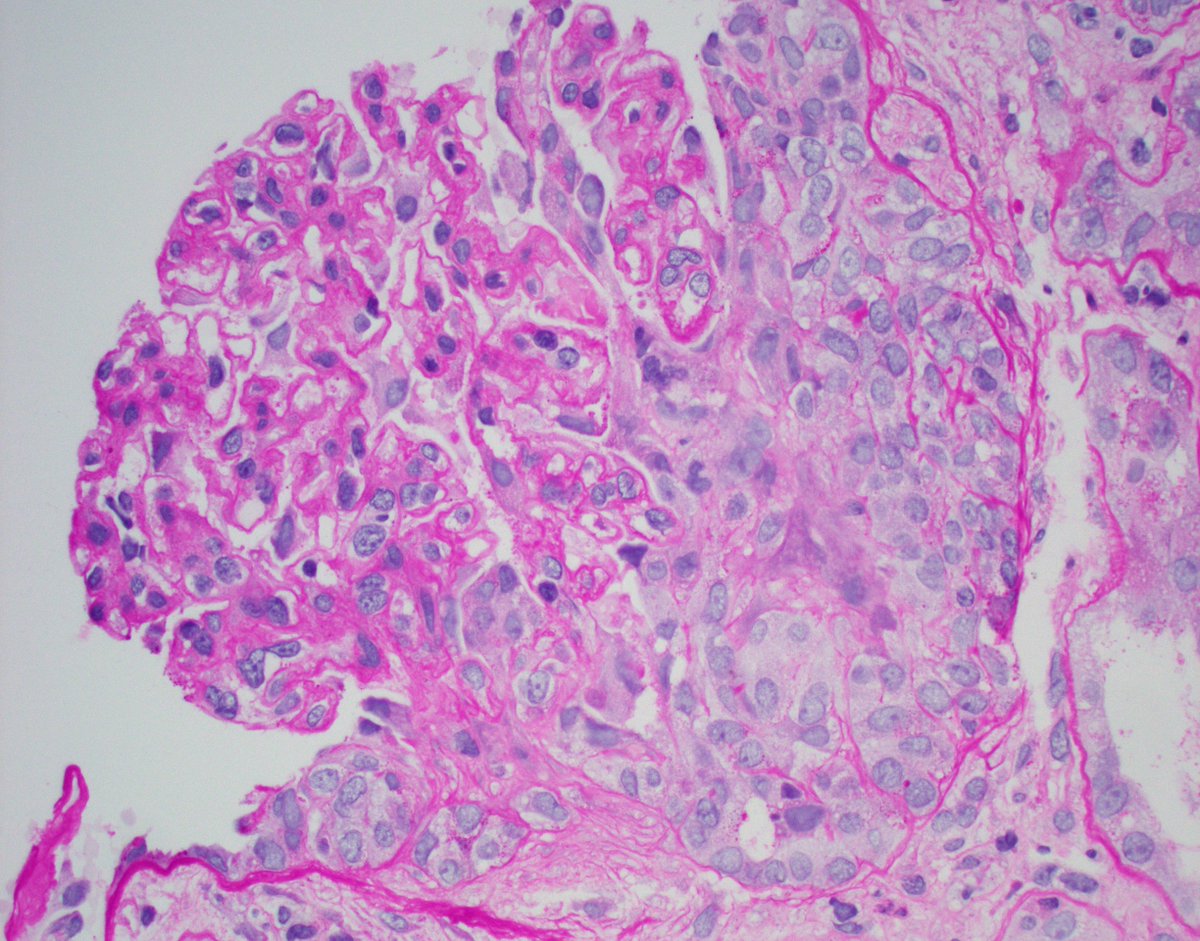
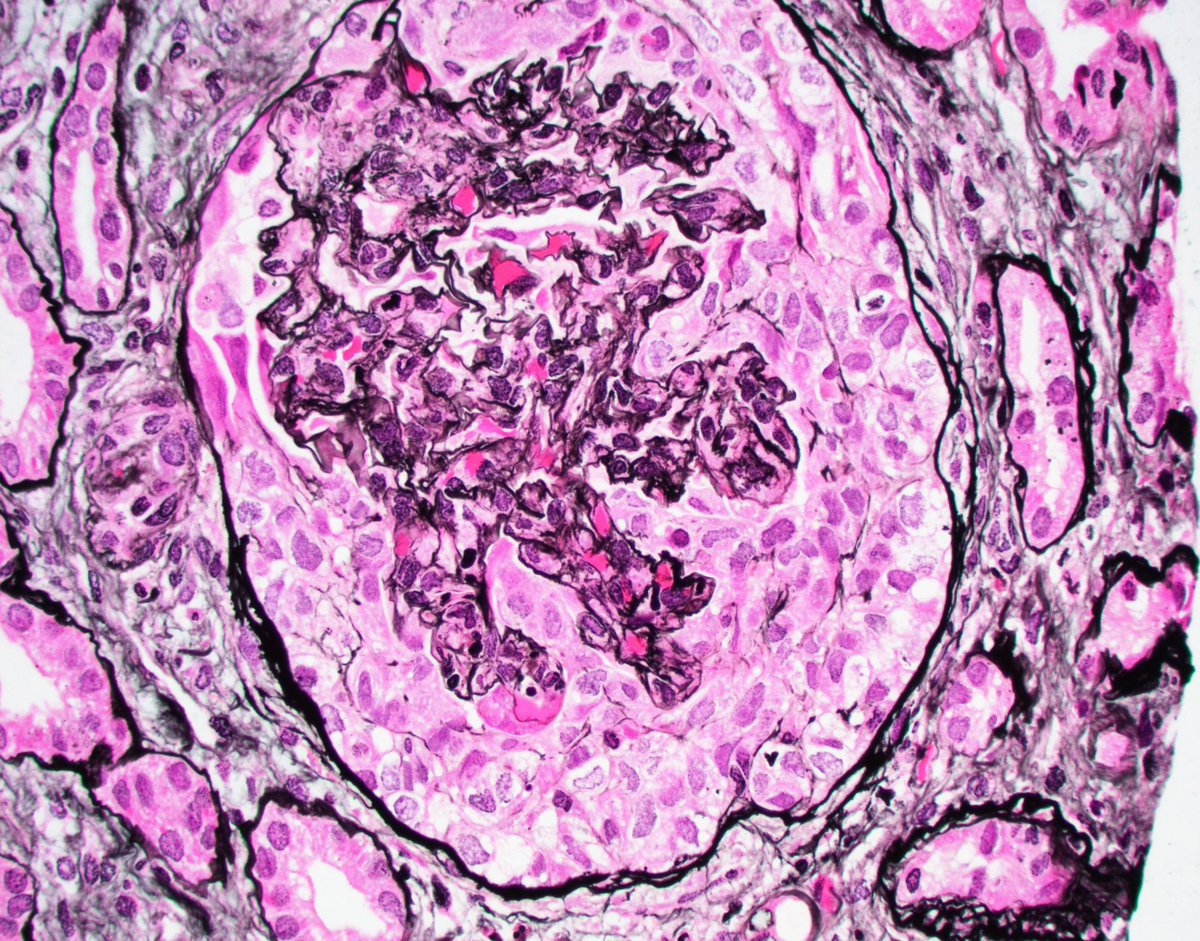
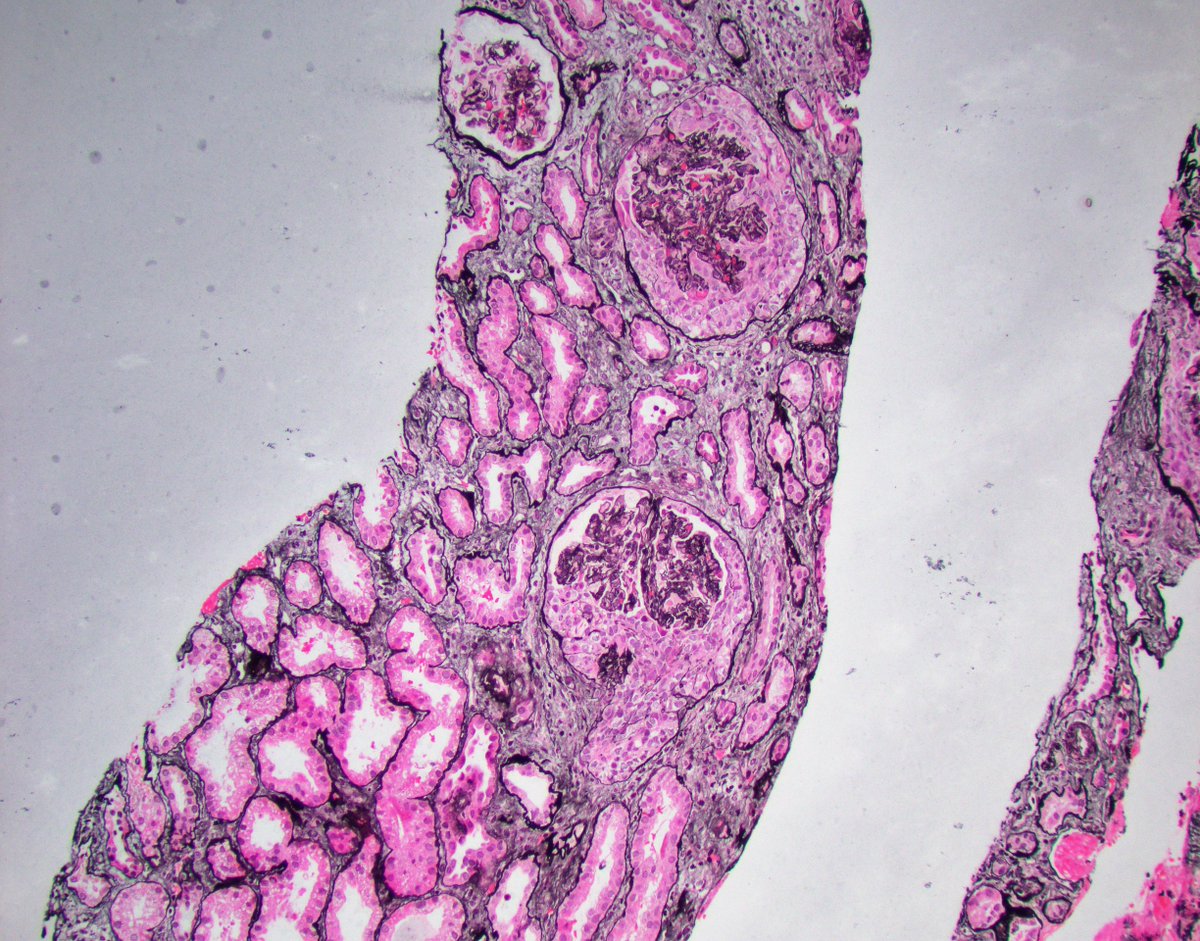
When you get a diagnosis of idiopathic MPGN-look again, the dx may be staring you in face.
60 yr man, dx of idiopathic crescentic MPGN for many yrs, treated with immunosuppression.
Rebx: IF=3+ IgA
Dx: IgA nephropathy, mesangial & endocapillary hypercellularity (MPGN pattern)
The kidney bx of a 40yr woman who presented with hypertensive crisis.
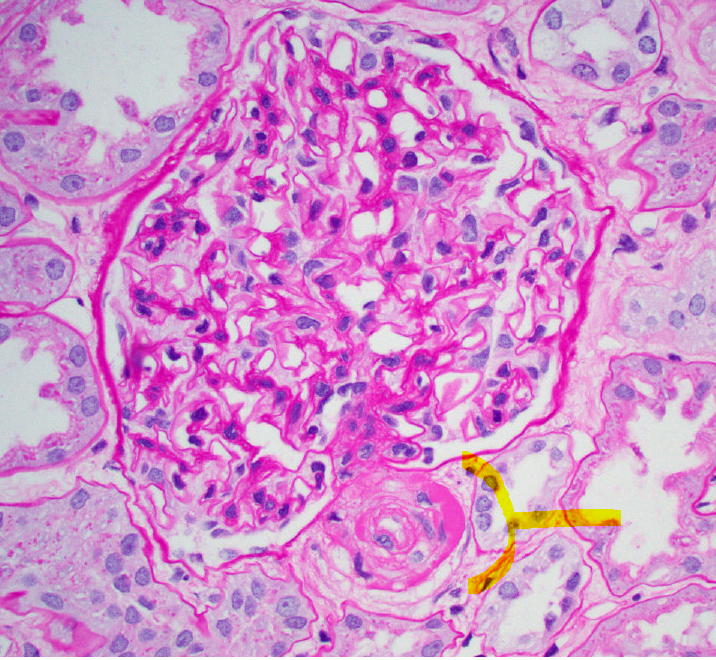
There is TMA of arterioles: "Onion-skin" suggests a chronic TMA. Glomeruli: Ischemic
The differential diagnosis is broad. I love this article from #MayoClinicProceedings with a nice algorithm.
@AshimaMakol
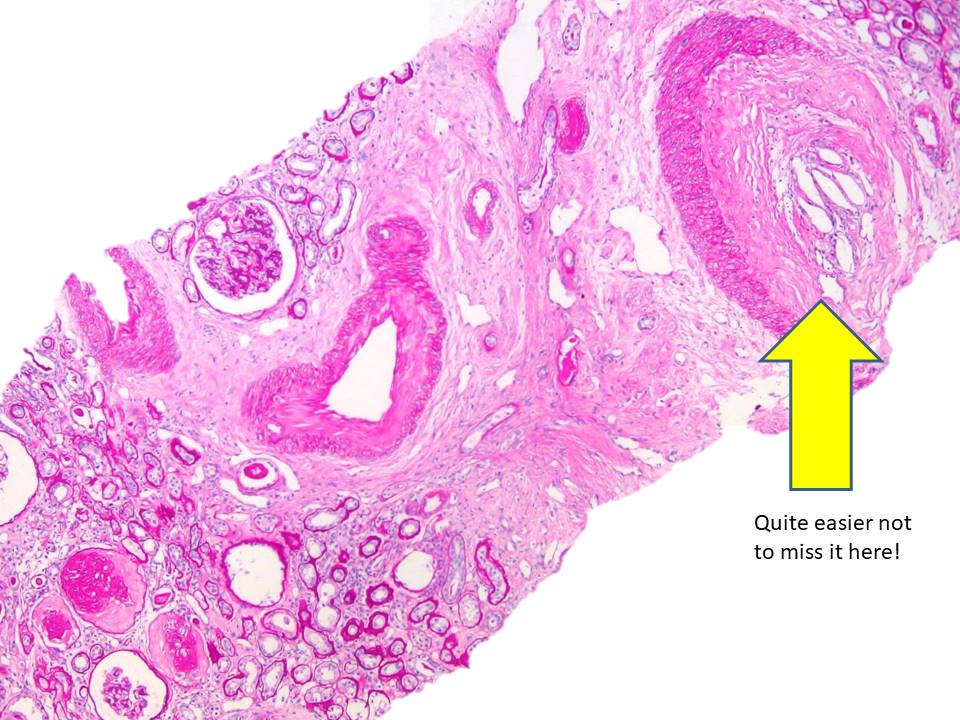
Time zero implantation biopsy with nodular medial hyalinosis of an arteriole. Typically considered a sign of chronic CNI tox. But as illustrated, not always specific. #renalpath#PathTwitter
Answer: Interstitial foam cells. I have not seen so many on IF. Sharing the images.
Bx showed membranous
Middle aged lady biopsied for increasing proteinuria. What’s that on the IF (arrows) ? Foam cells +++++
A patient with no significant PMHx is found to have acute kidney injury. The biopsy shows the light microscopy findings below. For those of you preparing for your path boards, what's your differential diagnosis? #renalpath#pathtwitter
Pronase IF to the rescue
LM: MPGN=mesangial & endocapillary hypercellularity, double contours, lobular tufts.
IF: All medulla.
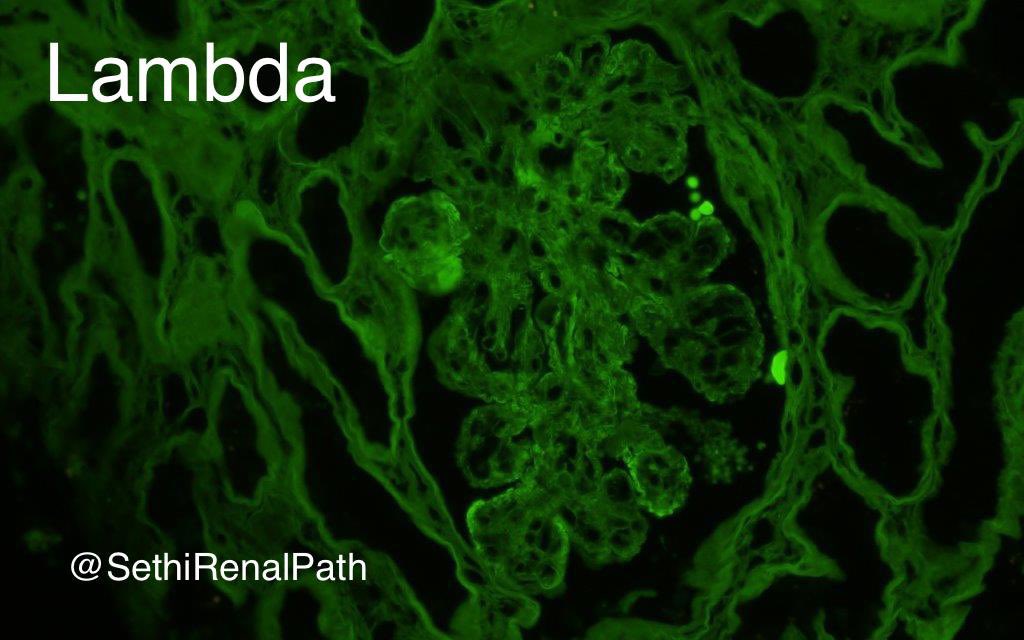
Did IF on paraffin: IgG+++ kappa+++ lambda neg
Dx: Proliferative GN with monoclonal Ig (PGNMID), IgG kappa.
68 yr-old, rise in Cr, UA=RBC & protein.
Comenzamos un nuevo camino, un proyecto único y sin precedentes en Canarias, pioneros en la digitalización en el archipiélago, la patología digital es una realidad. ANATOMÍA PATOLÓGICA RED CANARIA.
Rare case of bone fide crescentic IgA nephropathy (>60% cellular crescents). Occurs in ~5% of IgAN cases. Be sure to rule out ANCA in these cases as well. IF shows IgA staining. #renalpath#pathtwitter