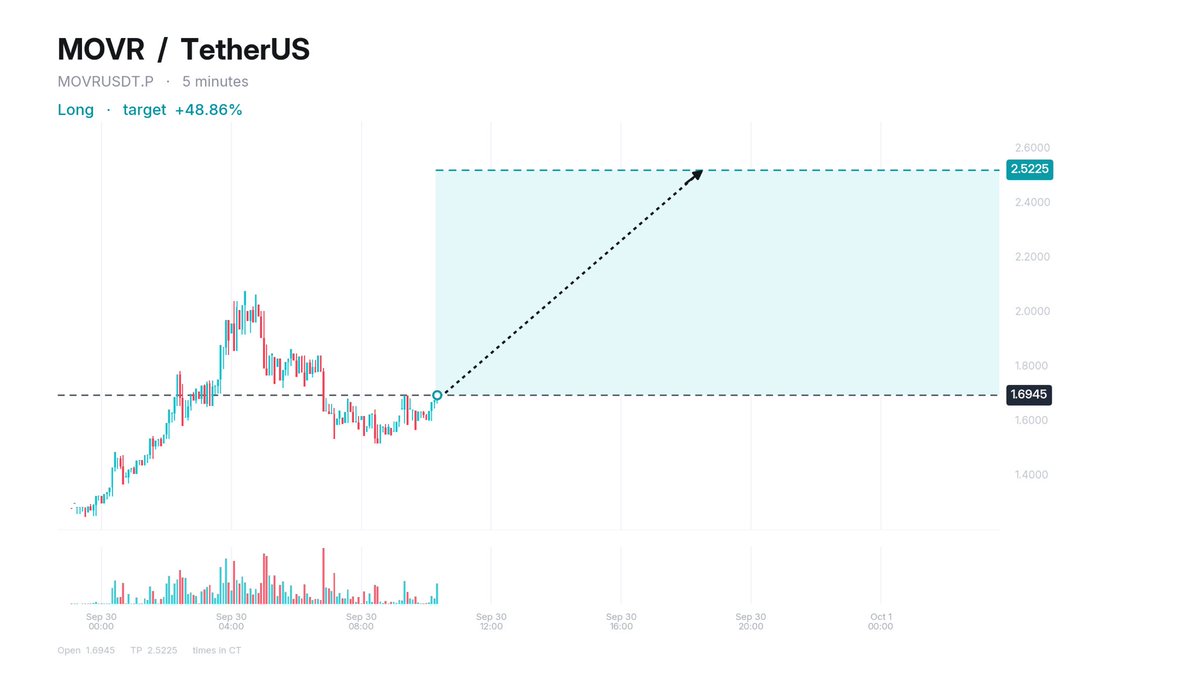
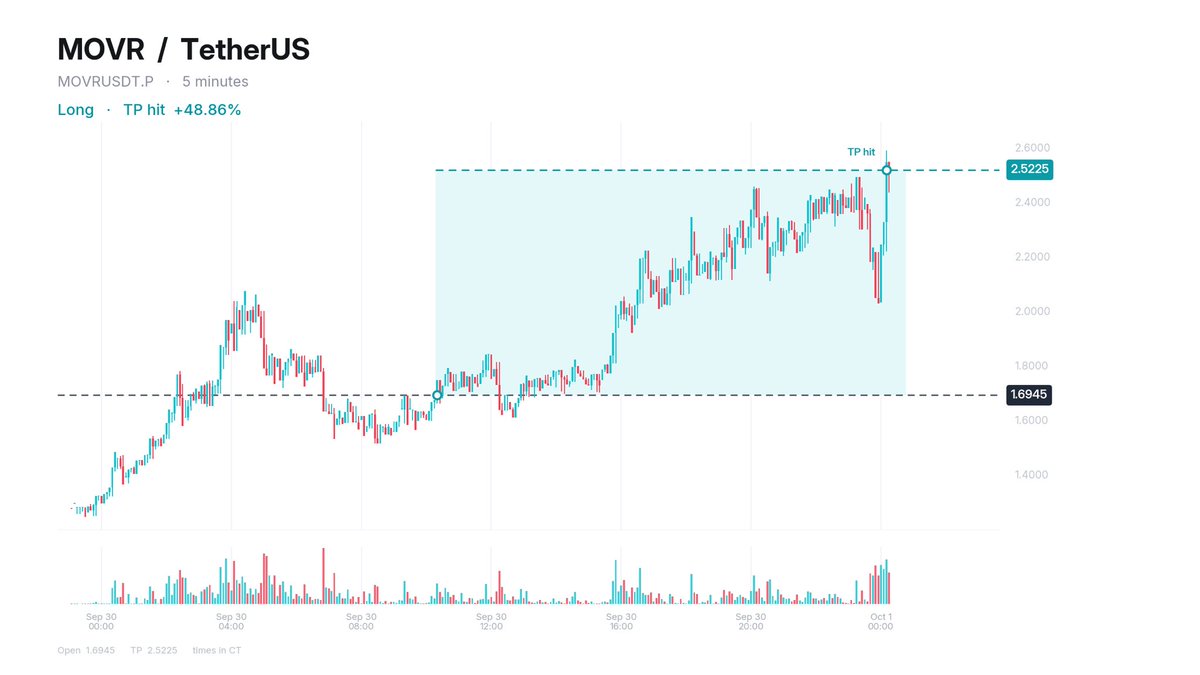
$MOVR played out exactly as expected, and gave 488.86% in profits at 10x leverage.
If you want the data and charts like these right away, join my private paid TG. Only a few spots left for joining free of charge.
I am still accepting a few select people free of charge that follow, like, and share my content. DM me if you want to be selected.
Appreciate the compliment brother!
It’s why I am building my following up to help others make gains. My private group gets all the data analysis and charts I post daily though. So, check that out it’s in the bio.
One of the most underrated crypto traders on X right now. He just started his account, and as you can see, his data and chart analysis are that of a very highly skilled trader.
One of the most underrated crypto traders on X right now. He just started his account, and as you can see, his data and chart analysis are that of a very highly skilled trader.
Boom, 488.86% in gains if you followed my entry. ✍🏽
Follow, like, comment, and RT if you want free access to my paid TG group where you get the data and chart right away. A few select people will get access free of charge. DM me for the opportunity.
@Hoostethics I really wish bronantnae didn’t fuck up my sleep bc it truly does live up to its hype. You tired Quviviq bs lemborexant? I liked quviviq more but that whole class needs to become generic. Best sleep med, as I don’t want to rely on a non benzodiazepines often.
why spend sm on supplements when there were plenty of free ways To get enough of most all of these in. Now depending on your labs there you’d maybe keep, unless you have money money. You do you ofc. Just hate seeing posts of people with sm money worth of supplements that at most move the needle barely. Versus if you truly had a a problem what a singular medication could do.
This is not true at all. any clinic that isn't cookie-cutter and has a provider who cares will tests every one of these. And I'd hope it costs less than your monthly stack. I know the cash-pay prices for all of these:
Cystatin C: $45
Direct bilirubin: $1.50
GGT: $1.50
ALP: I don't even have to price this one, because it's literally just alkaline phosphatase, which is already in a CMP-14. (So if your clinic isn't ordering CMPs at the minimum, probably get a new doctor. But my assumption is you didn't realize that and think you know more than you do.)
Sensitive E2: $20 (everyone’s knows regular e2 isn’t accurate, also you shouldn’t need an AI if your testosterone dose protocol is right, means your taking too much, or notnoonnning frequent enough, and getting labs at the wrong time)
SHBG: $8 (always tested at clinics, cause they all do hormones.)
Insulin: $3.50 (even a normal GP orders this lmao)
TSH + free T4: $5.25
Free T3: $2.75
And no doctor, not even the GP most people see once a year, would ever order just a TSH. It tells you nothing on its own. So idk where you got that from, but you really made this post thinking you did something here. Honestly, these are all common asf tests.
If you want to be really specific, a full thyroid panel would include TSH, free T4, free T3, TPO antibodies, thyroglobulin antibodies, reverse T3, and TSH receptor antibodies.
ApoB: $5.30, and you're wrong there. LDL-C doesn't measure the cholesterol inside all ApoB particles. It only measures LDL cholesterol. That's why ApoB is the better marker: it includes LDL, VLDL, and IDL, all the particles behind atherosclerotic plaque. But most regular docs don't order it, and non-HDL is just about as good, since it's doing the same thing by measuring everything except HDL.
It’s posts like these that make it seem like every provider out there doesn’t know what they’re doing or take the time and due diligence to order these test. And that’s simply wrong. Especially clinics are testing more labs than your normal primary care that include all these. Minus maybe cyststin C everytime, bc even though it’s the gold standard if you have really good creatinine and egfr output there is no reason to spend the extra on a cyststin C. Now if your kidneys show some distress then you’d get an adma/sdma and the gold standard cystatin C.
But as a “pharmaD” not a medical dr, but ofc that’s the first thing in your name username… you think you’d give more credit to your peers. Rather than make a post acting like these aren’t all very common ran test. Every single one of those is ran at a good clinic eveytime minus the cystatin C and full thyroid panel i mentioned not yours. Because those are on a as needed basis, based on symptoms prior labwork showing a lower creatinine/egfr.
@novvibee@grok boy went natty or to lower trt levels. You can tell by the top off his head he has used growth hormone white a bit. The rolls are a sign.
it’s because people don’t get seen or checked up on enough, ontop of with normal primary care your average visit is 6 minutes, and Colon Cancer is one of the fastest growing ones in terms of turning from stage one to four in a shorter period than other cancers.
So, everybody get your colonoscopies, use a colorist before if your lazy, but it is a in and out procedure. Gi lab was some of the most fun clinical rotations I had. And I don’t want hear I don’t have time. It takes one day (not even), but if you have to take one off. You get a 15 minute nap from some propofol, wake up funny, get drive home, and luckily it’s over and nothing was found. Once pulled a dental crown out of someone rear lol. That was cool.
@GrantHesser I don’t see it happening, that’s one area where human oversight will always be needed at the least. I do see in the next 5 years some ai coming into medicine in terms of not replacing doctors but equipment, data readings, the IT guy jk lol
Pregabalin is actually a very useful medication for many Dx’s. Especially the data’s for it anxiety, as it is actually approved and used for this reason in the UK, and off label in the US.
Here is the studies data using the Hamilton scale:
Pande 2003: 46% on 600 mg versus 27% on placebo. Lorazepam was 61%.
Feltner 2003: 61% on 300 mg, 47% on 450 mg, 53% on 600 mg.
Rickels 2005: 52% on the lower dose, 59% on the higher dose.
Montgomery 2006, the UK primary-care trial: 61% on 400 mg and 58% on 600 mg, versus 45% on placebo and 62% on venlafaxine.
It is a useful medication. Now his overall recreational use is so varied and out of control. It’s dangerous polypharmacy. But in medical terms for pt’s that have neuropathy and gabapentin isn’t cutting it and they are taking so many pills a day, the big brother Pregabalin comes in handy.
Absorbed better, faster onset, more effective, etc.
But I agree w/ your clav take
Isotretinoin is not a dopamine drug. The orbitofrontal finding is one PET study (Bremner 2005): glucose metabolism fell ~21% after 4 months. Depression scores did not change. Dopamine was not measured.
Hamilton depression scores did not differ between groups before or after. The authors note that mesocortical dopamine projects to the orbitofrontal cortex and that retinoids can change dopamine-receptor expression, then infer that isotretinoin might act through that pathway. They did not test it.
The paper in the screenshot (Tan, JAMA Derm 2024, 1.6M people) found no higher relative risk of psychiatric disorders, and fewer suicide attempts at 2–4 years. A rare idiosyncratic reaction is still possible. That mechanism is not established.
You need to lesrn to interpret studies I read this right away and knew you didn’t understand, the only study involving anything dopamine (D2 specifically) wise with accutane was a rat study, not human.