Health economist and systems scientist: health inequalities, place, prevention, and what AI changes for evidence and public services. @UofGlasgow and SDU.
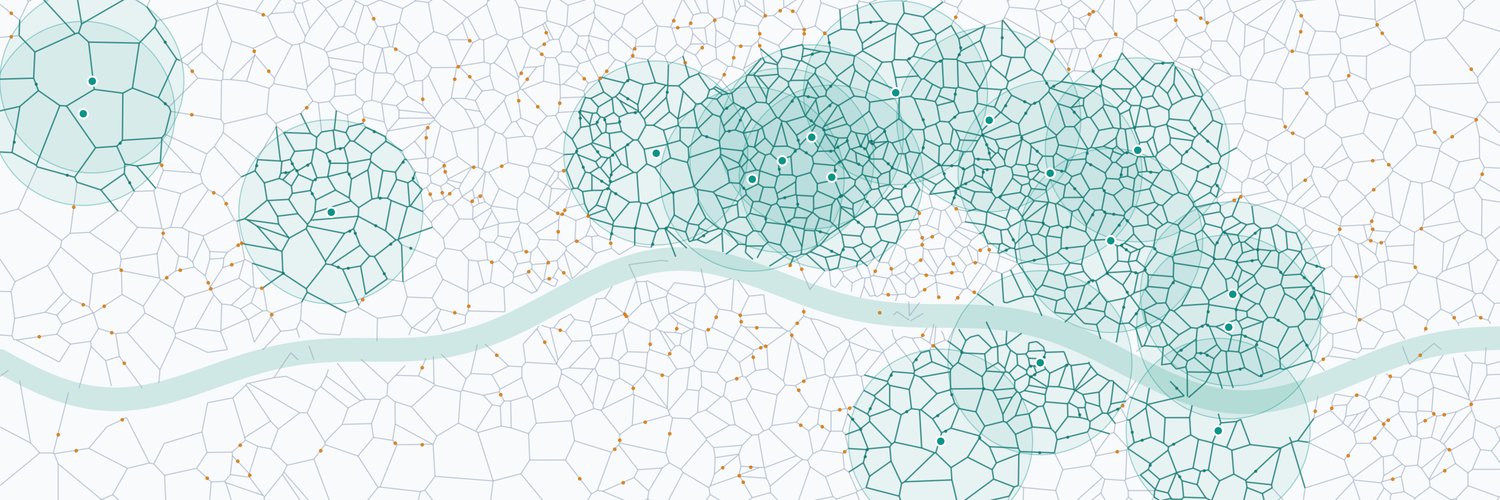
Some communities have everything they need on their doorstep. Others have almost nothing.
We built a dashboard to make that visible, linking service provision and health needs at neighbourhood level across Great Britain.
Explore your neighbourhood 👇
🔗 https://t.co/9wGOdq1RjW
Manchester United remind me of successive UK governments:
▪️Years of decline
▪️Repeatedly changing leaders only for the problems to get worse
▪️Asset stripping
▪️Selling home grown assets off to foreign investors
▪️Accumulating massive debt
▪️Failure to invest in infrastructures
#ATMMUN
YumYums is out on iPhone and iPad.
Save all your recipes in one place, cook step by step, and turn ingredients into a shopping list.
No account. No subscription. Optional sync through your own iCloud.
Try it out. I’d love to hear what you think.
https://t.co/aw88usQTUG
Enjoyed showing MPs our dashboard at Westminster today!
Explore what’s available in your neighbourhood (or anywhere else across Great Britain) and how that relates to health: https://t.co/BPnBXYzRiV
Funded by @NIHRresearch
Thanks to @MartinRhodes21 for hosting us! @UofGlasgow
Starting today, 10,000 scientists across every field, from math to chemistry to physics and more, can get Claude through our new Claude Team plan for scientists. Standard seats are free, and premium seats with 5x usage limits are $15 per month, an 80% discount, for one year.
Claude is becoming increasingly capable of scientific work, with recent progress on problems from advanced physics calculations to protein design. Alongside that progress, we've been investing in the research community: Claude Science launched in June, and our AI for Science program funds high-impact projects with free credits. Today's expansion builds on both.
Principal investigators (or equivalent) at academic and nonprofit research institutions can sign up, then add the researchers in their group. Over the coming months, we plan to extend the program well beyond the initial 10,000 seats.
Learn more: https://t.co/RTG1JxWi4Q
We're launching a program to get free or heavily discounted Claude usage to scientists, through Claude Teams for Science.
If you're a student or researcher in academia or a non profit org, ask your PI to apply. We're starting with 10,000 seats and will expand from there.
Take part in research about the economic impact of caring for people with cancer. If you provide unpaid care, are aged 16+ & live in Northern Ireland, Scotland or Wales we want to hear from you. For details & to register interest, go to: https://t.co/NxraISUZCA
@bmj_latest@MichaelMarmot@jessjallen Genuinely encouraging. But I lived in Manchester while the skyline filled with towers, and area-level gains can reflect who moves in as much as anyone getting healthier. Before we call it a model: whose life expectancy improved, and did they live there before?
Ending rough sleeping is a good ambition. But it cannot be delivered by homelessness services alone: housing, prisons, immigration policy and local government finance all determine who ends up on the street. Are we set up to act across those boundaries?
@CfSocialScience@PlymUni This looks timely. Regional and local policy are often where the social determinants of health become tangible, but the funding and accountability architecture still needs to catch up with that reality.
@SebRees1@CommonsHealth This is a fundamental prevention issue: areas carrying the greatest health and care need cannot rely on the weakest local tax base. Funding reform needs to reflect need as well as local revenue capacity.
A lot of methods debates are really status debates in disguise. The useful question is usually boring: what decision does this method improve, and for whom? If you can't answer that, the cleverness probably isn't doing much work.
Public health is far too polite about poverty. We keep translating political choices into softer words like 'determinants' and 'vulnerability', then act surprised when the solutions get softened too. Is the language helping us or hiding the argument?
Everyone's framing NHS records as "data sharing vs privacy". I think that misses the point.
The real question is who gets the value: patients and public services, or tech firms building products on public trust?
That feels like governance, not comms. What do you reckon?
'Health in all policies' is useless unless it also means accountability in all policies. Otherwise it's just asking the NHS to be nicer about absorbing the damage. Too blunt?
@PreventionPodc@BrineHealth@JimBethell Prevention keeps being framed as a priority, but budgets and accountability still reward downstream activity. I’d be keen to hear what would make upstream, place-based prevention genuinely investable over 5–10 year+ horizons.
The more I work on 20-minute neighbourhoods, the less I believe proximity is the point.
A GP, park or shop nearby only matters if people can actually use it, afford it, and feel it's for them. Equity is in the mechanism, not the map. What do you reckon?
@DHSCgovuk "20,000 fewer A&E visits" is the easy sell. The harder question: do single patient records help the people with the messiest, most fragmented care, or just (maybe) smooth the journey for those who could already navigate it?