📚 For access to the presentation materials, educational content, and references from today’s Joint Academic Activity, please visit the link below.
🔗 https://t.co/HlaPE6e0Ym
Thunderclap headache is a symptom, not a diagnosis. SAH is the first thing to exclude, and a normal neurological exam doesn’t rule it out.From Dr. Talal Alolowi @TAl_94 talk at today’s Activity.
#EmergencyMedicine#SBEM#MedEd#OnePulse
Normal CT within 6 hours of onset in an alert, neurologically intact patient, read by an expert, makes SAH very unlikely.
After 6 hours, CT alone isn’t enough. Choose LP or CTA together with the patient.
#EmergencyMedicine#SBEM#OnePulse
📚 For access to the presentation materials, educational content, and references from today’s Joint Academic Activity, please visit the link below.
🔗 https://t.co/HlaPE6e0Ym
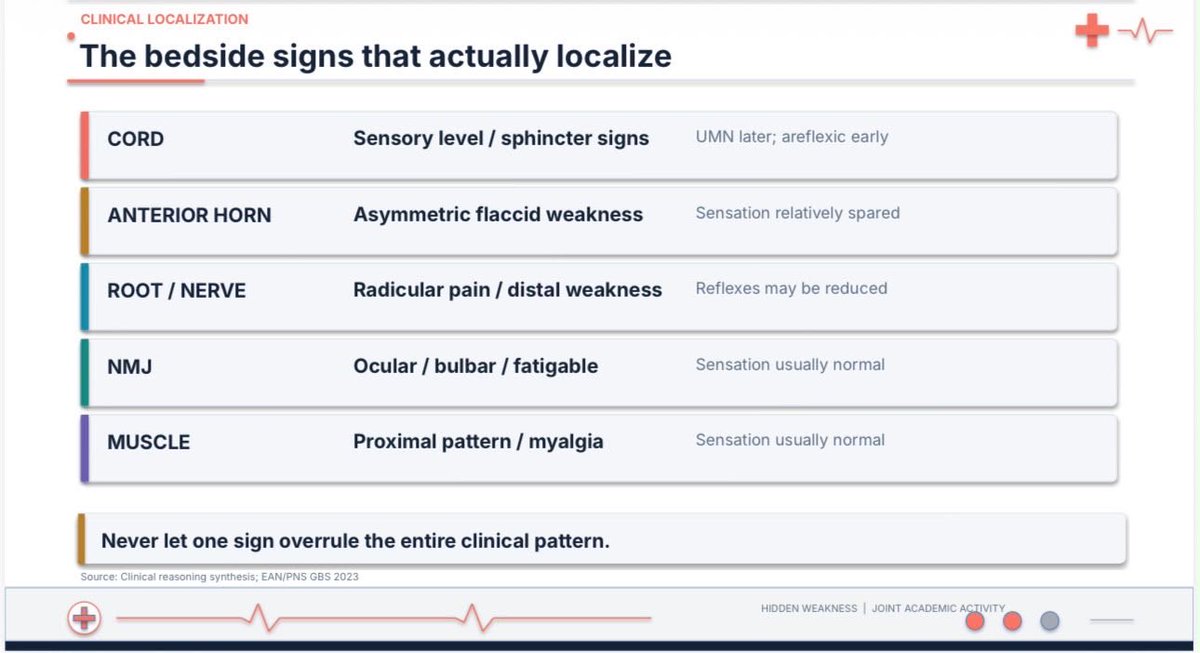
A normal SpO₂ does not guarantee ventilatory reserve. In neuromuscular weakness, check neck flexion, cough and serial FVC/NIF, not just the oximeter. Hussain Almazyadi @Alwh7sh at today’s Activity #EmergencyMedicine#SBEM#OnePulse
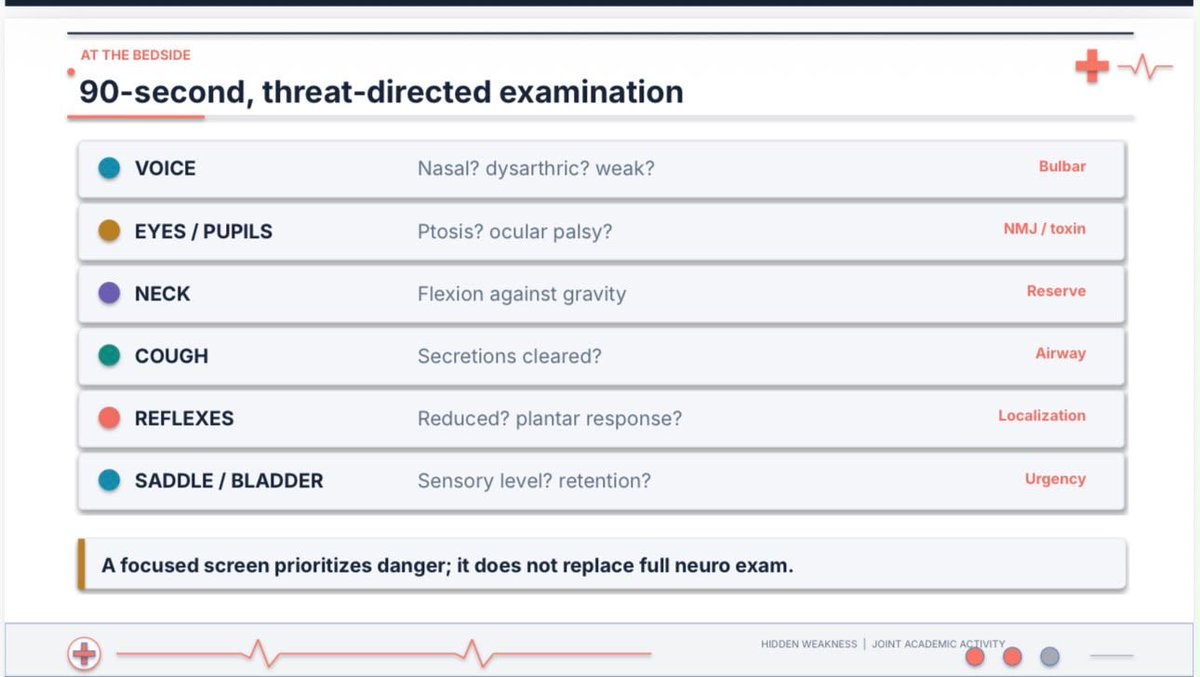
A 90-second threat-directed exam: voice, eyes and pupils, neck, cough, reflexes, saddle and bladder. It prioritises danger and doesn’t replace the full neuro exam. Presented at today’s Activity. #EmergencyMedicine#FOAMed#SBEM#OnePulse
📚 For access to the presentation materials, and references from today’s Joint Academic Activity, please visit the link below.
🔗 https://t.co/HlaPE6e0Ym
Altered patient in the ED? Before CT, check the 5th vital sign: glucose. It’s quick, it’s fixable, and it’s the one cause you can reverse in minutes. Dr. Abdulrahman Alagga @bo_da7m1996 at today’s Activity. #SBEM#MedEd#OnePulse
“Find the killer first. The CT can wait one minute.” Low RR + pinpoint pupils + low GCS think naloxone. Febrile and altered with no source think LP after imaging. #EmergencyMedicine#SBEM #FOAMed#OnePulse
📚 For access to the presentation materials, and references from today’s Joint Academic Activity, please visit the link below.
🔗 https://t.co/HlaPE6dt8O
“Find the killer first. The CT can wait one minute.” Low RR + pinpoint pupils + low GCS think naloxone. Febrile and altered with no source think LP after imaging. #EmergencyMedicine#SBEM #FOAMed#OnePulse
📚 For access to the presentation materials, educational content, and references from today’s Joint Academic Activity, please visit the link below.
🔗 https://t.co/HlaPE6e0Ym
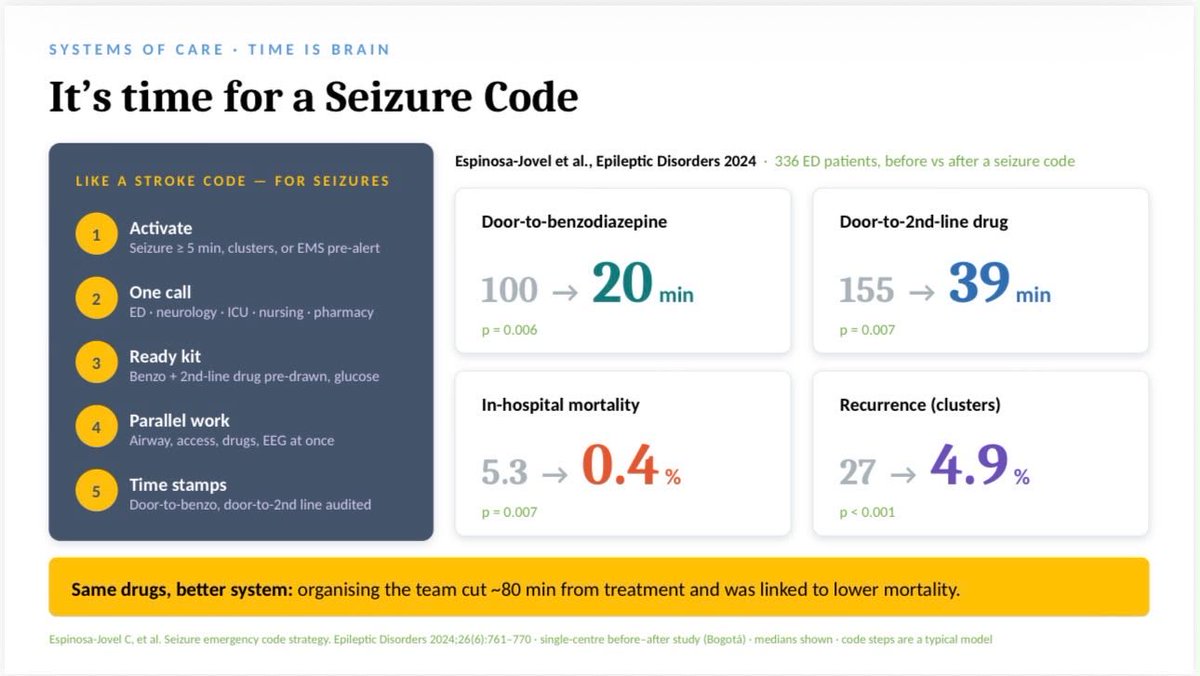
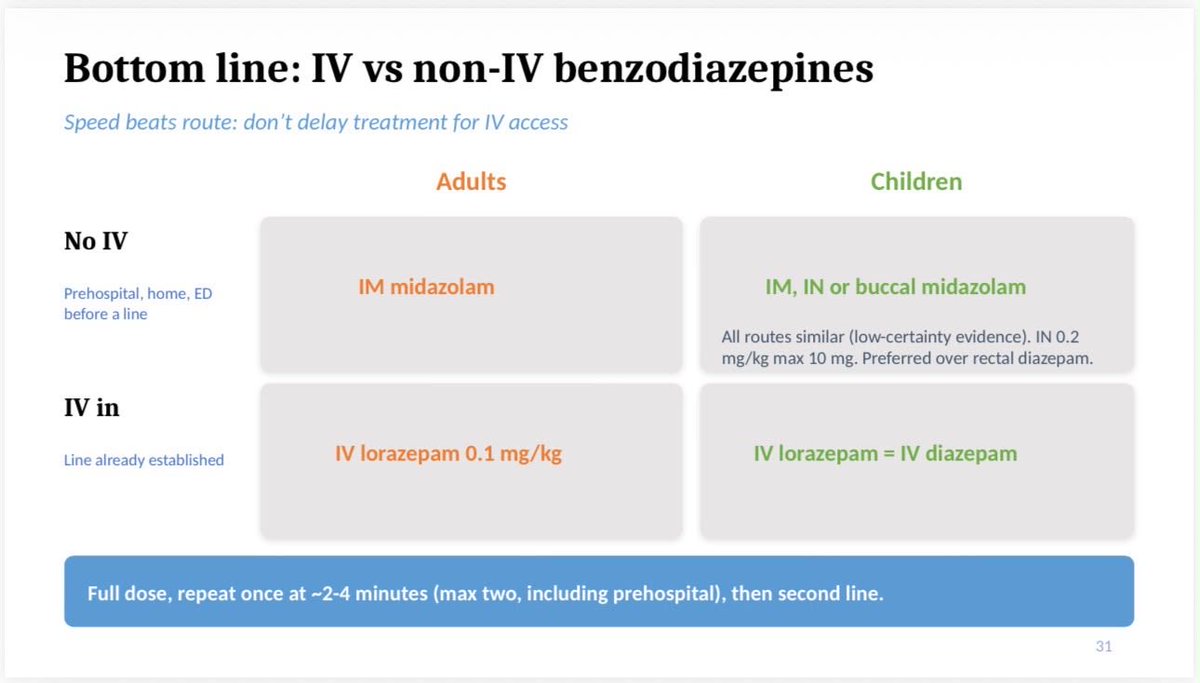
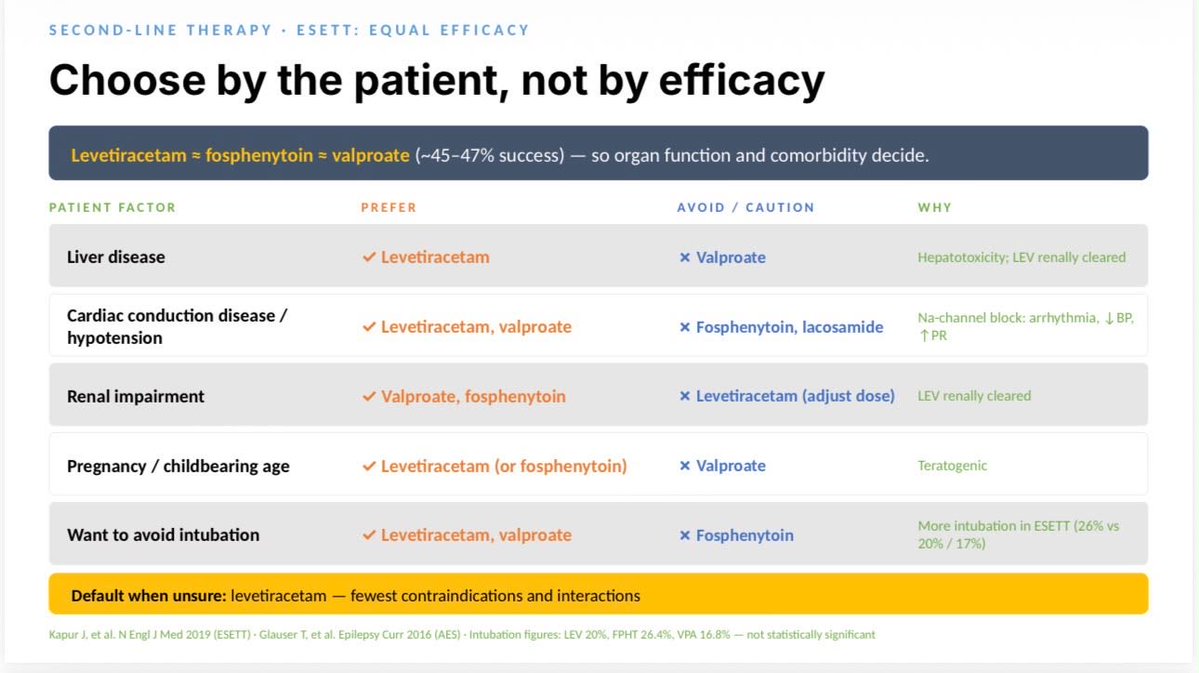
Time to the first benzodiazepine matters more than which drug or which route. Don’t wait for an IV line: IM midazolam is a reasonable first step. Dr. Mohammed AlQahtani @Dr_M0hammed at today’s 3rd Sector Joint Academic Activity. #OnePulse#EmergencyMedicine #SBEM
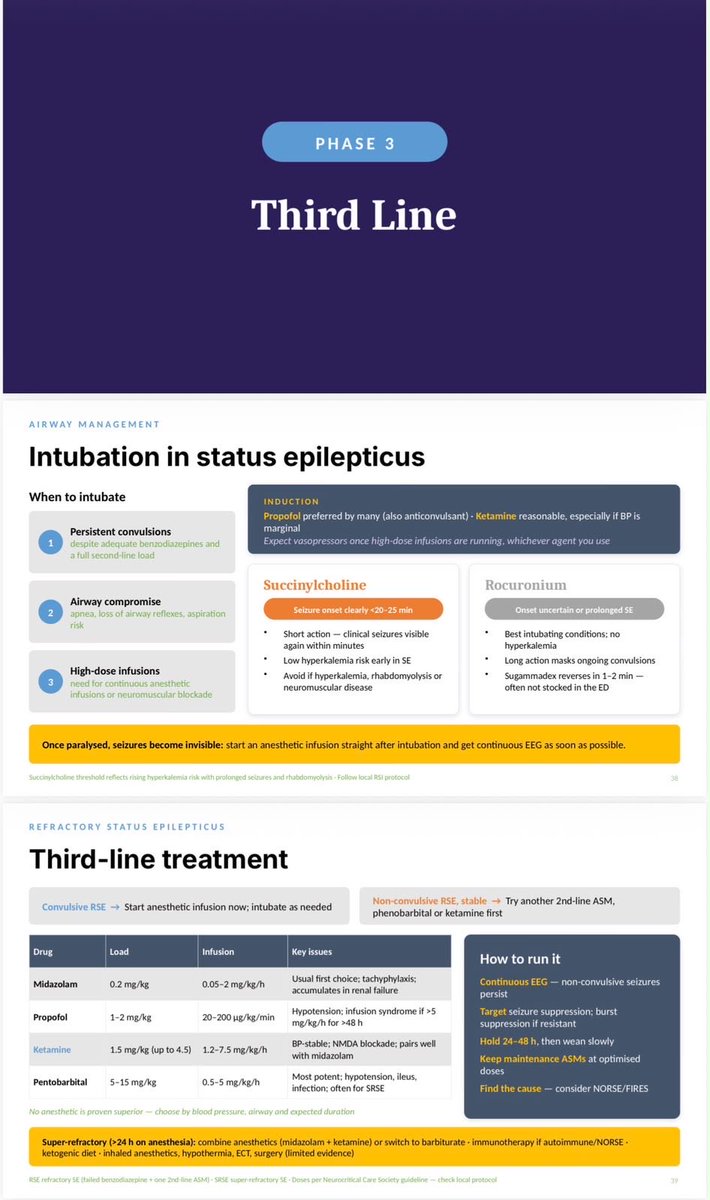
Treat a seizure as status once it passes 5 minutes. Resuscitate and stop the seizure at the same time, and check a fingerstick glucose in every seizing patient. #OnePulse #MedEd#FOAMed #SBEM
“Disabling” is defined by the patient, not the score. Would the deficit stop bathing, walking, toileting, hygiene, eating, or return to work? A teacher with aphasia and a low NIHSS can still be clearly disabled. Presented by Dr. Jawad Alzara @jawadzara at today’s Activity #SBEM
Normal CT within 6 hours of onset in an alert, neurologically intact patient, read by an expert, makes SAH very unlikely.
After 6 hours, CT alone isn’t enough. Choose LP or CTA together with the patient.
#EmergencyMedicine#FOAMed#SBEM
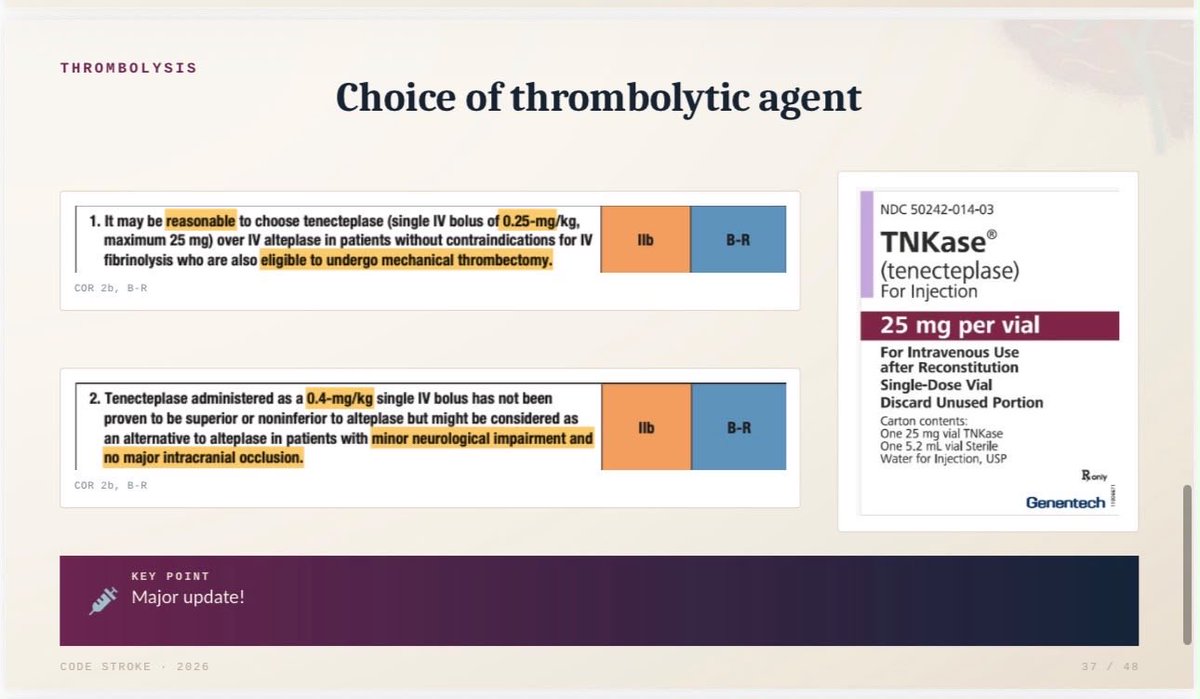
“Time is brain,” but the treatment window is evolving. Selected stroke patients may benefit from IV thrombolysis up to 9 hours and thrombectomy up to 24 hours. Patient selection is a key. Presented by Dr. Majed Aljohani at today’s Joint Academic Activity.
#SBEM#MedEd#OnePulse
Thrombectomy eligibility is expanding. A large ischemic core is no longer an automatic exclusion, and selected patients with basilar artery occlusion may benefit from EVT within 24 hours. The focus is on identifying who can still benefit from reperfusion.
#SBEM#MedEd#OnePulse