@MosheSaada1 כל מי שמוכן לשרת במערכת הבריאות הציבורית מבצע שירות לאומי מדי יום לאורך הקריירה.
אפשר בהחלט לנהל שיח על הצורך של מגזרי החברה לבצע שירות לאומי ועל הצורך ליישם העדפה מתקנת לטובת חיילי מילואים, אבל בבקשה אל תפגעו בעמיתים הערבים שלנו במערכת הבריאות על מזבח המאבק הפוליטי
@MosheSaada1 מר סעדה הנכבד,
הבחירה למקד את המאבק במגזר הרפואי כואבת לי מאוד.
מערכת הבריאות מלאה ברופאים אחיות וכח עזר מהמגזר הערבי (נשים וגברים כאחד) שמטפלים במסירות בציבור הישראלי כולו.
זה אולי המקום היחידי במדינה שמתקיימת בו שותפות אמיתית ושווה בין יהודים וערבים לטובת העתיד של כולנו.
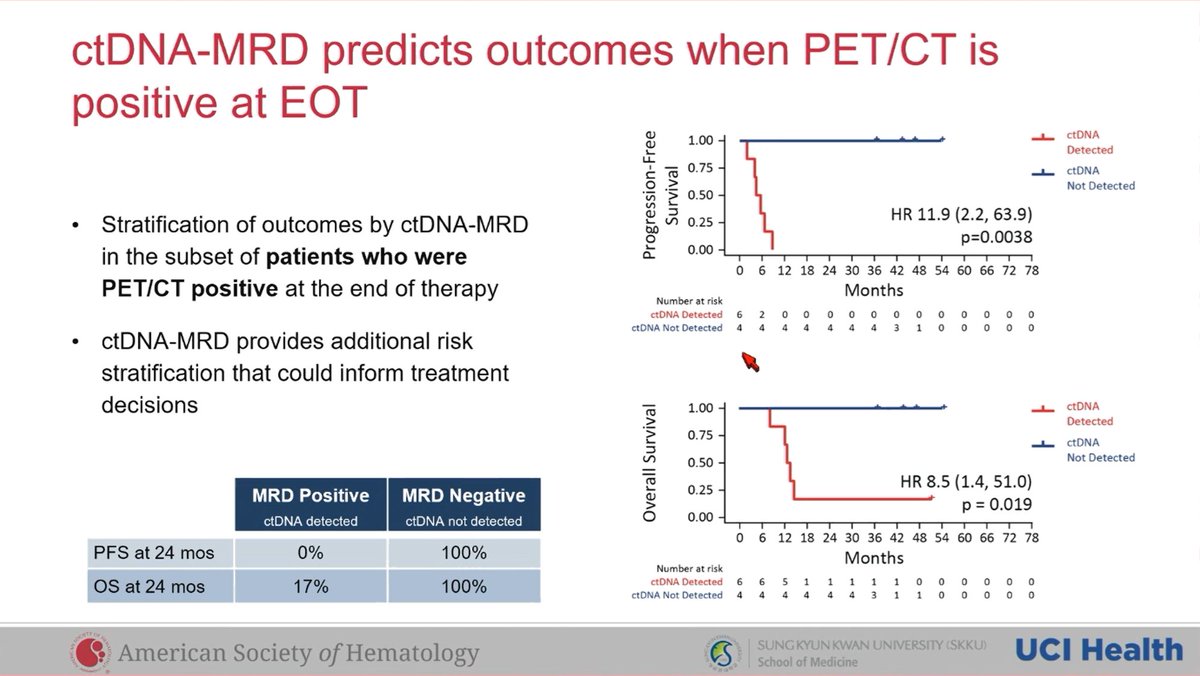
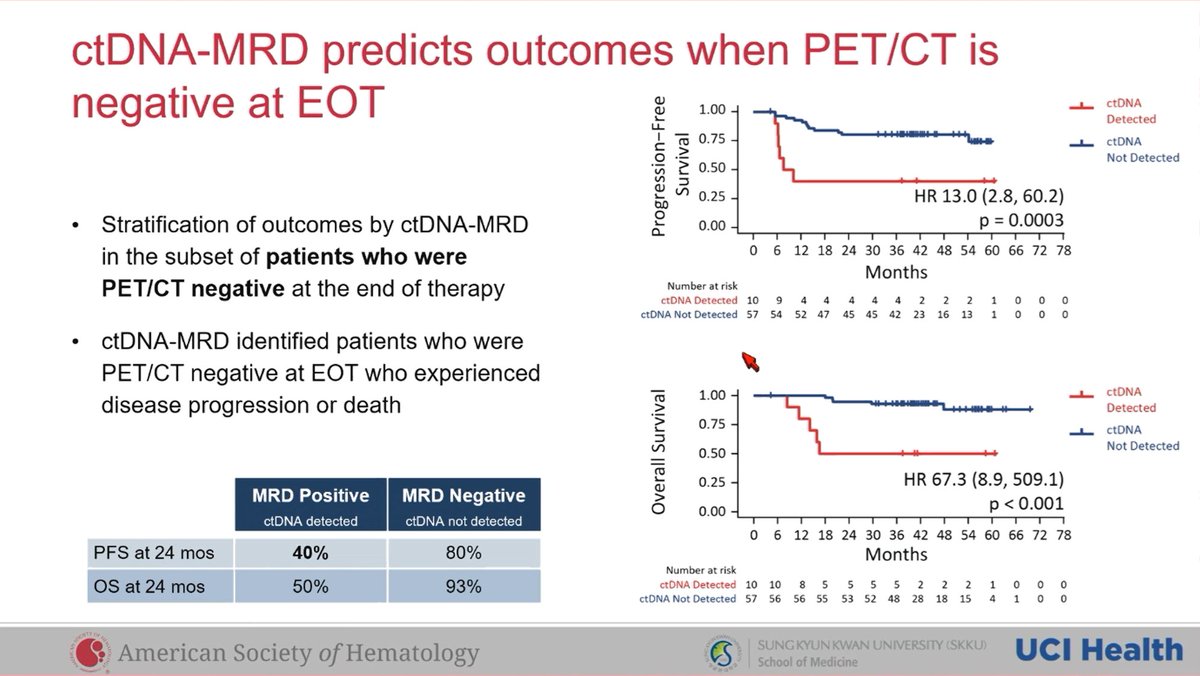
69: ctDNA MRD detection in DLBCL outperforms PETCT in both PET+ and PET- cases
(N=77; by PhasED-Seq)
* This was without a coupled tumor sample
** Physicians were blinded to the MRD results
https://t.co/unvDB8eIJA
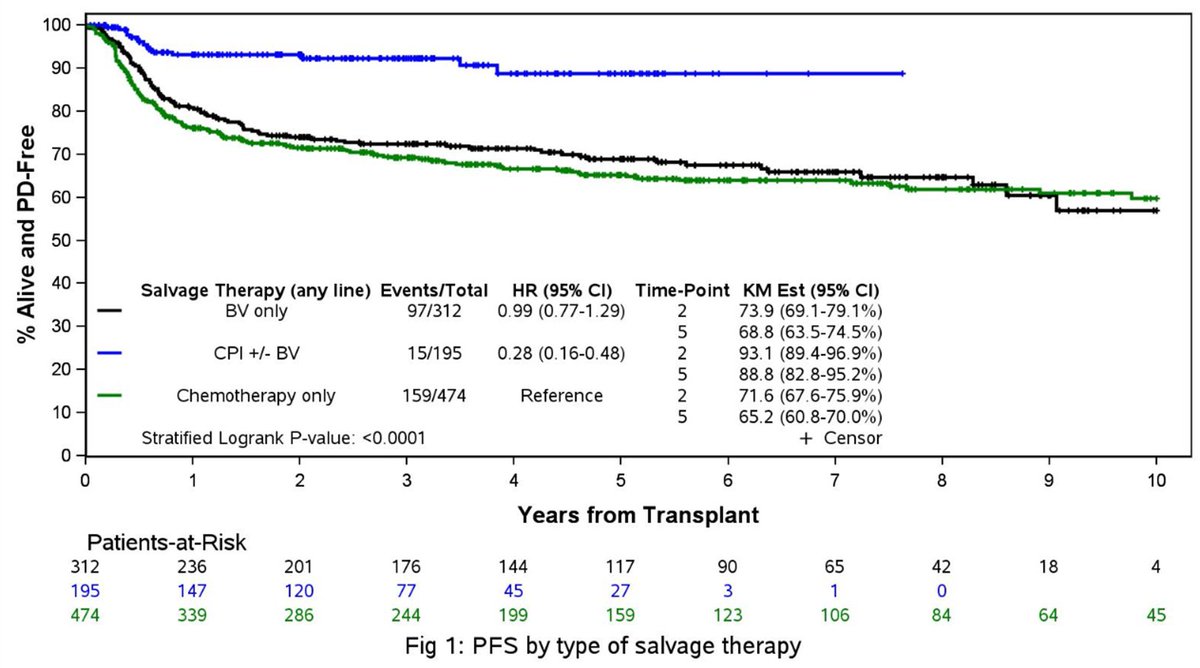
182: PD-1 Blockade before ASCT - updated report demonstrating superior outcomes
(N=195/981 on PD1i prior to ASCT)
SAT 14:15
CPI have to be administered as the line prior to ASCT !
I have transitioned to treating all my relapsed Hodgkin's pts. with nivolumab/pembrolizumab prior to ASCT since the initial report of Merryman et. al. came out in Blood Adv (2021).
Still grappling with how many cycles are enough. I have been primarily using pembro-GVD which is limited to 2 cycles but I am sometimes wary it might be too little.
https://t.co/TrjcowkFX3
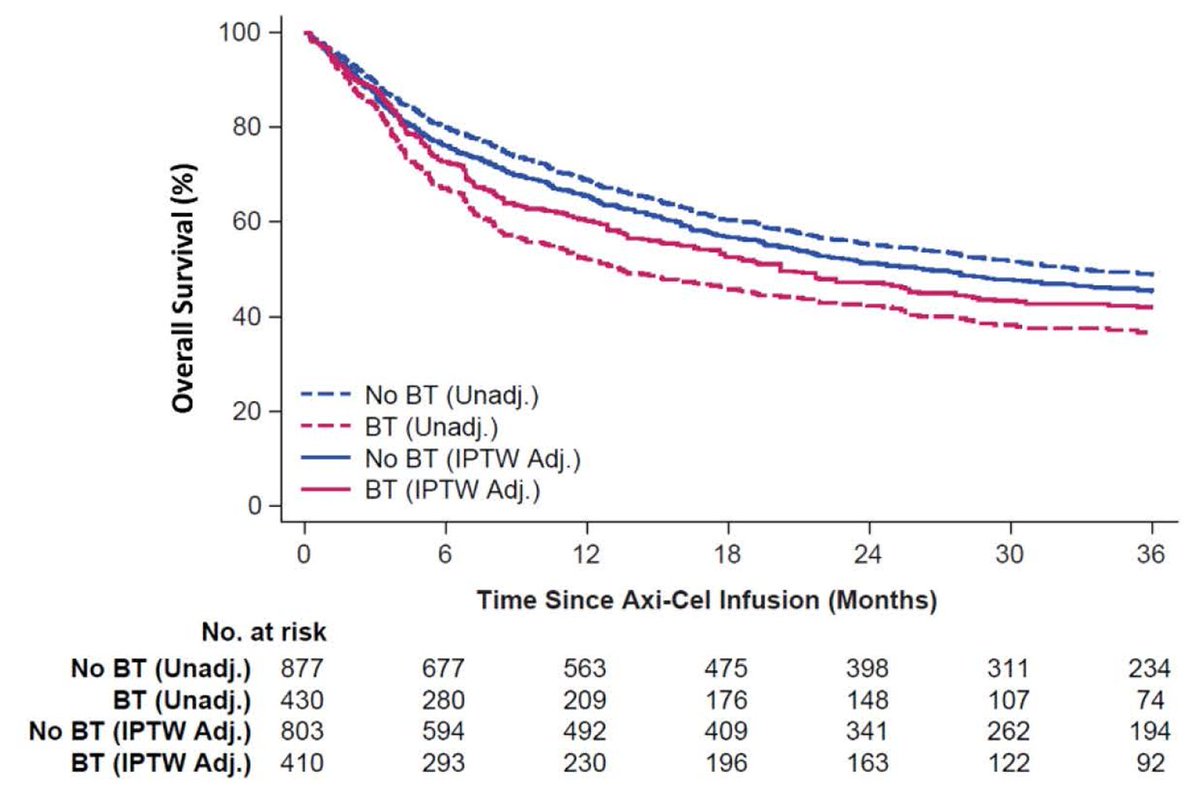
103: Bridging pre-CART (axicel) has NO impact on outcomes in DLBCL
(N=1500; propensity matched IPTW)
SAT 9:30
Patients without bridging fare the same as those with bridging (who represent ~ 1/3 of pts. in real-life and are possibly sicker)
https://t.co/mfw6XVkgoy
@chanyooncheah@tobyeyre82@michaelwangmd Seems to benefit only 10-15% of pts.
Unfortunately not those in most dire need (30% progress during 1y irrespective of arm; 30% long remission on either arm).
Likely another case of an additive effect rather than synergism.
https://t.co/T6kAn0b156
New paper:
Most approved drug combinations for advanced cancer (1995-2020) have predictable clinical efficacy, because they have additive effect on Progression-Free Survival times.
In @NatureCancer at https://t.co/Z7xabVpouT
by @HaeunHwangbo@SC_Patterson@PlanaDeborah
1/6
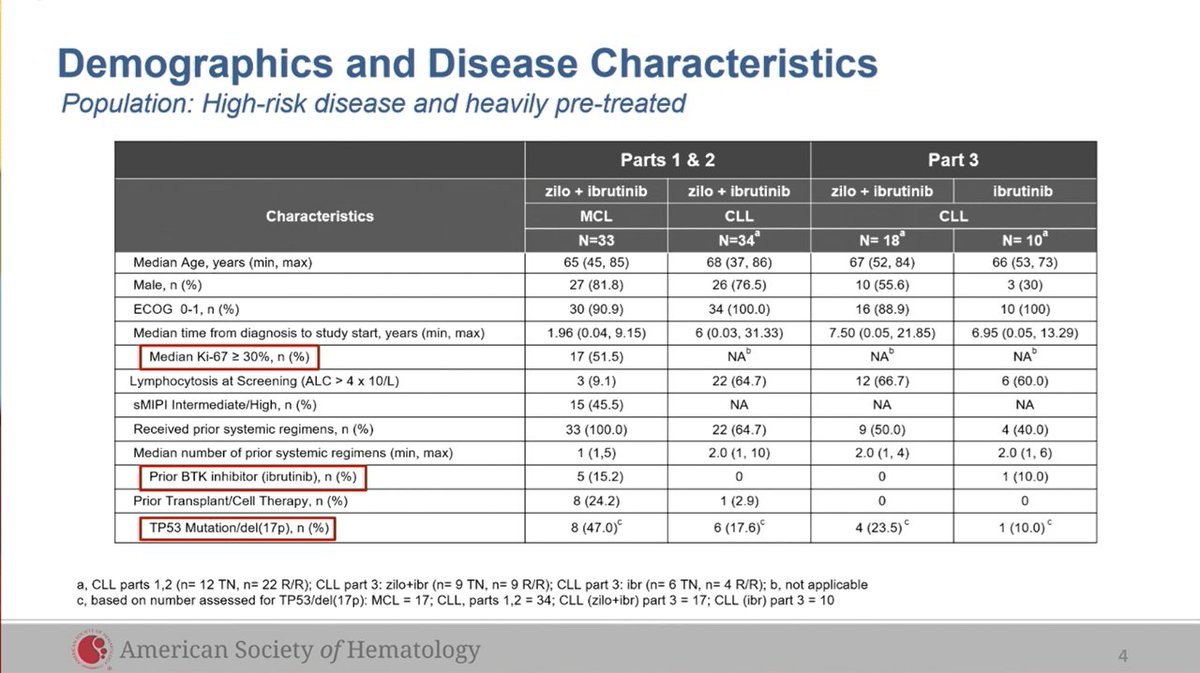
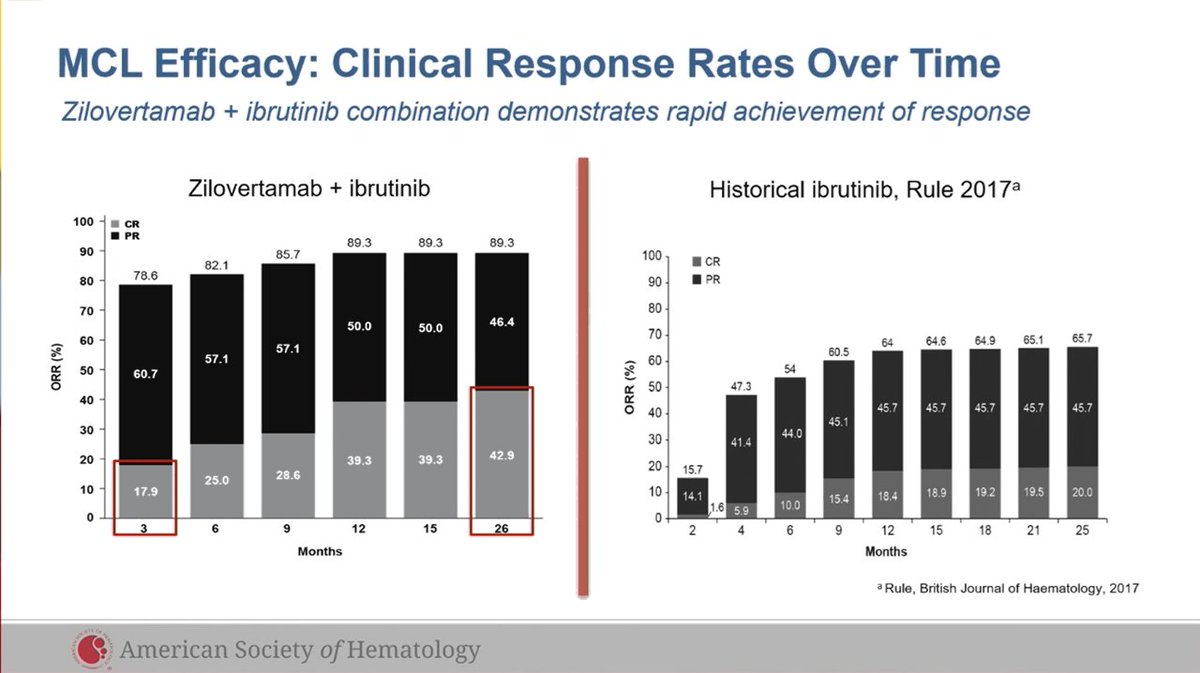
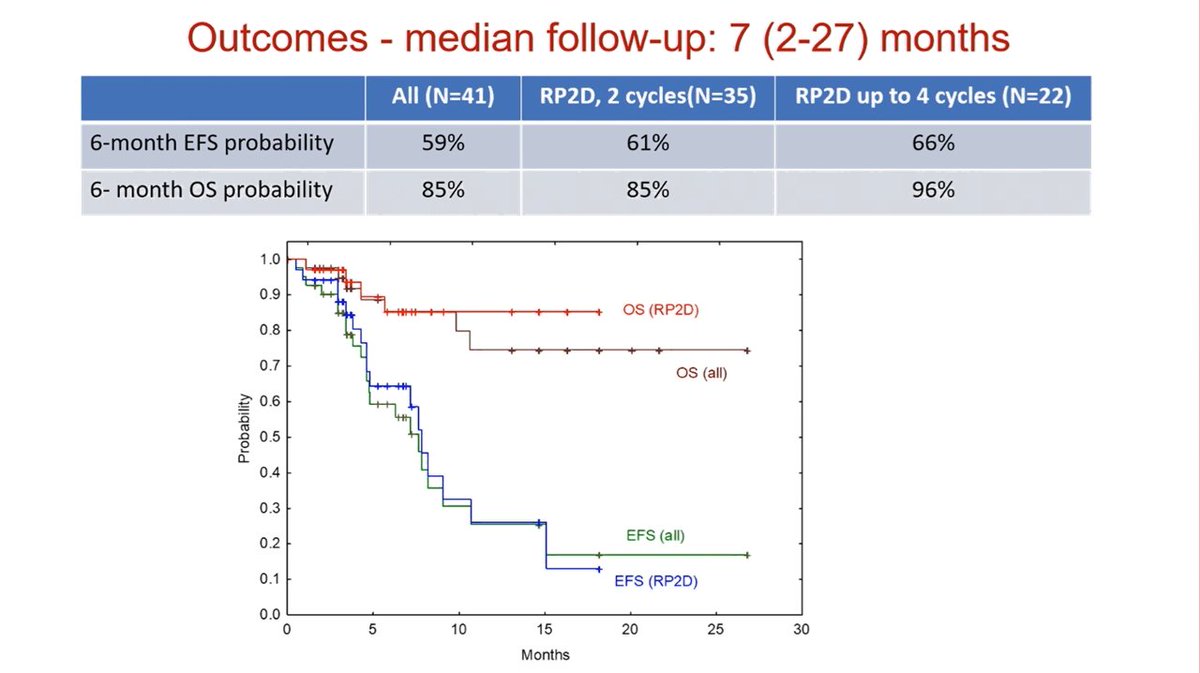
Zilovertamab ('naked' ROR1 ab.) + Ibrutinib in RR-MCL (N=33, most w/o prior BTKi)
2yPFS ~70% (ORR 6m ~ 80%; CRR ~ 25%)
DOR ~3y (> hx data)
Too bad phase-3 study compares to ibrutinib+placebo (may be difficult to enroll where other BTKi available)
https://t.co/Wv5zzbmSV5
@graham74GC@gloria_iacoboni Isn't there a selection bias in comparing 'cross-over' (N=46) to the entire upfront CART ?
The SOC arm had + 36 pts w/ CR (SOC + crossover CR = 54 vs. upfront CART CR = 61).
Zilovertamab (ROR1 antibody - the naked agent by Oncoternal not the ADC by Merck) showed promising efficacy in RR MCL and RR CLL (ASCO abstract)
RR MCL: ORR 85% CR 40% 1.5yPFS ~70%
RR CLL: ORR 90% CR 10% 2yPFS ~90%
Seemingly better than historical data of ibrutinib alone
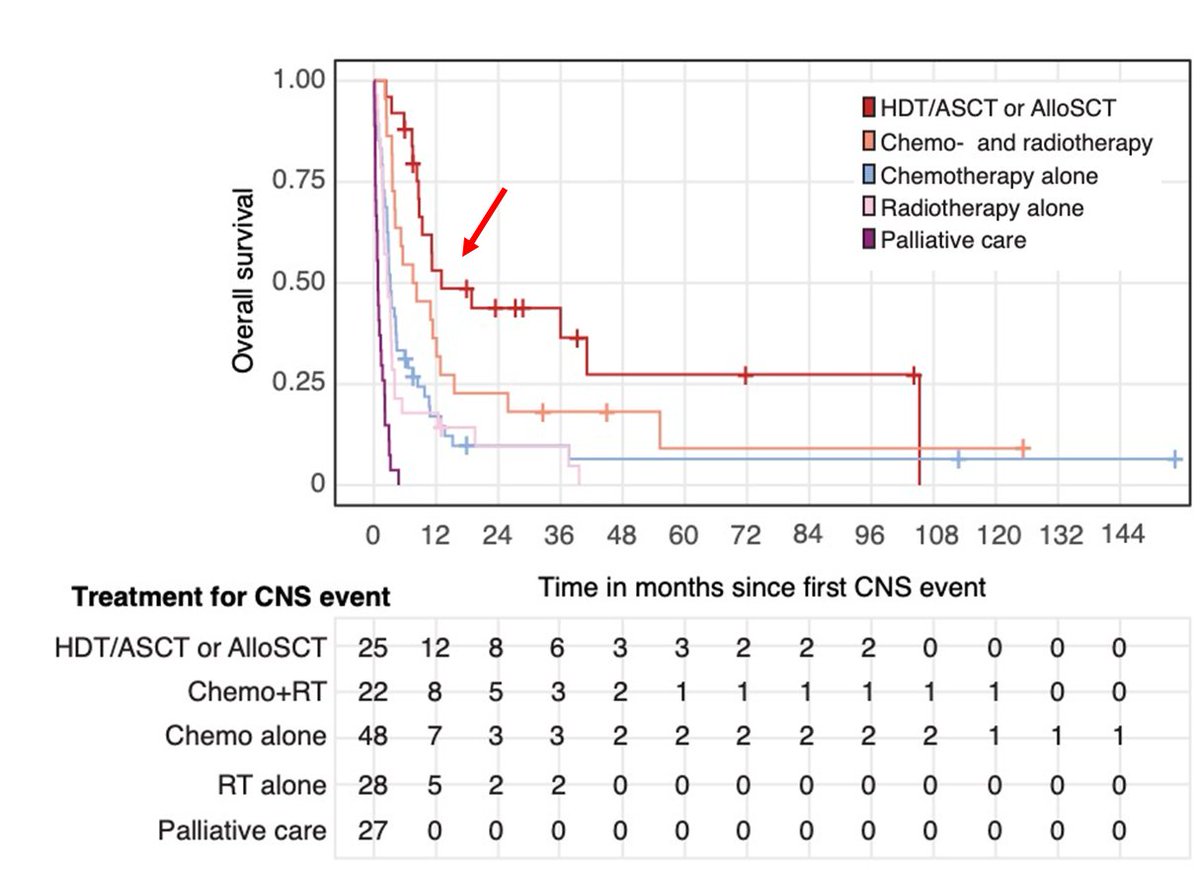
@patrickreville@graham74GC@DrAEvens@dgermain21 @AaronGoodman33 @chanyooncheah@Mohty_EBMT Could this be a BCL with features intermediate between DLBCL and HD ("grey zone") ?
Once upon a time we used to cure HD with radiotherapy. It has excellent CNS penetration :)
BTK inhibition w/wo CPI may also have a role as all these histologies are addicted to NFKB
Do update
Low efficacy of COVID-19 vaccine in CLL patients.
~ 50% develop antibodies (even treatment naïve); recent anti-CD20, ibrutinib or venetoclax < 20% immune conversion.
Patients should be careful. I have been sending all to semiquant anti-Spike tests
https://t.co/OzZQtPkYVr