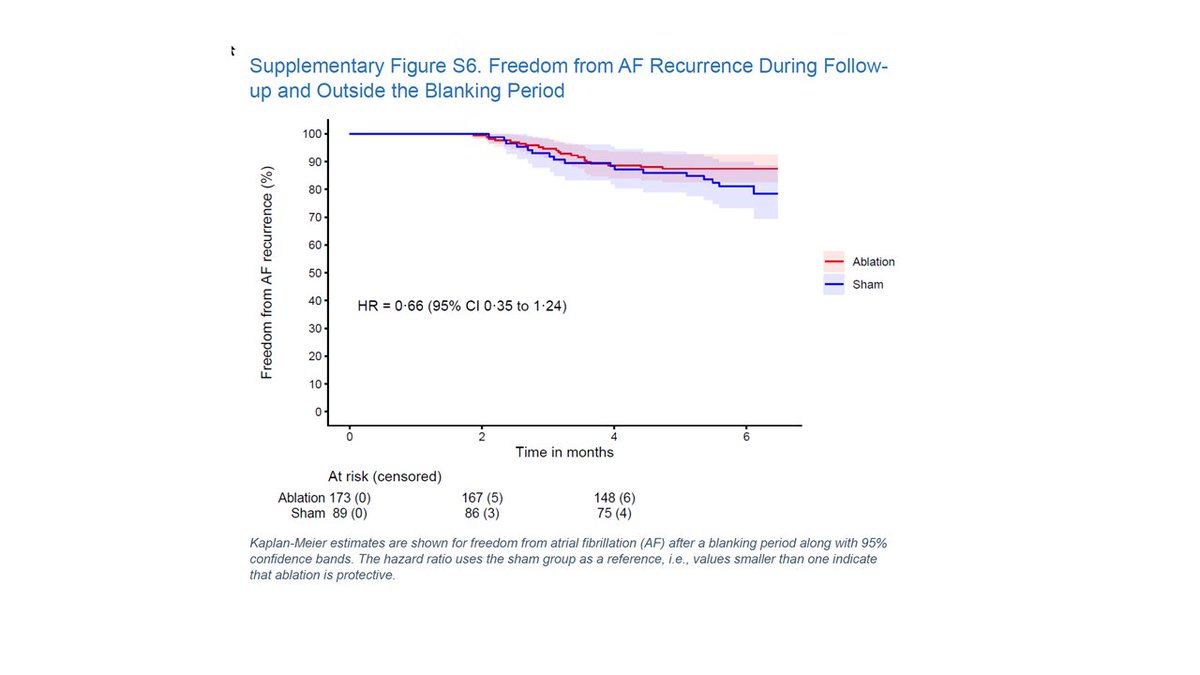
@nmarrouche If we look at supplemental figure 6, it really does look like we're comparing two rhythm control strategies with the two curves not separating much at all with only very modest difference near the end of the 6month mark. Not surprising that the QOL difference is not significant
@dnunan79@drjohnm@theheartorg https://t.co/ggxauxOiJu, here is one of the earlier ones from 2015. There are a lot of similar ones showing the actual incidence of stroke lower than expected based on CHADS-Vasc, hence the assumption that Watchman is likely better than nothing
@drjohnm@theheartorg Nice summary @drjohnm. One critical question is: for patients with serious bleeding who will likely be left alone off AC, is Watchman is better than nothing? It'll be interesting to compare the 10% of those off AC in the trial to the LAAO arm.
@JGarciaMD Thanks! Honestly it still puzzles me how the right bundle gets corrected/activated frequently by the so called LBBA pacing. I think deep septal/conduction system pacing may be a much better term😊
@jeffrey_vinocur Interesting observation 😊 It’s fairly common though in my experience to have some fusion between capturing of the conduction system and local myocardium, ie, an artificial type of WPW
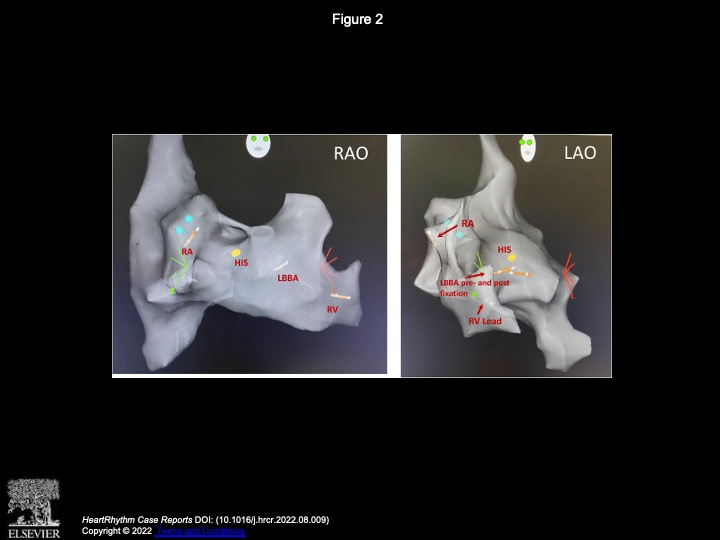
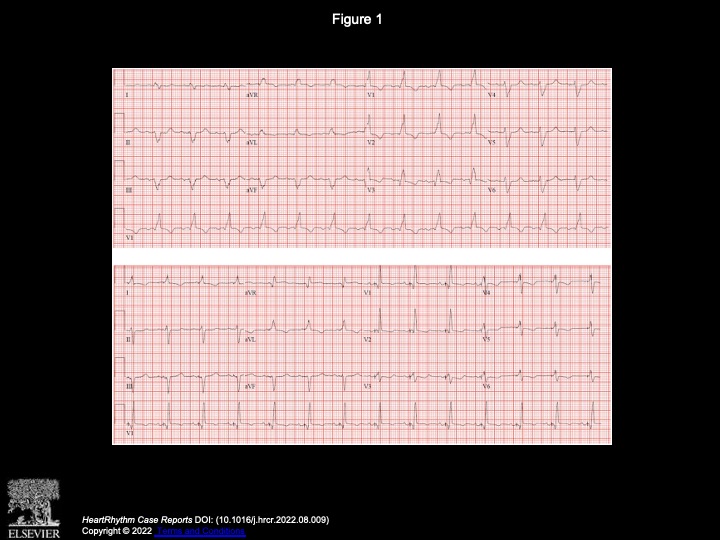
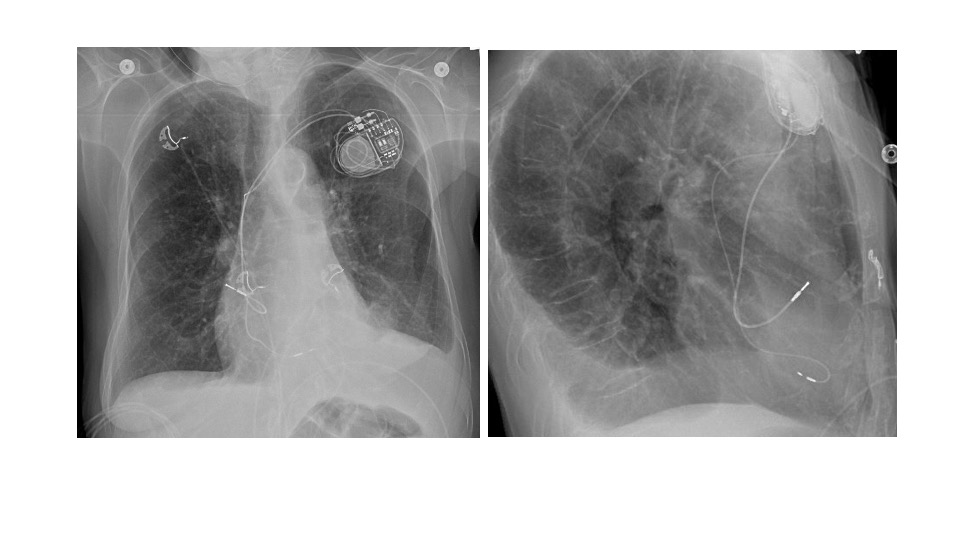
53 YOF, DX'd of LBBB (from previous WPW ablation) induced CM (all other evals are negative), EF 30-35%, class II-III CHF despite GMT > 3months. Would you recommend
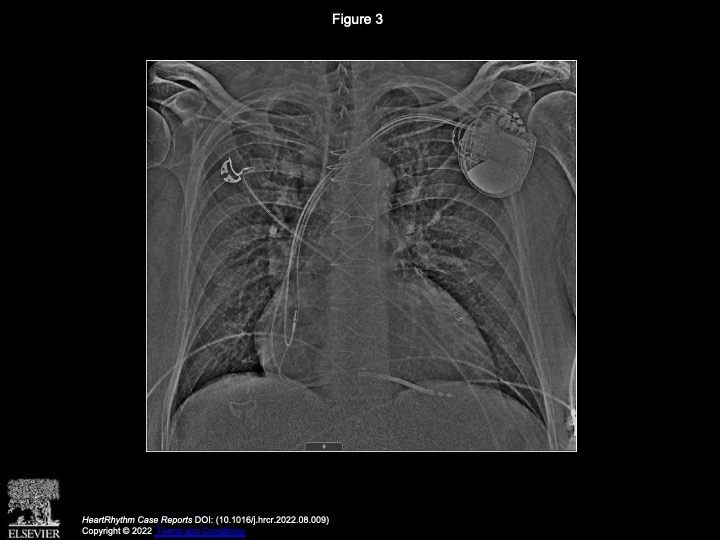
5. months post implant and CHF resolved. Proving the diagnosis of LBBB induced cardiomyopathy. In retrospect, the RV defibrillation lead (and bi-v PPM or ICD) may be unnecessary
4. cardiomyopathy then pacing the LBB would make the most physiologic sense. LBB pacing has also been my primary CRT approach for the last a few years. The patient had bi-v ICD implanted with LBB pacing only (RV lead output to minimum and VV timing at -80ms). EF normalized 2.5
@AveragingBogey This ecg and the other case I tweeted before suggest conduction system pacing or even bi-bundle pacing maybe a more accurate description
Intermittent, narrow RBBB pattern with no significant change in QRS width in a 78 YOF with complete heart block, who underwent intended left bundle area pacing. Mechanism?