Trump tells us the joke is no longer the joke but the strategy. He literally wants our country. This is war through economic means. Do Americans realize what their president is up to?
Trudeau cites how “Canadians fought and died” beside you. Cites Iranian hostage crisis. Hurricane Katrina. La fires. 911. “We were always there”. He is not wrong to cite these key moments. The sense of betrayal is palpable.
The NLN/ANA support keeping clinical hour requirements this low? 500hrs is 2 months of med school rotations. Given NPs have independent practice rights in >50% of the country this is indefensibly low. Their rationale about this worsening nursing shortages is a stretch at best.
Emergency physicians are reported as the specialty with the greatest burnout rate.
This evidence might be something healthcare leaders, HR managers and other administrators want to consider.
@acemonline@CAEP_Docs @ACEPNow
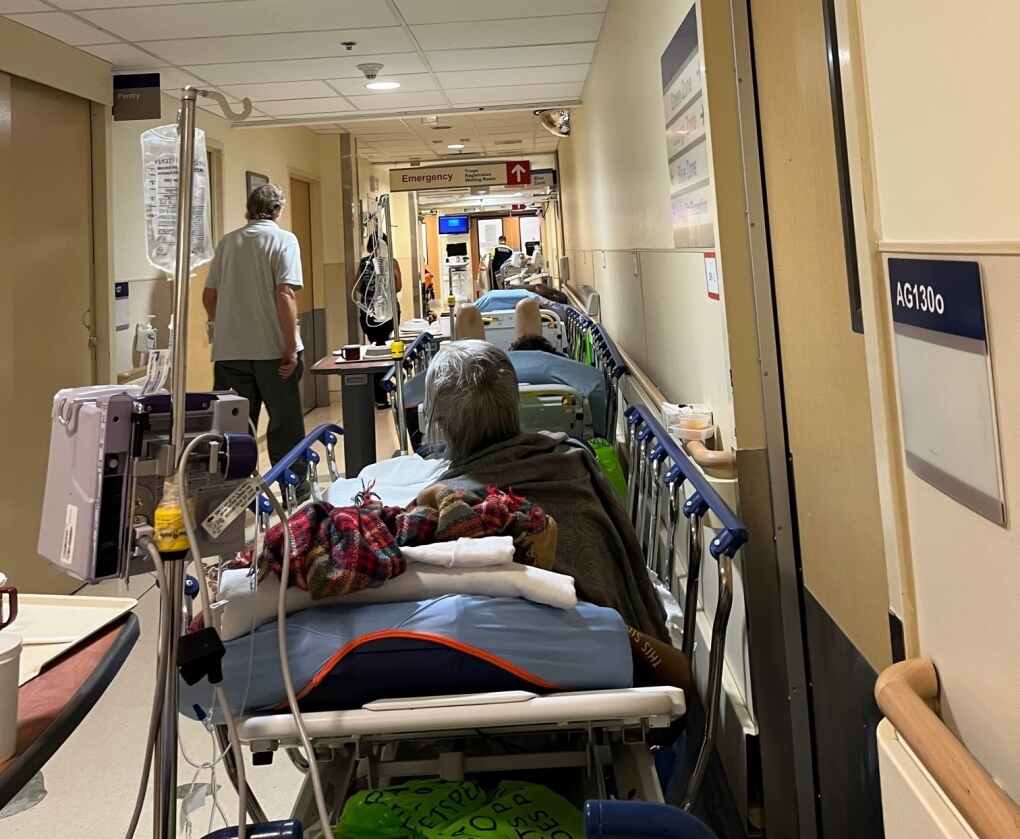
Hope you got a reality check. Forty-five years a physician, forty years in Ontario and never have things been this bad. Every day in an Ontario ER is a gong show except nobody gets to laugh at the incalculable level of human suffering.
@DrKhamisa Interesting- it's not an infrequent occurrence for patients to be sent to the ER by their family doctor asking for us to arrange IV iron for them. I always assumed hospital credentials was the barrier, I guess it's actually a backdoor way to get it covered if it's ordered in ER?
@DescallarEd@joshmcgoo That, or as I often suspect after conversations with American colleagues, it is possible that patients simply present earlier and healthier in a universal healthcare model rather than waiting until they're as serious risk of morbidity/mortality in the US system
@DescallarEd@joshmcgoo You've never seen a PE that didn't meet the Hestia criteria? I have to wonder if we (in Canada) are having a lower threshold to look for PE in stable chest pain patients if that's the case, I would say the *majority* of PE diagnoses I see meet Hestia criteria
@ViridianOnyx@DrHarryDOesHep@Gabby_Brauner27 Of course, which is why I alluded to a number of different steps, but when the physician providing the procedure only costs $49, a further $401 in ancillary costs seems unlikely and I suspect there is simply a massive profit margin being incorporated
@ViridianOnyx@DrHarryDOesHep@Gabby_Brauner27 I am speaking as a physician who has billed that. That $49 is all the physician performing the procedure sees. The patient doesn't pay anything, that's the compensation from the government. It *is* the subsidy
@realEDdoc@DrHarryDOesHep@Gabby_Brauner27 Sure, which is why I said there's a lot of steps, but when the ordering physician performing the procedure costs about $49, getting all the way to $450 seems like a ton of padding
@DrHarryDOesHep@Gabby_Brauner27 I mean, the OHIP (Ontario public healthcare) billing fee is about $9 for the physician services for a pap smear, + $40 visit fee. Sure there's a lot of steps between taking the sample and getting a result, but I struggle to see how you plausibly justify $450
@kimaenglish@NightShiftMD@DrCarolynSnider@alandrummond2@cbcwhitecoat I should add to this not only rural...just "suburban"
Standard of care even a 45 minute drive from downtown seems to shift dramatically due to the resource gap that emerges. Issues that affect outside that downtown core (ex. Defecit of trained EM docs) need to be included
@NightShiftMD@DrCarolynSnider@alandrummond2@cbcwhitecoat Respectfully, I think hearing voices outside of major centers/academic sites (like Alan) would be useful
I understand the major sites are struggling too, but the stark contrast in resources available in downtown Toronto vs the majority of Canadians should be reflected
Retweet if you agree that Ontario needs to end the wage suppression of nurses when hospital shutdowns are occurring due to a shortage of nurses. #RepealBill124