National recall of GLP-1 drug (tirzepatide) made by a US compounding pharmacy because it puts patients at risk, according to FDA
https://t.co/jd5Gjdmbac
gotta make their money off the people somehow right?
if a regulated peptide marketplace does become an option, it’s always going to come back down to price or I doubt much will change.
Calling these “retatrutide deaths” skips the biggest unanswered question: was retatrutide even in the vials?
The FDA received two reports. Neither establishes cause.
One involved a product from an “unreliable source” and kava. The other involved severe dehydration, malnutrition, and a nurse allegedly selling the vials and giving dosing instructions.
Mystery vials and zero traceability are the problem here.
Be safe out there folks.
https://t.co/MgErGfHt1V
The number of people using GLP-1s could more than double over the next few years.
And weight loss is just the beginning.
We’re seeing benefits that extend well beyond the scale:
- Blood pressure
- Blood sugar regulation
- Cholesterol
- Inflammation
- Potential anti-aging and anti-cancer effects
The long-term implications could be massive.
Why does retatrutide raise your resting heart rate?
1. Retatrutide activates the glucagon receptor on top of GLP-1 and GIP. Tirzepatide sticks to the first two.
2. Glucagon signaling turns up energy expenditure and body heat. A higher metabolic load needs a higher heart rate to support it.
3. The phase 2 numbers sit around 5 to 7 bpm at the higher doses, peaking near week 24, then easing back down. Tirzepatide runs closer to 2 to 4.
4. A bump in the first months is part of the mechanism. Log resting HR next to dose and timing and you get to watch the curve yourself.
The trials show the bump has a shape, and it settles.
Not medical advice.
Retatrutide hit 28.3% weight loss at the top dose but 19% at 4mg is the practical story.
Meaningful loss at one titration step means more people actually stay on it...
and that tells you more about what this drug looks like in real life than any headline number.
A summary slide of the TRIUMPH-1 retatrutide data presented today by Dr. Ania Jastreboff at #ADA2026
🚨 TRIUMPH-1: Phase 3 Obesity Trial with Retatrutide 🚨
Retatrutide 💉, a once-weekly triple hormone receptor agonist.
📅 80 weeks (20 months) | 12 mg
⬇️ 28.3% average body weight reduction
⚖️ 70.3 lbs (31.9 kg) lost
📈 Participants in Extension lost up to 30% (85 lbs) on average at 104 weeks
🎯 Weight Reduction Thresholds
✅ Nearly all lost ≥5%
✅ Over 85% lost ≥15%
✅ More than 1 in 4 lost ≥35%
📏 Anthropometric Treat-to-Target
🔵 BMI <30 → 2/3
🔵 BMI <25 → 1/3
📅 At 80 weeks | 4 mg (just 1 titration step) → 19% body weight reduction
🩺 Health Outcomes
🦵 Knee OA: >70% reduction in WOMAC pain subscale
😴 OSA: >60% reduction in AHI
🩸 Prediabetes reverted to normoglycemia in >95% of participants
⬇️ TG 41.0% | LDL 19.6% | SBP 12.3 mmHg
⚠️ Safety
🤢 Most common side effects were gastrointestinal, more frequent with RETA 9 & 12 mg
📉 Reported hypotension more common with RETA in participants on antihypertensive meds
🚽 UTIs more common with RETA, occurring mostly in female participants
#ADASciSessions #Obesity #Retatrutide
Most people don’t know why retatrutide’s results are so different from semaglutide or tirzepatide.
It comes down to receptors.
Semaglutide targets one.
Tirzepatide targets two.
Retatrutide targets three - adding glucagon to the mix, which accelerates fat burning in ways the others can’t.
Each receptor added has moved the needle significantly. The Phase 3 results reflect that.
RFK has been saying this was coming for weeks. Now it’s official.
The FDA is removing 12 peptides from the restricted list. BPC-157, MOTS-c, Semax, Epitalon, Thymosin beta-4 among them. Independent scientific review begins in July.
People have been sourcing these through grey markets for years because legitimate access was cut off. That’s what created real risk for real people.
This should never have happened in the first place.
Today, we took long-overdue action to restore science, accountability, and the rule of law.
In September 2023, the Biden FDA pushed a number of peptides into Category 2 — “Bulk Drug Substances that Raise Significant Safety Risks” — driving a dangerous black market that puts Americans at risk.
Now, after nominators withdrew 12 peptides, the FDA will remove them from Category 2 and will bring them to PCAC at its next two meetings, beginning in July—where independent experts will rigorously evaluate each substance on its scientific merits using full clinical, pharmacological, and safety evidence.
• BPC-157
• Thymosin beta-4 fragment (LKKTETQ)
• Epitalon
• GHK-Cu (injectable)
• MOTS-c
• DSIP (Emideltide)
• Dihexa Acetate
• Ibutamoren Mesylate
• Melanotan II
• KPV
• Semax (heptapeptide)
• Cathelicidin LL-37
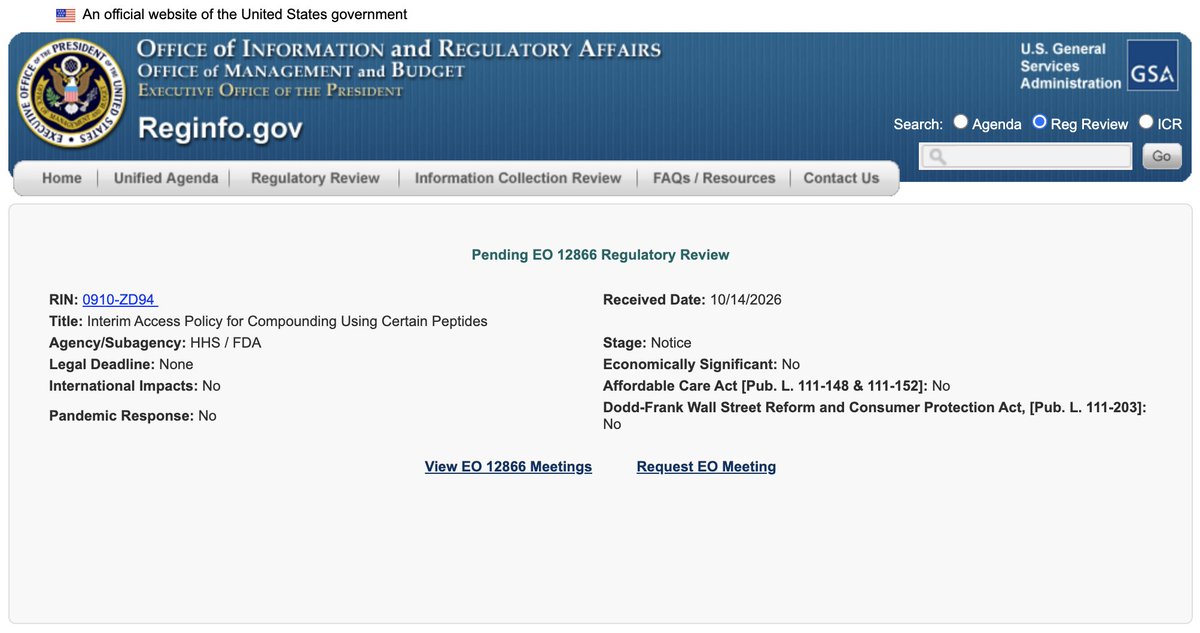
This action begins to restore regulated access and will immediately begin shifting demand away from the black market.
We will follow the science, enforce the law, and deliver the clarity patients, providers, and pharmacies deserve.
GLP-1’s don’t simply cause you to eat less.
They reduce inflammation, reduce cancer, improve arthritis pain, reduce alcohol consumption, protect the heart independent of weight loss, stimulate beta cells in the pancreas, keep you from developing type 2, and generally reduce all cause mortality. 😮💨
So no, you can’t just “eat less” and get the same benefits.
Eli Lilly's orforglipron just got approved as the first GLP-1 pill for weight loss.
A lot of people who passed on injections are about to reconsider.
The barrier to entry just got a lot lower.