@willkidney + @kevin_damman bring the heart of nephrology to the heart of Munich
#StampOnCKD@escardio@MarkusAtHome
Test for CKD in all ❤️ patients
Provide Nephroprotective Therapy
Give iv CM whenever needed
Prefer DOAC over VKA for most CKD pat
🚨BREAKING NEWS from #ESCCongress: The first 1️⃣ ESC Guidelines for the Management of Cardiovascular Disease and Chronic Kidney Disease are here!🫀🫘
The new approach: STAMP on CKD
📍 S-Screen: All patients with CVD should be screened for CKD using both eGFR and spot urine ACR; not creatinine alone
📍 T-Triage & stage: CKD is diagnosed when eGFR <60 mL/min/1.73 m² and/or uACR ≥3 mg/mmol persists for ≥3 months
📍 A-Address risk: Smoking cessation, weight control, physical activity and an SBP target of 120-129 mmHg, when tolerated
📍ACEi/ARB, statin-based therapy and SGLT2 inhibitors are recommended in the majority of patients with CKD, according to the individual indication & kidney function
📍Diabetic CKD with albuminuria, add GLP-1 RA & non-steroidal MRA when appropriate
📍 M-Modify CVD management: CKD changes drug pharmacokinetics and increases the risks of hyperkalaemia, bleeding and AKI; but necessary cardiovascular treatment should not be unnecessarily delayed
📍In HF with CKD, SGLT2 inhibitors & loop diuretics for congestion are recommended irrespective of LVEF, with additional therapy guided by EF and eGFR; overall there is limited evidence when eGFR <30 mL/min/1.73 m²
📍 P-Plan services: identify high-risk patients, minimize CKD-related treatment delays & strengthen multidisciplinary care
Read more📚: https://t.co/RUsCVUAyCu
@escardio #ESCGuidelines
#CKD #CVprev #Prevention #CVD
@kevin_damman@jozinetm
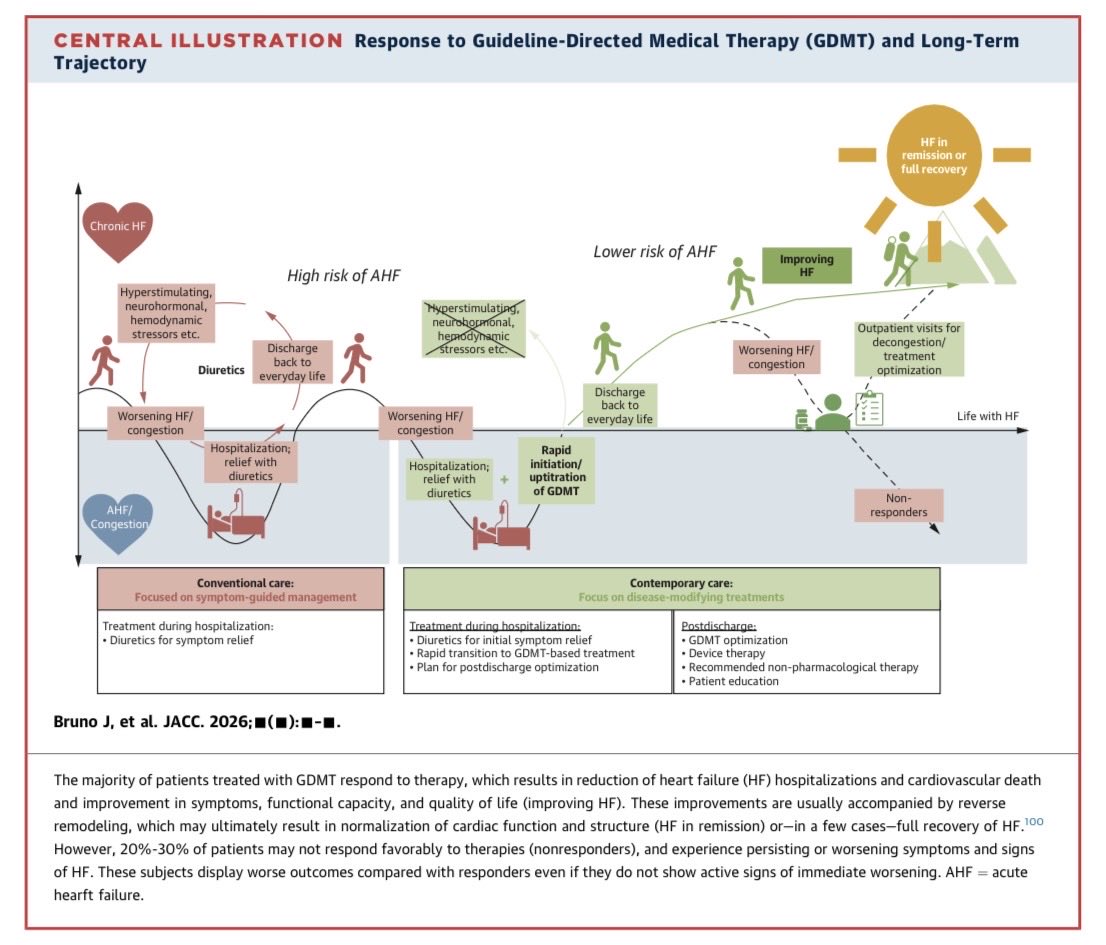
Una grandísima revisión de "Manejo de falla cardíaca descompensada" en JACC 2026. Puntos importantes actualizados:
🟠 Se añaden umbrales confirmatorios de falla: BNP >400 ng/L o NT-proBNP ajustado por edad (>450 ng/L en <50 años; >900 ng/L en 50-75 años)
🟠 Dosis inicial de furosemida — antes: 1-2.5 veces la dosis oral previa. Ahora: 40 mg IV en pacientes sin diurético, y si ya usaba: ≥80 mg IV o dos veces la dosis oral.
🟠 Ahora se sugiere valorar a las 2 horas buscando: uresis ≥300 mL o Na urinario ≥70–80 mmol/L.
🟠 Si hay resistencia ahora se sugiere duplicar el bolo hasta 250 mg de furosemida, considerar acetazolamida o tiazida.
🟠 Ahora se sugiere secuenciación temprana para usar iSGLT-2, ARM (como Espironolactona), ARNI, betabloqueador antes del alta.
Completo en el canal (https://t.co/3O93s10lns).
🚨 Managment of AHF is advancing!
Glad to share our review, aimed at:
🔄 Bring together management algorithms across different healthcare settings and resources
🏥 Translate contemporary evidence into practical bedside management
#HeartFailure#AcuteHeartFailure#JACC
The inaugural article in @JCFINT takes a fresh look at the intersection of EP + HF through the lens of AFFIRM
📌 56% of AF patients had HFpEF
⚠️ Rhythm control with Class Ic/sotalol ↑ mortality in HFpEF
✅ Amiodarone showed safer profile
🔗 https://t.co/JvhLZ5pSnM
#CardioX
🔥 HOT #HeartFailure2025
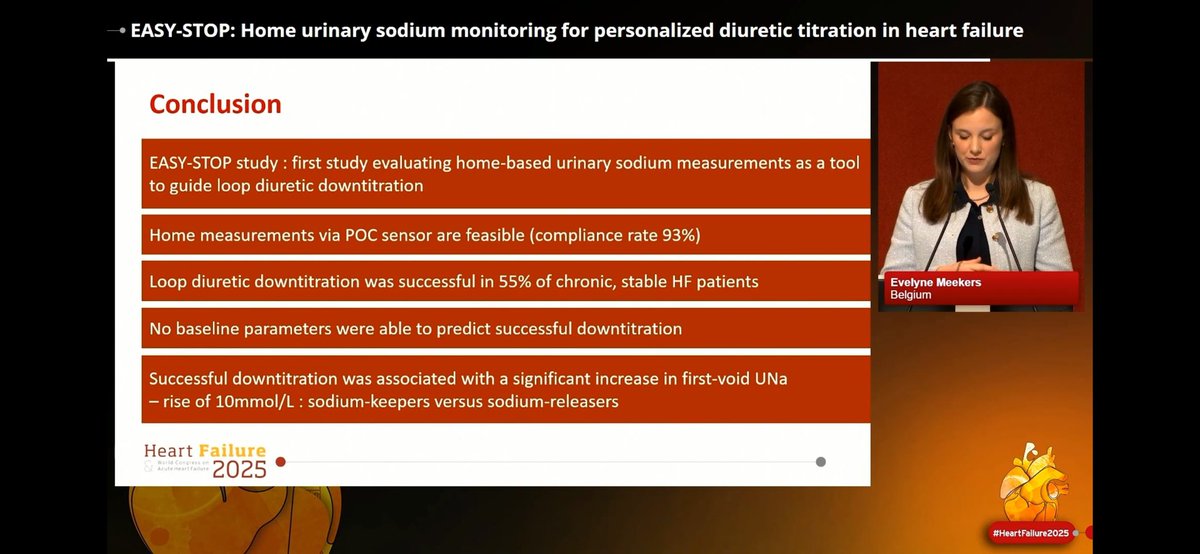
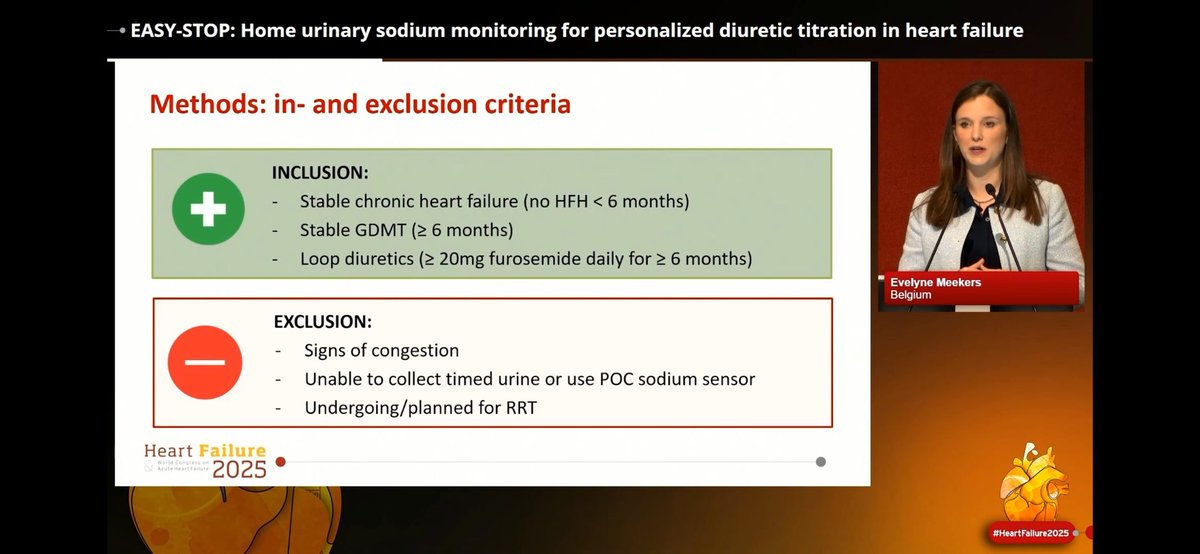
🏡 EASY-STOP: urinary sodium monitoring for diuretic optimization in CHF 💧
✅ The method was effective — 93% c
⚖️ 55% successfully ⤵️ the loop diuretic
❗ Baseline parameters don’t predict success — an individualized approach is needed @escardio
📢 Results of our EASY-STOP study now presented #LBCT at #HeartFailure2025! A thread 🧵
1/ 🚀 First study to evaluate home-based #UNa using a POC sensor to guide loop diuretic downtitration in chronic #HeartFailure patients. #Cardiology#FOAMed
#JACC HF:
From the CABANA trial:
Patients with #HFpEF benefited > from #Afib ablation:
⬇️Death/CV hospitalization
⬇️AF recurrence
Despite greater benefit of HFpEF patients, their risk of recurrence remained higher than in those without HFpEF
https://t.co/HmPe4jJK8N
Expert consensus #EJHF on urinary sodium-guided diuretic titration in #ADHF
Why #natriuresis matters in optimizing #decongestion, a thread🧵:
1️⃣/ 📍Congestion = main cause of #AHF hospitalizations🏥, yet not all patients were fully decongested
📍Low UNa+ ➡️sodium retention ➡️incomplete decongestion ➡️higher risk of poor outcomes. Fluid loss alone may not tell the full story
#HF #DiuresisJedi
@jozinetm@FH_Verbrugge
Interaction Between AF and MR – Insights from CABANA trial 📰
✅Strong interplay between AF, MR, and HFpEF
✅Ablation superior to drugs for rhythm and symptom control in AF patients with MR
✅Ablation associated with reduction in MR severity over time
https://t.co/szmB4ADZP7