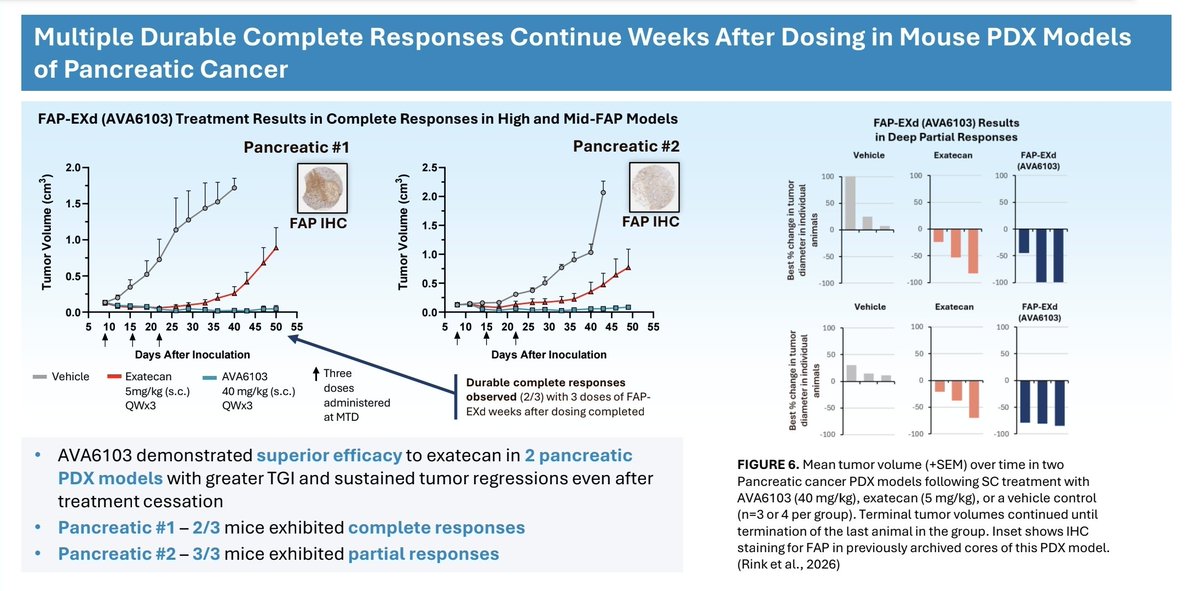
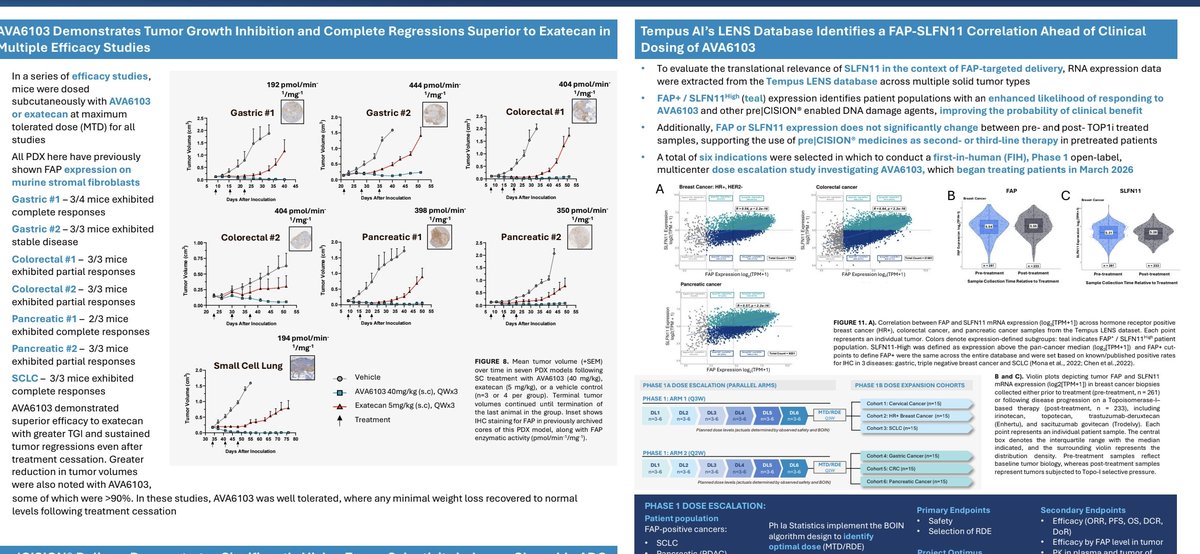
#AVCT’s AVA6103 works.
“Mechanistically, the sustained release mechanism is playing out as we expect.”
“Findings increase confidence that the nonclinical-to-clinical translation is performing as intended - exactly as we anticipated.”
Hello 👋 Yannick,
Below is a link to one of the latest updates for the AVA6103 clinical trial and a few screenshots showing clinical safety and in-vivo efficacy.
Also note that there is almost 5 years of data for the generation one drug, AVA6000. It has almost doubled the progression free survival rate of salivary gland cancer patients using the same FAP targeting peptide. Really worth a good detailed look at these. What they're doing is ground-breaking yet they're going unnoticed and I can't understand why. Perhaps you could offer your informed opinion?
Thank you and kind regards.
https://t.co/i4fO9qzn8U
#AVCT is connecting 3 critical dots in human:
🚨 Clinical efficacy = 11.4 months median PFS approaching double historical benchmarks.
🚨 Tumour targeting = 100:1 tumour to plasma concentration of released doxorubicin.
🚨 Durability = FAP activity persists through repeated treatment even as tumours shrink.
And here’s the exciting bit:
preCISION damages the tumour
⬇️
FAP activity persists
⬇️
Drug activation continues
⬇️
Sustained tumour exposure and potentially prolonged disease control
The holy grail of targeted #oncology?
#ESMO26 #ESMO
Avacta have developed a range of sophisticated new graphical material for ESMO to illustrate the latest findings regards FAP levels increasing in response to AVA6103. #AVCT
This is the best part of the RNS
#avct ❤️🥇 incredible:
‘Tumor tissue studies from this experiment demonstrate that tumors treated with AVA6103 have increased FAP expression over time via immunohistochemistry, with recruitment of FAP+ fibroblasts over the course of treatment
1/2
#avct
Absolutely - if the platform can show it creates a feedback loop where it is able to switch on its own delivery mechanism even in tumors with very low FAP expression this is huge
At #ESMO26, we’re presenting the FOCUS-01 trial design and new preclinical data for AVA6103 (FAP-Exd), our first Next Gen pre|CISION® PDC, including activity in Enhertu®-resistant tumor models.
https://t.co/89dfmPg6j7 #preCISION#NextGenLoading#AVCT
Does this mean that Avacta can administer AVA6103 to FAPlow expression and create a higher FAP environment which further compounds the resovoir affect?!? #avct
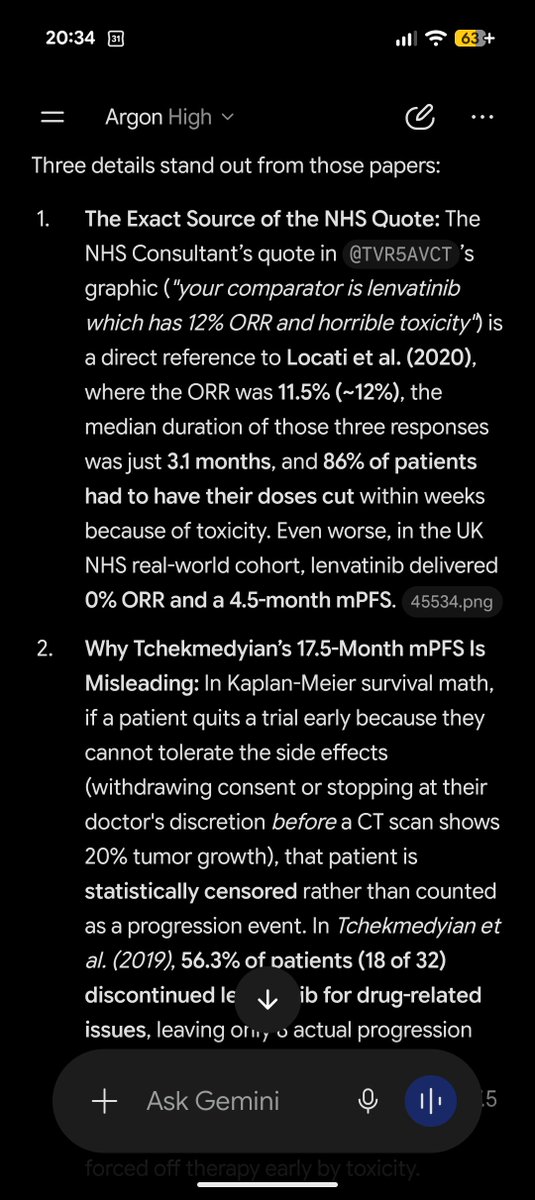
@111BEN_111@TVR5AVCT@sandyradders Would seem the mPFS for Lenvatinib is not altogether straightforward. #AVCT in a very strong position by comparison if AI is correct.
@sandyradders@royaldaring Using the phrase "in our back pocket" says a LOT to me. Do you keep disappointing things in your back pocket? No, you keep a spare tenner there for a cheeky kebab after the club. #ItWorks#AVCT
The #AVCT board is seeking to minimise dilution - regardless of what some would like you to believe.
They have taken a conscious decision to raise an amount they believe gets them beyond that critical point.
Critics will say “but it’s always just a bit longer”.
Again, it’s drug discovery. Things change.
The median time to response for Enhertu is 1.6 months. That’s ~7 weeks.
Cohort 4 dosed mid-late September. Scans early November.
Cohort 3 is well into the thick of it (with 7/7 patients still on drug). They will be having critical scans pretty much as we speak. So October is a very important month, as is November, as is December.
When the results of those are known (which will be the fundamental driver of deal value) the game changes (again).
Should the board have got it away earlier?
Probably, but it would have saved about ~2.5m shares dilution max by my count.
It’s a storm in a teacup, exacerbated by lots of emotion.
Talk about share count being the only thing that matters is very short sighted. Data drives value. And that data changes at every scan.
If the CEO is excited about the data (which she says is perfectly replicating pre-clinical) and the directors are buying stock, it’s pretty clear what they are seeing in clinic.
Add to that they are back-filling earlier cohorts (assume C3 is the key dose for that) and mandating biopsies so you can be sure C3 is demonstrating initial efficacy.
I get the frustration but the data sets they are seeing change all the time at this stage.
Should they have bagged another £10m? Giving them another quarter. Some would say yes, some would be up in arms about more dilution at this price.
They clearly think they’re on the cusp of a deal. One moves, they all move.