Clip’s on, aneurysm still filling on ICG. Your next move?
Teaching points from a hands-on clipping course at King’s College London, taught on our patient-specific MCA aneurysm model.
(Brain colours softened for social media. The real model is more lifelike)
#Neurosurgery #AneurysmClipping
A bag of saline on an IV pole gives you flow. It doesn't give you a pulse.
You notice the difference as soon as a device goes in. A microcatheter tip, a coil or an aspiration catheter behaves differently in a vessel that moves 70 times a minute than in one sitting under steady pressure. If you're teaching embolization, the way the embolic travels downstream depends on that pulse too.
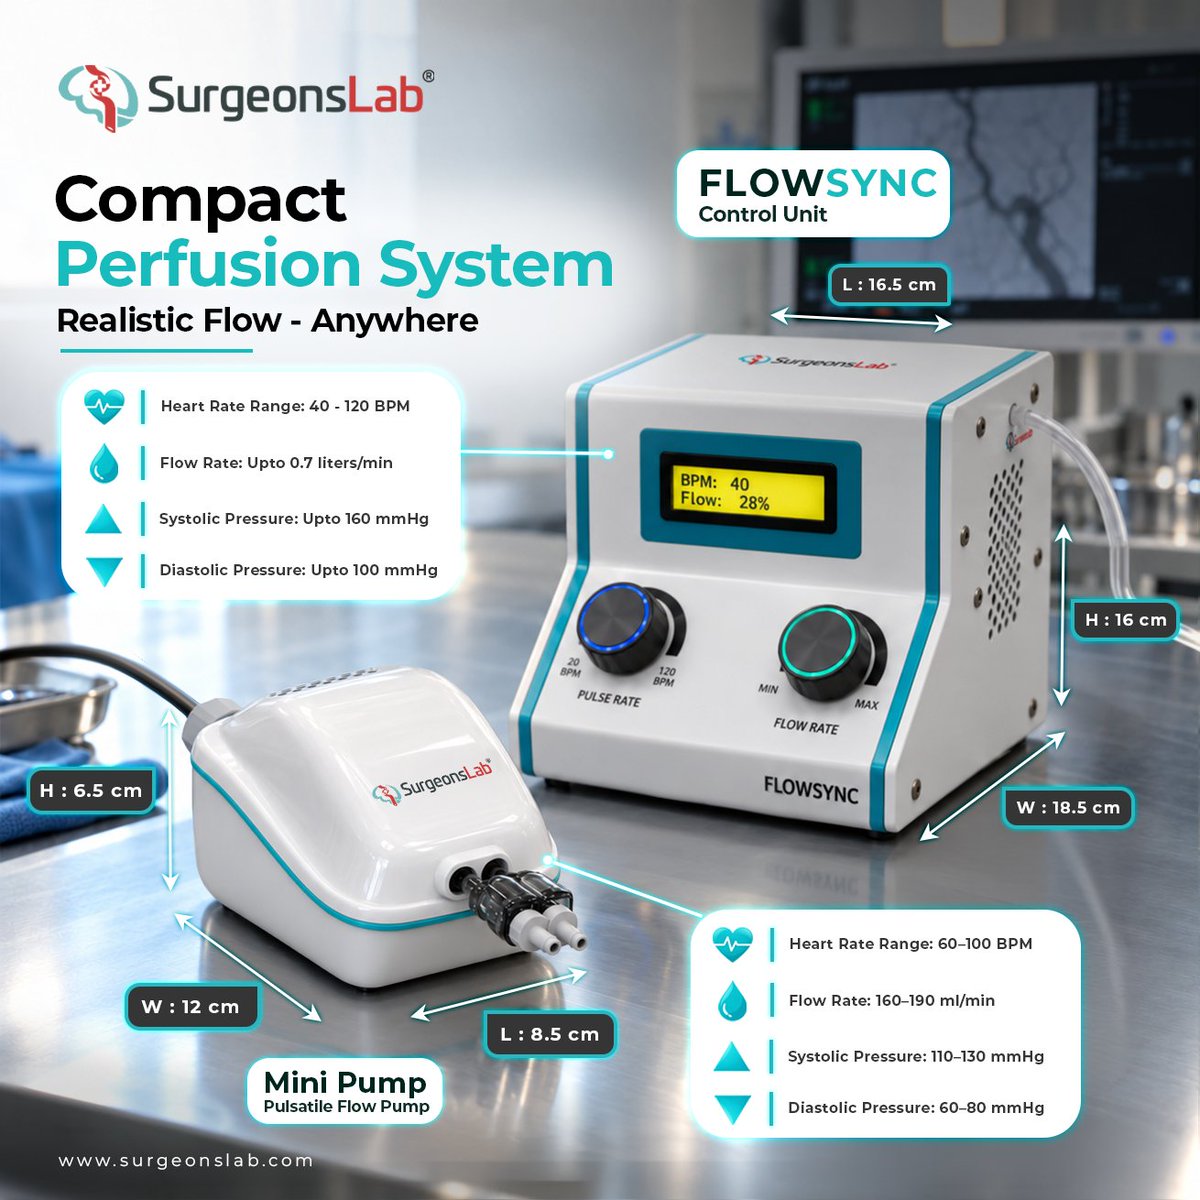
The pump also has to fit the job. A full vascular loop on a test bench needs more than a single model on a workshop table, so we built two compact pulsatile units.
FLOWSYNC Control Unit - For full circuits and models with higher flow needs
- Dimensions: 16.5 x 18.5 x 16 cm
- Pulse rate from 40 to 120 BPM
- Flow up to 0.7 L/min
- Systolic up to 160 mmHg, diastolic up to 100 mmHg
Mini Pulsatile Pump - For smaller models, focused sessions and portable workshops
- Dimensions: 8.5 x 12 x 6.5 cm
- Pulse rate from 60 to 100 BPM
- Flow rate from 160 to 190 mL/min
- Systolic 110 to 130 mmHg, diastolic 60 to 80 mmHg
On both, you set pulse rate, pressure and flow yourself.
On the FLOWSYNC you can run a model at 45 BPM, then take the same anatomy up to 160 systolic and watch what changes. They sit alongside the continuous-flow setups in our perfusion range, for models where steady flow is all you need.
Built for:
→ Interventional radiologists and course directors running embolization and endovascular workshops
→ Device engineers comparing designs under the same, repeatable conditions
→ Field and clinical education teams taking a working demo to a hospital or congress
Planning a workshop, a device demo or a new bench study? Tell us the model and the flow you need, and we'll help you pick the right setup. Visit: https://t.co/Vwg0SeDJ3U
What's the one thing your current flow setup can't do that you wish it could?
Setting up a vascular model, a test bench or your next workshop? Send us the application, the model size and the flow and pressure you need, and we'll suggest a configuration that fits.
Email us at [email protected] or Visit https://t.co/x6wTRihCf5
#InterventionalRadiology #Endovascular #Embolization #Hemodynamics #MedicalDeviceTesting #SurgicalSimulation #MedicalSimulation #SurgeonsLab
Heading to MD&M Midwest in Minneapolis? Come find us at Booth #2946.
If you're developing a device for spine, Vascular, peripheral or oncology procedures, you already know how far a benchtop fixture is from a real patient. That gap is exactly where we work.
At SurgeonsLab, we build simulation models that look, feel and behave like real anatomy. That means tissue with realistic feel, vessels with physiological flow, and anatomy that responds the way your device will meet it in the clinic.
Device teams work with us across the whole product lifecycle:
• R&D and early design iteration
• Bench testing and design verification
• Human factors and usability studies
• Physician training and procedural education
• Sales enablement and live demos that actually show your device in action
Whether you're working on a Class I instrument or a Class III implant, we can build around your device, your procedure and your target anatomy, including patient-specific models from imaging data.
At the booth you'll get hands-on time with:
Surgical Spine Model
Vascular & Tumor Model
Reusable Embolic Demonstrator (RED)
CathTrain VR endovascular simulator
Endovascular flow models with Circle of Willis aneurysms
What we'd most like to hear about is the procedure you're struggling to test, teach or demo. Bring it to us and let's talk about building it.
Flying in from the East Coast or elsewhere? Send me a message and we'll set a time to meet so you're not hunting for us on the show floor.
Booth #2946, Minneapolis Convention Center
October 28–29, 2026
#MDMMidwest #MedTech #MedicalDevices #MedicalSimulation #DeviceDevelopment #InterventionalRadiology #Endovascular #Neurovascular #SpineSurgery #HumanFactors #MedicalAlley #SurgeonsLab
Getting the embolic in is the easy part. The real question is where it goes next.
In MMA embolization, "how distal is distal enough?" has become one of the most debated questions in the field. Go deeper and you may cover more of the target territory. Push too hard and you risk reflux back along the catheter, or flow into places you never meant to reach.
The tricky part is that a lot of this happens in vessels smaller than a millimeter, where it's hard to see what's actually going on.
So we filmed it. This video is live fluoroscopy of a liquid embolic moving through our MMA model, with branches in the sub-millimeter range. You can watch two things happen in real time:
1. How far the embolic penetrates into those small distal branches
2. When reflux starts, and how far it travels back toward the catheter tip
Because the anatomy is the same every run, you can change one thing (injection speed, catheter position, the agent itself) and see exactly what that change does.
For physicians, that means practicing the feel of a controlled injection before it matters. For device teams, it means comparing how an agent or catheter behaves in a consistent, repeatable anatomy.
Watch it, and tell us: what would you test first?
#MMAembolization #Neurointervention #Embolization #Endovascular #InterventionalNeuroradiology #MedicalSimulation #MedTech #SurgeonsLab
Evaluating embolic penetration and reflux dynamics requires bridging direct bench-top observation with real-world clinical imaging.
The Reusable Embolic Demonstrator (RED) provides a single, flow-enabled platform supporting three distinct visualization modalities:
Optical Camera: Real-time, transparent tracking of vessel filling, reflux patterns, and occlusion mechanics.
Fluoroscopic: Seamless integration for embolic tracking and workflow evaluation in an angio suite
CT road mapping: High-resolution cross-sectional computed tomography imaging for detailed 3D volumetric assessment.
Pairing quick-swap pathology modules with multi-modal compatibility gives R&D and clinical teams a cost-controlled setup to validate embolic behavior from benchtop to angio suite.
Know more about the Reusable Embolic Demonstrator, visit https://t.co/5sqYuyWDH4
You can also drop us an email at [email protected]
#Endovascular #Neuroradiology #LiquidEmbolics #SurgeonsLab #MedicalDeviceTesting #Neurointerventions
Evaluating embolic penetration and reflux dynamics requires bridging direct bench-top observation with real-world clinical imaging.
The Reusable Embolic Demonstrator (RED) provides a single, flow-enabled platform supporting three distinct visualization modalities:
• Optical Camera: Real-time, transparent tracking of vessel filling, reflux patterns, and occlusion mechanics.
• Fluoroscopic: Seamless integration for embolic tracking and workflow evaluation in an angio suite
• CT road mapping: High-resolution cross-sectional computed tomography imaging for detailed 3D volumetric assessment.
Pairing quick-swap pathology modules with multi-modal compatibility gives R&D and clinical teams a cost-controlled setup to validate embolic behavior from benchtop to angio suite.
#Endovascular #Neuroradiology #LiquidEmbolics #SurgeonsLab #MedicalDeviceTesting #Neurointerventions
Advancing neurovascular training standards across the Middle East requires simulation infrastructure capable of replicating authentic anatomical friction, microscopic depth, and tactile feedback.
SurgeonsLab is pleased to announce the successful installation and operational setup of our SurgTrain surgical platform, endovascular aneurysm models and CathTrain VR at Children’s Cancer Hospital Egypt 57357 (CCHE 57357)—a premier regional center for pediatric and neuro-oncology care.
The installed suite provides CCHE 57357 with a comprehensive physical simulation environment:
SurgTrain Surgical Console: Designed for high-fidelity microsurgical clipping practice under microscope visualization, replicating realistic tissue resistance and spatial constraints.
Benchtop Endovascular Aneurysm Models: Configured for microcatheter manipulation, coil deployment, and navigating complex vessel tortuosity.
Neura-Bubble & Modular Units: Specialized setups engineered for targeted anatomical access and procedural refinement.
As healthcare institutions across Saudi Arabia and the broader MENA region continue to elevate clinical simulation infrastructure, establishing patient-specific, reusable dry-run environments is essential for building procedural confidence without intraoperative risk.
For neurosurgery and interventional radiology leads in the region: How is your institution incorporating physical simulation suites into resident training and complex case planning?
To explore bringing SurgeonsLab neuro-simulation platforms to your hospital or training center in the Middle East, contact our team at [email protected] or visit https://t.co/Y1IPYKJ6bO
#Neurosurgery #InterventionalRadiology #Neurovascular #SurgicalSimulation #MedTech #SaudiHealthcare #MENAHealthcare #CCHE57357 #MiddleEastMedTech #SurgeonsLab #SurgTrain #CathTrainVR #ClinicalTraining
Absolutely. The value of a realistic bench model is not just in reproducing anatomy, but in giving clinicians the opportunity to work through the technical challenges before they encounter them in the angio suite.
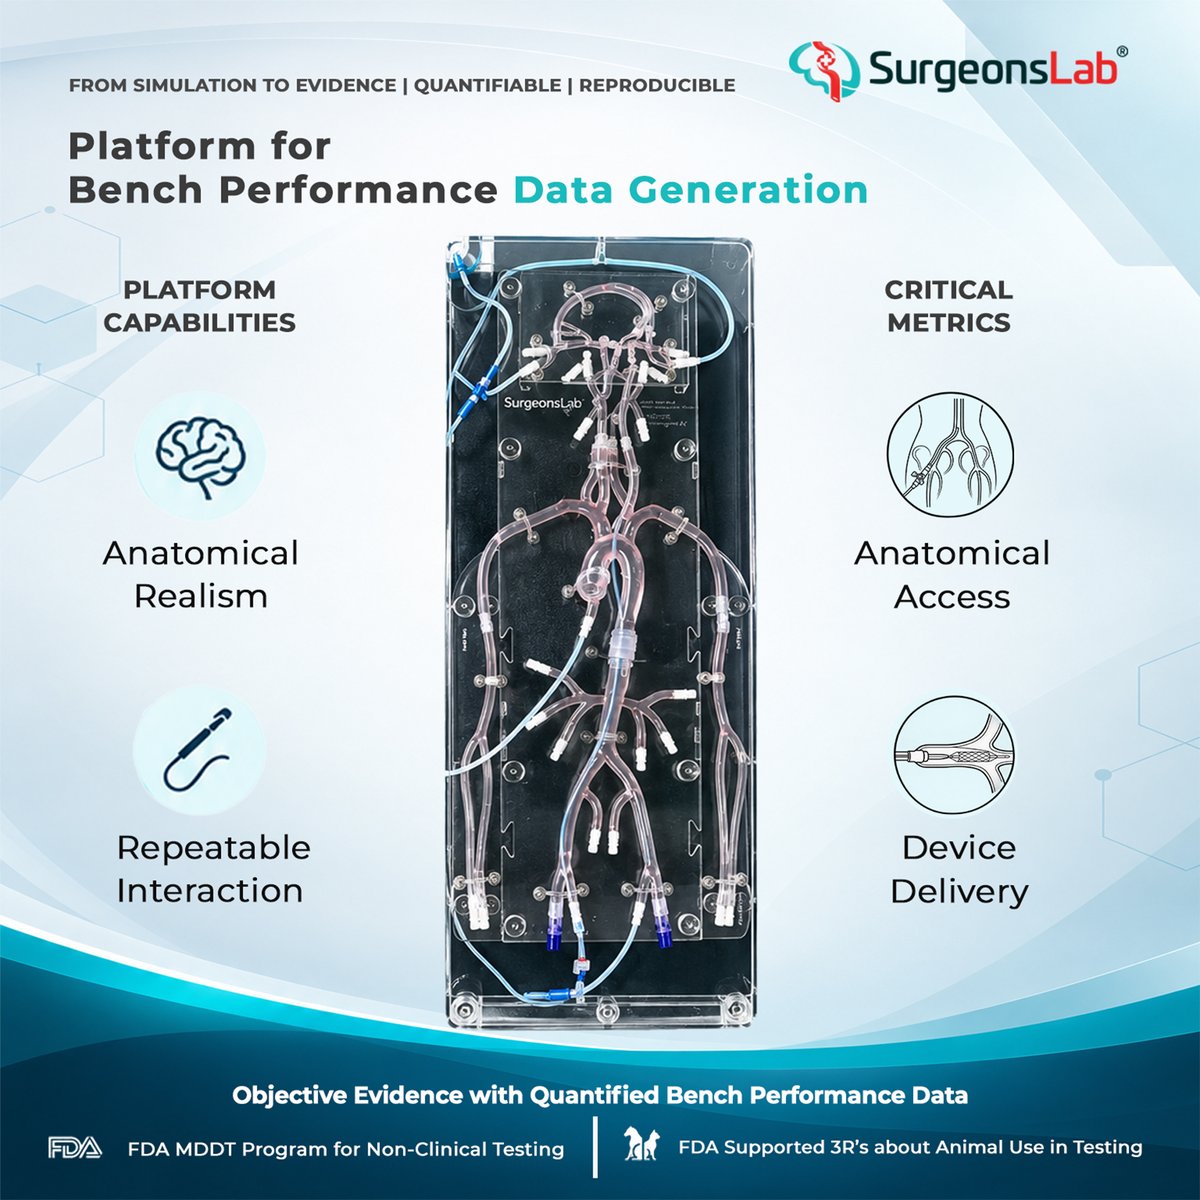
For us, that means realistic anatomy, repeatable device interaction, and measurable bench performance—so teams can train, evaluate, and refine technique in a controlled environment.
Appreciate you highlighting this. We’re continuing to build around that principle at SurgeonsLab.
Explore our endovascular simulation flow models, visit:
https://t.co/ihPIdoivxy
Anyone who's pushed a microcatheter through a tortuous vessel knows that knowing the anatomy is only half the job. The other half is knowing how your device will actually behave once it's in there.
That's hard to learn from a screen. Your hands need to feel the resistance, the lag in torque, the moment the wire wants to prolapse. So whether you're comparing radial and femoral access or training a new interventionalist on access selection, the bench model has to feel real.
That's what we built our platforms at SurgeonsLab to do using our Endovasular flow model with and without hydrophilic coated lumen. With the catheter in the system, teams can focus on:
Access site selection. How stable is the sheath? How clean is the entry angle across different access points?
Wire and microcatheter behaviour. Torque response, pushability and trackability through tight, winding anatomy.
Real-time simulation. Practising navigation and benchmarking devices in a fluid-filled setup before anyone steps into the angio suite.
When you can isolate these variables on the bench, you get data you can trust and repeat. That means fewer surprises in the procedure room, and that's better for everyone, especially the patient.
Curious how others handle this: how is your team testing microcatheter trackability and access selection right now?
#Neurovascular #InterventionalNeuroradiology #Endovascular #MedicalDevices #MedicalSimulation #CatheterNavigation #BenchTesting #MedTech #ClinicalTraining #SurgeonsLab
Glue or Onyx? Coils or particles? How distal is distal enough?
MMA embolization is everywhere in neurointervention right now, and good operators still disagree on how to do it. What nobody disputes is that it's a small, tortuous vessel with very little room for error.
So we built a model for it. True-to-scale MMA trunk and branches, validated with DMSO and nBCA, angio-ready, in 2D and 3D, single-use or reusable, with an optional closed-loop perfusion setup. Navigate, coil, glue, inject particles, then do it again.
For fellows, for experienced operators trying something new, and for device teams who need consistent anatomy.
Want one for your course or lab? Send us a message.
#MMAembolization #Neurointervention #Neurosurgery #MedicalSimulation #MedTech #SurgeonsLab
Understanding vascular anatomy on 2D imaging is straightforward. Navigating that anatomy under a surgical microscope is where procedural complexity begins.
During the 9th Walter E. Dandy India Neurosurgical Educational Course in Siliguri, the trainees got hands-on experience with complex aneurysm geometries and navigating deep surgical corridors. While pre-operative planning clearly outlined vessel connections, translating that plan to microscopic execution introduced real-world physical constraints: shifted working angles, restricted depth, vessel compliance, and precise clip orientation.
This gap between imaging and physical manipulation is why hands-on simulation on our SurgTrain Surgical Simulator is necessary for neurosurgeons and residents to practice patient-specific vessel tortuosity, testing force application, micro-dissection angles, and clip trajectories in a controlled environment.
True surgical readiness builds from refining and repeating techniques on the SurgTrain platform until execution is natural.
Our sincere thanks to the Walter E. Dandy India Neurosurgical Society, distinguished faculty, and participating trainees for an outstanding educational session.
To discuss patient-specific simulator models for your institution, connect with us at [email protected].
You can also connect with us at https://t.co/Y1IPYKJ6bO
#SurgeonsLab #WalterEDandy #Neurosurgery #SurgicalSimulation #NeurosurgicalEducation #Microsurgery #SurgicalTraining #MedicalSimulation #Neurovascular #ACOM #ICA #MCA #TumourResection #Neuro #Surgery Walter E. Dandy Neurosurgical Students Club India
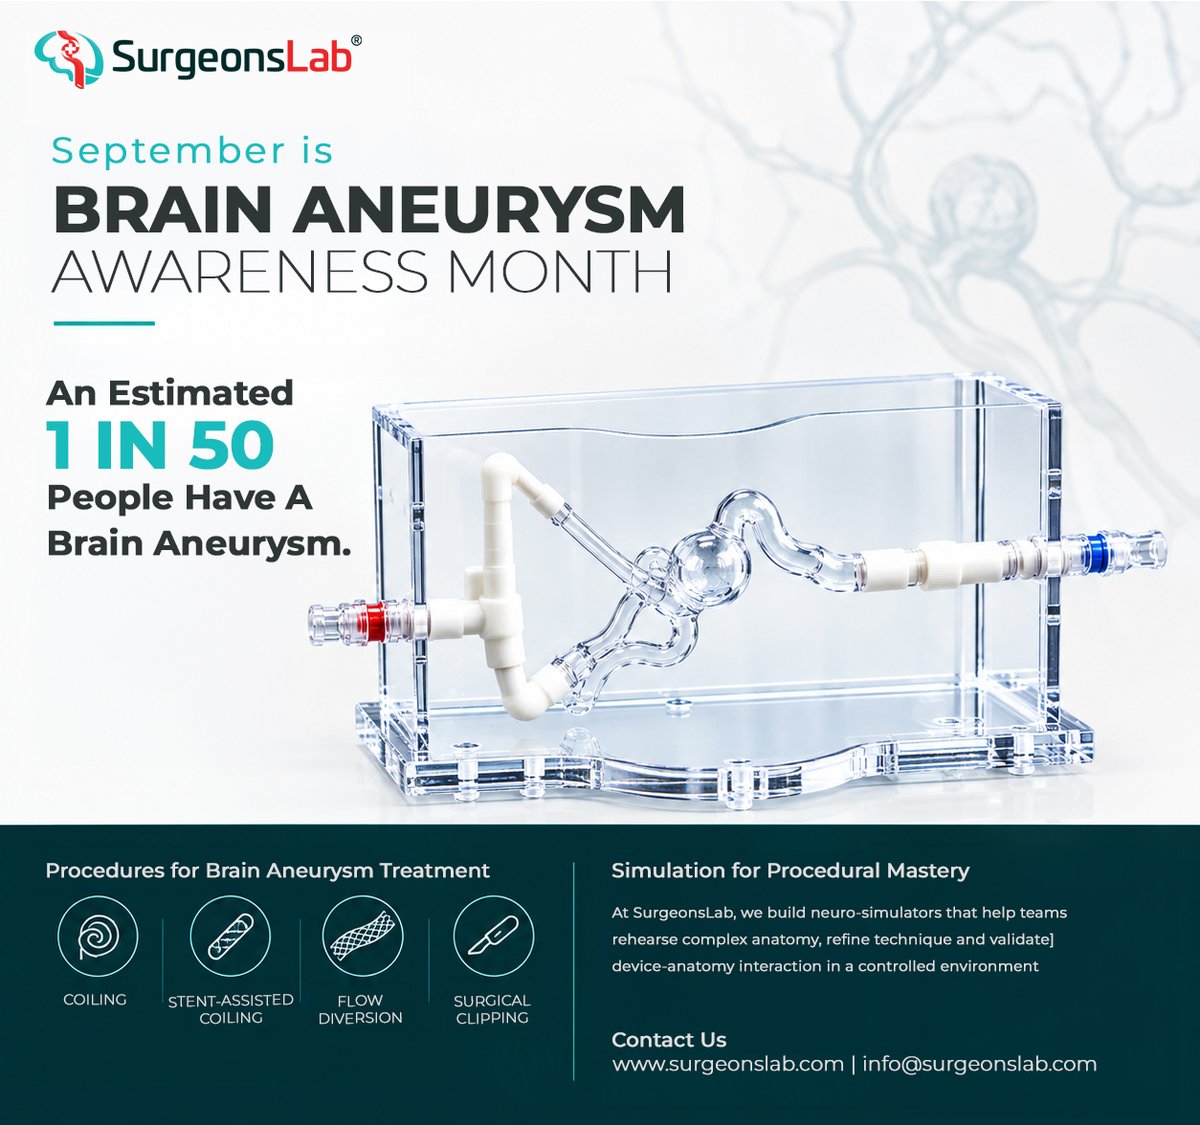
September is Brain Aneurysm Awareness Month.
A brain aneurysm is a weakened area in a cerebral artery wall that can create a complex clinical and procedural challenge.
1 in 50 individual have an unruptured cerebral aneurysm. When the aneurysm ruptures, the clinical impact is immediate—a critical stroke event carrying a 50% mortality rate.
Treatment may involve coiling, stent-assisted coiling, flow diversion, or surgical clipping, depending on the aneurysm and the clinical situation.
For neurovascular teams, whether deploying endovascular techniques like coiling, stent-assisted coiling, and flow diversion, or executing microsurgical clipping, navigating complex vessel tortuosity and delicate wall geometries leaves zero margin for error. Operative success relies on device behavior, precise positioning, and thorough anatomical familiarity before making the first access site.
This Brain Aneurysm Awareness Month, the focus must extend beyond detection to procedural mastery.
Rehearsing complex anatomy and device–anatomy interaction in a controlled environment can support technical training and procedural mastery.
At SurgeonsLab, we develop neuro-simulators designed to help teams rehearse, refine challenging neurovascular procedures and validate neurovascular devices faster.
This month is an opportunity to raise awareness, support education, and keep advancing preparation for complex cases.
Rehearse the anatomy. Refine the technique. Be ready for the procedure.
#BrainAneurysmAwarenessMonth #BrainAneurysm #Neurovascular #Neurointervention #MedicalSimulation #EndovascularTraining #SurgeonsLab #MedTech
5,000+ Followers.
A small number on a screen, but a meaningful milestone for the SurgeonsLab community.
Thank you to the surgeons, interventionalists, educators, biomedical engineers, device professionals, researchers, and MedTech teams who follow our work, challenge our thinking, and engage with what we share.
We started SurgeonsLab around a simple idea: realistic simulation should bring anatomy, devices, and procedural technique closer together.
That means more than replicating anatomy.
It means creating models where complex neurovascular anatomy, tortuosity, bifurcations, access challenges, and device–anatomy interaction can be explored in a controlled and repeatable environment.
Whether it is evaluating microcatheter navigation through acute bifurcations, studying embolic delivery in MMA models, or refining access techniques, the objective remains the same:
Understand the procedural challenge. Test it repeatedly. Generate meaningful evidence before it reaches the patient.
Over the past few years, the conversations with this community have helped shape the questions we ask and the problems we work to solve.
5,000 is not the destination. It is a reminder to keep building, testing, learning, and sharing.
Thank you for being part of the journey.
— SurgeonsLab
#SurgeonsLab #MedicalSimulation #MedTech #SurgicalTraining #EndovascularTraining
Spot-on observation @dtruscello215
Navigating 2nd and 3rd order intrahepatic ducts remains a major ERCP bottleneck—standard cannulas often lack the torque and stability for acute, tight branches.
Translating microcatheter mechanics into interventional GI brings three key advantages:
1:1 Torque Control: Selective entry into tight side-branches without wire buckling.
High Trackability: Superior column strength to cross fibrotic strictures.
Low Profile: Reduced mechanical trauma in sub-centimeter channels.
Bench-validating these navigation dynamics on anatomical models is the critical first step toward proving cross-disciplinary feasibility.
"Getting close to a 90 degree turn there."
That's not a physician. That's a device rep, on camera, first time putting a microwire through our MicroNav™ model. Nobody scripted it. He just narrated what he was feeling as the wire hit the bend.
Forty seconds later: "Yeah. So pretty amazing stuff." Here's why that reaction matters more than any spec sheet.
A guidewire's real differentiator is invisible in a straight vessel. Torque response, distal trackability, tip shape retention, kink resistance — every wire on the market claims all four, and on a straight silicone channel every wire delivers all four. They look identical.
The differences only appear where the anatomy stops cooperating. The branch coming off at a near-right angle. The vessel tapering below a millimetre exactly where the turn is. The point where the wire either follows your torque or straightens out and sends you back to reselect.
MicroNav™ is built to be that place. Transparent, sub-millimetre distal branches with genuinely acute takeoffs. You watch the wire fail or succeed in real time — no fluoro, no inference from a radiopaque marker, just the wire and the turn.
Same problem, every discipline:
→ Neuro — distal access, small-vessel embolization, feeder navigation
→ Interventional radiology — prostatic, genicular, uterine and bronchial embolization, where the targets are small and the takeoffs are unforgiving
→ Cardiology — CTO crossing, septal collateral channels, retrograde work
→ Peripheral — below-the-knee, tibial-pedal, pedal arch access
Sub-millimetre navigation through an acute angle is the same technical problem whether the vessel is in a skull or a foot.
For guidewire and microcatheter companies: this is where your product actually demonstrates. Congress booths, KOL sessions, proctoring, field team training, internal R&D comparison. Repeatable, transparent, angio-compatible — and hard enough that performance differences are visible to the person holding the wire.
For interventional programs: the operator builds the reflex here, not on the patient.
📤 Order patient-specific: https://t.co/4dN46D9V4a
🔗 https://t.co/T3nOXikjj7
#Guidewire #Microcatheter #MicroNav #Neurointervention #InterventionalRadiology #InterventionalCardiology #PeripheralIntervention #EndovascularTraining #MedTech
It starts as a stack of DICOM files — a CT or MRI, uploaded through our portal (https://t.co/4dN46D9V4a) from anywhere in the world, nothing about it yet resembling an object you could hold.
From there, our engineering team goes to work: automated segmentation of the vessel walls, tracing the exact tortuosity and branching of that specific patient's anatomy, reconstructing it into a 3D model that keeps the real geometry intact rather than smoothing it into a realistic average. This is the part most people never see — a scan becoming a shape, one vessel at a time, built to move fast because a research timeline or a trial enrollment window usually doesn't wait.
What comes out the other side is a physical, transparent vascular model — the same aneurysm or lesion that showed up on the original scan, now sitting on a bench, ready for a catheter, a device, or a set of hands that have never worked this exact anatomy before. For a device company validating a protocol or a program building investigator competency, that's the gap this closes: not a generic phantom, but the real case, reconstructed and ready before it becomes a live procedure.
Precision models. Stronger outcomes.
Upload your DICOM data: https://t.co/4dN46D9V4a
#ClinicalTrials #MedicalDevice #DeviceValidation #PatientSpecificModels #VascularModels #ClinicalResearch #MedTech #InvestigatorTraining #SurgeonsLab
A WEB doesn't sit in the parent vessel. It sits inside the aneurysm. That changes everything about how you deploy it.
Unlike a flow diverter or stent-assisted coiling, the WEB is a single self-expanding mesh that goes into the sac itself. It seals the neck from within and creates flow stasis leading to thrombosis. No metal across the parent vessel means no dual antiplatelet therapy — part of why it earns its place in wide-neck bifurcation aneurysms where a flow diverter is harder to justify.
That structural difference makes deployment its own skill. Not stent technique. Not coil technique. Its own thing.
Getting the microcatheter to the aneurysm is the routine part. The case is decided by what happens after release: how the device opens inside a sac that rarely matches its shape on the sizing table, where it settles relative to the neck, and whether the construct is actually sealing before the catheter comes out. In a bifurcation aneurysm with a difficult dome-to-neck ratio, a device that looks well-placed on the first pass can still be wrong.
Sizing is where most of that judgment lives — and sizing judgment comes from having seen the device behave in enough different sacs to know what you're looking at.
Our aneurysm model gives you that repetition.
Transparent anatomy, so you watch the mesh open against the wall instead of inferring it from a radiopaque marker. Pulsatile flow. Real wall resistance. The full sequence — navigate, position, release, assess the construct — repeated until the assessment is reflex.
Intrasaccular-device-agnostic and fluoroscopy-compatible. WEB, Contour, Artisse — the model runs in the angio suite with whatever platform your program or your field team trains on.
For neurointerventional programs: upload the DICOM of the case you're doing next month at https://t.co/4dN46D9V4a and we'll build the model from that patient's anatomy. Rehearse the actual bifurcation, not a generic one.
For intrasaccular device manufacturers and clinical training teams: physician training is an IFU requirement here, and most of it still happens on animal models, cadavers, or a proctored first case. This is repeatable, transparent, and patient-specific — for proctoring programs, KOL sessions, congress demos, and field support training.
Practice the procedure. Be ready for the patient.
🔗 https://t.co/wUm23loYlt
#WEBDevice #IntrasaccularDevice #Neurointervention #InterventionalNeuroradiology #WideNeckBifurcationAneurysm #Neurovascular #EndovascularTraining #MedTech