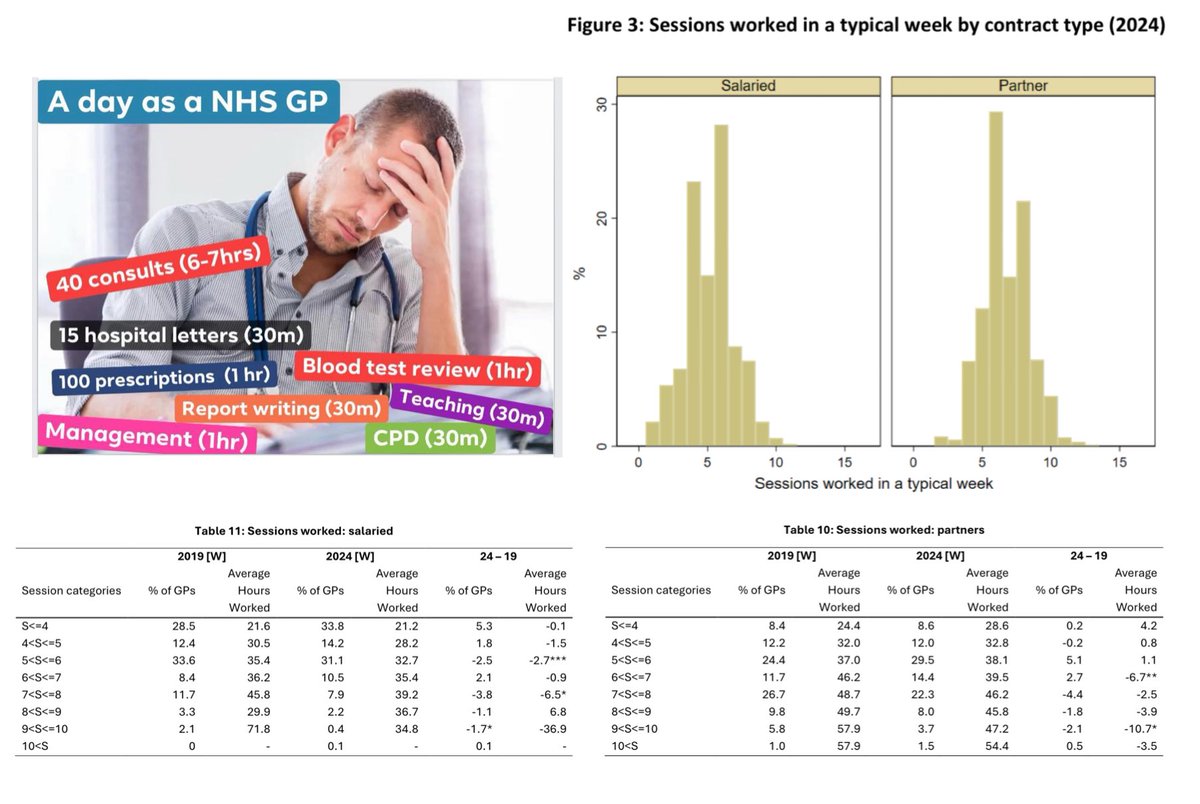
This is absolutely insane.
Short sighted penny pinching will undoubtably change or end the lives of patients that rely on the hospital leaders to look after them
If this is "normal" staffing at Arrowe, how can we trust they they will maintain patient care next week?
Most people assume that if the NHS needs more specialist doctors, the Government would train more of them.
But that’s not actually what’s happening.
The Government can decide how many specialist training jobs exist each year. They can increase them, reduce them, or remove them entirely. These numbers are a political decision.
So when the Government removes 1,000 future NHS specialist training jobs, that is an active choice to have 1,000 fewer future NHS specialists.
That means fewer potential radiologists reading scans.
Fewer potential surgeons doing operations.
Fewer potential anaesthetists running theatres.
Fewer potential psychiatrists and GPs seeing patients.
At a time when waiting lists are in the millions and patients are waiting months or years to see specialists, the Government has actively chosen to reduce the number of future specialists.
That doesn’t just punish doctors. It punishes patients and the NHS as a whole, because it means fewer potential specialists and longer waits in the future.
And the most concerning part is why this happened. These training jobs were discussed in the context of negotiations with doctors. That means specialist training jobs, and therefore future NHS specialists, were being treated as something that could be added or removed depending on whether doctors accepted Government terms.
That is not workforce planning.
That is using future NHS specialists as leverage.
The Government can create more NHS specialists if it wants to.
It can reduce waiting lists faster if it wants to.
It can train more doctors if it wants to.
Yet they’ve chosen not to.
This was a political choice that this Labour Government have made.
https://t.co/BMjkh5GwXD
Despite a year of warnings that strikes would harm patients, ministers have scrapped 1,000 desperately needed NHS training posts to punish doctors for taking industrial action
https://t.co/Li8gdElglc
We never rejected the 1000 places.
We rejected an offer that fails on pay, tried to lock us into below inflation deals, is full of vague promises for LEDs, and we worry you can’t deliver it.
Stop tweeting. There’s still time for a credible offer to call off these strikes.
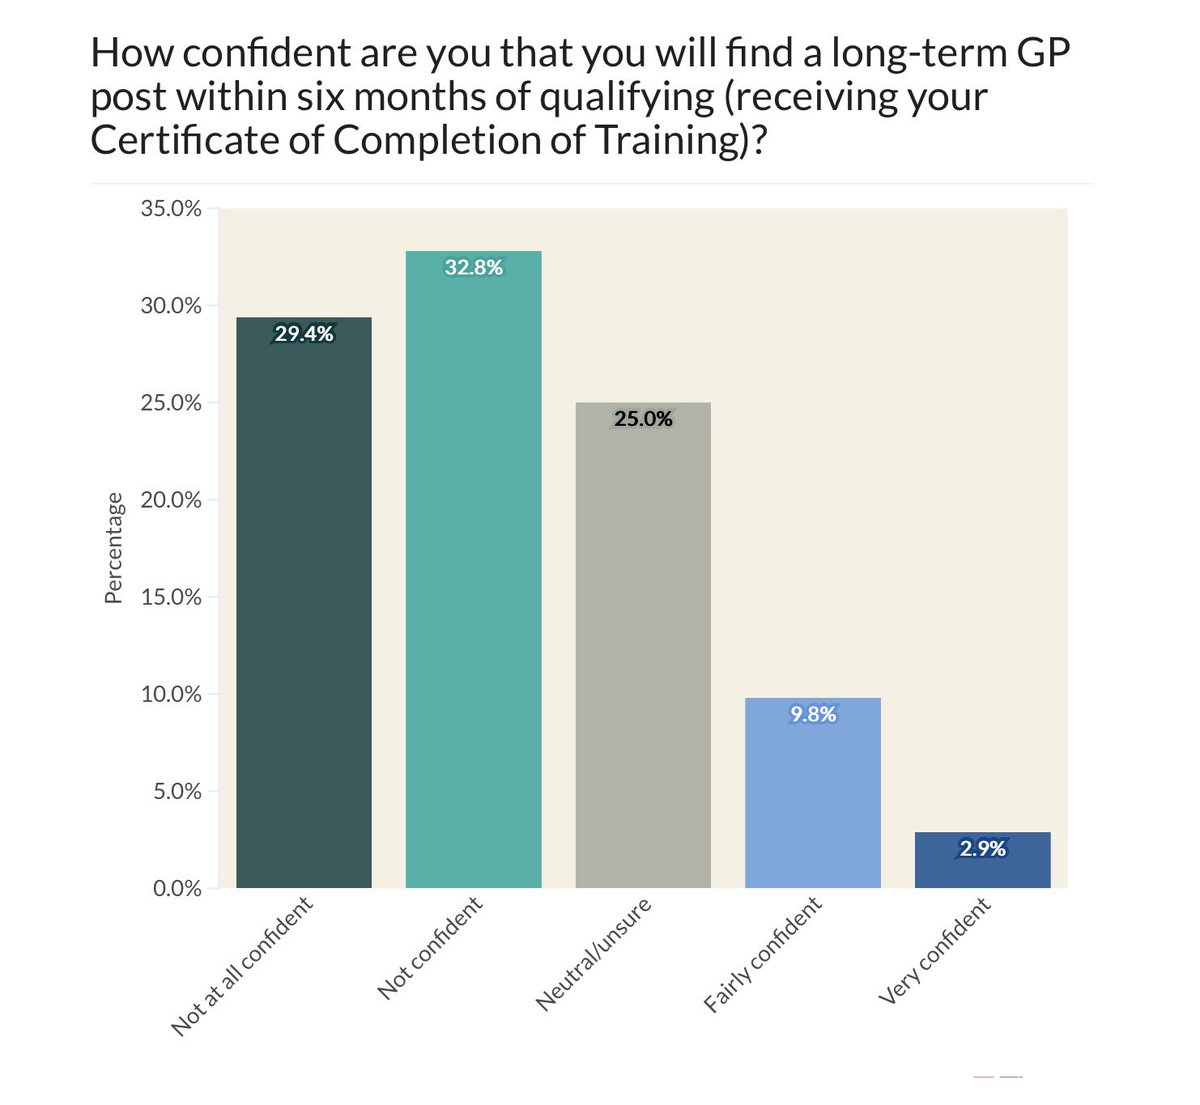
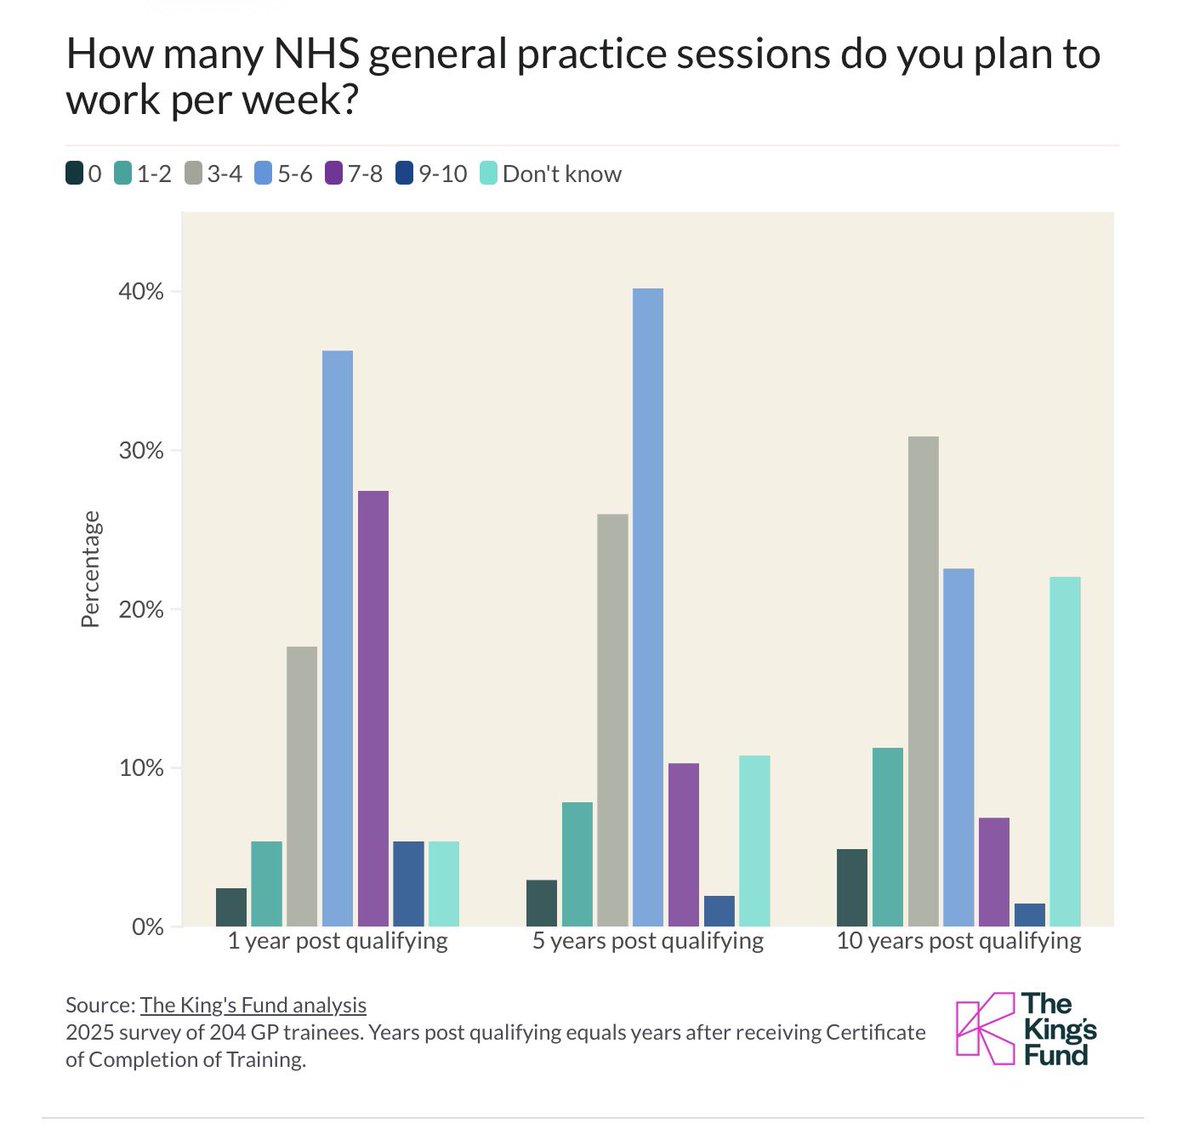
The GP employment paradox: why GP trainees are worried about finding jobs in a system short of GPs
Most see struggles ahead
That’s great for the future @wesstreeting
https://t.co/N9fKkZC7CY
Weird thing about Travelodge comms:
‘They followed procedures correctly’ = WORST possible message.
Implies anyone staying in any Travelodge can expect staff to hand out room keys in the middle of the night to anyone who knows your name.
Doubt that was the crisis comms goal.
A consultant Gynaecologist is unable to work at a GP practice and prescribe contraception as they would be deemed not qualified.
Yet a pharmacy technician can start and continue it from Boots on the high street.
This feels more like money laundering than actual healthcare.
@dave_dlt Are they required to sit down for 10 minutes by themselves, in a comfortable chair, in a quiet room, with no interruptions (including their own phones)? If not then a random drive-by BP is pointless!
Can anyone tell me, is there evidence for random BP checking in pharmacies? The bulk of the (unfunded) work this (funded) service generates for GP surgeries appear to be extremely fit and well young adults who have a single high reading???
Seems not very productuve.
Our complaint against Lord Chadlington has been upheld.
He has been suspended for 1 year. We welcome his decision to step down.
However long it takes, we will continue pursuing accountability for figures who abused their positions during the pandemic.
https://t.co/8kQnVPYGUJ
Have physician associates done more harm than good?
In a word: Yes.
It’s an unmitigated disaster, on a scale larger than any other healthcare scandal. Including Shipman!
@thetimes
https://t.co/hIOHEdkaOi
Yet the Government isn’t being investigated for allowing #NHS Dentistry to die
That’s why Private Dentistry exists it’s simple @wesstreeting
(General Practice will be next)
Our GPs committee in England has voted to REJECT the Government’s plans to impose changes to GP practice contracts.
We’re calling for the Government to directly negotiate a new practice contract, as promised repeatedly by Secretary of State Wes Streeting. https://t.co/3NUMLCPkVR
GP Referrals cannot be blocked by NHS Trusts due to Jess’s Rule
https://t.co/2jreIvVyly
The new GP contract stipulation of the use of Advice & Guidance pre-referral is null and void
Add to any referral ‘In accordance with Jess’s Rule & Patient choice’ #TeamGP
Thoughts?
Private equity is buying hospices. What happens in the US will arrive here.
Palliative care and impending death is seen as a profit opportunity.
PE destroyed care homes and vets. Patient deaths have risen in PE owned hospitals and nursing homes.
https://t.co/AE9EjWSfcM
This isn’t “fixing the front door of the NHS.” It’s setting it on fire.
You can’t demand unlimited same-day urgent care AND unlimited routine care with no extra funding, no extra workforce, and crumbling premises.
https://t.co/WXqnpKXwGf
This is a surprising piece of economic illiteracy from the normal sensible @JimBethell - you can see here that NHS funding has been inadequate (in historical terms) for over 25 years https://t.co/DUKbZIwgbx 1/2
“For every transfer of activity to the private sector, you are undermining the public sector…you’re undermining the NHS”
🎯 @DrTonyOSullivan is spot on.
Invest and build up our NHS so it can treat everyone.