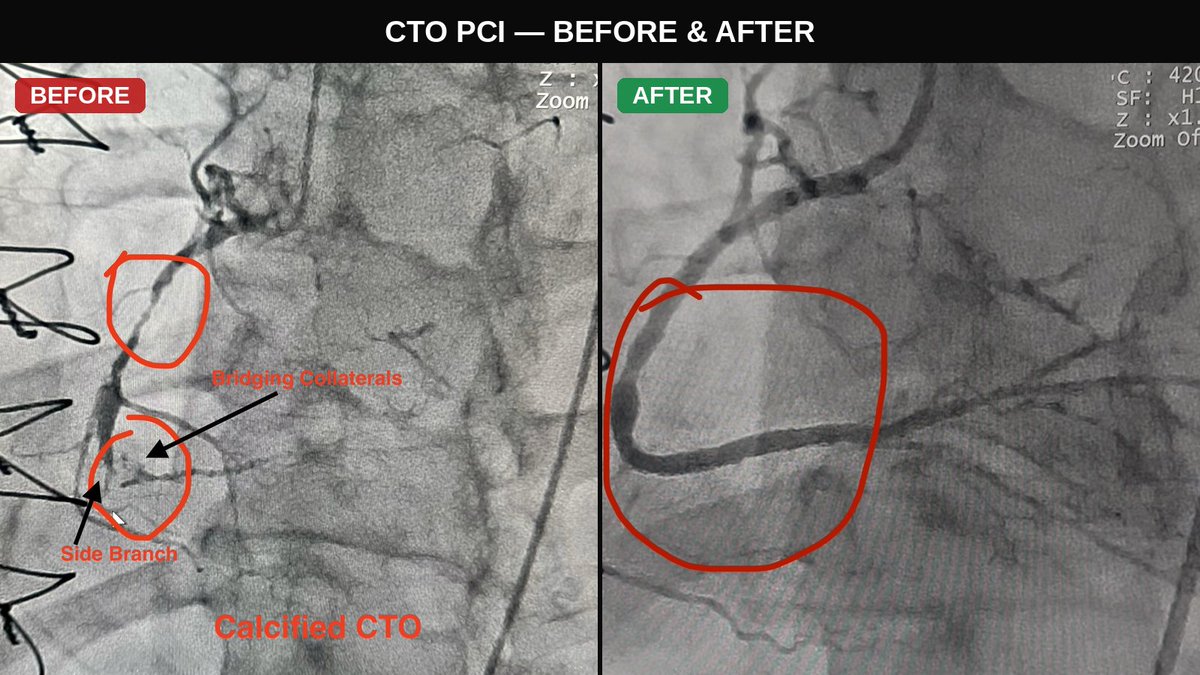
@realarainmd Agreed — clearly I need to level up my #HDR-Twitter skills from you, @realarainmd. 😂 I tried improving the image quality, but Twitter keeps humbling me by reverting it to potato mode every time I post. 🥔📸. Thank you for all your coaching @realarainmd!
Pt: late 50s, previously active, one wk SOB.
LVEF 15%.Transferred for high-risk PCI.
On arrival, CMR viable LCX and diagonal, but transmural scar distal LAD—small apical LV Thrombus.
>> Turned down for CABG.
Angiogram from referring attached below.
What would you do?
• IMPELLA OFF-LABEL USE: ECMELLA.
It is one of the most common off-label uses of Impella CP.
Although not FDA-approved, LV unloading during VA-ECMO has become common practice in experienced shock centers, particularly when left ventricular distension is detected. #impella
@realarainmd@grok@girishviswa Wow we might have to cath lab consult @grok when @realarainmd is out of the country lol - I have had good success with 50:50 laser on contrast approach when even microcatheters won’t spin across the lesion. I always use a trap to make sure push out blood when using laser.
What’s YOUR next move?!
@Grok may well be the wisest #CTOPCI guru to have never set a foot in the cath lab! 😂
A great f/u question. My 1st move is almost always to build up support. This is by far the most common reason devices won’t cross.
Option #2 is modify the cap/plaque.
Is even mild PVL no longer acceptable in #TAVR?
Our editorial on the #OCEAN-TAVI trial is now published in JACC: Interventions.
https://t.co/SFiZArziLp
RTIG Cap Puncture Tutorial
Here is a ‘self learning’ real time IVUS guided cap puncture tutorial as requested by several colleagues.
It has two parts - one for the angio and another for the IVUS. The primary operator usu. goes back and forth bet. them in real time.
Questions, comments and suggestions welcome!🙏🏼