Intraoperative adverse events occurred in 41 of 478 patients (8.6%) undergoing robot-assisted minimally invasive esophagectomy, and 92.7% were managed robotically without conversion. https://t.co/bhI5KVonZn
Thoracic / Chest phase in a total thoracolaporoscopic three stage oesophagectomy + feeding jejunostomy , total operative time 5 hours and 30 min, length of stay 11 days. Histopathology T3N0 40 LNs, today seen 3 months post op, feeding Jej removed as patient is tolerating orally well 🙏🏻
Surgical Anatomy of Thyroid - Every Triangle in One Diagram 🔵🟠🟣
This diagram is not one triangle, it's 7 danger zones. Here is what you must know:
#SoMe4Surgery#MedTwitter#ThyroidSurgery
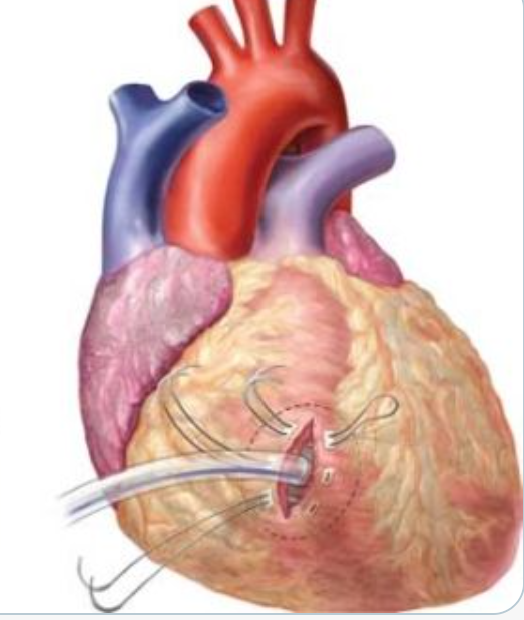
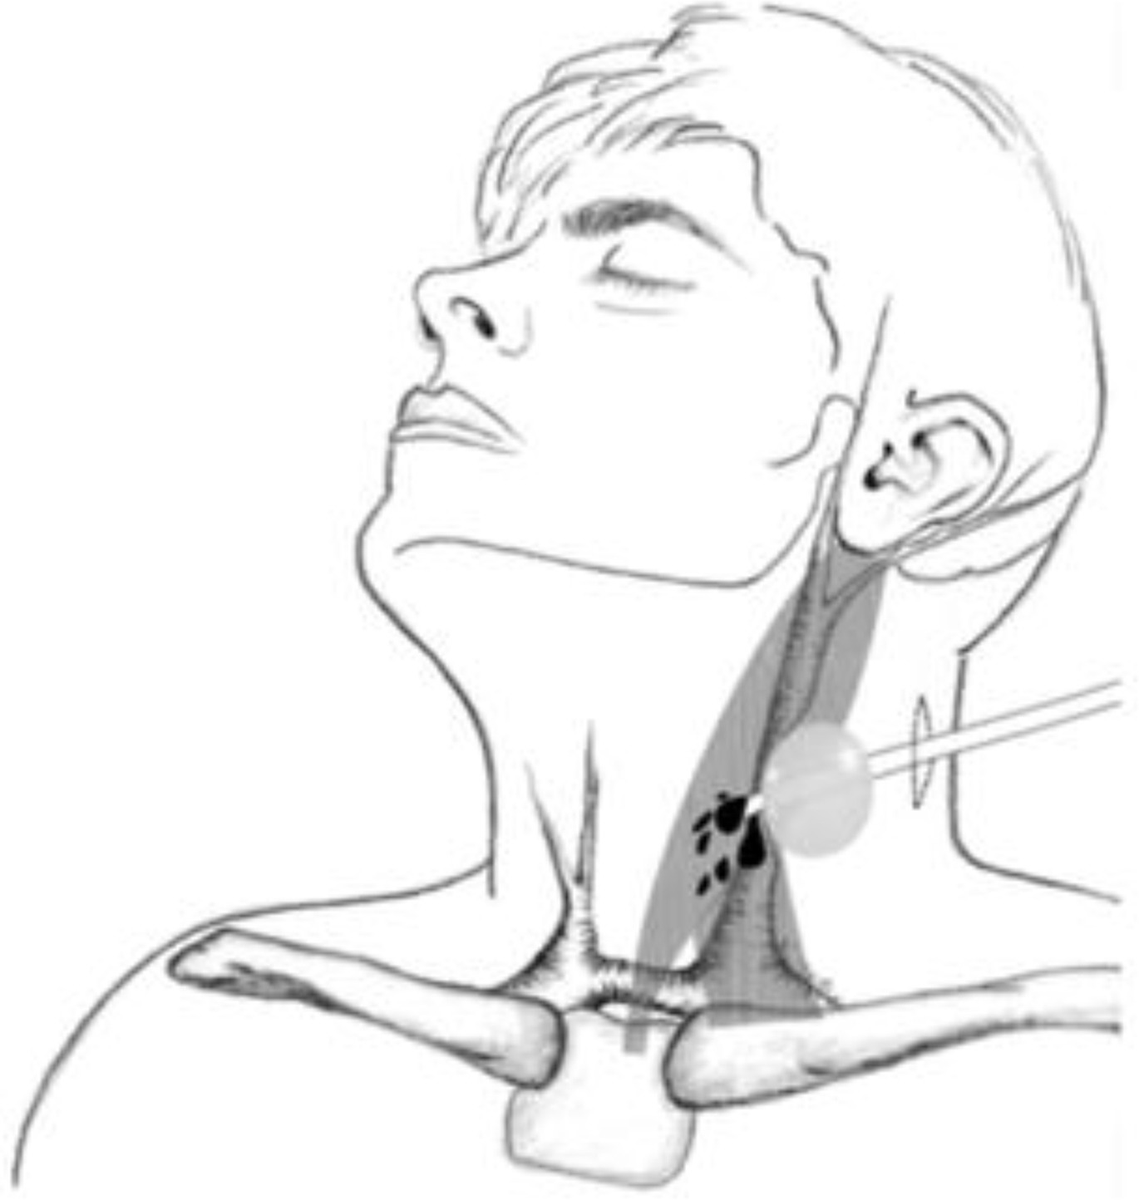
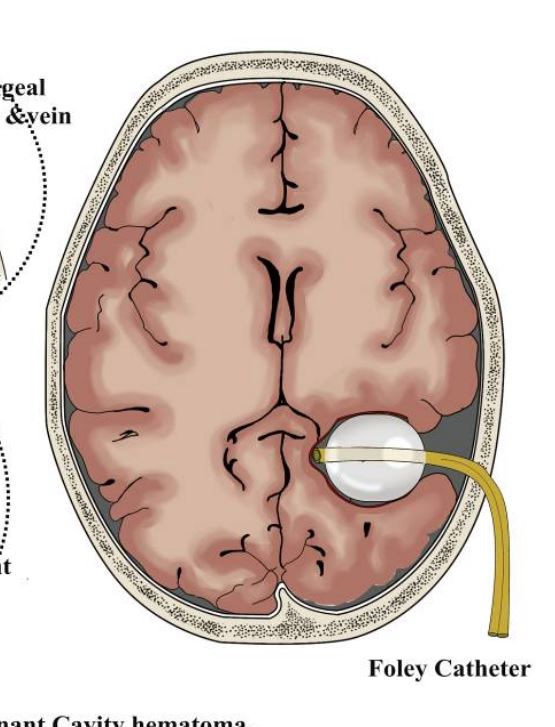
Many of my followers are urologists, and I'm talking with some of them this week, so I thought they might appreciate one of my early 🧵on the novel ways that Foley catheters have been used *other than* for draining the bladder. 🧐
When safe entry goes wrong
This video shares a small-bowel injury during port insertion for laparoscopic nephrectomy. It is a difficult complication to discuss, but an important one to learn from.
Previous abdominal surgery can leave bowel adherent beneath a port site that appears suitable. The case reinforces the need to plan entry carefully, recognise an injury early, assess the bowel, and manage the injury in a controlled manner.
Shared with patient consent and respect for everyone involved. Open discussion of complications helps us improve patient safety.
#PatientSafety #SurgicalEducation #LaparoscopicSurgery #Urology #Nephrectomy
𝙇𝙖𝙥𝙖𝙧𝙤𝙨𝙘𝙤𝙥𝙞𝙘 𝙍𝙚𝙥𝙖𝙞𝙧 𝙤𝙛 𝙋𝙚𝙧𝙛𝙤𝙧𝙖𝙩𝙚𝙙 𝘿𝙪𝙤𝙙𝙚𝙣𝙖𝙡 𝙐𝙡𝙘𝙚𝙧 𝙬𝙞𝙩𝙝 𝙋𝙧𝙞𝙢𝙖𝙧𝙮 𝘾𝙡𝙤𝙨𝙪𝙧𝙚 & 𝙊𝙢𝙚𝙣𝙩𝙖𝙡 𝙋𝙖𝙩𝙘𝙝
Presentation:
🔵1 day history of sever upper abdominal pain
🔵Smoker and excess ETOH
🔵CXR
➡️Pneumoperitoneum
🔵CT
➡️Perforated duodenal ulcer
🔵Time from ED➡️theatre 3 hours
Operative Approach:
🔴Thorough peritoneal lavage
➡️Lap washout allows for thorough removal of intra-abdominal contamination
➡️Modern OR table tilting can provide better view then open in select cases
🔴If fragile tissue then omental patch only
➡️This approach is a modified version of Grahams patch repair
➡️When suitable, we prefer primary closure with patch after
🔴For large perforations kocherisation of duodenum may be indicated
🔴Convert to open if:
➡️Large ulcer
➡️Associated ulcer bleed
🔴H. Pylori eradication therapy on discharge
🔴OGD in 6-8 weeks to confirm healing
Key Points:
🟢Timely intervention critical
🟢Lap approach in EGS should be encouraged
🟢Compared to open, advantages of lap are:
➡️Reduced pain
➡️Reduced LOS
➡️Reduced incisional hernia rate
🟢Trainees should be exposed to lap EGS early to develop skills and confidence
#FOAMed #GITwitter #MedEd #SurgEd #EGS #SoMe4Surgery
The future of surgery is single...port 🤖
Exciting times ahead for robotic surgery.
I’m incredibly impressed by the capabilities and versatility of this machine. Just imagine the possibilities!
In a multicenter study, investigators developed and externally validated the Diabetes Remission Index (DRI) and Weight Loss–adjusted DRI (W-DRI), new prediction tools designed to estimate type 2 diabetes remission following metabolic and bariatric surgery. https://t.co/cFNIgmfgf7
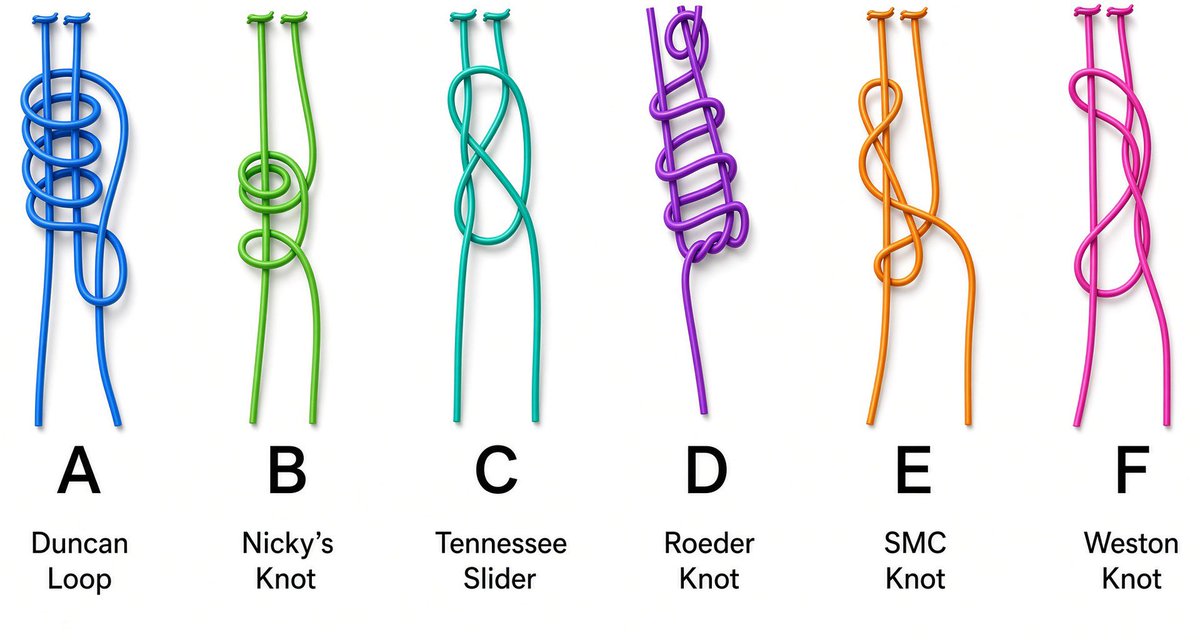
🧵regarding the 'figure-of-eight' suture. I did a similar one 3 yr ago, but the students and interns are new.
We'll go over the surgical application of the 'figure-of-eight' stitch, some technical pointers, and compare it to a similar stitch (the' horizontal mattress').
(1/ )
You never know when you will need to perform LOWER EXTREMITY FASCIOTOMY 👇🏼👇🏼
Be prepared. DOMINATE THE DAY.
From our TRAUMA SURGERY VIDEO ATLAS ➡️https://t.co/gPhJG6czV1
@georgoff@Kniery_Bird@mcclellanjm@clarkninam