🧠💉 ¿Quieres aprender Terapéutica del Dolor desde las bases?
En AnalgoHipnosis estamos construyendo un curso paso a paso: fisiología, farmacología y manejo clínico, explicado de forma práctica y basado en evidencia.
🎓 Visita nuestros canales
https://t.co/9Al1rv9IyF
@cajurite@b_cartera Hola, me parece muy interesante el mundo de las opciones, estoy formándome sobre el tema, me podrían aconsejar algún texto o curso donde se hayan formado, gracias
Se acaban de actualizar las guías de Fibrilación Auricular (FA) de la European Society of Cardiology (ESC), que reemplazan a las del 2020. Vamos a sintetizar lo más importante de las más de 100 páginas. 👇
💚💙 𝐅𝐞𝐥𝐢𝐜𝐞𝐬 𝟒𝟖𝟖 𝐚𝐧̃𝐨𝐬, 𝐦𝐢 𝐂𝐚𝐥𝐢 𝐪𝐮𝐞𝐫𝐢𝐝𝐚 🫶
Que el calor y la alegría de nuestra gente sigan bailando al ritmo de la salsa y los sabores típicos de nuestra tierra. 🔥
#Cali488#CumpleañosCali
@chileanestesia La estabilidad hemodinámica y el mantenimiento de la ventilación espontánea te permite brindar un acto anestésico de mayor seguridad, además se ha convertido en un As bajo la manga en pacientes ASA III/IV
@FH_Verbrugge discusses the top 10 diuretic mistakes at #HR24 .
If you prescribe lasix you need to read these key mistakes👇
10 Diuretic mistakes 🧵
#1: Not getting the job finished.. don't stop diuresis too early. If you fail to decongest, outcomes are worse and there is a higher risk of readmission to hospital.
#2: Being distracted by serum Creatinine.. rising Cr does NOT indicate dying kidneys!!
#3: Giving oral loop diuretics for in-hospital pts. with clear fluid overload (instead of IV diuretics)...
When dosing loop diuretics, there is a threshold effect that until above that you get no effect, and then a ceiling effect where any more diuretics don't increase diuresis.
#4: Underdosing (loop) diuretics and compensating with increasing maintenance outpatients doses instead.
Lasix dose = 1-2 times oral maintenance dose only makes sense IF the maintenance dose was appropriate... might not be the best place to start.
Does house of god (book) have it right? Adjust based on GFR. If you have poor kidney function need higher dosing... general gestalt
GFR>45 --> 80 IV lasix
GFR 30-45--> 120 IV lasix
GFR <30 -->120 IV lasix
#5: Too infrequent dosing of loop diuretics
LaSIX --> lasts six hours.
If you dose too infrequently then you get Na resorption in-between diuretic doses.
Start BID or TID with Lasix, not once daily! (sometimes even QID)
#6: Using loop diuretic drips (No lasix infusions!)
Higher plasma-renin activity with diuretic infusions...
#7: Failure to recognize fluid overload when cardiac filling pressures are normal / not terribly elevated
You can be overloaded with normal filling pressures. Volume does NOT equal pressure.
If overload + high filling pressures --> diurese fast
If overload + low filling pressures --> diurese slow
#8: Mistaking one size fits all for diuretic resistance
Steps to treat diuretic resistance:
1. Maximize Loop Diuretic
2. Add thiazide like diuretic (e.g Metolazone)
3. Add other nephro segment blocker (Acetazolamide, Spiro, Empagliflozin, Amiloride)
4. Consider hyperdiuresis (3% saline with diuretics)
5. Consider diuresis
#9: Don't be afraid of combination diuretic therapy
ADVOR trial: acetazolamide added to loop diuretic improved decongestion. We need to start thinking about multi-modal diuresis!
#10: Don't mistake decongestion for dehydration
Decongestion is about removing sodium.
Positive sodium balance with net fluid loss still portends worse survival (Hodson et al 2019).
#echofirst #Cardiology #medtwitter #foamed #foamcc #pocus #physiology
The key is in the pee
Check urine sodium concentration 1-2 hours post diuretic ... want a urine Na > 100 ideally (<80 is diuretic resistance)
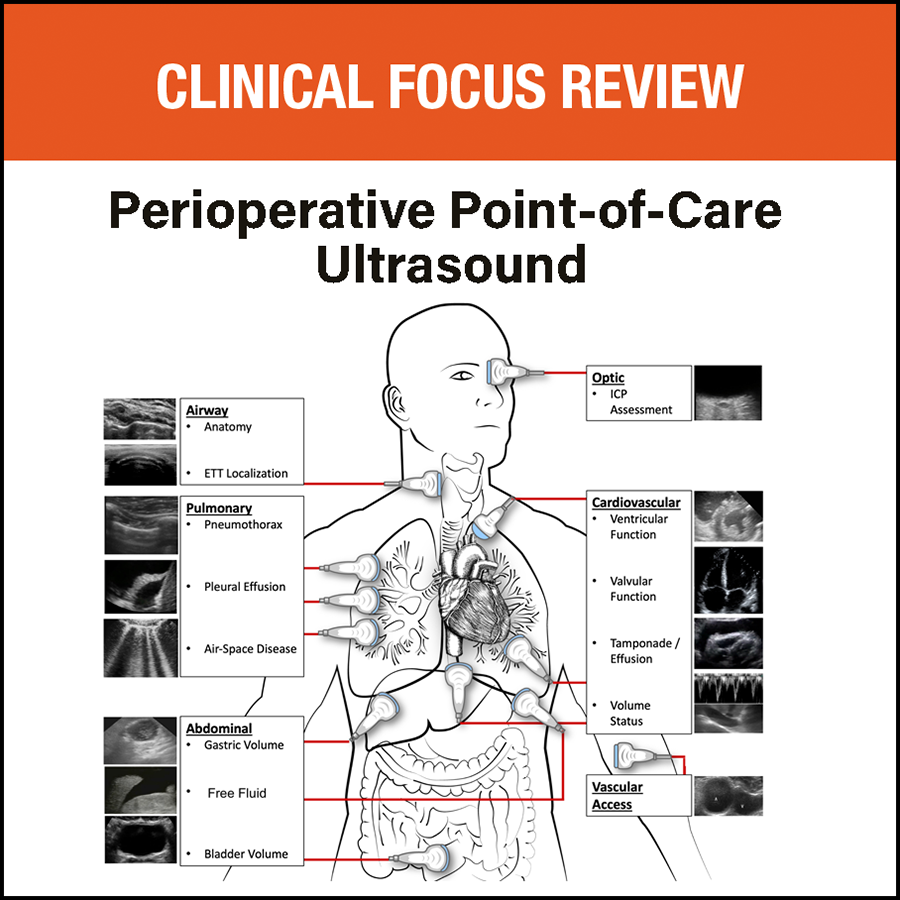
Tackling a topic relevant to all #anesthesiologists, authors highlighted the clinical utility, technology advancements, training/certification, education, reporting/billing, and limitations of perioperative point-of-care ultrasound. Read the article: https://t.co/WyNw79n5qg
👴🚩NO ES EL ENVEJECIMIENTO, ES EL SEDENTARISMO.
🙌🏻En comparación con las personas jóvenes activas, las personas mayores activas mantienen:
🟰 Misma cantidad de fibras musculares.
🟰 Misma cantidad de células satélites.
El factor clave no es el envejecimiento, es el hecho de entrenar vs no entrenar.