🩸 ASH iron-deficiency guidelines: a concern from the cancer/BMT clinic.
Cancer, CAR-T, HCT & GVHD patients can have high ferritin but severe iron-restricted erythropoiesis. ASH recognizes that inflammation can make stored iron unavailable. bloodadvances.2025015950.pdf
TSAT <20% gets my attention.
<15% worries me.
<10% + anemia? I strongly consider iron despite high ferritin.
Dialysis taught us: stored iron ≠ available iron.
Don’t let ferritin alone deny patients iron they may need. 🩸
You want to know more about how to treat chemotherapy induced thrombocytopenia with thrombopoietin receptor agonists?
@BloodPortfolio has you covered...
https://t.co/JzgV1qQaFn
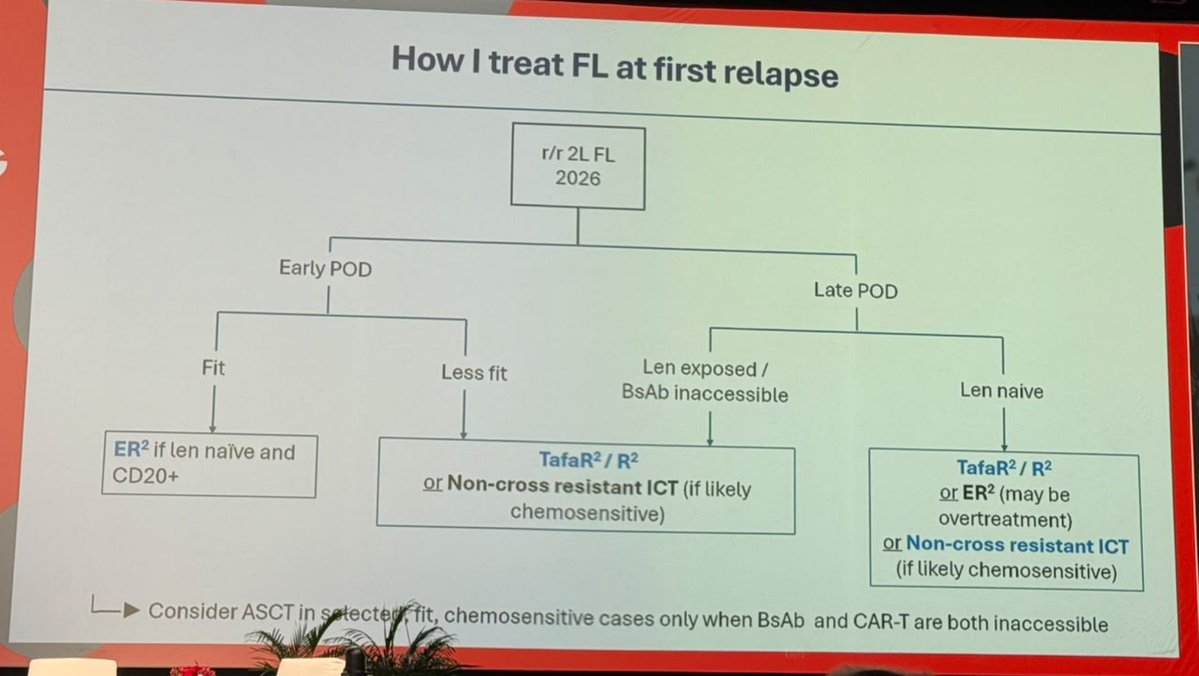
🧬 No more chemo for follicular lymphoma?
FL is an immune-responsive disease.
Immune modulation → immune amplification → T-cell redirection
R² became the backbone. Add CD19 targeting with tafasitamab or CD3×CD20 T-cell engagement with epcoritamab, and responses deepen, even in anti-CD20-refractory disease.
The future may be less chemotherapy, and more intelligent immunity. ⚡
#FollicularLymphoma #Immunotherapy #Medtwitter
#MyelomaTips: I have seen several referrals recently for myeloma based on isolated incidental finding of hypercalcemia.
➡️Isolated hypercalcemia is rarely myeloma.
➡️If hypercalcemia is the only abnormal finding with no anemia, renal impairment, or bone lesions; myeloma is an unlikely explanation.
➡️In iStopMM (n=2,546 MGUS pts), only 3% with persistent hypercalcemia had MM and every single one also had bone lesions/other CRAB features (Blood 2022;140:10099)
➡️Look elsewhere before anchoring on MM.
#MedTwitter #MultipleMyeloma #MMSM #MedEd
Cellular and bispecific therapies show promising activity for CNS myeloma, whereas IT therapy appears to have limited efficacy. CNS myeloma is rare, aggressive, and strongly associated with high-risk cytogenetics and multifocal EMD. Read in Blood Advances: https://t.co/mRC6limT6Y
Early Safety and Feasibility Results from a Phase II Trial of De-Escalated Ptcy and Ruxolitinib for Gvhd Prophylaxis in Older Patients Undergoing Reduced Intensity Conditioning Allogeneic HCT | Blood | American Society of Hematology https://t.co/P0rVIpU95G
High response rate (ORR 56%, CR 42%) and durable CR (1‑year DoCR 75.7%). Primary refractory/early relapsed disease, ECOG PS of >1, and bulky disease of ≥7.5 cm predicted lower CR rates and shorter PFS. Read the article in Blood ICT: https://t.co/rXe2RVodmn
#Hematology Barriers to Patient Referral and Completion of #CARTCell Therapy for Relapsed/Refractory Large B-Cell #Lymphoma#lymsm https://t.co/31nrknsqos
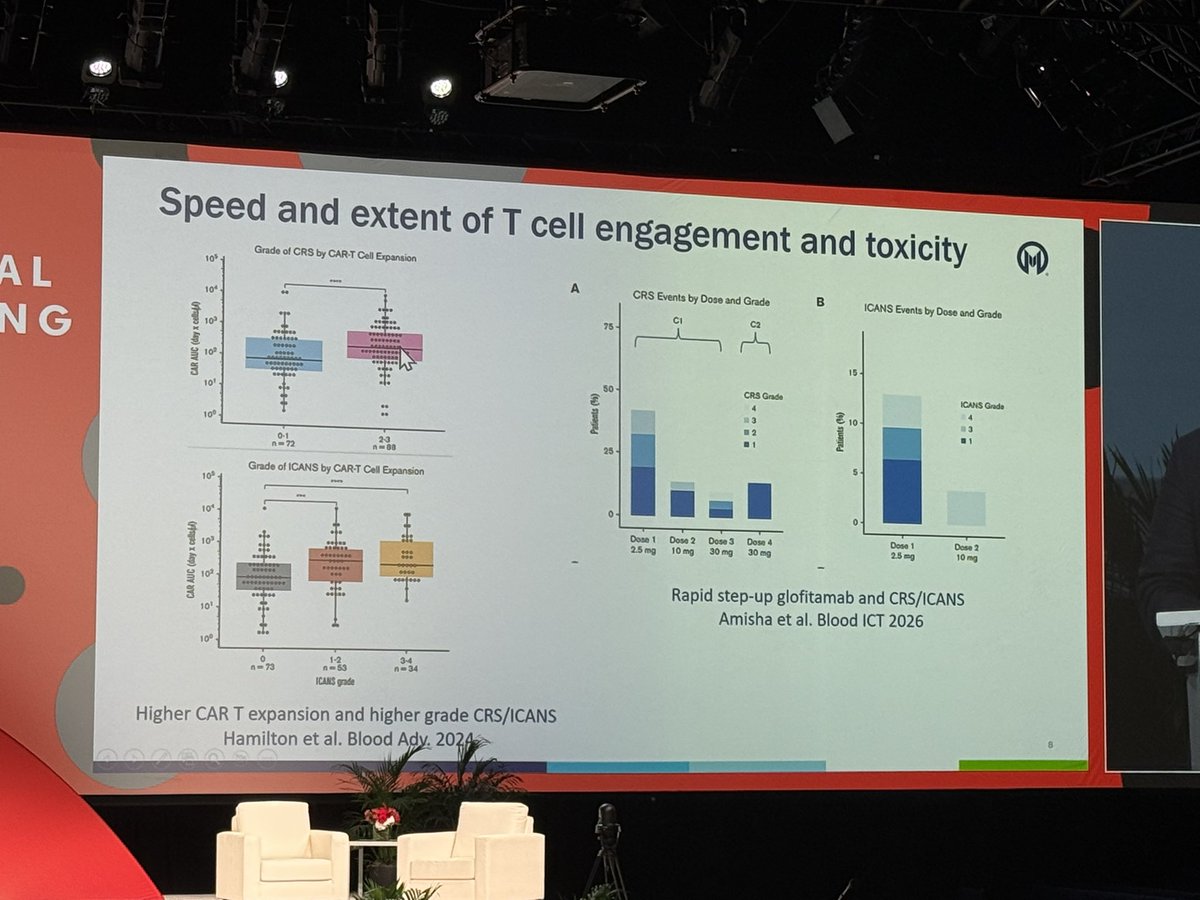
🩸🛡️ Preventing CRS & ICANS after CAR-T and bispecific antibodies: intervene before toxicity escalates!
1️⃣ BIOLOGY MATTERS
Greater CAR-T expansion is associated with more severe CRS/ICANS. With bispecifics, toxicity often clusters around initial step-up doses.
📌 Reducing CRS does not necessarily prevent ICANS—assess each separately.
2️⃣ BEFORE CAR-T
🔹 Refer early.
🔹 Optimize disease burden with appropriate bridging.
🔹 Consider product-specific toxicity alongside efficacy and eligibility.
🔹 Establish baseline neurological assessment and a monitoring plan.
🧠 The slide’s “4-1BB less toxic than CD28” is a broad observation; the complete product and patient context matter.
3️⃣ PROPHYLAXIS: PRODUCT-SPECIFIC EVIDENCE
💊 ZUMA-1 cohort 6 studied dexamethasone 10 mg orally daily on days 0–2, starting before axi-cel infusion, alongside earlier toxicity intervention.
✅ Severe CRS was uncommon, without an apparent loss of efficacy—but this was a nonrandomized cohort, not a universal CAR-T prophylaxis regimen. ZUMA-1 cohort 6
🧪 Other approaches under investigation:
• Prophylactic anakinra
• Fractionated CAR-T dosing in selected B-ALL protocols
• Concurrent BTK inhibition in selected settings
• JAK1 inhibition with itacitinib
These require protocol-specific interpretation. Anakinra phase II | Itacitinib phase II
4️⃣ BISPECIFIC ANTIBODIES
🔹 Follow approved step-up dosing and steroid premedication.
🔹 Obinutuzumab pretreatment is part of the glofitamab schedule.
🔹 Individualize inpatient/outpatient monitoring.
🔹 Prophylactic tocilizumab has emerging evidence, including in myeloma; applicability varies by agent and protocol. Tocilizumab prophylaxis study
5️⃣ WHEN TOXICITY DEVELOPS
🌡️ CRS: prompt tocilizumab ± corticosteroids according to grade, trajectory and product guidance.
🧠 ICANS: corticosteroids are central when treatment is indicated. Tocilizumab does not treat isolated ICANS; use it for concurrent CRS.
🚨 Persistent or worsening toxicity:
Reassess for infection, disease progression and alternative causes; escalate supportive care, corticosteroids and selected rescue therapy such as anakinra with the cellular-therapy/ICU team. Jain, Smith & Shah—Blood
#CART #BispecificAntibodies #CRS #ICANS #SOHO26 #ASH26
Aza-Ven vs Induction: What Changes in Our Clinical Practice?
Beautiful paper!
1. Fit ≠ automatic 7+3.
In selected non-favourable-risk, FLT3-wild-type AML, Aza-Ven is now a reasonable frontline option.
2. Get molecular data early.
CBF AML, FLT3-mutated AML and younger NPM1-mutated AML were excluded SO this is not a blanket replacement for induction.
3. Think transplant from Day 1.
HCT rates were 60% with Aza-Ven vs 40% with induction.
4. Huge relevance for Indian resource constraints.
First 30-day inpatient stay: 12.5 vs 27.3 days; ICU use: 0% vs 10%.
5. Low intensity ≠ low toxicity.
Cytopenias remain significant, but grade ≥3 infections and bleeding were lower with Aza-Ven.
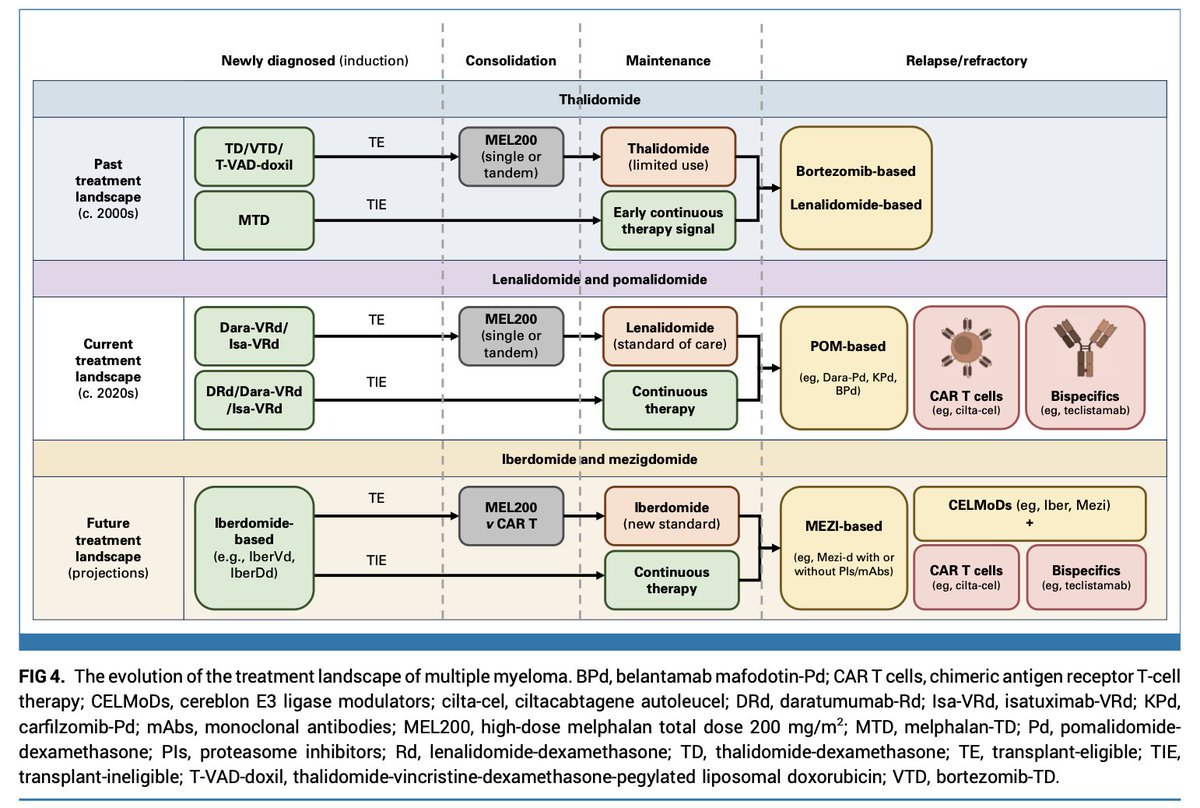
Nicest graphic I've seen on this! Excellent @JCO_ASCO review of IMiDs ➡️ CELMoDs in myeloma over time.
Easy to think of CELMoDs and TCEs as foes in this space, e.g. Iber-Dd vs tec-dara.
But in reality, most CELMoD use will likely be as maintenance after/with TCEs (or ASCT)!
We bank stem cells for the future. Why not bank T cells before we ruin them? 🧬🧊
New Blood data suggest CAR-T fitness may already be imprinted before manufacturing, with fitter CD4 T-cell states linked to more durable ide-cel outcomes.
Moffitt adds a fascinating proof-of-concept: earlier cryopreserved T cells from stem-cell collection could still generate fitter experimental BCMA CAR-T years later than later-collected cells from the same patients.
Then reality interrupts 😂: if early T cells are better, why not just give CAR-T earlier?
Bank early? Manufacture early? Treat early?
Maybe the next frontier is not only how we engineer T cells, but when we capture them.
#CART #MultipleMyeloma #Hemetwitter