I'm building a PVC analytics app to track burden with the whoop/apple watch.
If you know any cardiac electrophysiologist that would be open to discuss the methodology, please dm.
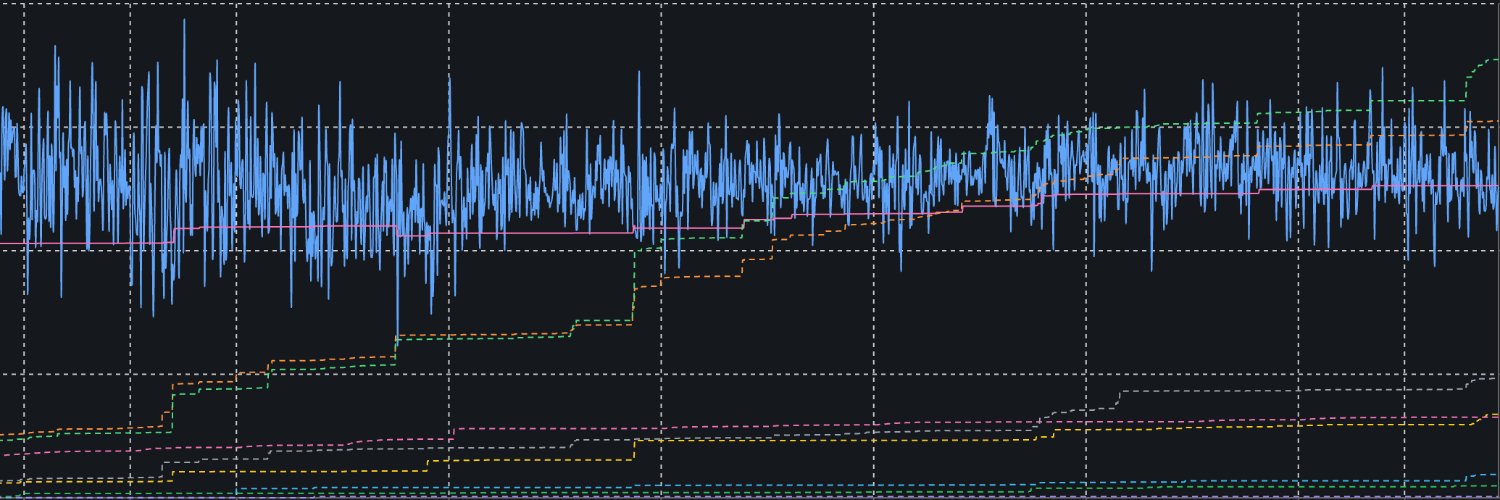
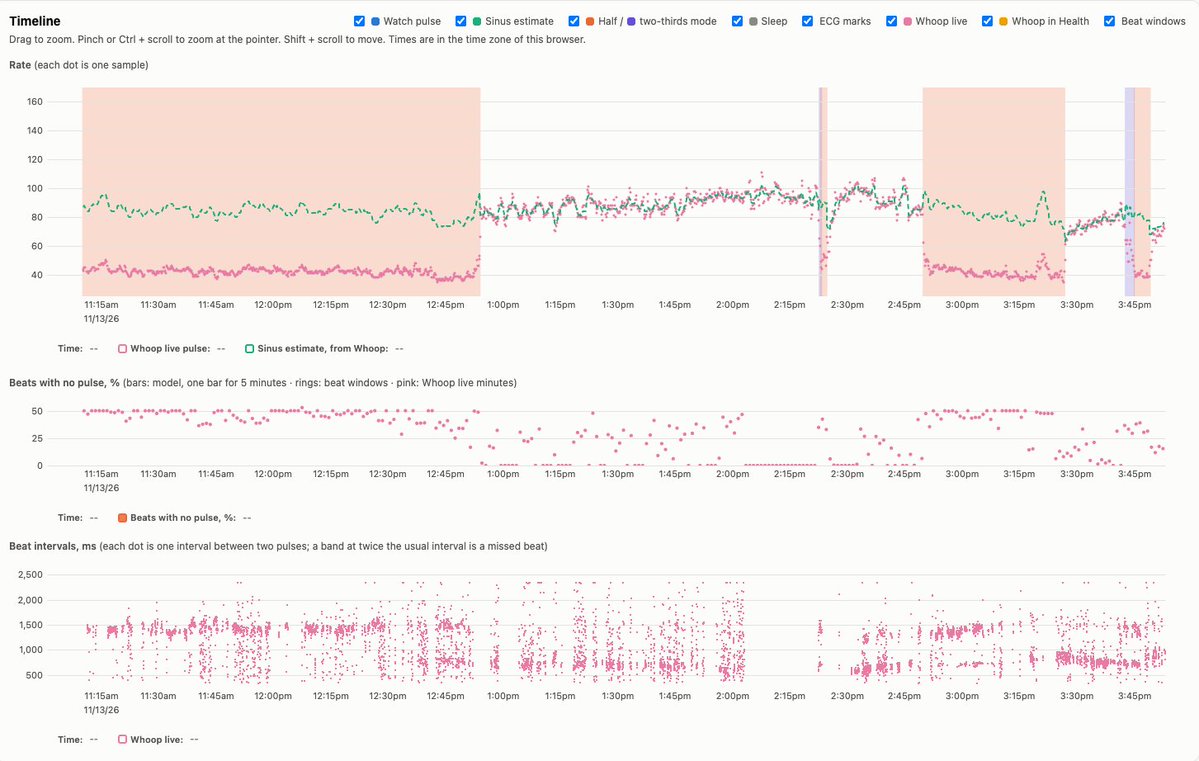
Using historical bpm to estimate RHR. Detecting PVC bigeminy/trigeminy episodes by looking for 1/2 and 2/3 HR rates. This can be done just with the apple watch export.
Add the whoop and we get more granular interval data. Tbd what to do with it.
I've been living with some minor (fingers crossed) heart abnormality for most of my life. I wanted to document publicly for possible serendipity.
As a teenager until my mid 20s, I had sudden-onset palpitations that I was able to intervene by laying down, sudden-offset. Heart rate would double, and be weaker during episodes. Possible SVT, never documented.
5 years ago, my insurance was ending so I decided to go to a cardiologist. At that time I had no SVTs, but felt my heart was sometimes abnormal.
Did a 5 day holter to find a 9.3% burden (2.6-21% daily). Mostly bigeminy. Was told to keep an eye on it every couple years. I supplemented potassium (4.0 -> 4.3) and things seemed to improve.
Over time with kids, forgot about it. A week ago, redid a 24h holter to find a 38% burden mostly bigeminy, which is very high. But all other tests come back with good news: Morphology: LBBB pattern with inferior axis, probably RVOT. Some couplets may show a second morphology. Echo: LVEF 60% (M-mode, during bigeminy). Paradoxical septal motion reported. Thyroid and renal function normal. No syncope. No known family history of sudden death or cardiomyopathy. Troponin: negative.
From here, there are a few options:
- ignore: I can live with the mild symptoms. I feel my heart beating. I feel minor discomforts from time to time.
- medicate with beta blockers: doesn't make sense to me. My PVCs are not triggered by stress, and they have side effects. antiarrhythmics: maybe?
- cardiac ablation: all other tests so far point to a good success rate and low complications for my case.
Currently reached out to 4 electrophysicians in SG for a consult. Planning a cardiac MRI.
Gotta thank @claudeai for shepherding.
Update: So I guess I'm getting heart surgery.
Consulted 3 electrophysiologists and they all recommended an ablation, albeit less urgently than the first cardiologist that I saw.
None recommend medication, because of low success rate, side effects, and adding a dependence. Which was my read as well after getting prescribed beta blockers by my first cardiologist.
Everything points to a simple right ventricular outflow tract case, which has the highest success rate and low complications.
A rough 1 week estimation of burden with a self built app with my whoop estimates a 17% burden which is lower than the second holter I got, but still above the one 5y ago, and above threshold for ablation recommendation.
The question is which doctor to pick:
- SGH, public doctor, will use RF ablation first then PF to homogenize the wound? Probably sees the most cases, trained at Cleveland.
- Private doc 1, RF only, says PF wasn't designed for PVCs and adds risk.
- Private doc 2, will do PF, willing to do a pre-op cardiac mri after I pushed back.
Honestly hard to pick since I didn't stick to a standard script. "And that's on me".
I'm building a PVC analytics app to track burden with the whoop/apple watch.
If you know any cardiac electrophysiologist that would be open to discuss the methodology, please dm.
Using historical bpm to estimate RHR. Detecting PVC bigeminy/trigeminy episodes by looking for 1/2 and 2/3 HR rates. This can be done just with the apple watch export.
Add the whoop and we get more granular interval data. Tbd what to do with it.
I'm building a PVC analytics app to track burden with the whoop/apple watch.
If you know any cardiac electrophysiologist that would be open to discuss the methodology, please dm.
Using historical bpm to estimate RHR. Detecting PVC bigeminy/trigeminy episodes by looking for 1/2 and 2/3 HR rates. This can be done just with the apple watch export.
Add the whoop and we get more granular interval data. Tbd what to do with it.
I've been living with some minor (fingers crossed) heart abnormality for most of my life. I wanted to document publicly for possible serendipity.
As a teenager until my mid 20s, I had sudden-onset palpitations that I was able to intervene by laying down, sudden-offset. Heart rate would double, and be weaker during episodes. Possible SVT, never documented.
5 years ago, my insurance was ending so I decided to go to a cardiologist. At that time I had no SVTs, but felt my heart was sometimes abnormal.
Did a 5 day holter to find a 9.3% burden (2.6-21% daily). Mostly bigeminy. Was told to keep an eye on it every couple years. I supplemented potassium (4.0 -> 4.3) and things seemed to improve.
Over time with kids, forgot about it. A week ago, redid a 24h holter to find a 38% burden mostly bigeminy, which is very high. But all other tests come back with good news: Morphology: LBBB pattern with inferior axis, probably RVOT. Some couplets may show a second morphology. Echo: LVEF 60% (M-mode, during bigeminy). Paradoxical septal motion reported. Thyroid and renal function normal. No syncope. No known family history of sudden death or cardiomyopathy. Troponin: negative.
From here, there are a few options:
- ignore: I can live with the mild symptoms. I feel my heart beating. I feel minor discomforts from time to time.
- medicate with beta blockers: doesn't make sense to me. My PVCs are not triggered by stress, and they have side effects. antiarrhythmics: maybe?
- cardiac ablation: all other tests so far point to a good success rate and low complications for my case.
Currently reached out to 4 electrophysicians in SG for a consult. Planning a cardiac MRI.
Gotta thank @claudeai for shepherding.
Btw, one way PVCs can be seen is with any retail heart rate monitor.
A heart rate monitor looks at your blood vessels dilate to count your pulse. But PVCs don't beat hard enough and the HR monitors like apple watches, whoops, garmin, etc will not register as a pulse.
Therefore your heart rate will be undercounted. And the popular HRV metric, recovery scores, etc will all be noise to you. Which is why I was never able to get anything useful from them.
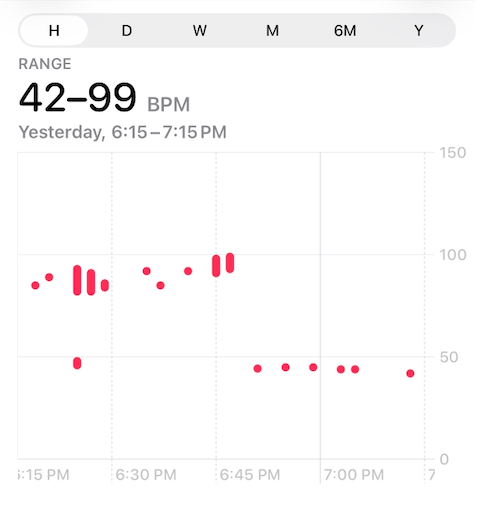
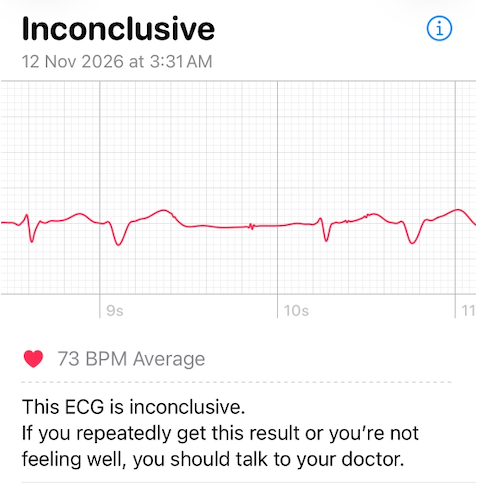
In my case, with continuous bigeminys, the measure HR drops to half. I.e. 80bpm real HR but watch registers 40bpm. See photo 1.
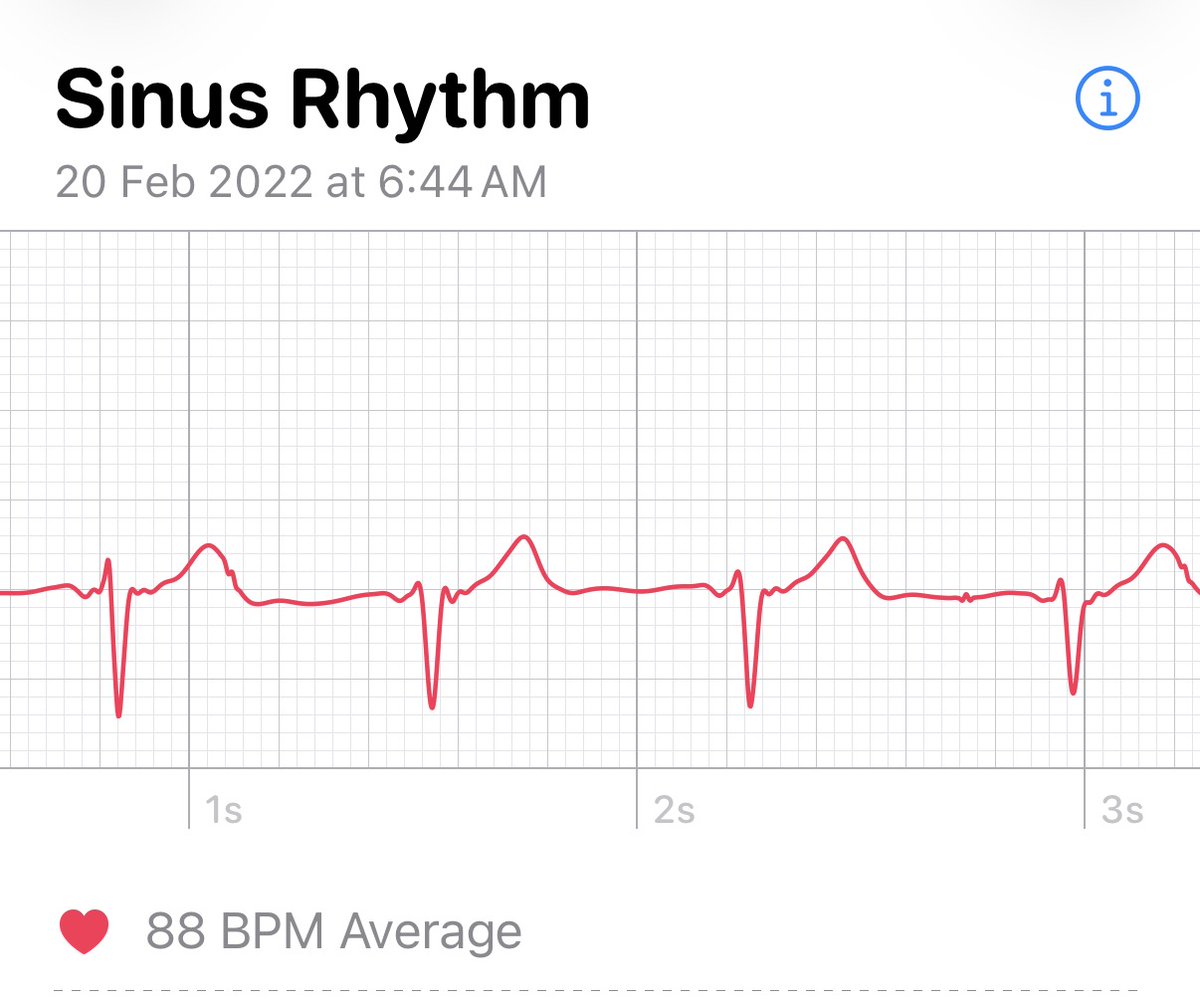
However, with an Apple Watch ECG, your heart rate will be accurate. Photos 2 and 3 for a normal (sinus) curve and a PVC bigeminy episode.
I've been living with some minor (fingers crossed) heart abnormality for most of my life. I wanted to document publicly for possible serendipity.
As a teenager until my mid 20s, I had sudden-onset palpitations that I was able to intervene by laying down, sudden-offset. Heart rate would double, and be weaker during episodes. Possible SVT, never documented.
5 years ago, my insurance was ending so I decided to go to a cardiologist. At that time I had no SVTs, but felt my heart was sometimes abnormal.
Did a 5 day holter to find a 9.3% burden (2.6-21% daily). Mostly bigeminy. Was told to keep an eye on it every couple years. I supplemented potassium (4.0 -> 4.3) and things seemed to improve.
Over time with kids, forgot about it. A week ago, redid a 24h holter to find a 38% burden mostly bigeminy, which is very high. But all other tests come back with good news: Morphology: LBBB pattern with inferior axis, probably RVOT. Some couplets may show a second morphology. Echo: LVEF 60% (M-mode, during bigeminy). Paradoxical septal motion reported. Thyroid and renal function normal. No syncope. No known family history of sudden death or cardiomyopathy. Troponin: negative.
From here, there are a few options:
- ignore: I can live with the mild symptoms. I feel my heart beating. I feel minor discomforts from time to time.
- medicate with beta blockers: doesn't make sense to me. My PVCs are not triggered by stress, and they have side effects. antiarrhythmics: maybe?
- cardiac ablation: all other tests so far point to a good success rate and low complications for my case.
Currently reached out to 4 electrophysicians in SG for a consult. Planning a cardiac MRI.
Gotta thank @claudeai for shepherding.