5 myositis antibodies. 5 phenotypes. Can you name each before the card flips? 🃏
MDA5 → RP-ILD
TIF1-γ → cancer in adult DM
Jo-1 → antisynthetase syndrome
Mi-2 → classic DM
HMGCR → necrotising myopathy
#Rheumatology#Myositis#MedEd#RheumTwitter#NEETSS@IhabFathiSulima
Critical digital ischemia ➡️ Save the digit‼️
🔹Act promptly: protect, relieve pain and vasodilate (CCBs, PDE5 inhibitors; IV prostanoids if severe).
🔹Assess thrombosis and infection.
🔹Dry gangrene: assess perfusion and demarcation; wet gangrene: urgent surgery. #ACR26
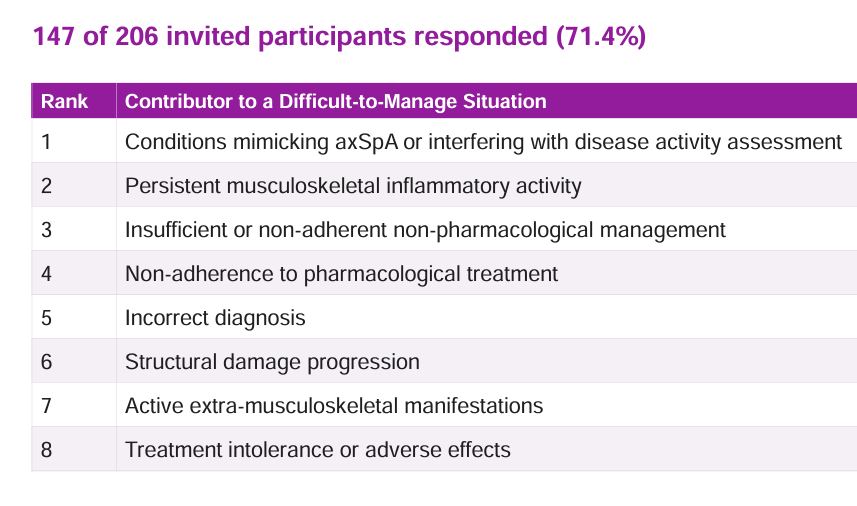
A#2944 ASAS Points to Consider for D2T and Rx-refractory axSpA:
Verify dx, rule out mimics, confirm inflammation with CRP/MRI, check adherence, address comorbidities, add non-pharm care, and provide education.
@RheumNow#ACR26
Bueno, entonces si el sindrome seco no es indispensable para sospechar de Sjogren, en quien sospecho Sjogren?
- neuropatias
- C3 bajo
- Púrpura
- parotiditis
- neumopatia intersticial
- factor reumatoide elevado
- IgG elevado
EULAR 2026 vaccination recommendations:
Assess vaccine status at diagnosis and annually. Individualize plans and vaccinate early, even with active disease.
Prioritize influenza, pneumococcal, recombinant zoster and COVID-19 vaccines; consider live vaccines cautiously. #ACR26
CONGRESS | #ACR26 | PRESENTATION
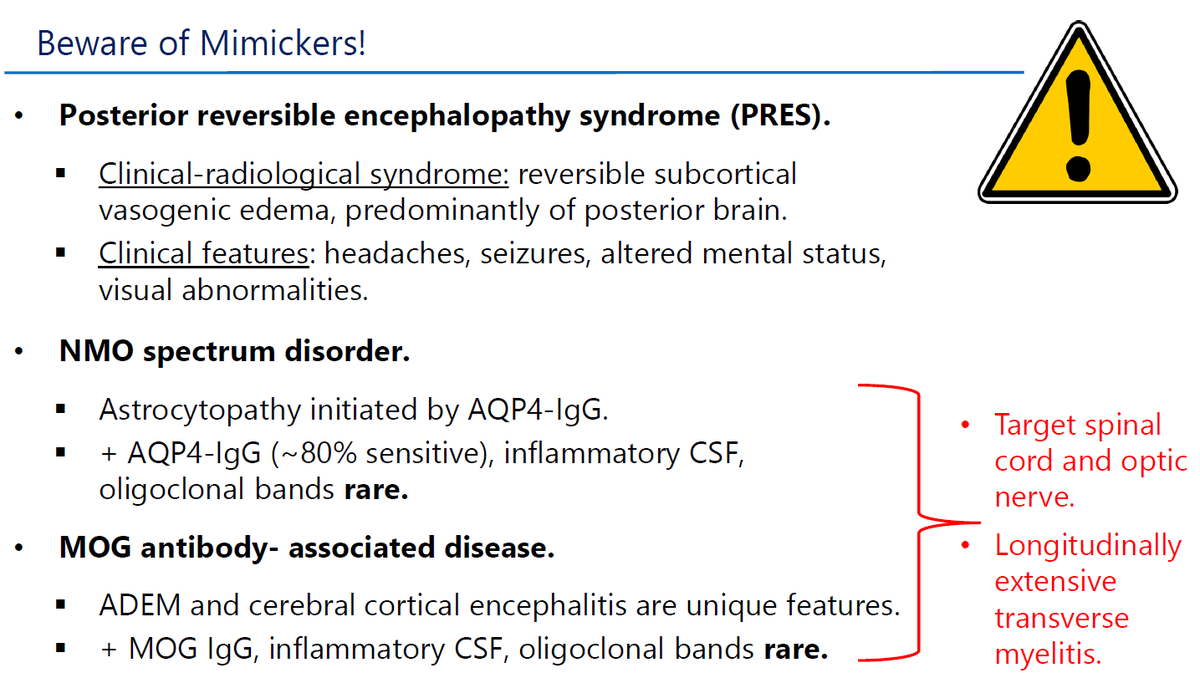
Maria Dall’Era discusses applying the 2025 ACR SLE Treatment Guideline to the evaluation and treatment of patients with neuropsychiatric SLE (NPSLE).
Evaluation should first exclude alternative causes and establish whether manifestations reflect active lupus, with investigations tailored to the clinical presentation. Treatment depends on the manifestation and underlying mechanism, with glucocorticoids and immunosuppressive therapy (e.g. cyclophosphamide, mycophenolic acid analogues, or anti-CD20 therapy) recommended for severe neuropsychiatric syndromes. Recognizing NPSLE mimickers, including posterior reversible encephalopathy syndrome (PRES), NMO spectrum disorder, and MOG antibody- associated disease, is important to inform accurate diagnosis and appropriate treatment.
Follow our live feed for more updates: https://t.co/5ju7zQWdBR
Intended for HCPs. This congress coverage is independently supported through funding from pharmaceutical companies. A full list of our funders can be found on our website. Funders are allowed no influence.
#Lupus #SLE #Rheumatology #MedEd #MedNews #MedicalCongress #RheumTwitter @UofCalifornia
La necesidad patológica de querer saberlo todo en medicina es un daño irreparable para la salud mental del médico y la atención al paciente.
Se tenía que decir y se dijo.
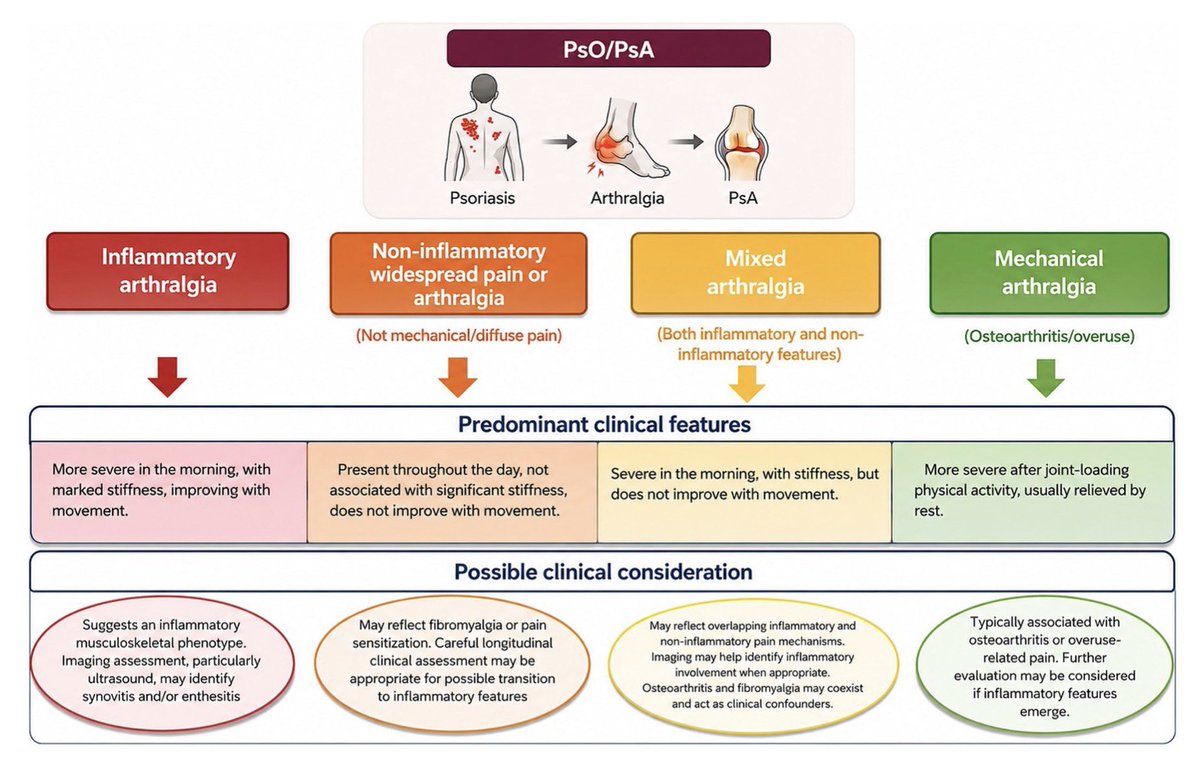
Artralgias en pacientes con psoriasis: un tema muy interesante valorado con mucho gusto en un nuevo artículo 📝
Acceso abierto 🔑 https://t.co/kumYOfTLM7
✅ What remains a possible use for #rituximab in systemic #Lupus and lupus #nephritis in 2026?
Check the opening slide from my invited talk at the national #Qatar#Rheumatology meeting of Doha (10-12 dec 2026)
Seguimos fortaleciendo la atención a nuestros pacientes renales. El @HIAyoraLoja
continúa recibiendo insumos fundamentales para el desarrollo de los tratamientos y la continuidad de la atención a quienes viven con enfermedad renal.
✅ Trabajamos con compromiso y responsabilidad
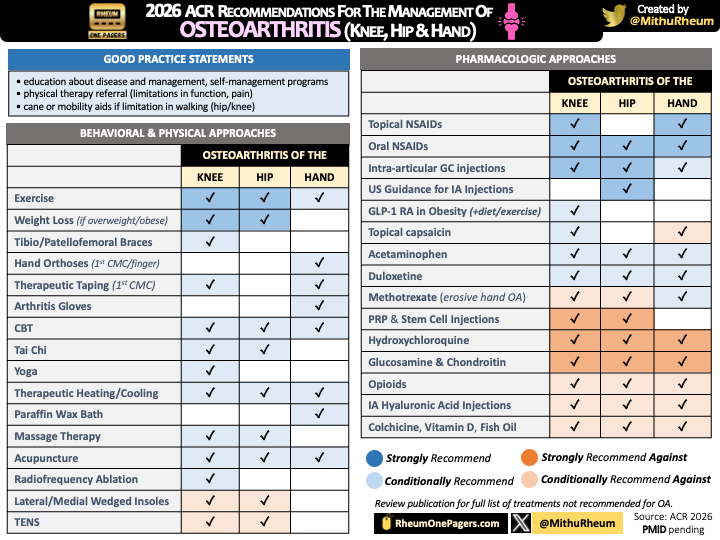
🆕 2026 ACR Recommendations for Management of Knee, Hip & Hand #Osteoarthritis
⬥ Behavioral/Physical vs Pharmacologic Treatments
⬥ New: GLP1 RA for Knee #OA, MTX for Erosive Hand OA?!
⬥ Treatments *not* recommended #Rheumatology
📝 ACR Guidelines⇢ https://t.co/NMhI2IsJYR
#ENTREVISTA | @BenjaminCe16810 a través de @UVNOTICIAS señala que la salud se garantiza a través de diferentes espacios, desde el equipamiento hasta la atención. Durante este tiempo se han fortalecido diferentes espacios.
L💙 No Dia Mundial da Osteoporose, destacamos a importância de cuidar da saúde óssea em todas as etapas da vida. A prevenção, o diagnóstico oportuno e o acompanhamento adequado são fundamentais para preservar a mobilidade e a independência.
🌎 Na PANLAR, promovemos maior conscientização sobre a saúde óssea e seu impacto na qualidade de vida.
#PANLAR #DiaMundialdaOsteoporose
#RECONOCIMIENTO | El @HIAyoraLoja
obtuvo el primer lugar en la presentación de proyectos de mejora continua, con la iniciativa “Fortalecimiento del conocimiento normativo #ESAMyN en el personal”, reafirmando su compromiso con la calidad de atención.
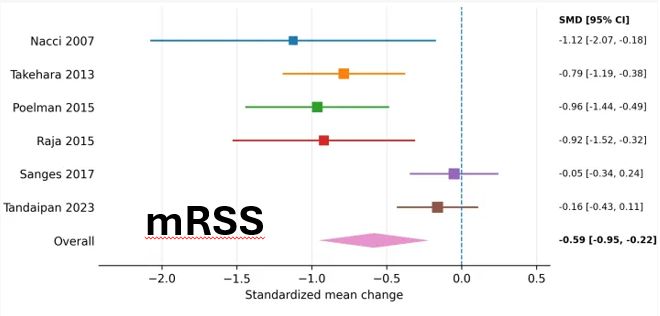
Metanalysis of IVIG in scleroderma (11 studies, 363 pts) showed IVIG to be safe; signif improvement in skin by mRSS (SMD −0.59; p 0.0019) & GI Dz (SMD −0.73; p 0.0012; I2 = 0%). W/ inflam myopathy signif reduction in CK (SMD −0.53; p<0.001) https://t.co/h53FrACCgA
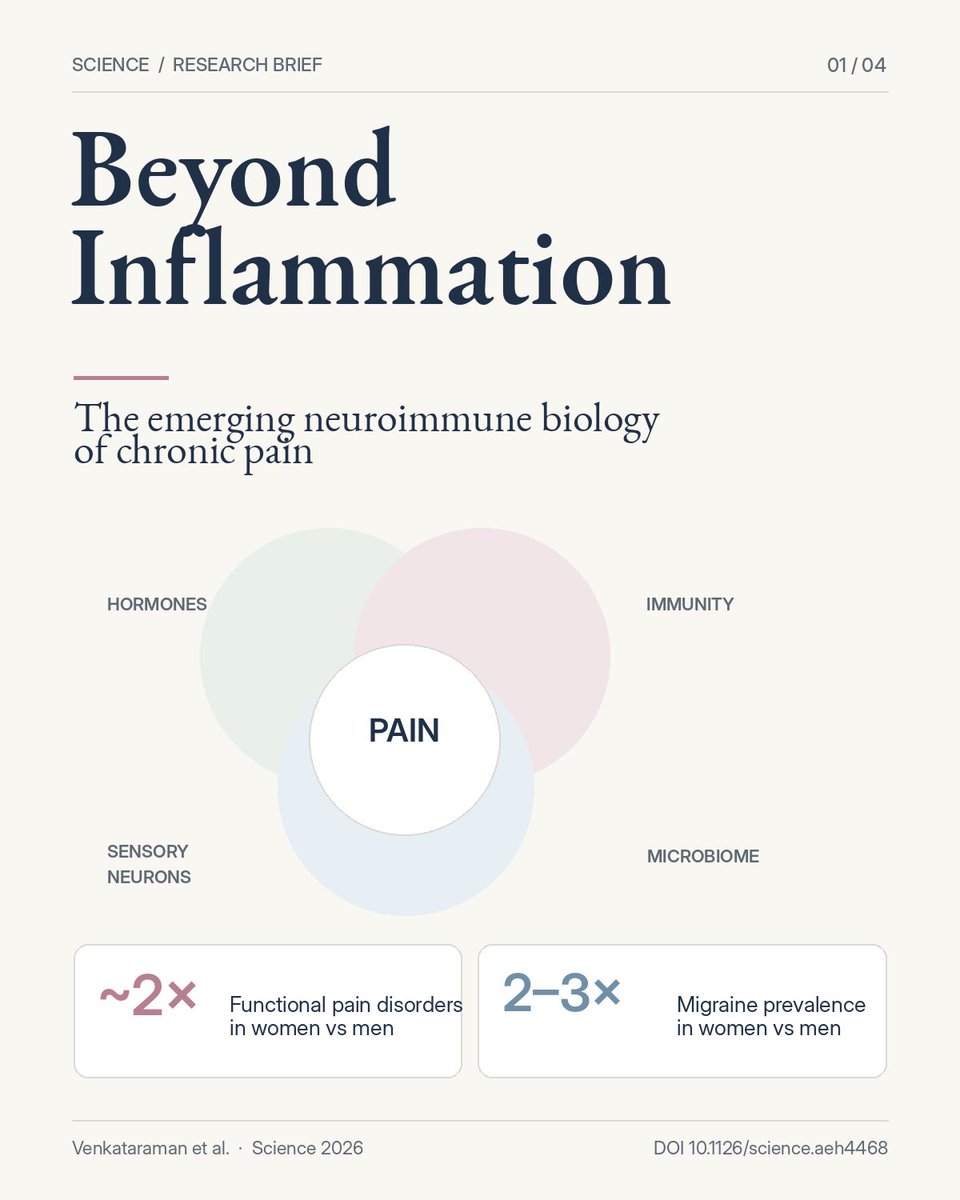
BEYOND INFLAMMATION: THE EMERGING NEUROIMMUNE BIOLOGY OF CHRONIC PAIN
How sex hormones, immune cells and endogenous analgesic pathways are reshaping our understanding of pain.
A fascinating 2026 review in Science challenges conventional thinking about chronic pain.
THE NUMBERS SPEAK
• Functional pain disorders: ~2× more common in women
• Migraine: 2–3× more frequent in women
• Knee OA: prevalence up to 2× higher in women
But the real discovery lies in the underlying biology.
1. THE PARADIGM SHIFT: TREGs AS NATURAL PAINKILLERS!
FOXP3+ regulatory T cells do more than maintain immune tolerance.
In female mice, researchers identified an extraordinary endogenous analgesic circuit:
Ovarian hormones → Meningeal Tregs → Enkephalin → δ-opioid receptors → Analgesia
• Meningeal Tregs release enkephalin, an endogenous opioid.
• Enkephalin activates δ-opioid receptors on MRGPRD+ sensory neurons.
• Remarkably, this analgesic mechanism is independent of conventional Treg-mediated immunosuppression!
The immune system can directly regulate pain without necessarily suppressing inflammation.
2. SAME PAIN, DIFFERENT IMMUNE CIRCUITS!
Experimental models reveal striking sex-dependent mechanisms.
MALES: Spinal microglia → IRF5/P2X4/BDNF → central sensitisation.
FEMALES: CD8+ T cells/PANX1 and macrophage-derived IL-23/IL-17A/TRPV1 pathways contribute to pain hypersensitivity.
Interestingly, CSF-1 promotes microglial activation in males but meningeal Treg expansion in females.
One mediator. Distinct neuroimmune responses.
3. FIBROMYALGIA: BEYOND CLASSICAL AUTOIMMUNITY
A landmark GWAS involving >2.5 MILLION individuals, including >50,000 affected individuals, revealed:
• Strong genetic association with IBS
• Enrichment in enteric neuronal pathways
• No comparable enrichment for classical autoimmune disorders
Another intriguing observation:
Gut microbiota transplanted from women with fibromyalgia induced pain-like and immune changes in germ-free mice!
This suggests a possible microbiome–immune–neuronal contribution to chronic pain.
4. ESTROGEN CAN AMPLIFY VISCERAL PAIN
A newly characterised pathway:
Estrogen → ERα → PYY → Serotonin/5-HT3 signalling → Visceral hypersensitivity
This provides a mechanistic link between ovarian hormones, intestinal epithelial cells and sensory neurons.
5. PAIN RESOLUTION: THE FORGOTTEN HALF!
Pain persistence may reflect not only increased nociception but also impaired resolution.
Androgens promote IL-10-producing monocytes, accelerating inflammatory pain resolution in experimental models.
Could stimulating endogenous pro-resolving immune pathways become a therapeutic strategy?
THE BIG PICTURE
Chronic pain is not simply persistent inflammation.
Sex hormones × Immune cells × Sensory neurons × Gut microbiome collectively influence pain initiation, amplification and resolution.
The next frontier in pain medicine may not be merely blocking pain-generating pathways, but harnessing the body’s own immune-mediated analgesic mechanisms.
These mechanistic discoveries are compelling, although most remain preclinical and require human validation.
REFERENCES
Venkataraman A, et al. Science. 2026.
DOI: 10.1126/science.aeh4468
Midavaine É, et al. Science. 2025.
DOI: 10.1126/science.adq6531
#Neuroimmunology #Rheumatology #Fibromyalgia #PainResearch
Urate-lowering therapy is the foundation of long-term gout management.
The aim is not just pain relief during flares, but sustained reduction of serum urate so that crystal burden gradually decreases.
Key principles:
Start low.
Titrate to target.
Use flare prophylaxis when starting.
Do not stop urate-lowering therapy during an acute flare.
Aim for serum urate <6 mg/dL, or <5 mg/dL in severe tophaceous gout.
Allopurinol remains the usual first-line option, while febuxostat, uricosurics, and pegloticase have specific roles depending on patient profile, renal function, cardiovascular risk, stone history, and disease severity.
Gout is treatable.
The target matters.
#Gout #Rheumatology #UricAcid #MedicalEducation #DrAravindPalraj @IhabFathiSulima
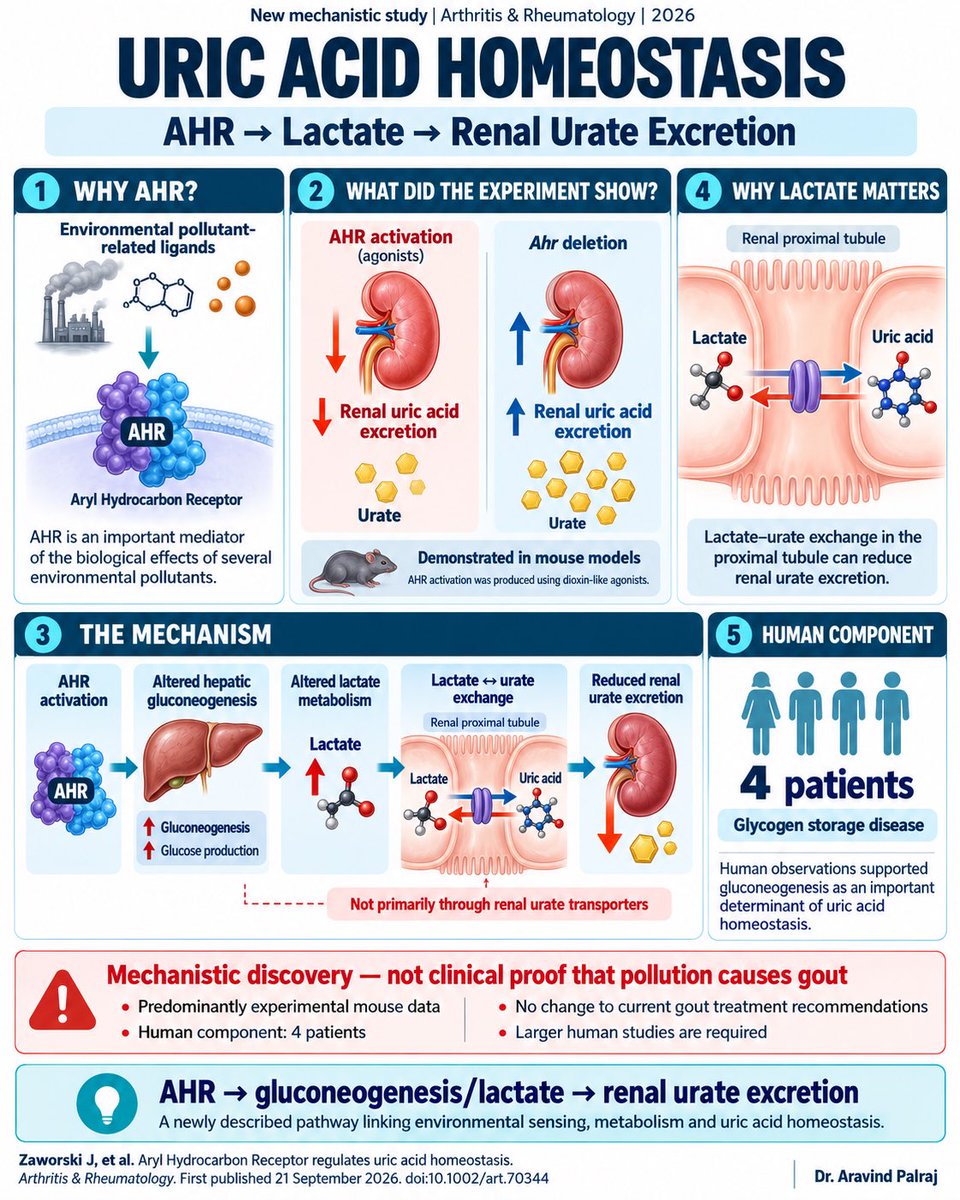
A new mechanistic study adds an unexpected layer to uric acid biology:
AHR activation → altered gluconeogenesis/lactate → reduced renal urate excretion.
Important: this is primarily experimental data—not proof that pollution causes gout. But it opens a fascinating link between environmental sensing, metabolism, and urate homeostasis.
doi:10.1002/art.70344
#Gout #UricAcid #Rheumatology #Metabolism #MedicalResearch @IhabFathiSulima