Sunday musings. Five things I have learned over the years, cemented by the consult service, that every pathologist should consider when releasing diagnoses into the wilderness.
1. Pathologists are morphologists, yes, but much more importantly, they are consultants. Findings that are beside the point and clinically insignificant need not clutter our microscopic description or diagnosis unless they are relevant to how the diagnosis was made.
2. Because pathologists are consultants, we need to know the clinical implications of our diagnosis. And if both entities on the differential are treated the same way, a differential is perfectly fine as a diagnosis.
3. Pathologists should remember what clinical finding prompted a biopsy. As obvious as this may seem, we sometimes report calcifications and forget that the clinical finding was a mass. If a mass forming lesion is not seen, then the biopsy may be non representative.
4. Immunohistochemistry should be spare and targeted. It should answer a morphologic question instead of serving as a small flash light in a vast and uncharted darkness.
5. Contrary to popular belief, a pathologist’s desire to be definitive is ever present, and always fueled by pressure from clinicians. It is ok not to know, it is ok to seek help, it is ok be inconclusive when facing too little material, as long as we try to provide a plan of action. A tiny bit of ugliness does not a monster make, and one small assumption can wreak irreversible havoc on a patient’s life.
#Pathology#quiz!
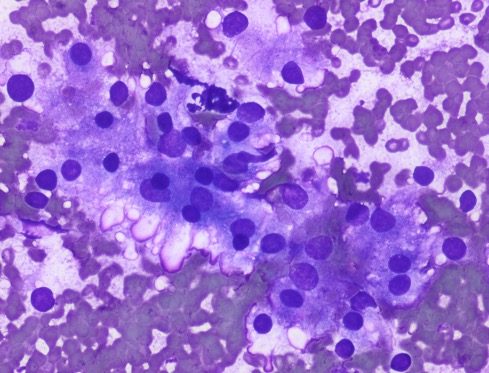
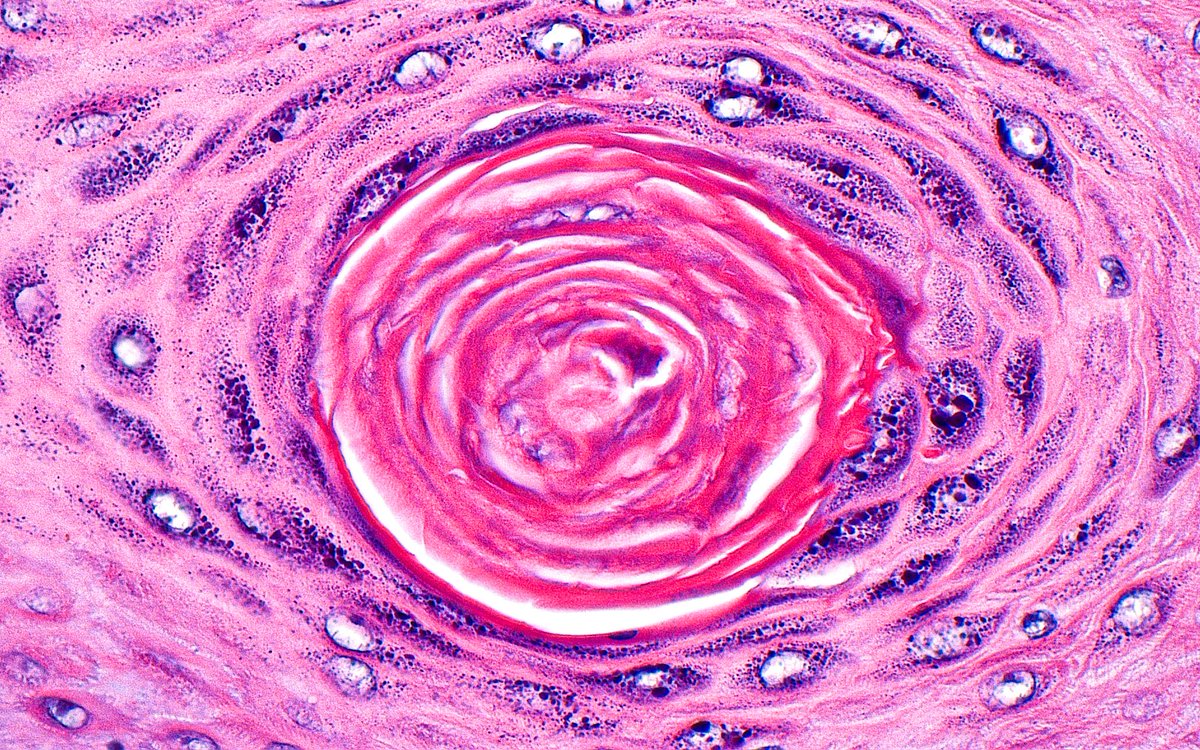
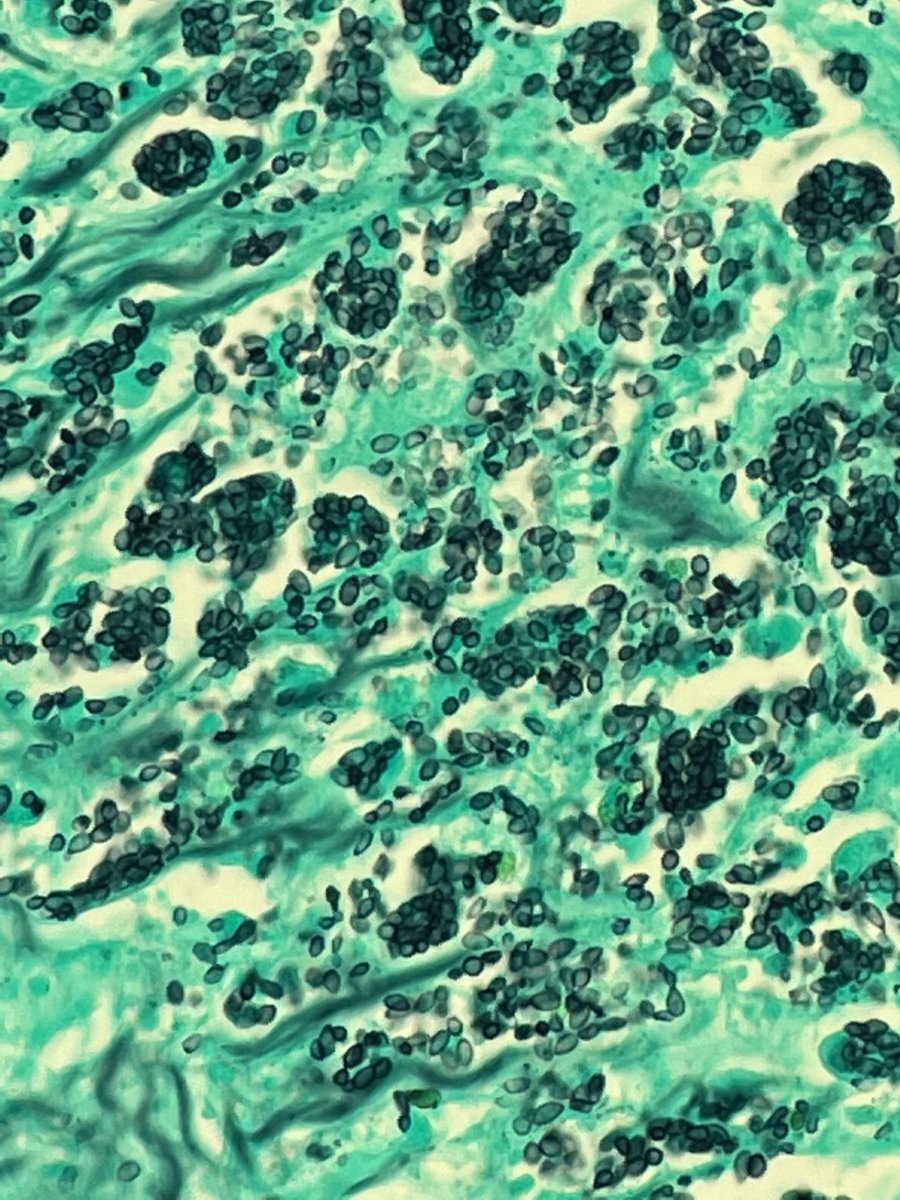
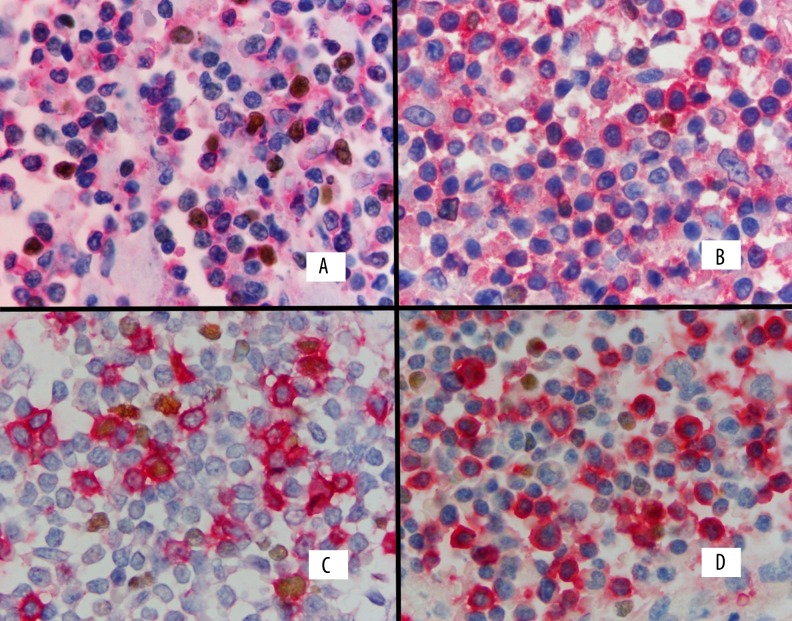
1. What tissue is this (#hemepath)?
2. What is in your differential?
3. What is your diagnosis? #WiyD
Case details will be posted as a reply soon!
Created more jobs in two years than any presidency has created in four.
Unemployment is near its lowest rate in over 50 years.
Our economic plan is working.
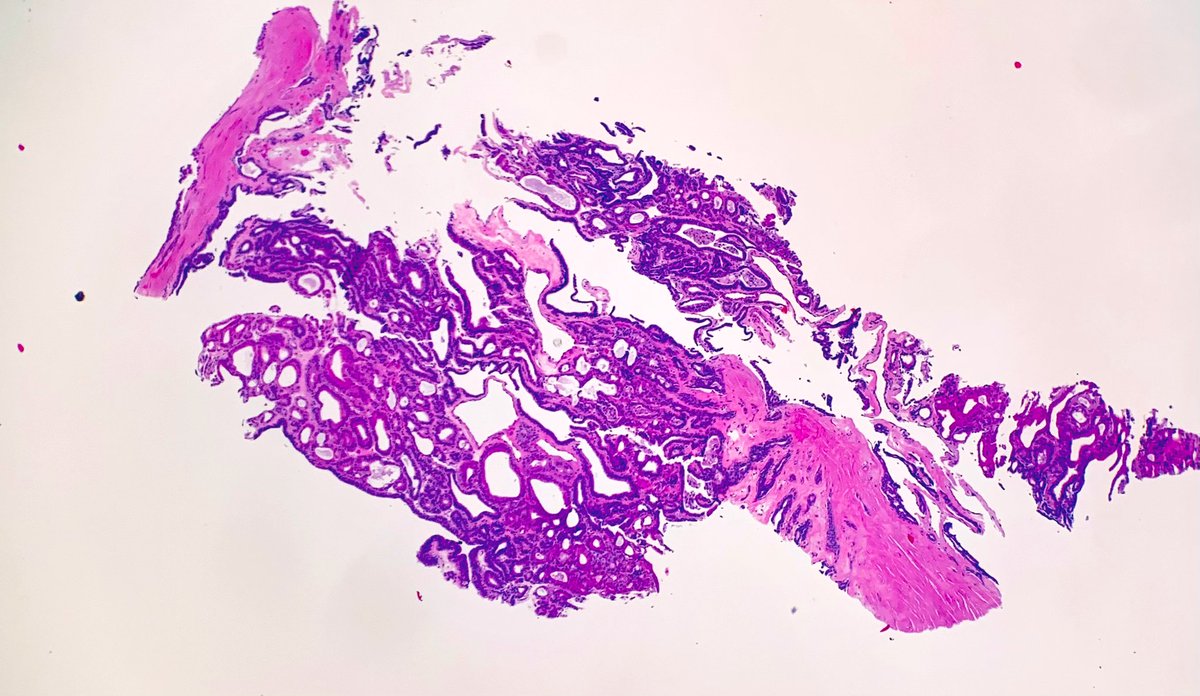
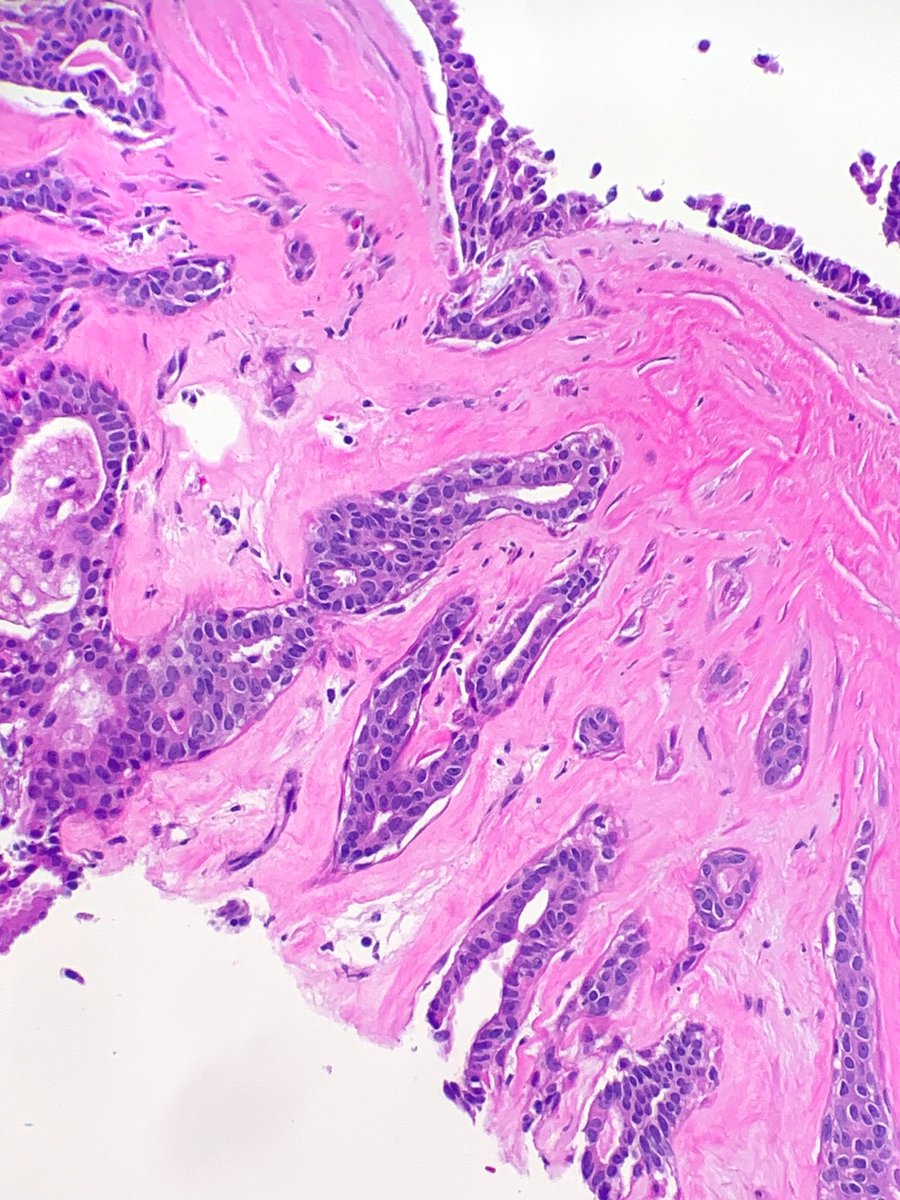
Dr. Vikas Mehta showing a great case of atrophic adenocarcinoma of the prostate! Note negative basal markers.
Atrophic ca: Acini are round, often dilated and distorted and lined by flattened attenuated epithelium with scant cytoplasm and infiltrative growth pattern
@Vijuananthan
#Pathology article of the day. #AotD
Busard 2011 "Deep infiltrating endometriosis of the bowel: MR imaging as a method to predict muscular invasion" #gynpath https://t.co/nzkRWidt2C
In Opinion
"President Biden is right," @jbouie writes. "The so-called MAGA movement, led by Donald Trump, is a direct threat to democratic self-government in the United States." https://t.co/p1c0D3ytJo
I think it’s time I do an official introduction for the twitter universe. My name is Taruna Ramnath. I’m a Trinidadian. 🇹🇹 I’m a current MS4 student applying to #PathMatch2023! I look forward to connecting with you all! All advice welcomed and appreciated! 🙏🏼#pathtwitter
For a magazine, I’m writing a piece about doctors organizing.
Do you know any people/orgs who have successfully lobbied for better working conditions in healthcare? Can be small local efforts.
Or — has anyone left traditional care models & designed their own practice?
DM me!