

Top Tweets for #APG777

Summary graphic of atopic dermatitis drugs/targets by benefit/treatment profile:
SOC benchmarks: #Dupilumab $SNY $REGN and #Upadacitinib $ABBV
Compare to:
Injectables in Ph2b trials
#APG777 $APGE
#Rezpeg $NKTR
Oral drugs in Ph2b trials
#soquelitinib $CRVS
KT-621 $KYMR


It's a smart bet
I have a slightly different perspective on it:
Dupi's 2031 LOE will be unique in a way where they will still be a Best in Disease gold standard product. When dupi biosimilars come into the market they will be widely used bc of this gold standard efficacy and safety combined with the discounted price (40-70% discount)
This creates a dynamic where payers will need to evaluate whether the premium they're paying for your drug is more value than a dupi biosimilar. This also increases the amount of dupi failures and dupi experienced AD in the market
So the question every drug program should be asking is:
1. How much do they differentiate (efficacy, safety, administration route, dosing frequency, durability) to a dupi? And is that enough to justify the pricing premium of your drug?
2. If I can't beat dupi on a price adjusted basis, can I work on dupi experienced and/or failure AD pts?
(There's also the ability capture that AD pt population that has a Asthma comorbidity but you still need to beat dupi here.)
Any drug program creating me-too drugs or dodging dupi-experienced and dupi failures pts in their phase 2 and 3 trials are essentially shooting themselves in the foot.
This is my view on these names: $KYMR's KT-621: MOA-wise they won't be beating dupi since they only target one source of that Th2 inflammation whereas dupi could hit the others. They will struggle on mixed Th2/Th17 diseases so if they have any asian sites or more African American patients, I'd be scared of being positioned in those readouts. It is an oral so I think they can capture pts that have needle phobia at 1L. After that, I'm not sure where they would fit especially if efficacy and safety doesn't hold up. Also $SNY dropped $KYMR's IRAK4 program so that partnership is not safe if efficacy doesn't hold up.
$NKTR should be able to work on dupi experienced and failures hence, why I'm confused why they had to filter for a biologic naive pt pop in their phase 2bs so now they have nothing to guide their phase 3 design. Their durability is real though. It looks like you have to dose for a longer period to balance the Treg/teff ratio to get more efficscy that's why phase 3 has a 24wk induction period.
IL-13s have some data on being able to work on dupi experienced and failures so they will have a place in this market and I believe $APGE (APG-777) dosing frequency can set itself apart
Ox-40s are essentially dead but if amli still sells, I'd say that's a good sign that the market is still looking for options
JAK inhibitors will still have a place in severe-very severe patients. I can actually envision a treatment landscape where JAK inhibitors are used in short course to quickly control disease and then Treg inducers $NKTR, $CRVS to maintain the response.
Need to look at $EVMN's programs but new MOAs and orals will carve a market share
Bispecifics will be interesting but it's all about whether they can best dupi and can work on dupi failures (especially IL17A/F x IL13, not sure about IL13xTSLP)
$CRVS program to me is the best suited to survive in this post-dupi LOE world. It's an oral and a new MOA. Works on dupi and JAK failures. Can work on th2/th17 diseases and CTCL pts that present themselves like AD (which allows it to be used 1L for some patients). It can work on Asthma comorbidity with it's effects on ILC2s and reduction of IL-5 and it can even work on the neutrophilic asthma pts where dupi is ineffective. Durability is similar to $NKTR's durability and good to know that longer dosing (more tregs) can lead to extended effects (increased EASI-100s). There's an unknown on safety though Ritlecitinib (hits ITK and JAK3 can provide some read-through as it is viewed as the safest JAK. It's early tho but mgt clinical development design, planning, and execution are top notch. It's hard not to be bullish when looking at it this way.

💡 Emma Guttman-Yassky, MD, PhD, provided insights into the emerging biologic #APG777 (Apogee Therapeutics), with its potential for extended dosing intervals and favorable safety profile in atopic dermatitis.
https://t.co/K4V3FdfyYy #AtopicDerm #DermTwitter

Patients with moderate to severe #atopic #dermatitis experienced a 71% decrease in Eczema Area and Severity Index scores from baseline through 16 weeks with #APG777, an anti-IL-13 antibody from #Apogee Therapeutics. https://t.co/Bdcn27Xmen

Atopic Dermatitis PBO-adj #EASI Reduction
New Trials:
🔹anti-IL-13: #APG777 $APG
🔹 IL-2R agonist: #Rezpeg $NKTR
🔹 #ITK Inh: #Soquelitinib $CRVS (oral)
🔹 anti-OX40L: #Amlitelimab $SNY
FDA Approved:
🔹 anti-IL-4Ra: #Dupilumab $SNY $REGN
🔹 anti-IL-13: #Lebrokizumab $LLY
🔹 #JAK1 Inh: #Upadacitinib $ABBV (oral)

Comparison of main adverse events and safety data for recent drug trials in atopic dermatitis compared to FDA approved treatments by drug target:
🔹 $CRVS oral ITK inhibitor #soquelitinib (Ph 1b)
🔹 $APGE anti-IL-13 #APG777 (Ph 2)
#conjunctivitis #headache #URTI

I continue to not understand why $APGE pursuing APG777 in #asthma due to consistent failed anti-IL-13 #asthma drug trials:
$LLY #Lebrikizumab
$GSK #Anrukinzumab
$AZN #Tralokinumab
$NVS #Dectrekumab
#Grok4 Prediction for success for #APG777 in asthma:
MODERATE to LOW likelihood of broad success
Analysis:
I supplemented my prior research with #Grok4 analysis of failed ant-IL-13 asthma trials, importantly incorporating key research showing IL-33-ST2-Treg axis + IL-13 essential for lung tissue repair seemingly ignored by industry.
https://t.co/KLOycnfq5N
Here is rationale and paper showing Tregs produce IL-13 in lungs and leads to tissue regeneration/repair. In fact IL-13 deficiency can exacerbate lung damage!
#Treg #IL13 BENEFICIAL in #asthma lung repair.
1. Injured endothelial lung cells release cytokine #IL33
2. IL-33 activates #ST2 receptor on Tregs
3. Tregs release IL-13 + IL-10
4. IL-13 inhibits further lung injury by #Vav1 apoptosis
5. Tregs promote M2 macrophages formation
6. IL-13 known to promote effective repair after acute lung injury and the pathogenesis of chronic diseases such as allergic asthma.
https://t.co/7hTqKJlDEF
7. IL-13 can reduce IL-6 in lung tissue inflammation, helping repair
Here is a post discussing why IL-13 and $CRVS ITKi approach to increasing #Tregs may have advantage in #asthma and #COPD indications allowing for continued IL-13 signaling for lung tissue repair:
https://t.co/EyWnfHfNdj


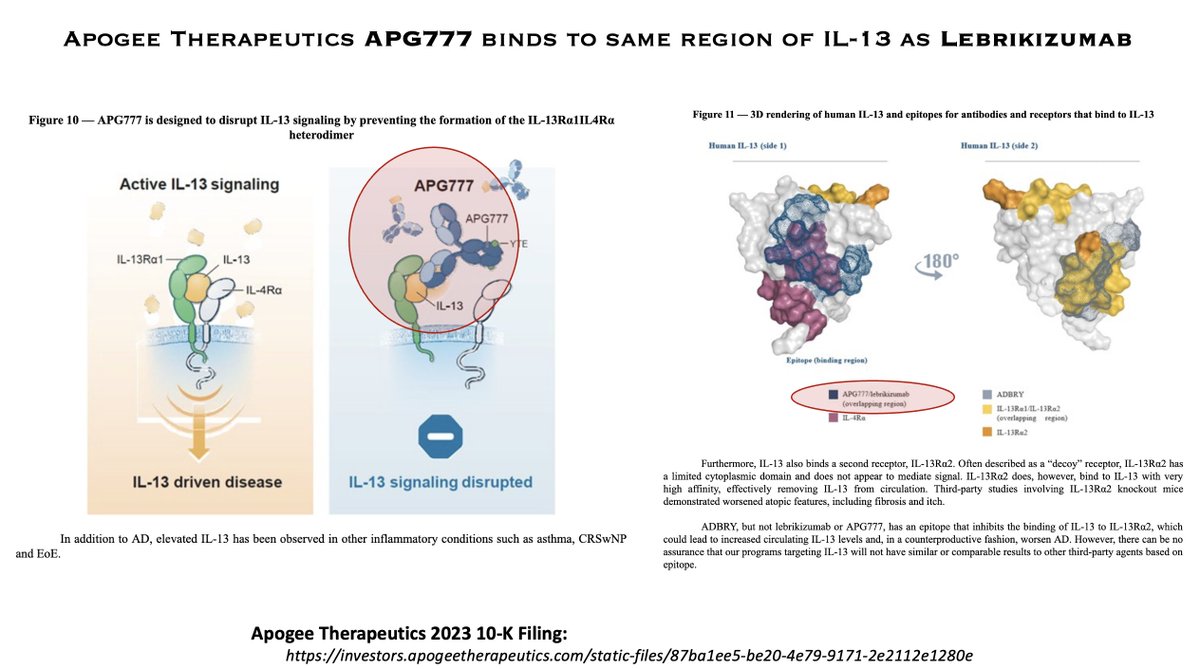
Research: Why is $APGE putting APG777 in #asthma when IL-13 mAbs tralokinumab, lebrikizumab failed?
- APG777 binding of IL-13 overlaps w/ lebrikizumab, why would outcome be different?
- IL-13 has multiple roles including anti-inflammatory + repairative function in lungs. Released by #Tregs after damage, so fully blocking IL-13 likely reason why biologics continue to fail in asthma indication
https://t.co/rZ22EPI47o
https://t.co/x64U2L77M2



Going through $APGE new presentation, nice narrative in one slide for increasing "absolute EASI-75" reduction, but maybe placebo-adusted more accurate?
I updated slide using PBO-adj EASI-75 comparing:
#Amlitelimab
#Dupixent
#Ebyglyss
#APG777
#Rinvoq
less obvious its better

$APGE had strong biomarker data in healthy volunteers for anti-IL-13 #APG777 in Mar '24 and went up over 100%, simlar to $KYMR recent share price move on biomarker HV data. The similarities don't end there, but extend to downstream effect on #STAT6.
$APGE showed nearly complete pSTAT6 inhibition up to 12 months w/ APG777. This interesting point may actually make some of APG777 data a meaningful predictor of $KYMR STAT6 degrader KT-621 efficacy/safety in patients for their planned Ph2b in 2026 in atopic dermatititis and thus strong implications for $KYMR lead program due to similar effects on STAT6.
What potential (if any) safety risks may emerge for $KYMR may emerge in $APGE APG777 due to its near complete inhibition of pSTAT6 for extended periods. My concern has to do with the pleiotropic distribution/expression of STAT6 across tissues and its non-immune functions that will also be impaired. $APGE APG277 Ph2b trial w/ about 80 patients on drug for 16 weeks could be very interesting.


$KYMR
Home run data.
Greater than 90% STAT6 degradation in blood; complete STAT6 degradation in blood and skin above 50mg MAD.
Biomarkers equal or better than DUPIXENT.
Again, no one sits on good data.
$xbi


IL-13 is a pivotal Th2 cytokine implicated in the development of #AtopicDermatitis, #asthma, and various inflammatory conditions. #APG777, a humanized IgG1 monoclonal antibody, holds promise in interrupting downstream inflammatory signaling.
Read more: https://t.co/ywIU5bFRxc
Last Seen Hashtags on Sotwe
踩踏
Seen from United States
Lebanese
korean
Seen from Kuwait
체벌
Seen from United States
compilation((()))***
Seen from Netherlands
ことば綱引き
Seen from United States
kiribaku
Seen from United States
minichat()*********************************
Seen from United Kingdom
เย็ดแม่ยาย
Seen from Thailand
minichatt video()*************************
Seen from United Kingdom
Trends for you
Most Popular Users

Elon Musk 
@elonmusk
241.5M followers

Barack Obama
@barackobama
118.8M followers

Cristiano Ronaldo
@cristiano
114.5M followers

Donald J. Trump
@realdonaldtrump
111.8M followers

Narendra Modi
@narendramodi
107.1M followers

Rihanna
@rihanna
98.7M followers

NASA
@nasa
92.3M followers

Justin Bieber
@justinbieber
91.8M followers

KATY PERRY
@katyperry
90M followers

Taylor Swift
@taylorswift13
84M followers

Lady Gaga
@ladygaga
75.5M followers

Virat Kohli
@imvkohli
73.5M followers

Kim Kardashian
@kimkardashian
70.9M followers

YouTube
@youtube
68.8M followers

Neymar Jr
@neymarjr
66.5M followers

Bill Gates
@billgates
65.3M followers

Selena Gomez
@selenagomez
63.1M followers

The Ellen Show
@theellenshow
62.2M followers

CNN
@cnn
61.7M followers

X
@x
60.7M followers