

Top Tweets for #pengblock

Enrique González Marcos et al.
🔗 https://t.co/0DTHUyg6jJ
#SurgicalTechniquesDevelopment #HipFractures #RegionalAnesthesia #PENGBlock

🧠 𝐏𝐄𝐍𝐆 𝐯𝐬 𝐎𝐍𝐁 𝐈𝐍 𝐓𝐔𝐑𝐁𝐓: 𝐖𝐇𝐄𝐍 𝐁𝐋𝐎𝐂𝐊 𝐂𝐎𝐌𝐏𝐀𝐑𝐈𝐒𝐎𝐍 𝐎𝐔𝐓𝐑𝐔𝐍𝐒 𝐁𝐀𝐒𝐈𝐂 𝐍𝐄𝐔𝐑𝐎𝐏𝐇𝐘𝐒𝐈𝐎𝐋𝐎𝐆𝐘
#ObturatorNerve #ObturatorNerveBlock #PENGBlock #TURBT #ObturatorJerk #RegionalAnaesthesia #RegionalAnesthesia #NerveBlock #Neurophysiology #MotorBlock
#CriticalAppraisal
𝐂𝐑𝐈𝐓𝐈𝐂𝐀𝐋 𝐀𝐏𝐏𝐑𝐀𝐈𝐒𝐀𝐋:
⚡ 𝐀. 𝐅𝐈𝐑𝐒𝐓, 𝐔𝐍𝐃𝐄𝐑𝐒𝐓𝐀𝐍𝐃 𝐓𝐇𝐄 𝐉𝐄𝐑𝐊
▫️ Lateral-wall cautery can directly stimulate the ON.
▫️ This generates an efferent motor impulse.
▫️ Result → sudden adductor contraction.
▫️ This is not simply a pain pathway.
🔌 𝐁. 𝐓𝐇𝐄 𝐁𝐀𝐒𝐈𝐂 𝐋𝐎𝐆𝐈𝐂
▫️ LA produces a conduction block at the injected segment.
▫️ It does not paralyse the entire distal nerve.
▫️ Direct stimulation distal to that block can still depolarize motor axons.
▫️ The impulse can travel distally to muscle.
▫️ Therefore, adductor contraction may still occur.
🎯 𝐂. 𝐓𝐇𝐄𝐍 𝐖𝐇𝐘 𝐃𝐎𝐄𝐒 𝐏𝐄𝐍𝐆 𝐖𝐎𝐑𝐊?
▫️ PENG was designed for hip analgesia.
▫️ It is not primarily an obturator motor block.
▫️ Reduced jerk may reflect obturator spread.
▫️ But similar outcomes ≠ identical mechanism.
▫️ Mechanism needs demonstration, not assumption.
🧬 𝐃. 𝐀𝐍𝐀𝐓𝐎𝐌𝐘 𝐂𝐎𝐌𝐏𝐋𝐈𝐂𝐀𝐓𝐄𝐒 𝐈𝐓
▫️ ON branching is variable.
▫️ Anterior/posterior divisions may separate proximally.
▫️ Motor branches arise at different levels.
▫️ Accessory obturator innervation may also exist.
🔥 𝐊𝐄𝐘 𝐓𝐀𝐊𝐄𝐀𝐖𝐀𝐘𝐒
▫️ Same outcome ≠ same mechanism.
▫️ Analgesia ≠ guaranteed motor silence.
▫️ A proximal block does not abolish distal nerve excitability.
▫️ In high-risk TURBT, the required endpoint is no movement.
▫️ Neuromuscular blockade directly controls the final effector, the muscle.
🎯 𝐊𝐍𝐎𝐖 𝐓𝐇𝐄 𝐁𝐋𝐎𝐂𝐊. 𝐁𝐔𝐓 𝐅𝐈𝐑𝐒𝐓, 𝐊𝐍𝐎𝐖 𝐓𝐇𝐄 𝐋𝐎𝐆𝐈𝐂.

🦴 𝐏𝐨𝐬𝐭𝐞𝐫𝐢𝐨𝐫 𝐇𝐢𝐩 𝐀𝐧𝐚𝐥𝐠𝐞𝐬𝐢𝐚 𝐢𝐧 𝐓𝐇𝐑: 𝐀𝐫𝐞 𝐖𝐞 𝐒𝐚𝐜𝐫𝐢𝐟𝐢𝐜𝐢𝐧𝐠 𝐏𝐫𝐨𝐩𝐫𝐢𝐨𝐜𝐞𝐩𝐭𝐢𝐨𝐧 𝐟𝐨𝐫 𝐏𝐚𝐢𝐧 𝐑𝐞𝐥𝐢𝐞𝐟?
#RegionalAnesthesia #THR #HipReplacement #PENGBlock #HipAnalgesia #UltrasoundGuided #PainManagement #Anesthesia
#MedEd #FOAMed #MedTwitter #GrayAreasInRA #GrayZonesinRA
𝐆𝐑𝐀𝐘 𝐙𝐎𝐍𝐄𝐒 𝐢𝐧 𝐑𝐀
1️⃣ 🔍 𝐏𝐨𝐬𝐭𝐞𝐫𝐢𝐨𝐫 𝐁𝐥𝐨𝐜𝐤 - 𝐖𝐡𝐚𝐭 𝐀𝐫𝐞 𝐖𝐞 𝐑𝐞𝐚𝐥𝐥𝐲 𝐃𝐨𝐢𝐧𝐠?
Posterior pericapsular block is, in essence:
🔹 Parasacral Ischial Plane Block
(a longitudinal probe variant of the parasacral sciatic approach)
🔹 Sciatic nerve exits below piriformis
🔹 LA deposited deep to piriformis → close proximity to sciatic nerve
Increasing volume → progressive sciatic involvement
🔹 Evidence speaks clearly:
5–10 ml → no motor block
15 ml → 62% sciatic motor blockade
👉 This is not precision targeting, rather its a volume-dependent spread.
2️⃣ 🧠 𝐏𝐨𝐬𝐭𝐞𝐫𝐢𝐨𝐫 𝐂𝐚𝐩𝐬𝐮𝐥𝐞: 𝐍𝐨𝐭 𝐉𝐮𝐬𝐭 𝐚 𝐏𝐚𝐢𝐧 𝐆𝐞𝐧𝐞𝐫𝐚𝐭𝐨𝐫
The posterior hip capsule is functionally rich:
🔹 Mechanoreceptors (Ruffini, Pacinian)
🔹 Proprioceptive fibers
🔹 Nociceptors
👉 Therefore:
❌ Blocking it does not selectively relieve pain
⚠️ It also disrupts joint position sense and stability feedback
3️⃣⚡ 𝐓𝐡𝐞 𝐌𝐲𝐭𝐡 𝐨𝐟 “𝐌𝐨𝐭𝐨𝐫-𝐒𝐩𝐚𝐫𝐢𝐧𝐠”
The so-called motor-sparing effect is:
🔹Volume-dependent, not anatomically selective.
🔹Low volume → sciatic trunk spared → appears motor-sparing.
🔹Higher volume → sciatic involvement → motor block
👉 This reflects dose–spread dynamics, not selective neural targeting
4️⃣🚶 𝐖𝐡𝐚𝐭 𝐃𝐨 𝐖𝐞 𝐔𝐥𝐭𝐢𝐦𝐚𝐭𝐞𝐥𝐲 𝐀𝐜𝐡𝐢𝐞𝐯𝐞?
✔️ Analgesia (anterior + posterior capsule)
✔️ Apparent preservation of motor function
❗ But also:
⚠️ Loss of proprioceptive input
⚠️ Impaired joint feedback
⚠️ Potential functional instability or delayed mobilization
5️⃣ 💊 𝐖𝐡𝐲 𝐏𝐄𝐍𝐆 𝐀𝐥𝐨𝐧𝐞 𝐌𝐚𝐲 𝐒𝐞𝐞𝐦 𝐈𝐧𝐚𝐝𝐞𝐪𝐮𝐚𝐭𝐞?
This is often misinterpreted.
❌ Not due to insignificant posterior capsule pain
🔹 More likely due to sparing of
T12 and LFCN dermatoms in surgical incision.
👉 Residual pain is largely cutaneous, not posterior capsular dominance
6️⃣ 🧬 𝐅𝐢𝐛𝐞𝐫 𝐏𝐡𝐲𝐬𝐢𝐨𝐥𝐨𝐠𝐲: 𝐓𝐡�� 𝐔𝐧𝐝𝐞𝐫𝐥𝐲𝐢𝐧𝐠 𝐓𝐫𝐮𝐭𝐡
🔹 Sequence of blockade:
B > Aδ ≥ C > Aγ > Aβ > Aα
Sympathetic → Pain → Proprioception → Touch → Motor
🎯 True Goal in THR Analgesia -
Not just “motor-sparing”
👉 Aim for:
✔️ Effective analgesia
✔️ Motor preservation
✔️ Proprioceptive integrity
💥 𝐅𝐈𝐍𝐀𝐋 𝐓𝐀𝐊𝐄𝐀𝐖𝐀𝐘
👉 Analgesia without stability is not success.
👉 Volume may spare motor, but not proprioception.
👉 Block Smart. Preserve Stability, Not Just Movement.


🚫💉 “Goodbye Obturator Block?” – Why Isolated ON Block Is Becoming Obsolete
#RegionalAnaesthesia #ObturatorNerve #TURBT #PENGBlock #HipAnalgesia #KneeAnalgesia #AdductorCanalBlock #DSB #IPACK #PoplitealPlexus #NeuroMuscularBlockade #Anaesthesia #RAInnovation
#TipOfTheDay #MyRATips
Tip of the Day:
Blocking the obturator nerve (ON) separately is gradually becoming less useful in modern regional anaesthesia - because in most clinical scenarios, its role is already covered indirectly or doesn’t solve the real problem. ✅
🧠 1) For Anaesthesia:
ON is already “included”
For surgical anaesthesia, when we perform proximal plexus-level blocks like:
✅ Lumbar plexus block / Lumbosacral plexus block
…the obturator nerve gets covered as part of the plexus itself.
➡️ So a separate ON block adds minimal extra benefit.
🦴 2) For Hip Analgesia:
We target the sensory branches
For hip joint pain, the clinically meaningful component is the sensory articular contribution of ON - and that is already addressed by modern hip blocks like:
✅ PENG block
✅ SIFI block
✅ Iliopsoas plane block
➡️ These are procedure-specific analgesic blocks, not isolated motor-targeting ON blocks.
🦵 3) For Knee Analgesia:
ON sensory components are already covered
✅ Anterior division (sensory component) gets covered in:
Subsartorial plexus block/
Femoral triangle block/DSB
✅ Posterior division contribution gets covered in:
Popliteal plexus block,
ACB,
iPACK,
Popliteal fossa block,
DSB,
4-in-1 block
➡️ So most obturator-linked knee pain pathways are already blocked indirectly.
🩺⚡ 4) Even in TURBT (Lateral Wall Tumours):
ON Block Often Fails
This is where many believe ON block is “mandatory”, but the physiology explains why it can still be unreliable.
✅ The real issue in TURBT:
During lateral bladder wall tumour resection, the obturator nerve can be directly stimulated by cautery, leading to sudden:
⚡ Obturator jerk (adductor spasm)
⚠️ bladder wall injury / perforation risk
🔥 Why ON block becomes ineffective here:
✅ Anything distal to the point of block can still create conduction and stimulate the muscle.
✅ The cautery stimulus is often directly on/near the nerve, not through pain pathways.
So in TURBT, it’s not just about “sensory block”…
➡️ it’s about stopping the efferent motor response.
🎯 5) The core limitation:
You can’t reliably block “ distal to stimulation ”
To fully prevent jerk, ideally the block should be placed:
✅ distal to the expected stimulation point on the nerve
BUT practically…
❌ Obturator nerve has frequent anatomical variations
❌ The stimulation may occur at unpredictable points
❌ Blocking on the common trunk vs individual divisions is hard to standardize
And to make it worse:
⚠️ In 15–30%, an Accessory Obturator Nerve contributes to muscular innervation.
➡️ So even a “perfect” ON block may miss motor supply.
✅ Bottom Line
🔥 In TURBT lateral wall tumours, nothing is fully reliable except direct neuromuscular blockade (NM blockade).
✅ Because the jerk is often due to direct nerve stimulation, and anatomical variations + accessory innervation make isolated ON block unpredictable.
🧠 Final Takeaway
🎯 Target the procedure, not the nerve.
And in TURBT lateral wall resections:
✅ ON block may help sometimes…
🚫 but NM blockade remains the most dependable solution when obturator jerk risk is high.

🩺 A Walk to Remember: Anesthetic Management of a 111-Year-Old Supercentenarian with Hip Fracture
#Anesthesia #RegionalAnesthesia #ElderlyCare #Supercentenarian #HipFracture #Cureus #CaseReport #PENGBlock #SIFIBlock #ERAS #Anesthesiology #MedicalInnovation #PerioperativeCare #HumanResilience
🔗 https://t.co/Wbm1H8wIKV
Highlights:
🌍 Successful surgery in a 111-year-old supercentenarian — one of the world’s rarest reported cases.
💉 Ultra-low-dose neuraxial anesthesia with proactive hemodynamic support.
🧠 Opioid-free analgesia using PENG & SIFI blocks — preserving cognition.
❤️ Frailty-based, physiology-driven strategy ensuring safety beyond age barriers.
🚶♂️ Early ambulation through ERAS — turning vulnerability into vitality.
📋 Includes institutional dosing protocol & supercentenarian-specific ERAS pathway.
✨ A true testament to human resilience — when science, precision, and compassion converge.


Meta-analysis on the #PENGblock for #THA confirms it's a viable option for #PainControl Reduces opioid use & is noninferior to other common blocks!
🔗https://t.co/Cn9LwVxAg4
#EFORT #EORJournal #Traumatology #Orthopaedics #MedicalResearch #Anesthesiology #PerioperativeCare


Bloqueo del grupo nervioso pericapsular (PENG), que es excelente para el control del dolor con preservación motora en fracturas de cadera. #osuem #PENGblock #teamultrasound

Our #POCUS pamphlet this week explores the pericapsular nerve group (PENG) block, which is great for motor-sparing pain control in hip fractures! #osuem #PENGblock #teamultrasound


Check out the August issue of the #miniflipbook. Articles on: #insulin # irondeficiency #adamgammadex #isoflurane #anaemia #PENGblock #opioids #pain #neuropatheticpain #PGF-15 #regioanlanaesthesia https://t.co/PHRdQtbaux

Check out the August issue of the #miniflipbook. Articles on: #insulin # irondeficiency #adamgammadex #isoflurane #anaemia #PENGblock #opioids #pain #neuropatheticpain #PGF-15 #regioanlanaesthesia https://t.co/PHRdQtbaux

“🦴 From Skin to Capsule: Smart Blocks for Every Hip Cut!”
#THR #RegionalAnesthesia #PENGblock #FICB #QLblock #TAPblock #LFCNblock #SmartAnalgesia #PostOpPain #OrthoAnesthesia
#TipoftheDay
#MyRATips
Tip of the Day:
The key to Post-op analgesia after Total Hip Replacement?
Block what matters—based on Surgical approach & Innervation.
▶️ Anterior Approach
🔹 Joint Capsule (Anterior)
– Use PENG block (targets FN, ON, AON)
🔹 Skin – Upper Incision
– Subcostal (T12), Iliohypogastric (L1)
– Add TAP (subcostal/lateral) or QL block (Type 1/2)
🔹 Skin – Mid/Lower Incision
– IIN, GFN, LFCN → Block with FICB, TFP, or LFCN block
▶️ Anterolateral Approach
🔹 Joint Capsule (Anterior & Lateral)
– Covered well by PENG block
🔹 Skin
– Mostly LFCN, ± IIN/GFN
– Use FICB or LFCN block
– If upper extension → add TAP/QL
▶️ Posterolateral Approach
🔹 Joint Capsule (Posterior)
– Minimally nociceptive → No sciatic block needed
– Use PENG for anterior capsule
🔹 Skin – Upper Incision
– T12, L1 (Subcostal, IHG) → TAP/QL block
🔹 Skin – Lower Incision
– LFCN → Use LFCN block or high-volume FICB
▶️ Local Anesthetic Strategy
🧪 Type:
Ropivacaine 0.2–0.25%, Bupivacaine 0.125–0.25%
💉 Volumes:
– PENG: 20 mL
– FICB: 30–40 mL
– TAP/QL: 20–30 mL
– LFCN: 5–10 mL
My go-to hierarchy for THR analgesia:
QLB > FICB > PENG + LFCN
"Block smart.
Incision-specific.
Capsule-aware.
Approach-adapted."


Congratulations on publishing a #TopDownloadedArticle @PEM_Ultrasound
https://t.co/U9AV9B4UAb
#OpenAccess
@WileyHealth @acemonline


Discover the PENG Nerve Block 🎯: a game-changer in pain control for left IT femoral fractures.
By: Dr. Anthony and Dr. Zinsou
#PENGBlock #PainFreeRecovery #POCUS #FOAMED #MedEd #emergencymedicine #ultrasound #fellowship #eusfellowship #NYP #BMH #ultrasoundcases #EUFAC #FPD

Comença el simposium d'Anestesiologia a l'Hospital del Mar. Presentació i mesa de debat amb els Drs. Fernández, Dra. Nieuwveld, Dra. Vilà, Dr. Aguilera, Dr. Ródenas i Dr. Álvarez.
#preoperatori #cirurgiamamaria #pengblock #esp
@hospitaldelmar


A veces no contamos con transductor curvo, pero en pacientes delgados es posible trabajar con un lineal. Solo considerar cambios en lo que se acostumbra ver.
🤩 Bloqueo PENG
#anestesiaregional #PENGblock

How does PENG block compare with Fascia Iliaca block for analgesia post total hip arthroplasty?
Read this systematic review in Nov '23 issue of #IJA https://t.co/q62nDRDd1u
#hipreplacement #pengblock #fasciailiaca @ASRA_Society @ESRA_Society @RegionalAnaesUK @AoraIndia
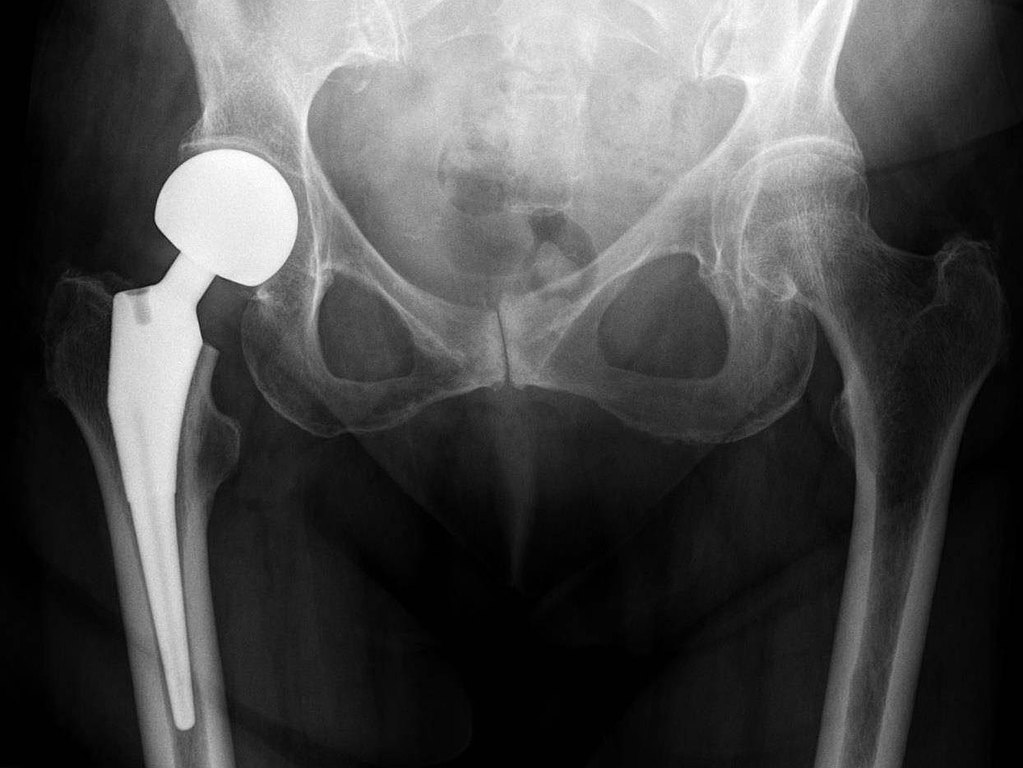
"PENG Block"
Do u know about other Pericapsular Blocks of Hip joint?
#PENGblock
#Pericapsularblocks
#Hipjointanalgesia
#RAinHipSx
#IPPBlock #IlioPsoasPlaneBlock
#ABFNBlock
My 10 Points:
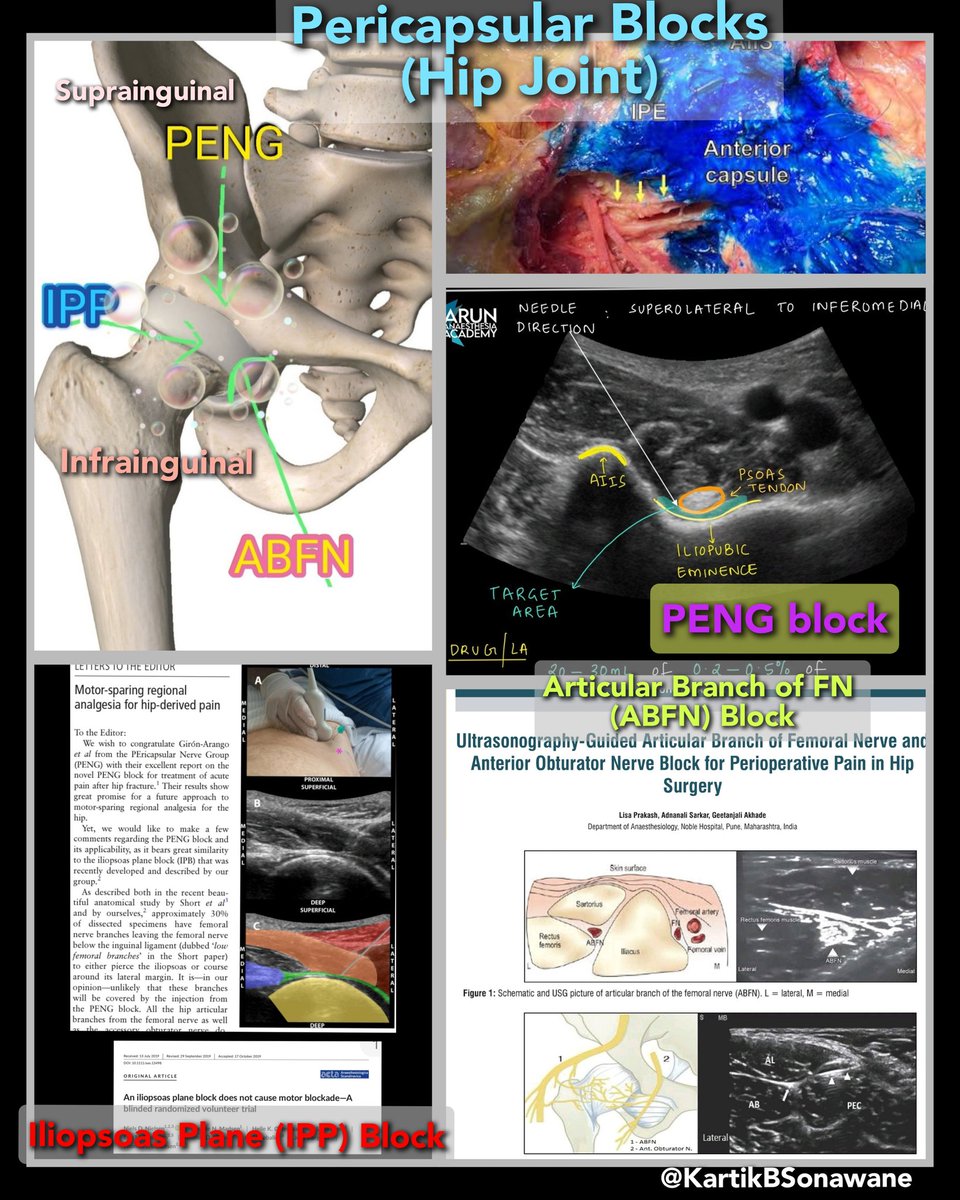
1. A PENG block involves a pericapsular plexus consisting of articular branches (arising from FN, OBN, and accessory OBN) that supply the anterior hip joint capsule. However, two infrainguinal blocks [Iliopsoas plane block (IPP) and Articular Branch of FN (ABFN) block] also cover capsular innervation.
Total 3 Pericapsular blocks: 1 suprainguinal (PENG) and 2 infrainguinal (IPP and ABFN).
2. An IPP block with 5-10 ml can have the same coverage as PENG. ABFN block with 20 ml involves articular branches of FN only (not OBN/AOBN).
3. A PENG block with LA volume of up to 20 ml is required to involve all articular branches. However, lower volumes (10-15ml) can have a patchy effect due to inadequate coverage.
4. A PENG block with higher volumes (30-40 mL) is also described to provide analgesia to the acetabulum #, subtrochanteric #, or femoral shaft #. Higher volumes may involve articular and parent branches (FN and OBN).
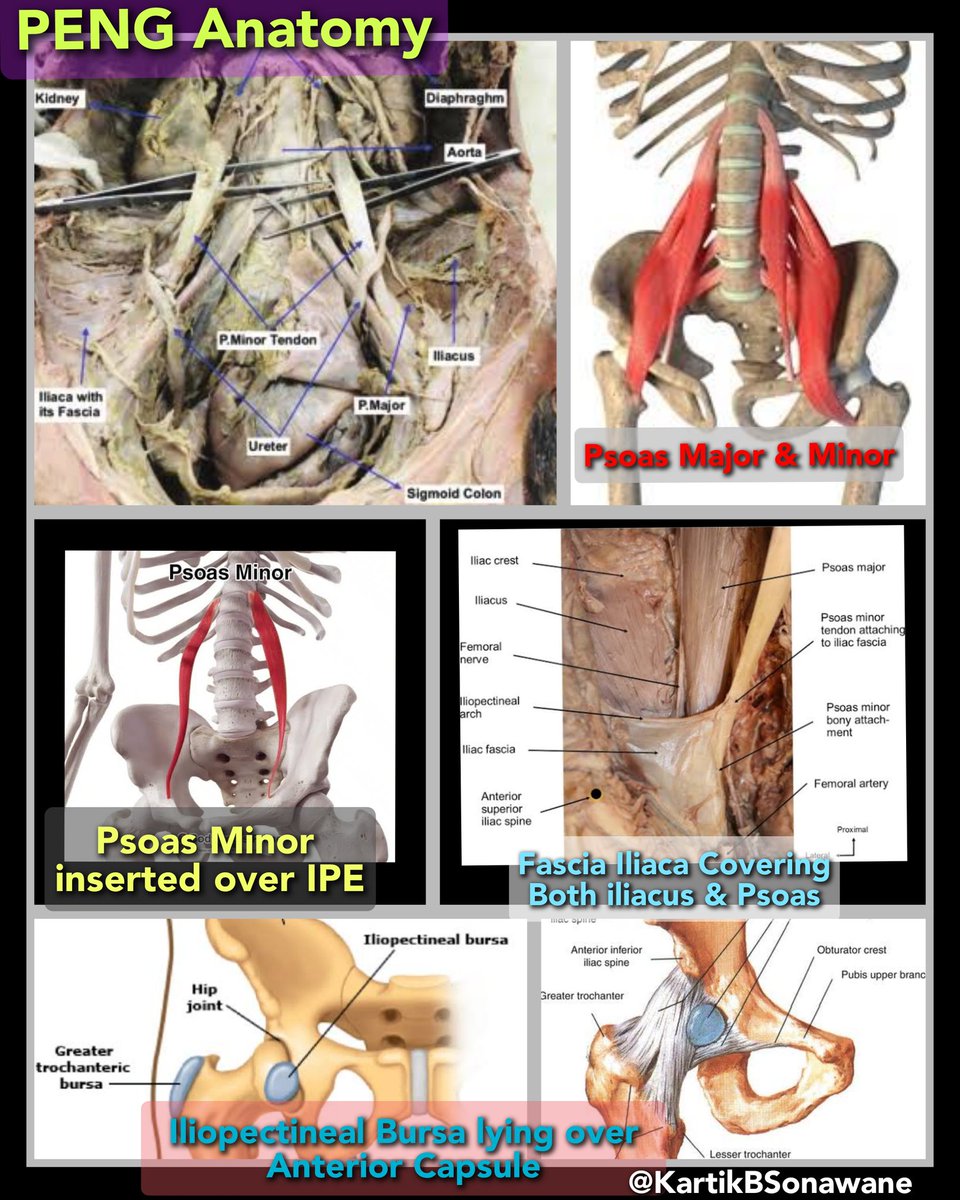
5. The target site in the PENG block is the iliopubic eminence (IPE), where the Psoas Minor tendon gets inserted. It appears as a hyperechoic round structure over IPE that gets elevated during LA deposition. The Psoas Major tendon gets inserted over the lesser trochanter of the femur. Both Psoas muscles lie medial to the iliacus muscle within the fascia iliaca.
6.PENG block region can be divided into 3 Zones: WHITE (below Psoas tendon), BLACK (near the femoral nerve and vessels), and GRAY (below the black zone and above the Psoas tendon). The ideal injection site is below the Psoas tendon, i.e., the WHITE zone. BLACK zone injection can be associated with Quadriceps weakness due to FN involvement. GRAY zone injections are common in obese and difficult anatomy patients, leading to mixed effects depending on LA Concentration and Volume.
7. Quadriceps weakness is mainly due to the involvement of FN either due to LA volume (>20 ml), LA concentration (Higher>Lower), or proximity (BLACK zone).
8. The analgesic effect of PENG block is mainly due to the blockade of all innervations of the anterior capsule of the Hip joint. Some suspect possible joint analgesia due to LA deposition in the iliopectineal bursa beneath the psoas tendon, which communicates with the hip joint. However, this bursa lies mainly over the anterior capsule and has no connection to the joint cavity.
9. Possible (SPECULATED )complications of PENG block Include - Laterally, injury to LFCN at the needle entry point while directing the needle towards the target site. Medially, the needle can enter the ureter, especially when the bladder is full (pushing the ureter close to the target site). At the target site, iliopectineal bursitis can develop due to direct needle injury.
10. PENG provides optimum and faster onset analgesia (resting and dynamic) when used as an “on-arrival” block due to complete coverage of the richly innervated and more nociceptive anterior capsule. PENG + LFCN = Perioperative analgesia option.
For other details, Plz Click on,
https://t.co/gmSnN9tOYE
https://t.co/wrOAhHBhri
https://t.co/umqGWp7KHt
If you know any of the interesting points about PENG block, Plz Share.


With @DrPhilipPeng 😀 #PENGblock is a good choice for #regionalanesthesia for postoperative analgesia in both pediatric and adult hip surgeries! And works as a miracle especially in kids! @drEmilBosinci @baby_blocks @ESRA_Society #ESRAworld2023


Very informative, effective block I use routinely in hip/IT fx. No motor blockade is a +. Should be in every regional anesthesiologist arsenal #PENGblock

Read about the PEricapsular Nerve Group (PENG) block in the latest #ASRANews! The #PENGblock targets sensory innervation to the anterior hip capsule during total hip arthroplasty (#TKA) and hip fractures... the second most common joint replacement surgery! https://t.co/oKEtZlXccY
Read about the PEricapsular Nerve Group (PENG) block in the latest #ASRANews! The #PENGblock targets sensory innervation to the anterior hip capsule during total hip arthroplasty (#TKA) and hip fractures... the second most common joint replacement surgery! https://t.co/oKEtZlXccY

#SonoGames23 is TODAY! Check out the Round 0 #1 Album Artwork submission by @VCUEM / @Ultrasound_VCU on the #PENGBlock!
https://t.co/ZlJvkBCZ0Q

Trends for you
Most Popular Users

Elon Musk 
@elonmusk
241.7M followers

Barack Obama
@barackobama
119M followers

Cristiano Ronaldo
@cristiano
114.4M followers

Donald J. Trump
@realdonaldtrump
111.9M followers

Narendra Modi
@narendramodi
107.2M followers

Rihanna
@rihanna
98.7M followers

NASA
@nasa
92.4M followers

Justin Bieber
@justinbieber
91.8M followers

KATY PERRY
@katyperry
90M followers

Taylor Swift
@taylorswift13
83.9M followers

Lady Gaga
@ladygaga
75.4M followers

Virat Kohli
@imvkohli
73.4M followers

Kim Kardashian
@kimkardashian
70.9M followers

YouTube
@youtube
68.8M followers

Neymar Jr
@neymarjr
66.4M followers

Bill Gates
@billgates
65.2M followers

Selena Gomez
@selenagomez
63.1M followers

The Ellen Show
@theellenshow
62.3M followers

CNN
@cnn
61.8M followers

X
@x
60.7M followers