Evidence over ideology. Explaining science in context, exposing harmful misinformation, sharing references—and posting reminders the world is beautiful.
1/10
America is losing scientific expertise from its federal government at an extraordinary rate.
Thousands of researchers, physicians, engineers, and other specialists have left agencies responsible for protecting public health, evaluating medicines, forecasting disasters, and supporting scientific discovery.
We can measure the departures. The longer-term consequences are harder to quantify.
Let’s examine what the evidence tells us.
@jeffreytucker Jeffrey, I knew we could find some common ground, eventually.
Trumps understanding of tariffs reminds me of the way a mafia don looks at a protection rackets.
IMO, it may take a decade or more to undo the damage he has caused the US.
🚨BREAKING: Attorney General Todd Blanche on Thursday said the U.S. Department of Justice (DOJ) might launch more California-style lawsuits to block states from counting ballots for the midterm election. https://t.co/2Bp5pAhE5f
H5N1 has been confirmed in captive mink on a Utah farm — and reports describe substantial mortality.
That deserves attention.
Not because it means a human pandemic is imminent. It doesn’t.
But when an avian influenza virus repeatedly enters dense populations of mammals, scientists pay attention for a very specific reason:
It gives the virus opportunities to adapt.
A thread on what we know — and what we don’t.
2/ Tenebra, knowing you’re referring to Mary Talley Bowden makes your concern considerably more specific.
Bowden is an ENT and sleep medicine physician, with no demonstrated specialist training in thrombosis or pulmonary vascular disease.
But there’s a more consequential issue here.
In her July interview with Tucker Carlson, Bowden invoked Fauci’s reported pulmonary embolism alongside his COVID vaccinations, insinuating a causal relationship without demonstrating one.
Fauci’s diary actually described a pulmonary infarction. Its cause was not established in the publicly reported entry.
We also have substantial epidemiological evidence showing no increased PE risk following Moderna vaccination, while recognizing the distinct, rare thrombotic syndrome associated with certain adenoviral vaccines.
An ENT can certainly discuss pulmonary embolism. But when a physician moves from discussing a clinical event to suggesting vaccine causation, the burden of evidence becomes considerably greater.
That’s where I’d focus the criticism. The problem isn’t simply her specialty. It’s the unsupported inference.
1/ Tenebra, you’re absolutely right to question the choice of expert. A hematologist specializing in thrombosis, a pulmonary vascular specialist, or a cardiologist experienced in PE would be natural choices.
One useful addition: the 2026 AHA/ACC pulmonary embolism guidelines actually emphasize multidisciplinary PE response teams.
An ENT could conceivably have relevant expertise, but that expertise needs to be demonstrated, not assumed from the letters after their name.
And if the discussion involves vaccine-associated PE, I’d want someone who understands thrombosis and vaccine safety epidemiology. Temporal association isn’t proof of causation.
The strongest question isn’t simply why an ENT was invited. It’s what qualifies this particular ENT to speak authoritatively on the subject, and whether the evidence supports their claims.
@JoGorilla10@KarenStrine3 You’re not capable of having a constructive dialogue.
Your MO is like that of a drive by shooter spraying bullets in all directions.
You’ve earned yourself a block. Well done.
Dr. Peter Hotez has raised an important question about America’s measles resurgence.
What happens to infants who are old enough to lose the protection they received from their mothers, but too young for routine measles vaccination?
As of October 15, the CDC had recorded 4,410 U.S. measles cases in 2026, nearly twice the total reported during all of 2025.
For babies between roughly 5 and 11 months of age, this raises an uncomfortable question: should we be offering measles vaccination earlier?
@JoGorilla10 Fuck off.
Dr. Hotez knows more about autism than a thousand contrarians like yourself.
Accusing Dr Hotez of such malfeasance should be beneath you.
The simple truth is you don’t know what you’re talking about.
It’s clear, you’ve had little if any formal training (as displayed in each of your tweets, I’ve responded to). You have access to the world’s knowledge but without the framework to access it.
Go back and read what I wrote to you…if you truly understand what Zi wrote you should be able to answer the questions I presented clearly. But you’ve made zero attempt to do so.
You respond like a troll who pretends to know things…but without the clarity of thought to express it in a meaningful, falsifiable way. Science dude, science.
You were asked a straightforward scientific question: identify the alleged neurotoxins and carcinogens in MMR, their concentrations, and the evidence that those doses cause harm.
Instead, you’ve offered a misleading analogy, an unsupported immunological assertion, and a collection of insults.
Let’s address your latest claims.
First, vaccine dosing is not conventional drug dosing. MMR’s standard 0.5 mL dose is designed to stimulate an immune response, not achieve a drug concentration proportional to body weight. Vaccine antigen doses are established through immunogenicity and safety studies. A 4-pound newborn isn’t even eligible for MMR vaccination.
Second, your claim that the immune system of a 6–11-month-old infant is approximately equivalent to that of a geriatric patient is scientifically indefensible. Infant immunity is developing; immunosenescence involves age-related deterioration and remodeling of immune function. Both can involve vulnerabilities, but they are not immunologically interchangeable.
Third, early MMR vaccination is not routine. It is recommended from 6 months under specific circumstances, including international travel or qualifying outbreaks. An early dose does not replace the two subsequent routine doses, partly because younger infants may mount less reliable immune responses.
And severe immunodeficiency is an established contraindication to MMR. Your argument ignores that distinction entirely.
Finally, we’re still waiting for you to identify those supposed carcinogens and neurotoxins. MMR contains neither thimerosal nor aluminum adjuvants. Its ingredients are publicly documented.
You can keep repeating frightening words and personal insults, but neither constitutes evidence.
Name the substance. Quantify the exposure. Demonstrate the harm.
That’s how toxicology works.
If you cannot do those three things, you don’t have a scientific argument. You have rhetoric masquerading as one.
If you came of age inn the 70’s you likely witnessed the magic of Elton John and Bernie Taupin.
Here Rick Beato talks with Taupin about that magical relationship.
How Bernie Taupin and Elton John Became The Greatest Songwriting Duo https://t.co/haHuAzf7j0 via @YouTube
1/3
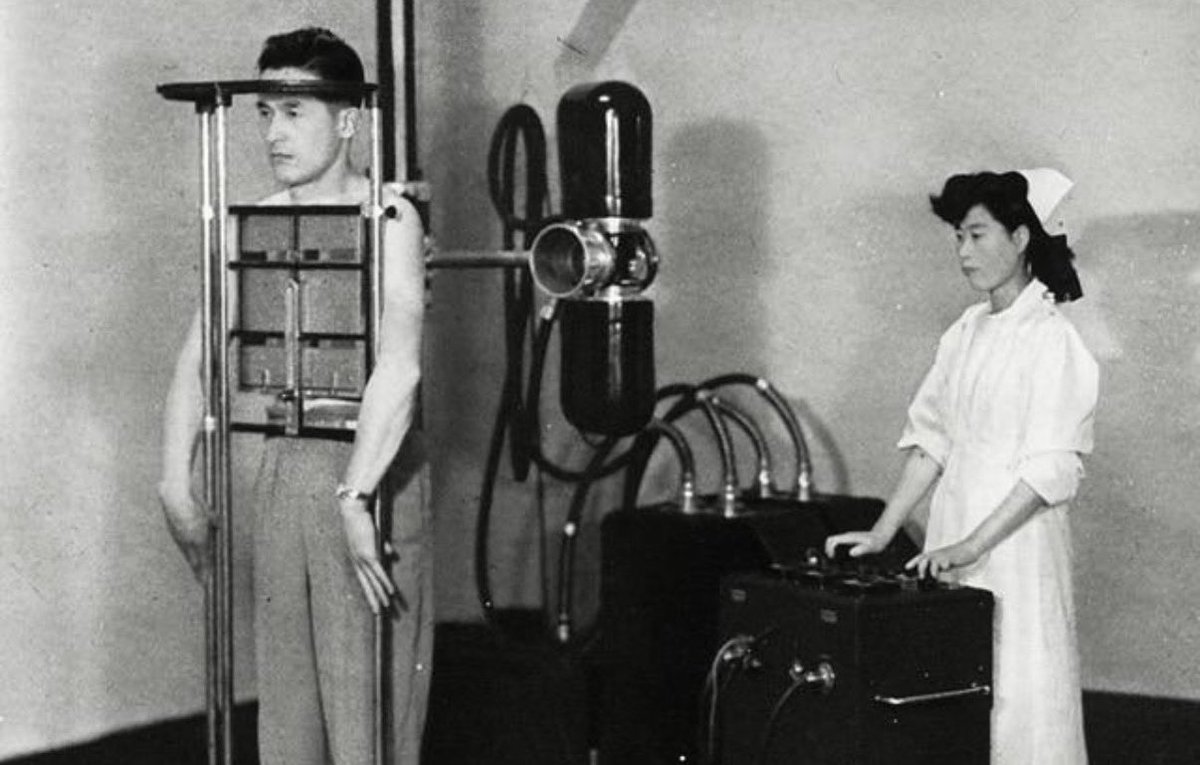
On August 9, 1945, a 37-year-old Japanese physician was working at Nagasaki Medical College when an American atomic bomb exploded over the city.
His name was Dr. Takashi Nagai.
He was a radiologist, a husband, and the father of two young children.
And he was already dying.
In June 1945, just two months before the bombing, Nagai had been diagnosed with leukemia. Years of occupational radiation exposure during his work with X-rays were believed to have caused the disease.
His physicians reportedly gave him approximately three years to live.
At 11:02 a.m., the atomic bomb detonated over Nagasaki, devastating the medical college and surrounding neighborhoods.
Nagai survived, but flying glass severed an artery near his right temple. He suffered severe bleeding.
His wife, Midori, was at their home in the Urakami district. She was killed in the bombing.
Their children, Makoto and Kayano, survived because they had been evacuated to the countryside.
Within moments, Nagai had lost his wife, his home, and much of the medical community in which he had spent his career.
He was seriously injured, already suffering from leukemia, and surrounded by thousands of people desperately needing medical attention.
Yet despite his condition, he helped organize medical relief.
The physician who had spent years studying radiation was now confronting the consequences of the most destructive use of radiation the world had yet witnessed.
And the medical catastrophe was only beginning.
Sources | At the Edge of the Unknown — Story 02
Nagai Takashi Memorial Museum, Nagasaki City:
Life and work:
https://t.co/AlmDZLrcNf
Under the Mushroom Cloud:
https://t.co/csBLRYtfgk
Relief of the Atomic Bomb Victims:
https://t.co/WlomDAda6k
Leaving These Children Behind:
https://t.co/5inJWGpPnk
Nagasaki Atomic Bomb Museum — Dr. Takashi Nagai:
https://t.co/9sppOjrJwK
Historical note: Nagai’s leukemia was diagnosed before the bombing and was attributed to occupational radiation exposure. The precise contribution of his subsequent bombing-related exposure to his later decline cannot be established.
You’ve managed to pack several scientifically misleading claims into a single sentence. Let’s examine them.
“Megadoses of neurotoxins”? Name the substance, its concentration, and the evidence that the administered dose produces neurological toxicity. The MMR vaccine contains neither mercury-based preservatives nor aluminum adjuvants. Its ingredients are publicly documented in FDA-approved prescribing information.
“Carcinogens”? Which ingredient, at what dose, has been demonstrated to cause cancer through MMR vaccination? Simply attaching a frightening label to a chemical isn’t evidence of carcinogenic risk.
“Live viruses”? Yes. MMR contains live attenuated viruses, deliberately weakened to induce protective immunity. This is elementary vaccinology, not some concealed danger.
“The immunodeficient”? You’re confusing the developing immune system of a healthy infant with clinical immunodeficiency. Severe immunodeficiency is specifically a contraindication to MMR vaccination. During outbreaks, eligible infants aged 6–11 months may receive an early dose under public health guidance.
Now consider what you’ve conveniently omitted.
Wild-type measles can cause pneumonia, encephalitis, permanent neurological injury, and death. It can also impair previously acquired immune protection through a phenomenon called immune amnesia.
MMR has genuine, documented adverse effects, including a small risk of febrile seizures. Those risks should be discussed accurately.
If you want to make a toxicological argument, provide actual toxicology: substance, dose, exposure, biological mechanism, and evidence of harm.
Until then, you’re offering a collection of alarming words dressed up as a scientific argument.
Fear-inducing vocabulary is no substitute for evidence.