#ICU Evidence #002:
Earlier vasopressin in septic shock (VASSPR trial): are we treating the patient or the norepinephrine dose?
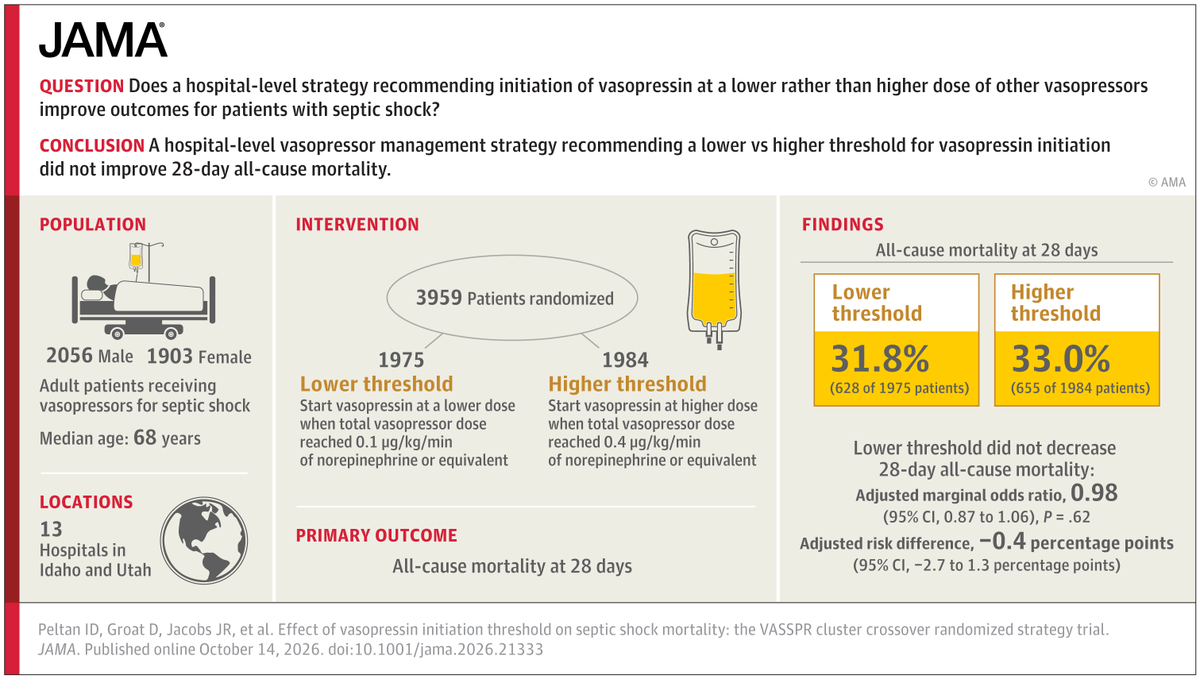
Add vasopressin at a norepinephrine-equivalent dose of 0.1 or 0.4 µg/kg/min? VASSPR tested these strategies across 13 US hospitals and nearly 4,000 patients. It changed practice, but not outcomes. I think it also raises a more interesting question:
Should vasopressor dose alone tell us when to add another hemodynamic intervention?
This was a pragmatic cluster-crossover trial. Hospitals alternated monthly between recommending fixed-dose vasopressin at a norepinephrine-equivalent dose ≥0.1 µg/kg/min (0.1 arm) or ≥0.4 (0.4 arm). Clinicians retained discretion, so this was not vasopressin vs placebo or a protocol that overrode clinical judgment.
Among patients reaching the relevant vasopressor range, vasopressin was used in 68.0% in the 0.1 arm vs 42.7% in the 0.4 arm. But 28-day mortality was 31.8% vs 33.0%, 90-day mortality 37.9% vs 38.4%, and clinically significant arrhythmias 18.4% vs 18.1%. None of the other secondary clinical outcomes materially differed either.
Here is what bothers me. Two patients on exactly the same norepinephrine dose may have profoundly different circulations: vasoplegia with preserved cardiac output, septic cardiomyopathy with impaired forward flow, RV dysfunction, persistent tissue hypoperfusion despite acceptable macrohemodynamics, or some combination.
A norepinephrine dose tells us how much drug we are giving, not WHY the patient remains in shock.
So I struggle with using a drug-dose threshold to trigger another major hemodynamic intervention. Starting vasopressin changes vascular tone and therefore the loading conditions under which the heart and circulation operate. Before treating the blood pressure, I want to understand the circulation.
POCUS is an excellent bedside tool here: LV and RV function, chamber size, important valvular or pericardial pathology, and clues about filling and forward flow, integrated with examination, perfusion, lactate trajectory, and other hemodynamic data.
This also brings to mind the four-hemodynamic-interface model proposed by @ThinkingCC and colleagues. Increasing vascular tone may be exactly what a profoundly vasoplegic patient needs. In another phenotype, excessive vasoconstriction could adversely affect ventricular-arterial coupling (Interface I, the heart pumping into the arterial system) and potentially arterial-to-microcirculatory coupling (Interface II, translating arterial pressure and flow into tissue perfusion). A higher MAP is not necessarily better hemodynamics.
And we should look again after starting vasopressin. Did MAP rise? Fine. But what happened to cardiac function, forward flow and tissue perfusion? Is the RV tolerating the new loading conditions? Can catecholamines actually be reduced? Otherwise, hemodynamic management risks becoming “set it and forget it”: reach a norepinephrine threshold → add vasopressin → celebrate the MAP → move on.
One safety finding caught my attention. Clinically diagnosed cardiogenic shock occurred in 7.4% in the 0.1 arm vs 6.3% in the 0.4 arm (adjusted OR 1.19, 95% CI 0.93–1.54). This was an exploratory endpoint and the difference was not statistically significant, so I would not interpret it as evidence that earlier vasopressin causes cardiogenic shock.
I do question the endpoint itself. Cardiogenic shock was captured as a clinical diagnosis rather than defined by a pre-specified objective hemodynamic phenotype. I appreciate that systematically phenotyping cardiac function in a pragmatic 4,000-patient trial is not trivial. I’d still want something more objective than a clinical diagnosis, especially with echo this accessible.
There’s some irony here: we study when to alter vascular tone, see a hint of a cardiac signal, and still know little about what the heart and circulation were actually doing.
My criticism is of the paradigm, not the investigators. Running a cluster-crossover trial across 13 hospitals and actually changing bedside vasopressin use is an impressive accomplishment. VASSPR answers the pragmatic policy question it was designed to answer.
What it cannot tell us is whether earlier vasopressin might benefit one hemodynamic phenotype while being unhelpful, or potentially disadvantageous, in another.
Perhaps our next trials should ask less “What norepinephrine dose have we reached?” and more:
“Why does this patient still need norepinephrine, and what happened after we intervened?”
“Pragmatic” explains the design. It does not replace physiology.
#JAMA #FOAMcc #FOAMed
#ICU Evidence #001:
Dobutamine during (mostly) abdominal surgery for septic shock: who actually needs it?
A new multicenter RCT from China randomized 584 patients with septic shock undergoing surgical source control, predominantly abdominal, to intraoperative dobutamine + norepinephrine vs norepinephrine alone.
The headline is impressive: AKI within 7 days fell from 34.7% to 22.8%.
But it is worth looking under the hood:
→ Creatinine-only AKI: 15.5% vs 18.7%
→ Urine-output-only AKI: 0.7% vs 6.8%
→ Both criteria: 6.6% vs 9.2%
A substantial part of the AKI separation came from urine-output-defined AKI. That doesn't invalidate the finding, but it is particularly interesting when the intervention is a hemodynamically active drug that may influence renal perfusion and urine output.
The physiology is interesting too. With dobutamine, lactate was lower at 1 h (2.3 vs 2.8 mmol/L) and at the end of surgery (2.2 vs 2.6), ScvO₂ was higher at the end of surgery (80.4% vs 77.6%), and capillary refill time was shorter. Norepinephrine requirements were also lower: mean 0.11 vs 0.15 μg/kg/min and maximum 0.17 vs 0.23 μg/kg/min.
So dobutamine clearly did something physiologically. But here is my problem: only 82/584 patients (14%) underwent advanced hemodynamic monitoring. Among those with paired measurements, cardiac index changed +0.5 vs −0.2 L/min/m² from baseline to the end of surgery (between-group difference +0.72 L/min/m²).
Who actually needed an inotrope? Low cardiac output? Septic cardiomyopathy? Vasoplegia with preserved/high CO? Persistent hypoperfusion despite adequate flow?
The trial randomized the drug—not the physiology.
And here is a thought experiment: what if, instead of routinely adding dobutamine, we added a fixed dose of vasopressin? Could we also produce a favorable renal signal through an entirely different hemodynamic mechanism? Possibly. VANISH previously suggested a renal signal with vasopressin, including less kidney replacement therapy, despite a neutral primary outcome.
My point is not that vasopressin would necessarily have been better. It is that improving a renal endpoint with a vasoactive drug does not necessarily tell us which hemodynamic abnormality we corrected or whether that abnormality was present in the first place.
Another interesting observation concerns arrhythmias. Despite more tachycardia with dobutamine (41.0% vs 29.9%), atrial fibrillation was similar (2.8% vs 2.4%), as was ventricular tachycardia (0.7% in both groups). Even mean heart rate at the end of surgery was nearly identical: 97.4 vs 96.2 beats/min.
Perhaps we sometimes overestimate dobutamine's arrhythmogenic contribution in septic shock? Or perhaps the underlying illness, concurrent norepinephrine exposure, and lower NE requirements with dobutamine matter more than we appreciate. With so few arrhythmic events and such short exposure, we cannot answer that question, but I find the observation intriguing.
Then there are the outcomes patients care about most. ICU mortality was 13.1% vs 15.6%, in-hospital mortality 17.6% vs 20.7%, and kidney replacement therapy within 7 days 9.0% vs 10.9%. None of these differences was statistically significant.
A personal note:
I don't think it is realistic to expect every critical care trial to demonstrate a mortality benefit. Mortality has too many determinants, and adequately powering every ICU trial for mortality would often be impractical.
And there is an additional consideration here: dobutamine was administered only intraoperatively, for a median of 155 minutes. Is it realistic to expect a few hours of improved hemodynamics to translate into a measurable mortality benefit weeks later? Perhaps not. Conversely, preventing kidney injury during a particularly vulnerable period could still have meaningful clinical consequences.
So I would not dismiss this trial because mortality was unchanged. But when an intervention substantially improves an intermediate endpoint, I still want to see some indication that the benefit extends toward hard, patient-centered outcomes (dialysis, duration of organ support, ICU stay, functional recovery, or survival).
My take:
Interesting physiology, a striking AKI signal, and potentially reassuring short-term arrhythmia data. But this does not yet convince me to routinely add dobutamine without knowing the hemodynamic phenotype I'm treating.
And credit to the investigators: this is a good, clinically provocative randomized trial addressing a difficult question. Medical Twitter will always find something to criticize -including me 😄- but good studies should make us think. This one does.
One final thought:
I wish we had more direct participation from Chinese clinicians and researchers on Medical Twitter. China produces important clinical research, and discussions like this would be even better if the investigators themselves could join us. We are missing valuable perspectives.
#JAMA #FOAMed #FOAMcc
https://t.co/nyKXkHhtNP
“If doctors aren’t happy with their pay, they should get a different job”
Yeah, we are.
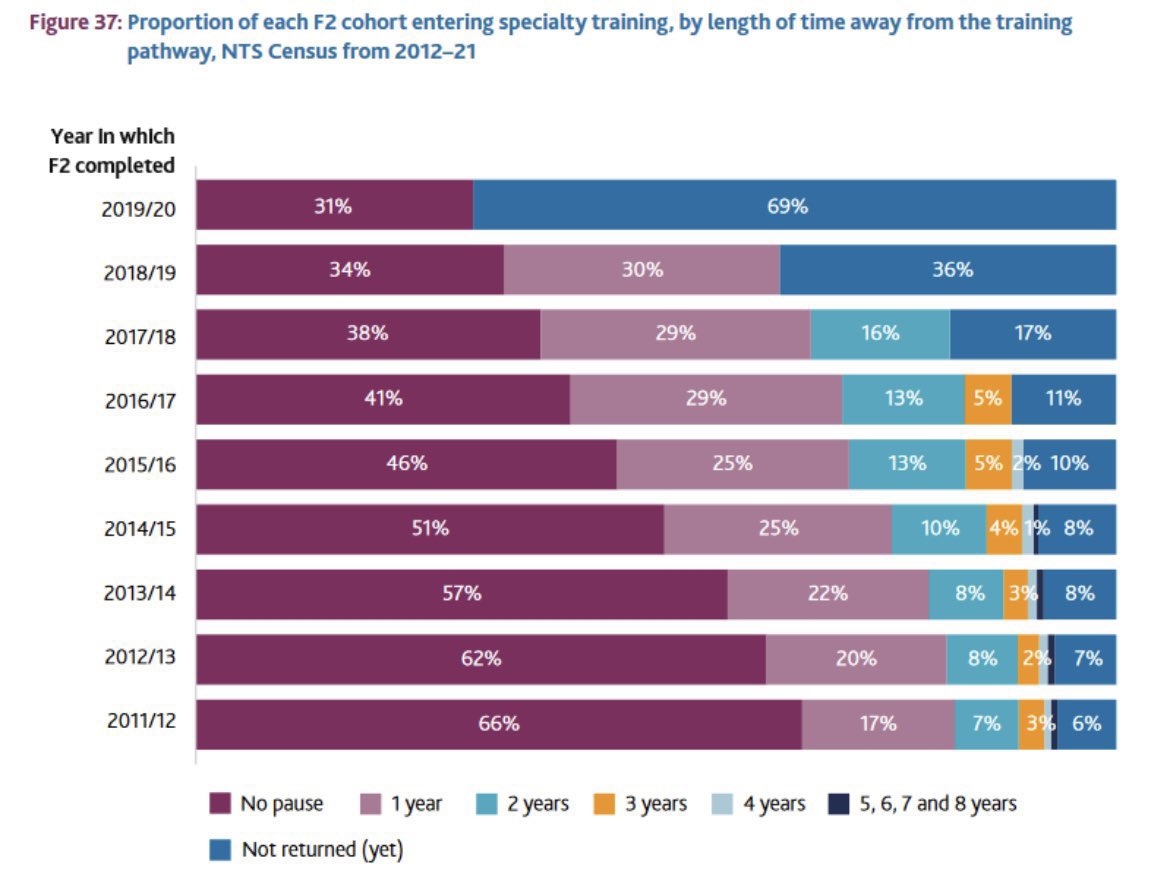
This is the most striking graph I’ve seen so far regarding the retention of doctors. Full pay restoration or watch the graph turn blue
This is untrue. We set no preconditions unlike you.
These were the additional preconditions you wanted us to sign along with the others you set to get in that room.
Weird that you would blatantly misrepresent the truth like that
Who do people trust?
Politicians or Doctors?
This guy 🤦🏻♂️ @BMA_JuniorDocs wrote to him back in mid-August saying if he did not commit to pay restoration it would lead to industrial action.
Last week he said he didn’t have a mandate to discuss pay with us & today he didn’t even turn up to meet us.
This bs👇🏻 is for the press
great news we won at @LivHospitals award night
well done to all our team involved. the photograph is only a handful of the people and specialities involved in delivering this amazing service to the people of mersey cheshire and isle of man . team work . 🩼🫁🩺🦾🚁🚑🏥🩸
Interested in AI for Medical Education? 🤖
I am really pleased to have award-winning @Recourse joining the @LivUniMedicine#healthtechinternships for a second year in a row! Great team led by @_Scott_Martin with a really fascinating platform to improve meded, and patient care.
Join us next Thursday for the first installment of our MTF Spotlight series!
Dr Abudullah Albeyatti will be talking about his journey to setting up his own medtech company and the lessons along the way.
Thursday 24th February 2022 - 9pm
https://t.co/TtkgEM6V6i
‼️CLINICAL INTERN WANTED‼️
eConsult are a venture-backed online consultation platform used in over 3,300 practices, accessing 29 million patients in the UK and generating over 1M consultations each month.
Apply on Handshake: https://t.co/zObx7lSSvo
Looking forward to @_Scott_Martin’s session tomorrow evening 👌
Come join if you’re a med student interested in MedTech, Entrepreneurship or just want to hear a bit about being a co-founder of a successful startup 🙌
🚨Tomorrow 7pm🚨
Join us a @_Scott_Martin leads a session in pitching and how to get funding as a MedTech startup.
Free to attend and open to all students at liverpool.
See FB even for full details: https://t.co/uH8oosQmAi
Come and join us on Wednesday where @_Scott_Martin, CEO and Co-founder of @Recourseai will be talking to us about pitching technique and tips on obtaining funding!
Free to attend, held over zoom and open to all students at Liverpool.
FB event: https://t.co/CLcWKvxNPs
🚨 TONIGHT AT 7pm 🚨
Dr Michael Watts, co-founder of blüm health will be talking us through the lean business model canvas!
Check out his short overview video below 👇
Join us this Wednesday as Dr Michael Watts, NHS doctor and founder of Blüm health, talks us through the lean business model canvas!
Check out his video below 👇
THIS WEDNESDAY, 7pm
The experienced and knowledgable Alistair Clarke will be holding the next session of our Innovation Programme - Medical Device Regulations.
This talk is completely free to attend even if you've missed our previous talks!
Intersted? Link below
Join us this Wednesday at 7pm for an exciting talk on trauma anaesthesia and damage control resuscitation by @simonjudemercer
Full details on Facebook event: https://t.co/21gwSRc3ek