80% of people who lose weight on Retatrutide gain it back within a year. Most of them never built the habits underneath the drug while they had it working for them.
When you come off Reta, three things stack against you at once. Your appetite comes back because the GLP-1 suppression is gone. Your resting metabolic rate drops because the glucagon piece was running your liver like a furnace, burning fat around the clock. And your body stops using food as fuel and starts storing more of it as fat, because that nutrient partitioning benefit from the GIP receptor goes with it (Regmi et al., 2024, Cell Metab).
If your tracking and your sleep were never dialed in while you were on it, coming off exposes that fast. Titrate down the same way you titrated up, and get the foundation built before you make that move.
Join the free community:
Men: https://t.co/OOmhSVZoqs
Women: https://t.co/nA8dYusu7K
Coaching:
Men: https://t.co/J7hNiHonfO
Women: https://t.co/xjXrrc9a3r
Anvil Nutrition: https://t.co/vi0MBZ0zMy
Free Tracker: https://t.co/LxqDNFSWo1
#retatrutide #weightloss #glp1 #fatloss #metabolism
Why would I go for 15mg of Reta?
This question caught my attention.
Because I currently plan to run a low dose of Reta for the foreseeable future.
Possibly, for the rest of my life.
Or, until something better comes along.
Why would I NOT take low dose Retatrutide, indefinitely?
Appetite: down
Weight: down
Waistline: down
Alcohol intake: down
Cravings: obliterated
Energy: up
Focus: up
Self confidence: up
Compliments: up
Fun Factor: through the roof
I'm not even listing labs on BP, a1c or triglycerides.
Because I haven't been to the Doctor. But we know those are / will improve.
All at 1.5mg weekly dose of Reta?
What is the downside?
Seriously, WHERE is the downside???
It's not side effects. Not at 1.5 mg weekly. Not for me.
It's not cost. Not once you get your bearings in this space.
I'm essentially paying a drug co-pay per month.
Ok, I don't actually like needles. Small downside. But I can man-up over that.
At 1.5 mg weekly, a 15 mg vial of Reta is about perfect.
10 weeks.
That's about how long we're truly comfortable keeping reconstituted Reta in the fridge.
Correct?
Be honest. We don't believe in the 28 day limit.
But we believe there IS a limit that prudence dictates. Somewhere in the 2-3 month range.
I'll take ALL the Reta15 vials.
And I'll grin all the way to the freezer.
(btw, I think the original question was a legit question)
She reversed Hashimoto’s in 16 weeks
(personal case study & testimonial)
And I’m giving you everything we did
to reverse Hashimoto’s (yeah it’s free)
Here��s everything you need ⬇️⬇️
https://t.co/Mv0zD3xlJh
This is a case study of a patient of mine who was put on thyroid medication
12 years ago…Synthroid & levothyroxine
And every follow up doctors visit
the MD would increase her dosages…
And she felt terrible
When she asked them if she could wean off the medication they told her it had been too long…
and that she would die without thyroid medication…
And now, since working with me
She’s been off thyroid meds for 9 months
Here’s what happens to most people…
you go to the endocrinologist
TPO antibodies are at 800
TSH & thyroid peroxidase are sky high
you get told you have Hashimoto’s etc
put on thyroid medication
& sent on your way…
And never solve the real problem
Hashimoto’s is not a thyroid issue
It never was
Labs will be in my stories
along with her longer video
(her full 15 minute video about everything will be up in the next week)
Everything you need
Is in the research playbook
Never Miss
Dr Trevor Bachmeyer
The Spartan
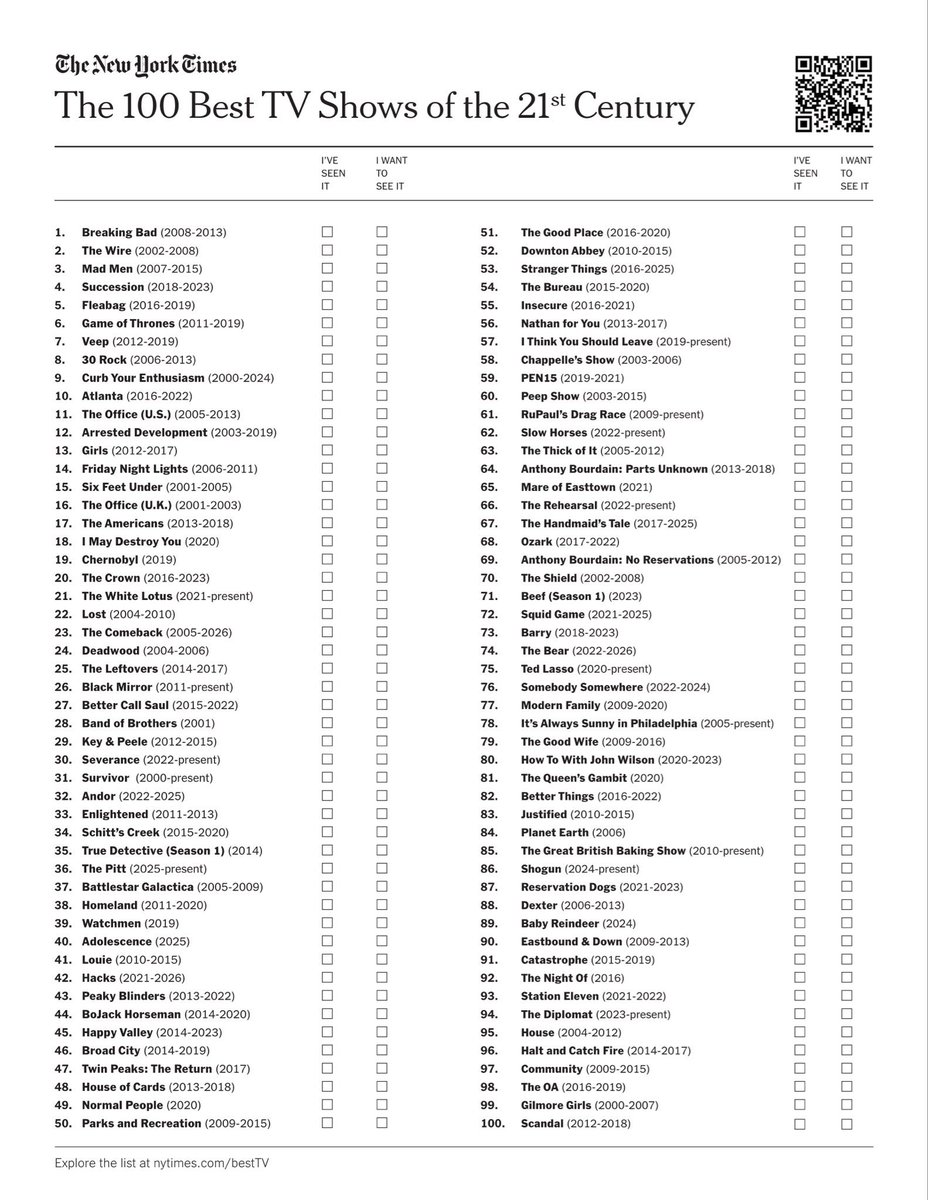
Started watching The Diplomat this week. The cast, the direction, the wardrobe, the music... absolutely fantastic. I often struggle to find a show that holds my attention, and wow does this ever. I'm ~4 episodes in and cannot wait to settle in tonight...
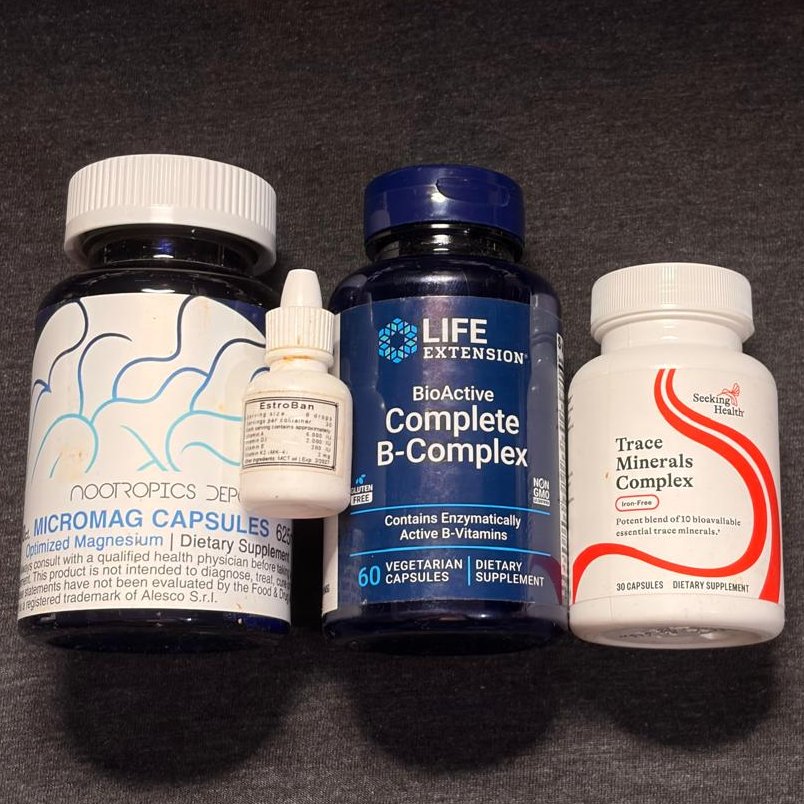
90% people only need these 4 supplements
• B100 Complex
• Trace Minerals Complex
• Estroban
• Magnesium
Here's why and science behind👇
High-Potency B-Complex: The Mitochondrial Combustion Engine
Every single step of glucose oxidation—from glycolysis in the cytoplasm to the Krebs cycle and the Electron Transport Chain (ETC) in the mitochondria—is strictly cofactor-dependent on B-vitamins:
• B1 (Thiamine) & The PDH Gatekeeper:
Thiamine pyrophosphate (TPP) is the mandatory cofactor for the Pyruvate Dehydrogenase (PDH) multienzyme complex and alpha-ketoglutarate dehydrogenase.
Without high-dose B1, pyruvate cannot convert into Acetyl-CoA. Cellular metabolism stalls, and glucose is shunted into lactate, triggering systemic lactic acidosis, muscle weakness, and fatigue.
• B2 (Riboflavin) & Complex II:
Riboflavin forms the reactive core of FMN and FAD/FADH2, feeding directly into Complex II (Succinate Dehydrogenase) of the mitochondrial ETC and powering glutathione reductase to recycle your master cellular antioxidant.
• B3 (Niacinamide) & The NAD+/NADH Ratio:
Supplies the backbone of Nicotinamide Adenine Dinucleotide (NAD+), which drives cellular ATP production, repairs DNA via PARP enzymes, and suppresses pathological free fatty acid lipolysis that blocks glucose oxidation (the Randle Cycle).
• B5 (Pantothenic Acid) & Coenzyme A:
The foundational building block of Coenzyme A (CoA), essential for synthesizing Acetyl-CoA, synthesizing steroid hormones in the adrenals and testes, and driving the breakdown of fats.
• B6 & Prolactin Suppression:
Acts as the non-negotiable cofactor for DOPA Decarboxylase and Glutamic Acid Decarboxylase (GAD).
It converts DOPA into Dopamine and glutamate into calming GABA, while directly suppressing elevated pituitary prolactin.
Broad-Spectrum Trace Mineral Complex: The Enzymatic Spark Plugs
Vitamins are useless without minerals. Minerals serve as the physical prosthetic groups at the catalytic centers of metabolic enzymes:
• Copper & Zinc (Cytochrome c Oxidase & SOD1):
Copper is the active metallic core of Cytochrome c Oxidase (Complex IV), the terminal and rate-limiting step of mitochondrial respiration that utilizes oxygen to synthesize water and ATP.
Paired with Zinc in a biological ratio (roughly 10:1 or 15:1 zinc to copper), they form Cu/Zn Superoxide Dismutase (SOD1), neutralizing destructive superoxide radicals before they degrade cell membranes.
• Selenium (Deiodinase Activation & T3 Conversion):
Active cellular thyroid hormone (T3) dictates the basal metabolic rate of every cell.
The enzymes responsible for cleaving inactive T4 into active T3—Type 1 and Type 2 Iodothyronine Deiodinases—are strictly selenoproteins.
Without selenium, deiodinases shut down, creating functional tissue-level hypothyroidism regardless of what total thyroid numbers show.
• Manganese (MnSOD / SOD2):
Forms the core of mitochondrial Superoxide Dismutase (MnSOD), the primary shield protecting mitochondrial DNA from oxidative fragmentation.
• Molybdenum & Boron:
Molybdenum fuels Sulfite Oxidase, preventing toxic sulfite accumulation from dietary protein.
Boron downregulates Sex Hormone-Binding Globulin (SHBG), rapidly liberating bound testosterone into Free, Bioavailable Testosterone while reducing urinary magnesium and calcium wasting.
Estroban (The ADEK Matrix): The Anti-Estrogen & Tissue Shield
Estroban provides the four critical fat-soluble vitamins—Vitamin A (Retinol), Vitamin D3, Vitamin E (Mixed Tocopherols), and Vitamin K2 (MK-4)—which operate in tight physiological synergy to halt tissue calcification and estrogenic stress:
• Vitamin E (The Master PUFA Shield & Aromatase Blunter):
The primary chain-breaking, lipid-soluble antioxidant.
It inserts into mitochondrial and cellular phospholipid bilayers, halting the toxic lipid peroxidation chain reactions driven by dietary polyunsaturated fatty acids (PUFAs).
Furthermore, Vitamin E antagonizes estrogen at the receptor level and downregulates the aromatase enzyme, dropping circulating estrogen.
• Vitamin K2 (MK-4) & The Calcium Shunt:
MK-4 is the biologically active tissue form of Vitamin K2.
It acts as a cofactor for gamma-glutamyl carboxylase, activating Osteocalcin (to pull calcium into bones and teeth) and Matrix Gla Protein (MGP) (which physically prevents calcium from depositing into arterial walls, kidneys, and soft tissues).
It also functions as an alternative electron carrier in the mitochondrial membrane.
• Vitamin A (Retinol) & Steroidogenesis:
Pure retinol binds Retinoid X Receptors (RXR), which heterodimerize with thyroid receptors (TR) to initiate metabolic gene transcription.
Retinol is mandatory for the testicular conversion of cholesterol into pregnenolone, driving endogenous androgen synthesis and maintaining mucosal barrier integrity.
• Vitamin D3 & Immune Tolerance:
Coordinates systemic calcium absorption and regulates over 1,000 genomic pathways governing immune modulation and neuromuscular contraction.
Critical Rule: High-dose Vitamin D without K2 and A drives soft-tissue arterial calcification; taking them in the unified Estroban matrix prevents toxicity entirely.
Bioavailable Magnesium: The ATP Complexer & Voltage Plug
Magnesium is the unsung mineral governor of human electrophysiology. It is involved in over 600 enzymatic reactions, yet modern monoculture agriculture has depleted it from the food supply:
• Mg-ATP Chelation (The True Energy Molecule):
"ATP" does not exist in biological systems as a naked molecule.
Biologically active ATP is almost entirely complexed as Mg-ATP.
Magnesium binds to the polyphosphate chain of ATP, stabilizing its negative charges and allowing enzymes like the Na+/K+ ATPase pump to hydrolyze it for energy.
Without magnesium, your cells cannot spend the ATP they produce.
• The NMDA Voltage-Dependent Plug:
In the brain, Magnesium sits directly inside the pore of postsynaptic NMDA receptors as a physical voltage-dependent plug.
When magnesium is deficient, the plug is absent, allowing unregulated, toxic influxes of Calcium (Ca2+) into neurons.
This causes non-stop glutamate excitotoxicity: manifested as physical anxiety, muscle twitches, restless leg syndrome, brain fog, and chronic hyper-irritability.
• Activating Vitamin D:
Every step of Vitamin D metabolism—hepatic 25-hydroxylation, renal 1-alpha-hydroxylation, and synthesis of Vitamin D Binding Protein (VDBP)—requires elemental magnesium.
Taking high-dose Vitamin D without magnesium rapidly depletes your body's magnesium reserves, causing severe heart palpitations, muscle cramps, and insomnia.
The Synergistic Synthesis: Why This Stack Replaces 20 Bottles
When you deploy these four compounds simultaneously, you create a self-reinforcing biological loop:
The B-Complex delivers the cofactors to break down carbohydrates and fuel the Krebs cycle.
The Trace Mineral Complex supplies the metallic engines for Complex IV, SOD enzymes, and thyroid deiodinase (T4 to T3).
Magnesium complexes the resulting ATP so it can be utilized, while keeping NMDA receptors plugged to eliminate anxiety and muscle tension.
Estroban (ADEK) ensures that the calcium mobilized by metabolic recovery is deposited into skeletal bone rather than soft tissue, while shutting down the estrogenic and oxidative stress of dietary PUFAs.
Strip away the chaotic, redundant, 20-bottle supplement routines. Provide the foundational biochemistry your mitochondria actually recognize, and your biology handles the rest.
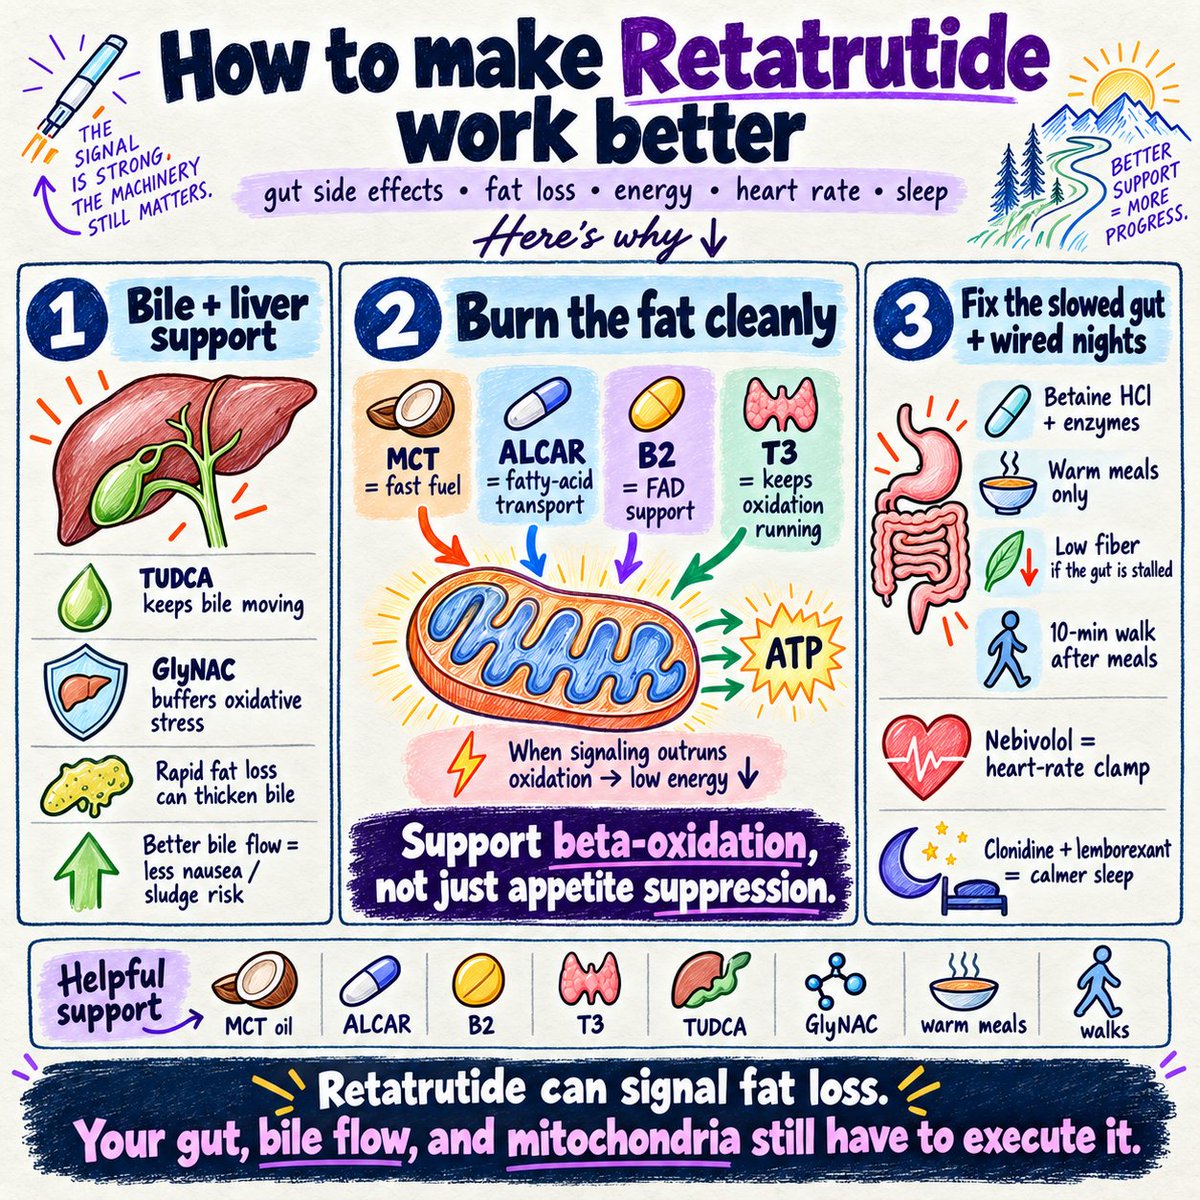
People taking Retatrutide who are experiencing gut related side effects, struggling to lose fat or dealing with low energy, would benefit greatly from adding:
• TUDCA
• T3
• GlyNAC
• 5–10 mL of Coconut/MCT oil with each meal
• 250 mg of ALCAR 2–3x per day
• Vitamin B2 (R5P) 4–5x per day
• Walking after meals
• Betaine HCl and digestive enzymes
• Warm meals only
• Low-dose Nebivolol for heart rate management
• Avoiding excessive fiber intake
• Clonidine and lemborexant for sleep issues
Here's why and science behind:👇
The Biliary Flush & Hepatic Detox: TUDCA & GlyNAC
The glucagon agonism of Retatrutide causes unprecedented, rapid clearance of intrahepatic triglycerides (reversing fatty liver within weeks).
However, dumping that volume of mobilized lipids and cholesterol directly into the biliary tree creates severe physiological strain:
• TUDCA (Tauroursodeoxycholic Acid) — Preventing Biliary Stasis:
When the liver exports massive waves of cholesterol into bile, the bile becomes supersaturated, viscous, and lithogenic.
This leads to biliary sludge, impaired bile flow, and an extreme risk of gallstones (cholelithiasis)—a primary complication of rapid weight loss.
TUDCA is a hydrophilic bile acid that displaces toxic, hydrophobic bile salts.
It stimulates the Bile Salt Export Pump (BSEP), dramatically lowers bile viscosity, prevents cholestasis, and resolves endoplasmic reticulum (ER) stress in hepatocytes, keeping the liver and gallbladder flushing smoothly.
• GlyNAC (Glycine + N-Acetylcysteine) — Neutralizing Lipoperoxidative Stress:
Accelerated fat oxidation surges the generation of reactive oxygen species (ROS) and lipid peroxides.
Supplying Glycine and NAC directly feeds the rate-limiting enzyme Glutamate-Cysteine Ligase (GCL), surging intracellular Glutathione (GSH).
Glycine also provides the required substrate to conjugate toxic bile acids, while NAC protects liver parenchyma from oxidative collapse during hyper-accelerated lipolysis.
The Beta-Oxidation & Mitochondrial Engine: MCT, ALCAR, B2 & T3
Glucagon signals the body to burn fat, but signaling oxidation is not the same as having the cellular machinery to execute it.
If fatty acids enter circulation faster than mitochondria can oxidize them, you generate toxic lipid intermediates (ceramides, diacylglycerols) that cause severe issues.
• Coconut or MCT Oil (5–10ml with Meals) — Bypassing the CPT-1 Gate:
Medium-Chain Triglycerides (specifically C8/C10) bypass the lymphatic system and the rate-limiting Carnitine Palmitoyltransferase-1 (CPT-1) mitochondrial gate.
They diffuse directly into the mitochondrial matrix and convert rapidly into Acetyl-CoA and Ketone Bodies (beta-hydroxybutyrate).
This supplies instantaneous cellular ATP to the brain and heart, preventing the lethargic energy crashes typical of deep caloric deficits.
It will also help with intestinal lubrication and digestion.
• ALCAR (Acetyl-L-Carnitine, 250mg 2–3x Daily) — Long-Chain Transport:
While MCTs bypass transport gates, the mobilized long-chain fatty acids from Retatrutide require carnitine to cross the inner mitochondrial membrane via the CPT-1 and CPT-2 shuttle.
ALCAR donates carnitine for fatty acid transport while supplying an acetyl group to fuel the Krebs cycle, preventing mitochondrial gridlock and muscle catabolism.
• Riboflavin-5-Phosphate (B2 R5P, 4–5x Daily) — Powering FAD:
The very first step of mitochondrial fatty acid beta-oxidation is catalyzed by Acyl-CoA Dehydrogenase, an enzyme strictly dependent on Flavin Adenine Dinucleotide (FAD).
FAD is synthesized directly from active Vitamin B2 (Riboflavin-5-Phosphate).
If active B2 is depleted, beta-oxidation halts mid-cycle, spilling toxic dicarboxylic acids into the urine and causing extreme muscle weakness.
Micro-dosing(25-50mg) R5P throughout the day(Because of short half life and rapid renal clearance) keeps FAD pools saturated, allowing uninterrupted fat burning.
Some people also need extra B5.
• Low-Dose T3 (Liothyronine) — Sustaining Cytochrome c Oxidase:
Under heavy caloric restriction and rapid lipolysis, the body downregulates peripheral Type 1 and Type 2 Deiodinases, dropping active T3 to preserve energy.
Micro-dosing T3 (5mcg 3-4x per day) prevents metabolic adaptation, preserves basal metabolic rate, and directly drives Complex IV (Cytochrome c Oxidase) in the electron transport chain, ensuring cells cleanly burn the mobilized fatty acids.
The Mechanical Gastric Architecture: Overcoming Severe Hypomotility
Retatrutide’s GLP-1 and GIP agonism dramatically slows gastric emptying (gastroparesis).
Treating a Retatrutide-slowed gut like a normal digestive tract leads directly to food rotting in the stomach, sulfur burps, severe reflux, and intractable nausea:
• Betaine HCl & Full-Spectrum Digestive Enzymes:
Delayed gastric emptying causes stomach acid to buffer out, leading to functional hypochlorhydria.
Proteins sit un-denatured, putrefying and generating gas.
Taking Betaine HCl and Digestive Enzymes forces the chemical breakdown of chyme in the upper stomach, eliminating the nausea and sulfur gas caused by undigested food sitting for 8 hours.
• Strictly Warm Meals & Zero Cold Water Around Meals:
Cold fluids shock the pyloric sphincter and gastric smooth muscle, triggering acute gastric spasm and diluting what little stomach acid exists.
Consuming only warm, cooked foods and warm fluids maintains local microcirculation and ensures digestive enzymes operate at peak kinetic temperatures.
• Avoiding High-Fiber Diets:
Mainstream dietitians push massive fiber on peptide patients, which is a catastrophic mistake.
In a hypomotile gut, insoluble fiber forms physical obstructions (bezoars), ferments into excess hydrogen and methane gas, feeds SIBO, and exacerbates severe abdominal distension.
Keep carbohydrates easily digestible, peeled, and thoroughly cooked (white rice, pureed squash, strained fruit juices).
• The 10-Minute Post-Meal Walk:
Gentle postprandial ambulation stimulates mechanoreceptors and parasympathetic vagal output, mechanically driving gastric clearance and intestinal peristalsis without triggering nausea.
Autonomic Clamping & Sleep Architecture: Nebivolol, Clonidine & Lemborexant
Both GLP-1 and Glucagon receptors are expressed directly on cardiomyocytes and autonomic control centers:
• The Tachycardia Reality:
Retatrutide directly stimulates GLP-1 and Glucagon receptors in the Sinoatrial (SA) node, while elevated glucagon upregulates systemic sympathetic nervous system tone.
This causes an unavoidable, persistent elevation in resting heart rate (typically +5 to +15 bpm) that disrupts sleep, elevates cortisol, and strains the cardiovascular system.
• Low-Dose Nebivolol (2.5mg) — The Selective Beta-1 Clamp:
Traditional beta-blockers (like Propranolol or Metoprolol) blunt lipolysis, impair insulin sensitivity, and cause fatigue.
Nebivolol is completely different: it is an ultra-selective Beta-1 adrenoceptor antagonist with unique Beta-3 agonist-mediated Endothelial Nitric Oxide (eNOS) properties.
It slows resting heart rate back to optimal baseline, lowers blood pressure, and improves peripheral vascular flow without interfering with Retatrutide-induced fat oxidation.
• Clonidine (50-100mcg) — The Central Sympathetic Brake:
An agonist at central presynaptic Alpha-2A adrenoceptors in the rostral ventrolateral medulla.
Clonidine directly shuts down excessive central norepinephrine outflow, muting the "wired-and-tired" jitteriness driven by glucagon and dropping nighttime stress hormones.
• Lemborexant (Dayvigo, 5mg) — Precision Sleep Architecture:
Sympathetic over-activation on Retatrutide causes nocturnal awakenings and fragmented Slow-Wave Sleep.
Do not use GABAergic sedatives (benzodiazepines or Z-drugs), which cause tolerance and suppress respiratory drive.
Lemborexant is a Dual Orexin Receptor Antagonist (DORA) that selectively blocks OX1 and OX2 receptors in the lateral hypothalamus.
It silences the hyperactive wakefulness signal triggered by sympathetic overdrive, allowing natural, restorative Slow-Wave and REM sleep architecture without morning hangover.
Obviously: B100 Complex, Trace minerals Complex and Estroban(A,D3,K2,E).
I have mentioned a few times one of the most important factors in migraines are Histamine receptors. Serotonin, gut microbiome and histamine all interplay in neuroinflammation (control layer) and indeed mental health.
B1 and B2 play crucial roles here in regulating the immune, cortisol, inflammatory and nervous system (activity layer).
Magnesium glycinate may not be working because you are taking it at the wrong time or with the wrong foods.
Here is exactly how to time it so it actually helps.
THIS SEED CLEANS YOUR KIDNEYS WHILE YOU’RE ASLEEP
1. Stop chugging alkaline water - it stresses filtration. Chew 5 coriander seeds before bed - binds heavy metals, urinary pH balances by midnight.
2. Your renal pelvis is holding micro-sand. Soak fennel seeds overnight, sip the water at 2 AM if you wake - dissolves oxalate crystals before they seed.
3. One pinch of celery seed powder on your tongue triggers a nocturnal diuresis wave - flushes uric acid without dehydrating you.
4. Eat ¼ tsp black cumin seed oil with a date 15 min before bed - lowers intraglomerular pressure, your GFR improves 15% by morning.
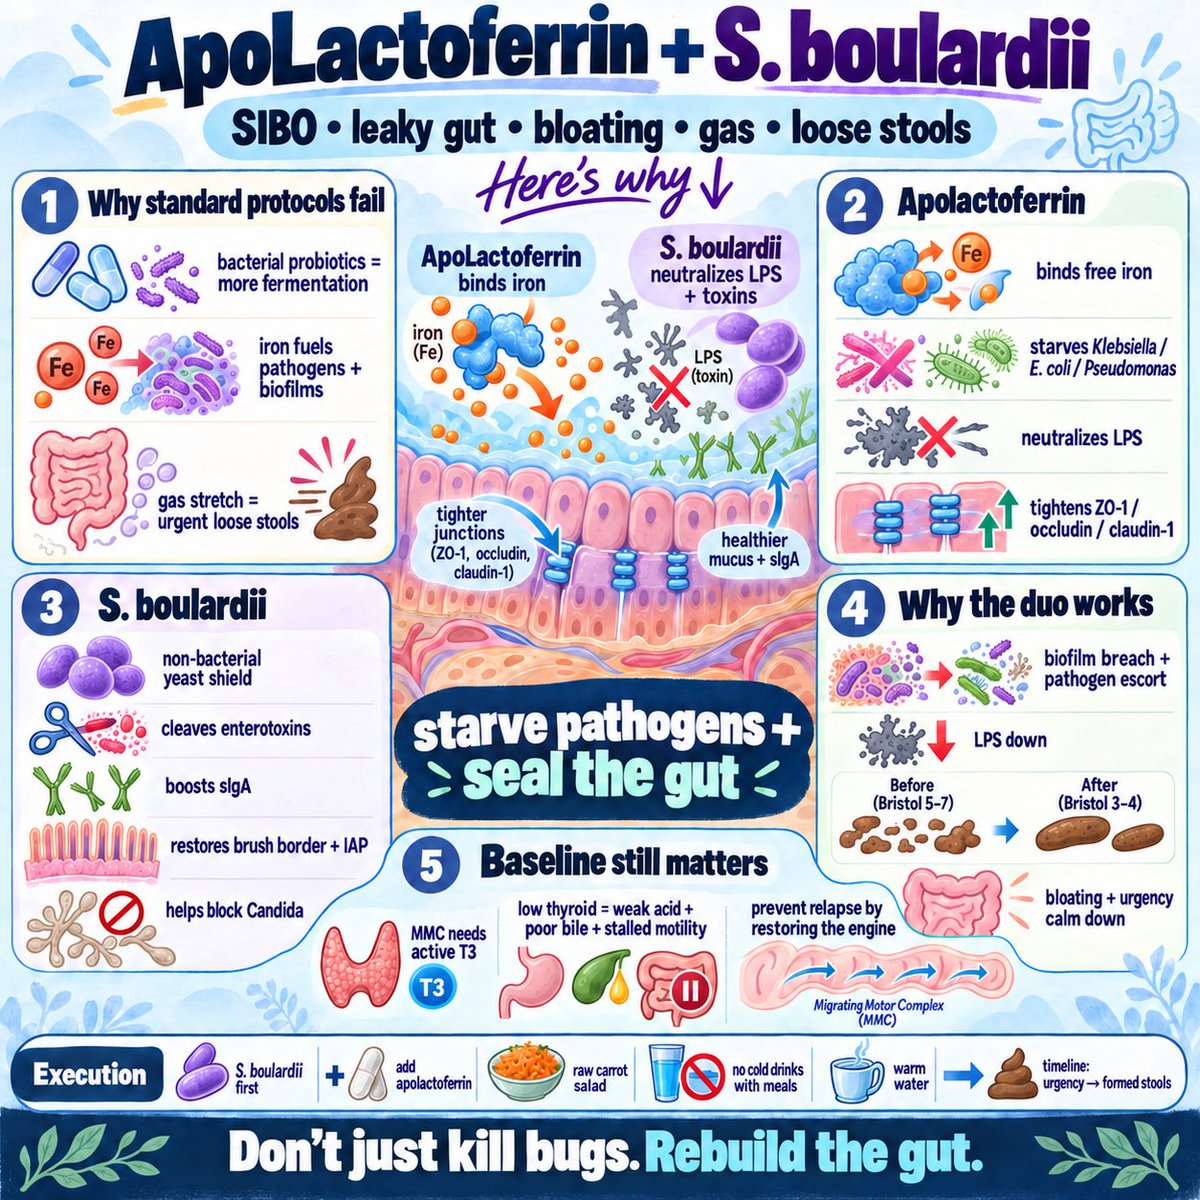
ApoLactoferrin + S. Boulardi is the best duo to fix SIBO, leaky gut, bloating, gas, and loose stools.
it starves pathogens of iron, dissolves biofilms, neutralizes luminal endotoxin (LPS), surges secretory IgA (sIgA), and tightens epithelial junctions to permanently halt loose stools.
Here is the cellular science and execution protocol👇
Why Traditional Protocols Fail in SIBO & Loose Stools
• The Probiotic Fermentation Trap:
In SIBO, bacteria colonize the small intestine. Adding standard bacterial probiotics acts as fertilizer, triggering rapid carbohydrate fermentation, distension, and histamine flares within 30 minutes of eating.
• Iron Hoarding & Biofilms:
Opportunistic pathogens (Klebsiella, E. coli, Pseudomonas) scavenge free ferric iron (Fe3+) via siderophores to proliferate and construct extracellular polymeric biofilms, shielding them from traditional therapies.
• Hyperactive Gastrocolic Reflex:
Fermentation gas mechanically stretches the small intestine, firing an aggressive reflex that dumps unabsorbed water and bile into the colon, producing 4 to 6 loose, urgent stools daily.
Apolactoferrin: Iron-Starvation & Mucosal Sealing
Use Apolactoferrin (iron-depleted, less than 5% iron saturation), not hololactoferrin:
• Bacterial Starvation:
With iron affinity roughly 300 times higher than transferrin, it strips free luminal Fe3+, starving pathogens of the substrate required to divide and maintain biofilms.
• Lactoferricin Lysis:
Gastric pepsin cleaves apolactoferrin into Lactoferricin, a positively charged antimicrobial peptide that binds negatively charged LPS on Gram-negative bacteria to trigger osmotic lysis.
• LPS Neutralization:
Binds the toxic lipid A domain of free luminal endotoxin (LPS), neutralizing it before it can activate enterocyte TLR4/NF-kB inflammatory destruction.
• Tight Junction Re-Assembly:
Upregulates Zonula Occludens-1 (ZO-1), Occludin, and Claudin-1, sealing paracellular leaks against antigen translocation.
Saccharomyces boulardii: The Non-Colonizing Yeast Shield
A non-bacterial, antibiotic-resistant probiotic yeast that completely clears within 3 to 5 days of cessation:
• 54-kDa Protease Cleavage: Secretes a serine protease that cleaves and deactivates bacterial enterotoxins (e.g., C. difficile, E. coli), shutting down toxin-induced chloride and water dumping.
• Surging sIgA Defense: Upregulates polymeric immunoglobulin receptors (pIgR), driving massive luminal secretion of secretory IgA (sIgA) to neutralize antigens.
• Brush-Border Restoration: Stimulates intestinal lactase, sucrase, maltase, and Intestinal Alkaline Phosphatase (IAP), which detoxifies endotoxin and eliminates carbohydrate-driven osmotic diarrhea.
• Candida Antagonism: Secretes capric acid, halting Candida albicans filamentation and biofilm synthesis.
The Synergistic Lock: Halting Loose Stools Fast
• Biofilm Breach & Escort: Apolactoferrin dismantles biofilm iron scaffolds, allowing S. boulardii to capture exposed pathogens via surface mannose adhesions and sweep them out in stool.
• Stool Consolidation (5–6 Down to 1–2): Blunting inflammatory cytokines while downregulating mucosal cAMP/cGMP halts fluid dumping, shifting stool form from liquid (Bristol 5–7) to formed logs (Bristol 3–4).
• Commensal Optimization: Synthesizes short-chain fatty acids (SCFAs like butyrate) to fuel colonocytes without fermenting in the small intestine.
The Motility Engine: Cellular T3
Clearing overgrowth fails long-term if your Migrating Motor Complex (MMC) is stalled:
• The MMC cleans the small intestine every 90 to 120 minutes during fasting via smooth muscle contractions dependent on active cellular T3 and vagal acetylcholine tone.
• Hypothyroidism blunts gastric acid, reduces antimicrobial bile flow, and halts the MMC, allowing bacteria to migrate upward. Restoring metabolic rate and stomach acid is non-negotiable to prevent relapse.
Clinical Dosing & Execution Directive
• Phase 1: S. boulardii (Days 1–3): 250mg to 500mg (5 to 10 billion CFU) twice daily with warm water, 20 to 30 minutes before your two main meals to prime sIgA and prevent Herxheimer die-off.
• Phase 2: Apolactoferrin (Day 4 Onward): 250mg to 500mg once to twice daily on an empty stomach (45 minutes pre-meal or pre-bed) with warm water.
• Mandatory Operational Rules:
No Cold Liquids With Meals: Avoid drinking cold fluids around food to preserve gastric acid concentration and gut motility.
Daily Raw Carrot Salad: Grated washed carrot, 1 tsp coconut oil, 1 tsp apple cider vinegar, and salt taken 2-3 hour post-breakfast to bind and excrete loosened endotoxin.
• Timeline: Days 1–5 resolve cramping and urgency; Days 7–14 consolidate bowel movements down to 1–2 solid stools; Days 14–30 clear systemic endotoxemia, resolving brain fog and expanding dietary tolerance.
The internet once told me this:
“Stick out your tongue for 40 seconds removes cortisol faster than any pills and breathing exercises.”
1. That's oversold. But stress really does tighten your neck.