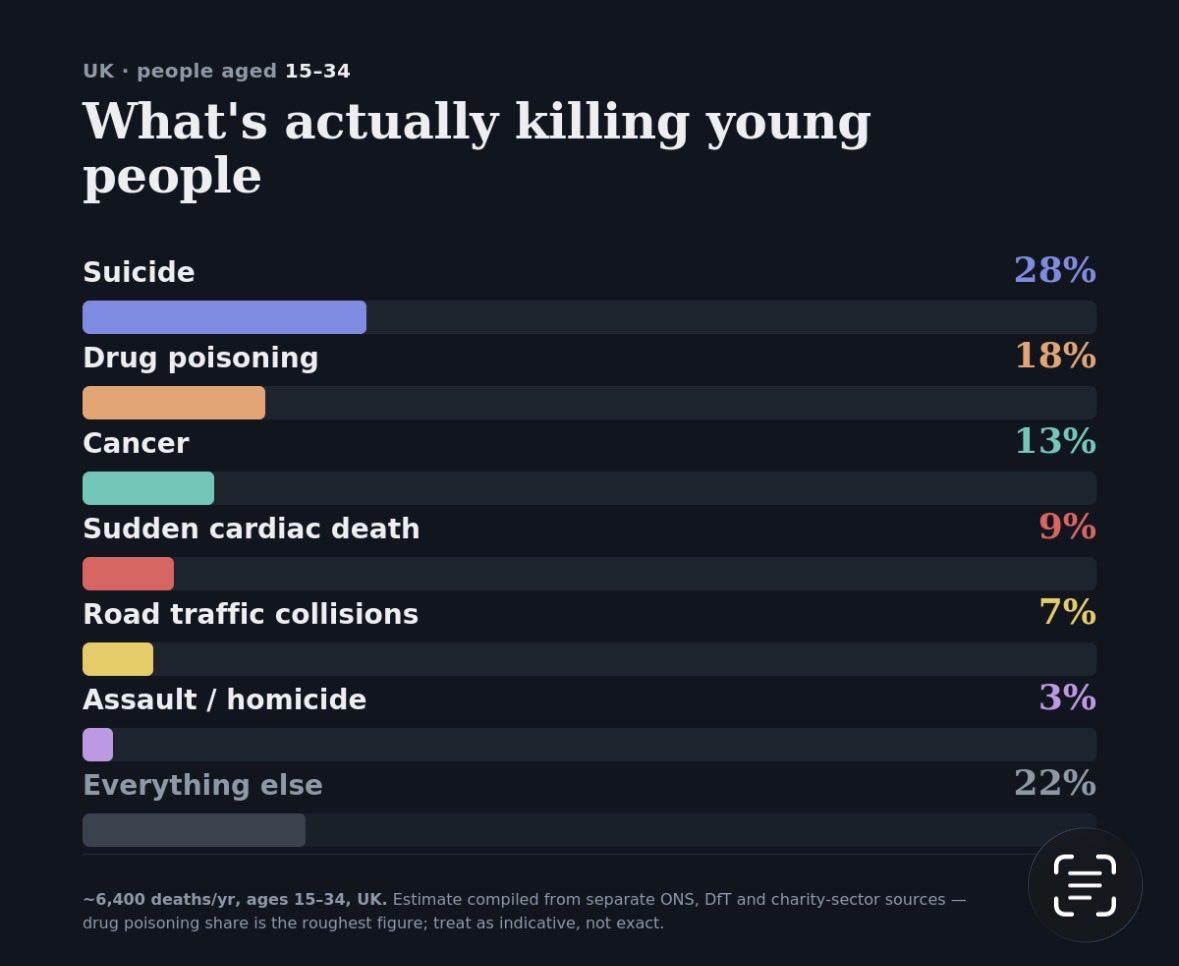
What do we say to Young Sudden Cardiac Death? Not today Death, not Today. SCD kills 12 people a week between ages 14 and 35 in UK. Follow and we Follow back.
Every week in UK 12 young people die from sudden cardiac death. Many of these deaths could be prevented. Make cardiac screening available to all young people. #cardiacscreening#12aday#testmyheart
Prof , if we are such a powerhouse why do we still allow 12 young people a week to die of sudden cardiac death. Japan Taiwan Israel Italy and 4 US states all have laws to mandate or promote cardiac screening. FIFA , IOC, ESC and AHA all recommend cardiac screening for competitive amateur athletes but in UK only the Elite get screened (a reflection of UK society maybe).
The UK screening commitee is set to refuse screening for the general population again, whilst also rejecting screening for sportspeople as “inequitable”.
If the UK is such a powerhouse then you’d probably wonder why the NSC documents seem such a poorly reasoned piece of science that doesn’t seem to follow any of the principles that we’d see in a medical review of evidence.
Can I ask that you or one of your team or colleagues spend a bit of time casting your eye over this NSC review and the up to date evidence they’ve excluded and call it out if you think it’s as flawed as I do.
I’d also ask you to wonder why none of the 3 US biotech companies racing to provide a genetic cure for ACM are not doing trials in UK. And why the ACM TARGET trial is happening in Canada and not here. BHF is focussing on projects for Inherited Cardiac Conditions that won’t reach fruition for decades (by their own admission) in the meantime no UK based biotech to treat cardiomyopathies ?!?!
Dear Dr Peedell, seeing as you can’t go to U.S. - can I ask you to spend an hour looking over the latest output from the National Screening Committee on the topic of Cardiac Screening to prevent Sudden Cardiac Death in the young.
I know this isn’t your field but this process desperately needs scrutiny from independent clinical academics to examine its rigour.
The consultation has now closed, but even when it opened the committee said it wasn’t minded to change its previous decision.
12 young people a week die from sudden cardiac death in the UK and 80% had no warning. On screening provided by charities 1 in 300 had conditions associated with Sudden Cardiac Death.
The screening committee rejected cardiac screening in 2019 and continues to oppose it, and the document to support this standpoint is riddled with illogical and circular arguments and misses out numerous recent studies and international guidelines.
In particular the screening committee doesn’t list in the evidence it will consider the ESC or AHA or FIFA position statements of cardiac screening in youth sports. There is no consideration of the JACC 2026 article reviewing outcomes of CRYs 10 year screening of more than 100000 voulnteers. The committe states that there is no evidence that screening can reduce sudden cardiac deaths while ignoring the ESC document on Ventricular arrhythmias which are evidence based consensus guidelines on managing conditions associated with SCD which the screening program would aim to identify. The committee says that a screening program may make people anxious and put them off sport but doesn’t offer any evidence of this. They argue there isn’t infrastructure to support screening but ignore the fact this is the case for most screening programs - the workforce and infrastructure have to be provided for the screening to happen. They attempt to equate Israeli screening results with Italian while not acknowledging the Israeli results are based on newspaper reports of deaths in 2 newspapers and the Italian results are based on a comprehensive longstanding registry of all child and juvenile deaths. They draw on concerns from the US about the cost to families of follow up care after screening but don’t acknowledge this is less of an issue here due to the NHS. They don’t even refer to Japan and Taiwan which are the only 2 countries in the world who screen all their youth. Some serious clinical academics need to look at the “work” the committee have done here and at least call out their lack of rigour, and ask serious questions - the committee seem to be suffering from cognitive dissonance, unable to even countenance the thought that they made the wrong decision in 2019.
Making routine cardiac screening available as per FIFA guidelines and supported by European society of cardiology ? If these players were in Italy they’d get cardiac screening every year, in Japan they’d be screened at school , in Israel when they started playing competitively, in Florida at school before being allowed to play competitively sport. In the “home of football” nothing unless you are elite or are lucky enough to get charity to do it.
1 in 300 young people in UK have a condition they don’t know about that leaves them open to sudden cardiac death. 1 in 15000 grassroots players will have a cardiac arrest on the pitch (those are the FAs figures)
When will the FA address screening for the grassroots ?
Dear Dr Galloway.
Congratulations on your award and setting up the charity and I hope it works out for your beautiful daughter.
Sadly I lost a child to Sudden Cardiac Death.
I wanted to ask if you could spare a bit of your valuable time to look at the National Screening Committees stance and consultation on Cardiac Screening in Young People to Prevent.
Sudden Death.
At present it’s estimated that 12 young people a week die from Sudden Cardiac Death between 14-35 and 80% have no warning.
Screening could help save some of these young people. Italy Israel Taiwan Japan Florida Texas Tennessee Pennsylvania all have laws to Mandate or Promote screening in some form.
The UK led by the NSC refuses to allow screening outside of charities and elite sport. This is despite European Society Cardiology and American Heart Association both recommending some sort of cardiac screening for competitive youth sports. Both FIFA and the IOC back this approach as well.
The NSC refused screening in 2019 and this year ran a review and consultation which its opening position was that it did not support screening. Some of its reasons lacked any evidence and could be used as argument against starting any sort screening ie generating anxiety and no initial infrastructure or workforce - like arguing no to breast screening because there aren’t enough screening vans!
The NSC argue there’s no evidence that screening stops sudden cardiac death but don’t address that once a SCA causing condition is found there’s a huge amount of data and research showing they can be managed and risks reduced, not withstanding rapidly evolving gene therapy treatments and disease modifying drugs.
The NSC don’t weight research and trials as we would expect to see in Medical Metaanalysis instead they treat everything equally. For instance the analysis of the effectiveness of Israeli screening relies on frequency of reports in 2 newspapers of athletes having cardiac arrests, whereas the Italian data relies on registry data before and after introduction of screening, the registry covering all deaths of children and young people by law.
I’m sure in your role in ED you will have witnessed the devastation a young sudden cardiac death can wreak on a family and community.
I’d ask that you use your experience as a doctor used to reviewing medical research and expert opinion and look at how the NSC is conducting this review. Call it out for what it is, it wouldn’t get published in a reputable journal it’s so weak.
I’d be happy to discuss if you wanted more details. Thanks for your consideration of this and have a good evening.
The term “escalation of commitment” is a term that describes when a group make a decision, but later realise they are wrong, but instead of changing course they continue on the same path but argue even more for the wrong decision.
In patient safety circles this is called “cognitive dissonance” or a “fixation error”.
This phenomenon is fully on display with the UKs National Screening Committee.
In 2019 they rejected bringing in Cardiac Screening for Young People to Reduce Risk of Sudden Cardiac Arrests - it was a contentious decision at the time.
Since then they have rejected Cardiac Screening for Amateur Sports People - saying it’s too difficult to determine what a sportsperson is , so many people play sports it’s a back door attempt to reverse their decision and it’s inequitable if people who play sport benefit from screening when sedentary people don’t ( although remember they said there was no benefit )
They reopened an evidence review in 2026 by saying they’d already decided not to reexamine in detail.
They demand rigorous evidence but then ignore recent papers and international consensus guidelines - pretending they don’t exist. They advance reasons why screening could be harmful but can’t produce evidence of this.
They offer CPR and genetic testing as alternatives while accepting that survival from cardiac arrest in UK is 10% and one of their own members has admitted the genetic screening system is not fit for purpose.
The people who make up this committee are unelected and unaccountable and non representative of the group that they make decisions about.
Enough is enough, they need to be called out and the debate to be had in the open just like with assisted dying - but this is about helping young people to live.
In Florida the politicians got tired of seeing their voters die, they don’t wait for the medical committees any more , they passed a Law , the Second Chance Law. Now it’s time for our Lawmakers to act. @andyburnham@YvetteCooperMP@matthewsyed@Jeremy_Hunt@KemiBadenoch@Nigel_Farage@RupertLowe10@EdwardJDavey@ZackPolanski
Dear Dr Ruzieh can I ask you to spend a couple of your valuable hours looking over the latest offering from the National Screening Committee of the UK on Cardiac Screening to prevent sudden cardiac death in the young. The consultation has now closed, but even when it opened the committee said it wasn’t minded to change its previous decision.
About 12 young people a week in UK die from sudden cardiac death and the UK health system and authorities have repeatedly refused to address this.
The document to support this standpoint form the NSC is riddled with illogical and circular arguments and misses out numerous recent studies and international guidelines.
In particular the screening committee doesn’t list in the evidence it will consider the ESC or AHA or FIFA position statements of cardiac screening in youth sports. There is no consideration of the JACC 2026 article reviewing outcomes of CRYS 10 year screening of more than 100000 voulnteers. The committe states that there is no evidence that screening can reduce sudden cardiac deaths while ignoring the ESC document on Ventricular arrhythmias which are evidence based consensus guidelines on managing conditions associated with SCD which the screening program would aim to identify. The committee says that a screening program may make people anxious and put them off sport but doesn’t offer any evidence of this. They argue there isn’t infrastructure to support screening but ignore the fact this is the case for most screening programs - the workforce and infrastructure have to be provided for the screening to happen. They attempt to equate Israeli screening results with Italian while not acknowledging the Israeli results are based on newspaper reports of deaths in 2 newspapers and the Italian results are based on a comprehensive longstanding registry of all child and juvenile deaths. They draw on concerns from the US about the cost to families of follow up care after screening but don’t acknowledge this is less of an issue here due to the NHS. They don’t even refer to Japan and Taiwan which are the only 2 countries in the world who screen all their youth. Some serious clinical academics need to look at the “work” the committee have done here and at least call out their lack of rigour.
Dr Qasim can I ask you to spend a couple of your valuable hours looking over the latest offering from the National Screening Committee on Cardiac Screening to prevent sudden cardiac death in the young. The consultation has now closed, but even when it opened the committee said it wasn’t minded to change its previous decision.
The document to support this standpoint is riddled with illogical and circular arguments and misses out numerous recent studies and international guidelines.
In particular the screening committee does list in evidence it will consider the ESC or AHA or FIFA position statements of cardiac screening in youth sports. There is no consideration of the JACC 2026 article reviewing outcomes of CRYS 10 year screening of more than 100000 voulnteers. The committe states that there is no evidence that screening can reduce sudden cardiac deaths while ignoring the ESC document on Ventricular arrhythmias which are evidence based consensus guidelines on managing conditions associated with SCD which the screening program would aim to identify the committee says that a screening program may make people anxious and put them off sport but doesn’t offer any evidence of this. They argue there isn’t infrastructure to support screening but ignore the fact this is the case for most screening programs - the workforce and infrastructure have to be provided for the screening to happen. They attempt to equate Israeli screening results with Italian while not acknowledging the Israeli results are based on newspaper reports of deaths in 2 newspapers and the Italian results are based on a comprehensive longstanding registry of all child and juvenile deaths. They draw on concerns from the US about the cost to families of follow up care after screening but don’t acknowledge this is less of an issue here due to the NHS. They don’t even refer to Japan and Taiwan which are the only 2 countries in the world who screen all their youth. Some serious clinical academics need to look at the “work” the committee have done here and at least call out their lack of rigour.Qasim
Dr Jones - can I ask you to spend a couple of your valuable hours looking over the latest offering from the National Screening Committee on Cardiac Screening to prevent sudden cardiac death in the young. The consultation has now closed, but even when it opened the committee said it wasn’t minded to change its previous decision.
You probably know that 12 young people a week die from sudden cardiac death in UK. Screening could save some of them. The UK resists screening both the general population and athletes and sports players. The process of how this decision is arrived at is seriously flawed. I hope that influential doctors who understand research / trials and expert guidelines can look at how the committe has reached its decision and at least call out its lack of rigour.
The document to support this standpoint is riddled with illogical and circular arguments and misses out numerous recent studies and international guidelines.
In particular the screening committee does list in evidence it will consider the ESC or AHA or FIFA position statements of cardiac screening in youth sports. There is no consideration of the JACC 2026 article reviewing outcomes of CRYS 10 year screening of more than 100000 voulnteers. The committe states that there is no evidence that screening can reduce sudden cardiac deaths while ignoring the ESC document on Ventricular arrhythmias which are evidence based consensus guidelines on managing conditions associated with SCD which the screening program would aim to identify the committee says that a screening program may make people anxious and put them off sport but doesn’t offer any evidence of this. They argue there isn’t infrastructure to support screening but ignore the fact this is the case for most screening programs - the workforce and infrastructure have to be provided for the screening to happen. They attempt to equate Israeli screening results with Italian while not acknowledging the Israeli results are based on newspaper reports of deaths in 2 newspapers and the Italian results are based on a comprehensive longstanding registry of all child and juvenile deaths. They draw on concerns from the US about the cost to families of follow up care after screening but don’t acknowledge this is less of an issue here due to the NHS. They don’t even refer to Japan and Taiwan which are the only 2 countries in the world who screen all their youth. Some serious clinical academics need to look at the “work” the committee have done here and at least call out their lack of rigour.
Dear Dr Hammond - can I ask you to spend a couple of your valuable hours looking over the latest offering from the National Screening Committee on Cardiac Screening to prevent sudden cardiac death in the young.
I know this is a bit off topic for you at moment but it’s really key. I guess you know that 12 young people a week die of sudden cardiac death in UK. The UK government refuses to implement screening either generally or for the sporting population. I believe there is serious questions about how this review is conducted but only through questioning by influential doctors who can understand the evidence can this be called out.
The consultation has now closed, but even when it opened the committee said it wasn’t minded to change its previous decision.
The document to support this standpoint is riddled with illogical and circular arguments and misses out numerous recent studies and international guidelines.
In particular the screening committee does list in evidence it will consider the ESC or AHA or FIFA position statements of cardiac screening in youth sports. There is no consideration of the JACC 2026 article reviewing outcomes of CRYS 10 year screening of more than 100000 voulnteers. The committe states that there is no evidence that screening can reduce sudden cardiac deaths while ignoring the ESC document on Ventricular arrhythmias which are evidence based consensus guidelines on managing conditions associated with SCD which the screening program would aim to identify the committee says that a screening program may make people anxious and put them off sport but doesn’t offer any evidence of this. They argue there isn’t infrastructure to support screening but ignore the fact this is the case for most screening programs - the workforce and infrastructure have to be provided for the screening to happen. They attempt to equate Israeli screening results with Italian while not acknowledging the Israeli results are based on newspaper reports of deaths in 2 newspapers and the Italian results are based on a comprehensive longstanding registry of all child and juvenile deaths. They draw on concerns from the US about the cost to families of follow up care after screening but don’t acknowledge this is less of an issue here due to the NHS. They don’t even refer to Japan and Taiwan which are the only 2 countries in the world who screen all their youth. Some serious clinical academics need to look at the “work” the committee have done here and at least call out their lack of rigour.
Dr Chatterjee can I ask you to spend a couple of your valuable hours looking over the latest offering from the National Screening Committee on Cardiac Screening to prevent sudden cardiac death in the young.
I know this may not be strictly your field but doctors with a strong clinical background who are also used to looking at data and research need to look at this process and call it out if they think it’s flawed
It’s important as 12 young people a week in UK die of sudden cardiac death and the UK government persistently refuses to implement screening.
The consultation has now closed, but even when it opened the committee said it wasn’t minded to change its previous decision.
The document to support this standpoint is riddled with illogical and circular arguments and misses out numerous recent studies and international guidelines.
In particular the screening committee does list in evidence it will consider the ESC or AHA or FIFA position statements of cardiac screening in youth sports. There is no consideration of the JACC 2026 article reviewing outcomes of CRYS 10 year screening of more than 100000 voulnteers. The committe states that there is no evidence that screening can reduce sudden cardiac deaths while ignoring the ESC document on Ventricular arrhythmias which are evidence based consensus guidelines on managing conditions associated with SCD which the screening program would aim to identify the committee says that a screening program may make people anxious and put them off sport but doesn’t offer any evidence of this. They argue there isn’t infrastructure to support screening but ignore the fact this is the case for most screening programs - the workforce and infrastructure have to be provided for the screening to happen. They attempt to equate Israeli screening results with Italian while not acknowledging the Israeli results are based on newspaper reports of deaths in 2 newspapers and the Italian results are based on a comprehensive longstanding registry of all child and juvenile deaths. They draw on concerns from the US about the cost to families of follow up care after screening but don’t acknowledge this is less of an issue here due to the NHS. They don’t even refer to Japan and Taiwan which are the only 2 countries in the world who screen all their youth. Some serious clinical academics need to look at the “work” the committee have done here and at least call out their lack of rigour.
Dr Clarke - can I ask you to spend a couple of your valuable hours looking over the latest offering from the National Screening Committee on Cardiac Screening to prevent sudden cardiac death in the young.
I know this isn’t your field but it’s really important to get high profile doctors who are used to looking at clinical research and guidelines to scrutinise this process.
The consultation has now closed, but even when it opened the committee said it wasn’t minded to change its previous decision.
The document to support this standpoint is riddled with illogical and circular arguments and misses out numerous recent studies and international guidelines.
In particular the screening committee does list in evidence it will consider the ESC or AHA or FIFA position statements of cardiac screening in youth sports. There is no consideration of the JACC 2026 article reviewing outcomes of CRYS 10 year screening of more than 100000 voulnteers. The committe states that there is no evidence that screening can reduce sudden cardiac deaths while ignoring the ESC document on Ventricular arrhythmias which are evidence based consensus guidelines on managing conditions associated with SCD which the screening program would aim to identify the committee says that a screening program may make people anxious and put them off sport but doesn’t offer any evidence of this. They argue there isn’t infrastructure to support screening but ignore the fact this is the case for most screening programs - the workforce and infrastructure have to be provided for the screening to happen. They attempt to equate Israeli screening results with Italian while not acknowledging the Israeli results are based on newspaper reports of deaths in 2 newspapers and the Italian results are based on a comprehensive longstanding registry of all child and juvenile deaths. They draw on concerns from the US about the cost to families of follow up care after screening but don’t acknowledge this is less of an issue here due to the NHS. They don’t even refer to Japan and Taiwan which are the only 2 countries in the world who screen all their youth. Some serious clinical thinkers need to look at the “work” the committee have done here and at least call out their lack of rigour.
Depending on your issue and your age I’d be cautious about having a heart problem “cleared” by your GP without exercise testing , 24 or 72 hour monitoring monitoring and an echocardiogram. The stuff that’s killing young people like ACM, HCM, DCM, Brugada, WPW can easily be missed on a simple 12 lead ecg. Some of it looks like the “normal” changes the heart undergoes if you do a lot of exercise. Some problems will only reveal themselves under heavy exercise in the early stages. All these countries like Italy, Israel, Japan, Taiwan Florida Texas Pennsylvania and Tennessee aren’t suggesting young people get cleared by their family doctor or GP. FOFA aren’t recommending that grassroots players pop into the GP to get screened they provide specific guidance on who is qualified to do it.
I appreciate your sympathy and concern but please don’t reassure people this is something an appointment with GP can sort ( unless GP has special interest in Sports medicine or sports cardiology )
Dear Prof - can I ask you to spend a couple of your valuable hours looking over the latest offering from the National Screening Committee on Cardiac Screening to prevent sudden cardiac death in the young. I know this isn’t your field but this process desperately needs scrutiny from independent clinical academics even to examine its rigour. The consultation has now closed, but even when it opened the committee said it wasn’t minded to change its previous decision.
The document to support this standpoint is riddled with illogical and circular arguments and misses out numerous recent studies and international guidelines.
In particular the screening committee does list in evidence it will consider the ESC or AHA or FIFA position statements of cardiac screening in youth sports. There is no consideration of the JACC 2026 article reviewing outcomes of CRYS 10 year screening of more than 100000 voulnteers. The committe states that there is no evidence that screening can reduce sudden cardiac deaths while ignoring the ESC document on Ventricular arrhythmias which are evidence based consensus guidelines on managing conditions associated with SCD which the screening program would aim to identify the committee says that a screening program may make people anxious and put them off sport but doesn’t offer any evidence of this. They argue there isn’t infrastructure to support screening but ignore the fact this is the case for most screening programs - the workforce and infrastructure have to be provided for the screening to happen. They attempt to equate Israeli screening results with Italian while not acknowledging the Israeli results are based on newspaper reports of deaths in 2 newspapers and the Italian results are based on a comprehensive longstanding registry of all child and juvenile deaths. They draw on concerns from the US about the cost to families of follow up care after screening but don’t acknowledge this is less of an issue here due to the NHS. They don’t even refer to Japan and Taiwan which are the only 2 countries in the world who screen all their youth. Some serious clinical academics need to look at the “work” the committee have done here and at least call out their lack of rigour.
Please - you cannot get screening at your GP for Inherited Cardiac Conditions. You cannot ask for a referral to a clinic but these clinics would not see you without a family history , symptoms a genetic result.
Interpreting a 12 lead RCG looking for subtle signs of some of these conditions is a specialist skill at the moment - usually the preserve of a sports or ICC cardiologist. I’m not knocking GPs but coroners reports full of cases where signs on ECGs were missed by doctors and only seen by an expert in retrospect.
You can ask try and book a screening with a charity like CRY but they have capacity for 30000 a year. Even they say most people should be screened twice.
Prof - can I ask you to spend a couple of your valuable hours looking over the latest offering from the National Screening Committee on Cardiac Screening to prevent sudden cardiac death in the young. The consultation has now closed, but even when it opened the committee said it wasn’t minded to change its previous decision.
The document to support this standpoint is riddled with illogical and circular arguments and misses out numerous recent studies and international guidelines.
In particular the screening committee does list in evidence it will consider the ESC or AHA or FIFA position statements of cardiac screening in youth sports. There is no consideration of the JACC 2026 article reviewing outcomes of CRYS 10 year screening of more than 100000 voulnteers. The committe states that there is no evidence that screening can reduce sudden cardiac deaths while ignoring the ESC document on Ventricular arrhythmias which are evidence based consensus guidelines on managing conditions associated with SCD which the screening program would aim to identify the committee says that a screening program may make people anxious and put them off sport but doesn’t offer any evidence of this. They argue there isn’t infrastructure to support screening but ignore the fact this is the case for most screening programs - the workforce and infrastructure have to be provided for the screening to happen. They attempt to equate Israeli screening results with Italian while not acknowledging the Israeli results are based on newspaper reports of deaths in 2 newspapers and the Italian results are based on a comprehensive longstanding registry of all child and juvenile deaths. They draw on concerns from the US about the cost to families of follow up care after screening but don’t acknowledge this is less of an issue here due to the NHS. They don’t even refer to Japan and Taiwan which are the only 2 countries in the world who screen all their youth. Some serious clinical academics need to look at the “work” the committee have done here and at least call out their lack of rigour.
Wow I remember this! Wayne as you came up through the academy and pro system you benefited from regular best in world cardiac screening. Despite FIFA reccomendations saying it’s best practice, competitive grassroots footballers in UK don’t get cardiac screening. 12 young people a week in UK die of sudden cardiac death and 80% have no symptoms beforehand. On screening 1 in 300 young people in UK are found to have a condition that can cause sudden cardiac death. The UK government and the FA will not act. Italy Japan Taiwan Israel Texas Florida Pennsylvania and Tennessee all have laws that promote or mandate cardiac screening on young people. Can you speak out to give grassroots footballers the privilege you had growing up.