Is STEMI reperfusion a satisfied need?
🚩NO! - Most developing countries still face significant barriers for reperfusion
So, let me take you through our new "Clinical Consensus Statement for STEMI reperfusion in LMICs, representing ACVC, EAPCI, EAPC, ESCWGT & SSL"
A tweetorial
Nos falta entusiasmo por este “posible” quinto pilar 🤔
Vuelve al ruedo⁉️
Segunda oportunidad para digoxina (en forma de digitoxina) …..
💊 Digotoxina
Estudio #DIGIT-HF
⬇️18% del end-point primario ( 🪦 & 🏥 por IC)
👥1212 pacientes con HFrEF
FEVI ≤40% + NYHA III–IV o FEVI ≤30% + NYHA II
•Terapia óptima: BB (97%), ARNI (40%), MRA (76%), SGLT2i (19%), CDI 65%/TRC 25%
NNT:22
Segura…. Pero mayores eventos 4.7% vs 2.8%
-Bajo de poder ….. 🆗
Mejor digitoxina (por la ERC) mas estable.
Renacen los glucósidos⁉️
Mejor un digital que ivabradina⁉️
Nunca se fue el digital, sin embargo, su beneficio en hospitalizaciones generaba mayor dudas con el tratamiento actual, que ahora fue considerado 💊 (ARNI & iSGLT2)
#ESCCongress #SIACenESC
@cifacah
https://t.co/fAvsohTjxW
🚨 2025 Focused Update of the 2019 ESC/EAS Guidelines for the management of dyslipidaemias
#Cardiology#ESC2025#LipidUpdate
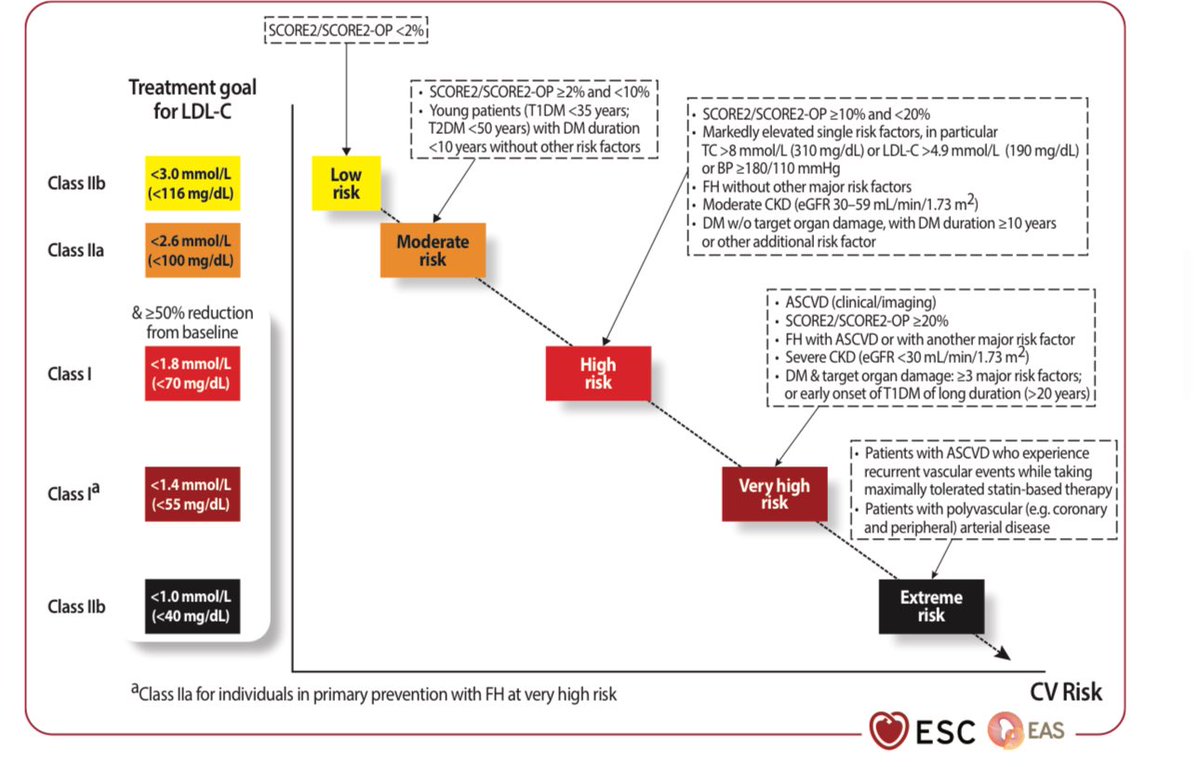
1️⃣ NEW cardiovascular risk estimation:
Use updated #SCORE2 & #SCORE2OP algorithms for 10-year risk in adults aged 40–89, calibrated to local mortality rates.
Risk categories: Very High, High, Moderate, Low.
2️⃣ LDL-C remains the main target ⚡
Lowering #LDLC reduces #ASCVD risk—start pharmacological therapy at thresholds determined by risk and baseline LDL-C.
Goal: “The lower, the better!”
3️⃣ 👨⚕️📉 Innovations in therapy 🧪
•Bempedoic acid now recommended for statin-intolerant/high-risk patients!
•Evinacumab for homozygous familial hypercholesterolemia (FH).
•Inclisiran: ongoing trials, promising ~50% LDL-C reduction.
4️⃣ Acute coronary syndromes (ACS): Early & intensive lipid lowering 🏥
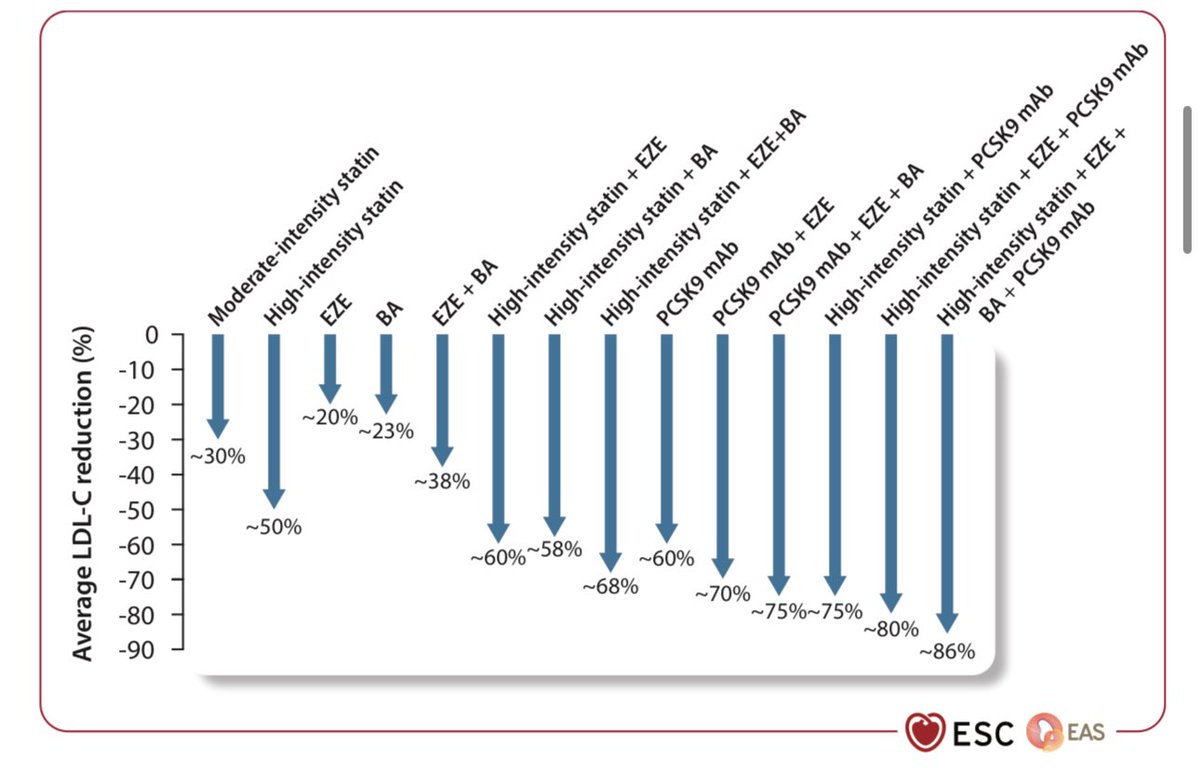
•Initiate high-intensity statin + ezetimibe during ACS hospitalization.
•Combination therapy = Faster & deeper LDL-C reductions, improved outcomes.
5️⃣ Lipoprotein(a): Causal role confirmed
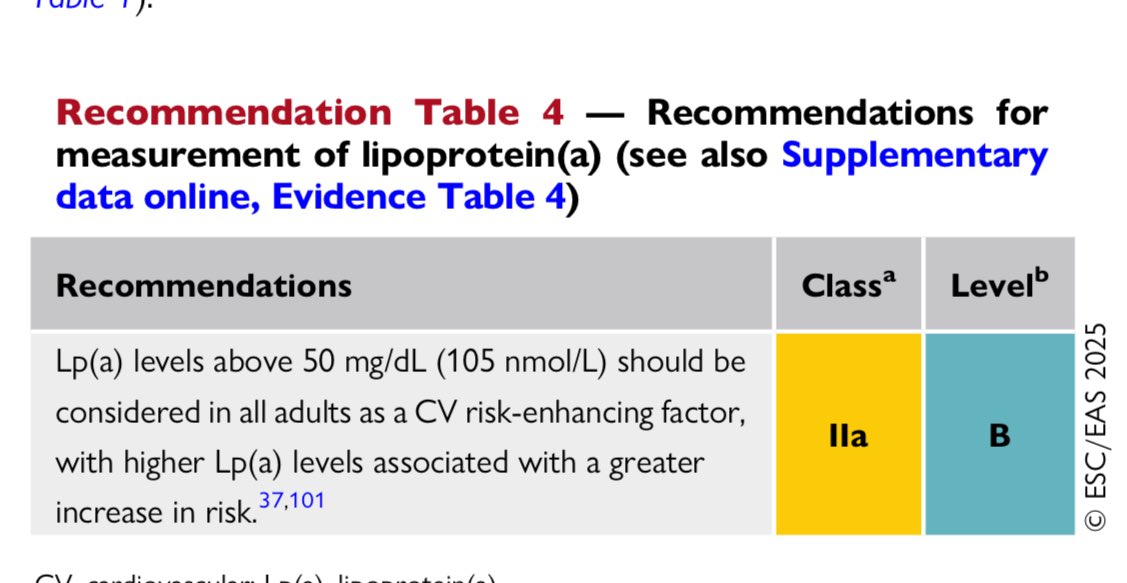
•Measure #Lp(a) at least once in all adults.
•Levels >50 mg/dL (≥105 nmol/L) are risk-enhancing, require aggressive management.
6️⃣ Hypertriglyceridaemia update
•Statins first-line; fibrates not indicated for CV event reduction.
•High-dose icosapent ethyl (4g/day) for high-risk patients with tg 135–499 mg/dL, proven CV event reduction.
•Volanesorsen for familial chylomicronaemia syndrome.
7️⃣ Special populations
•HIV: Statins recommended ≥40 years regardless of LDL-C.
•Oncology: Statins considered in high CV toxicity risk during anthracyclines.
8️⃣ Dietary supplements: 🚫 NOT recommended
•No supplement/vitamin without proven safety & LDL-C efficacy reduces #ASCVD risk.
•Statins and evidence-based therapies continue to lead.
#Guidelines #ESC #Dyslipidaemia #PreventiveMedicine
2025 ACC/AHA/ACEP/NAEMSP/SCAI
Guideline for the Management of Patients
With Acute Coronary Syndromes: @CircAHA@JACCJournals
🥸Here are class 1 recommendations from the document; Massive effort - congratulations to the authors: @SVRaoMD
😱 Below
👇👇👇
Top 🔟 ACC News Stories of 2024: https://t.co/sSR3cezcT6
1️⃣ ACC/AHA Perioperative Guideline
2️⃣ ACC/AHA Guideline on Management of Lower Extremity #cvPAD
3️⃣ ACC/AHA Guideline on Evaluation & Management of People W/ #cvHCM
4️⃣ ACC ECDP: Updated Guidance on #HFrEF Management
5️⃣ And more!
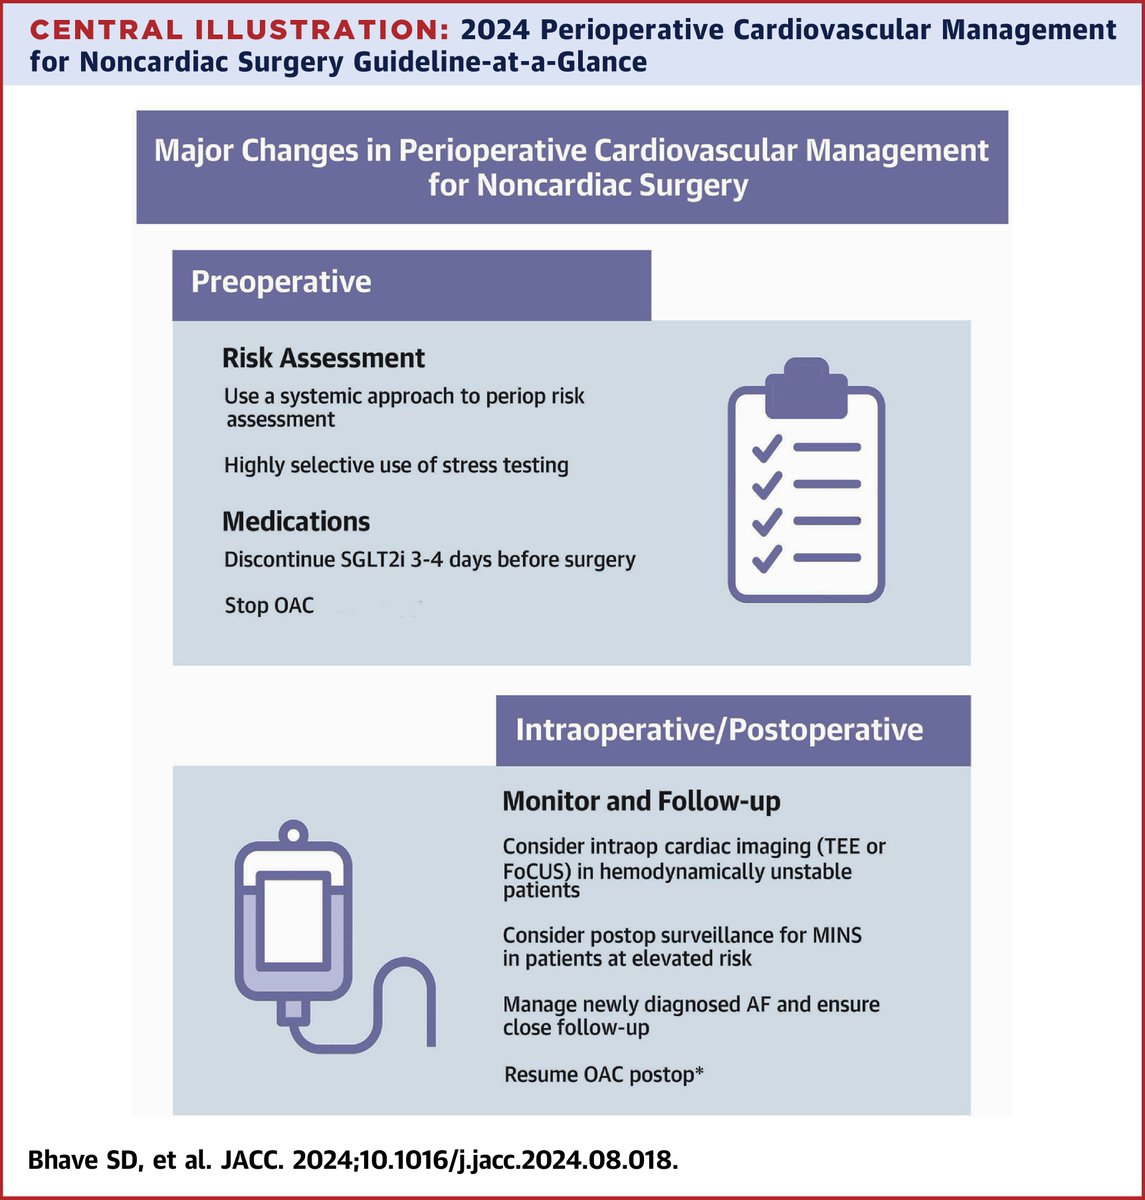
1/ Published today, the Guideline for Perioperative Cardiovascular Management for Noncardiac Surgery
📷: Stepwise Approach to Perioperative Cardiac Assessment.
Complete vs Culprit-Only Revascularization in Older Patients With Myocardial Infarction With or Without ST-Segment Elevation: @JACCJournals
🥸 A subanalysis of the Fire Trial: Physiology guided complete revascularization in older adults works!
😱 Summary
👇👇👇