GI Faculty #VanderbiltUniversity | Former Resident / Fellow #VUMC | Alumni of #VandyMed | Opinions mine and do not represent medical advice nor my employer
Received an amazing birthday gift today from the NIH with the notice of award for our R01 on novel therapeutics for achalasia!! #michaelvaezi#annegershon @VUMC_MD @VUMC_GI @Columbia. Celebrated today with complex EMR cases, esophageal dilations, and now toddler snuggles/cake!
Serious imposter syndrome giving my talk on EoE flanked by two titans @Khanna_S on a masterclass on C. Diff and #BrooksCash on Diarrhea @2026 Music City Summit. Thank you @ibddoc09 , Ziad and Michael for the invitation to speak!
Join us tomorrow for the 5th Annual GI and Liver Summit co-directed by @ibddoc09 for a stellar line up of internationally recognized leaders including my IBD friends @HorstIBDDoc and @BaldeepPablaMD and an update on EoE with me. Register here https://t.co/PvhBfo5oRr
So excited to share our work, vision, and management of Esophageal and Gastric Management of patients with solid organ transplant, especially lung transplant. Thank you to the @VUMChealth Transplant Course 2026 for the invitation!
Phenomenal talks by the leaders in the field on management by @AllonKahn@MRadlinski@andrew_scanga
🔑 UnderSaline EMR vs cold snare versus hot snare
🔑 High quality Barretts screening and identifying patients for EMR vs ESD
🔑 Baveno VIII = more eso stents and TIPS
Large polyps, resection of esophageal cancer, and management of variceal hemorrhage, oh my!
I will be moderating the best endoscopic session at our 2026 Vanderbilt Update Course on Endoscopy.
Looking forward to 🔥 talks by @MRadlinski@andrew_scanga and our guest @AllonKahn
A great roadmap for what to do when the PPI fails.
Persistent dysphagia and chest pain shouldn’t automatically trigger more acid suppression.
The challenge is figuring out what we are actually treating.
Optimize therapy.
Evaluate structurally.
Test physiology.
Assess motility.
And, importantly, learn to phenotype.
Because “PPI failure” may ultimately unmask ongoing reflux, reflux hypersensitivity, functional disease, or an esophageal motility disorder and each requires a very different approach.
Excellent practical framework from @RishiNaikMD on moving from persistent symptoms → objective testing → the right diagnosis → targeted treatment.
Are patients with persistent GERD symptoms being managed appropriately beyond PPIs? Find out more in this activity, Managing Erosive Esophagitis: When PPIs are Insufficient from my chief #MichaelVaezi , https://t.co/0MR4MTz5m3 @Medscape
Algorithms are helpful.
Patients don’t always follow them.
The best foregut care often starts where the algorithm ends, with thoughtful discussion, multidisciplinary collaboration, and clinical judgment.
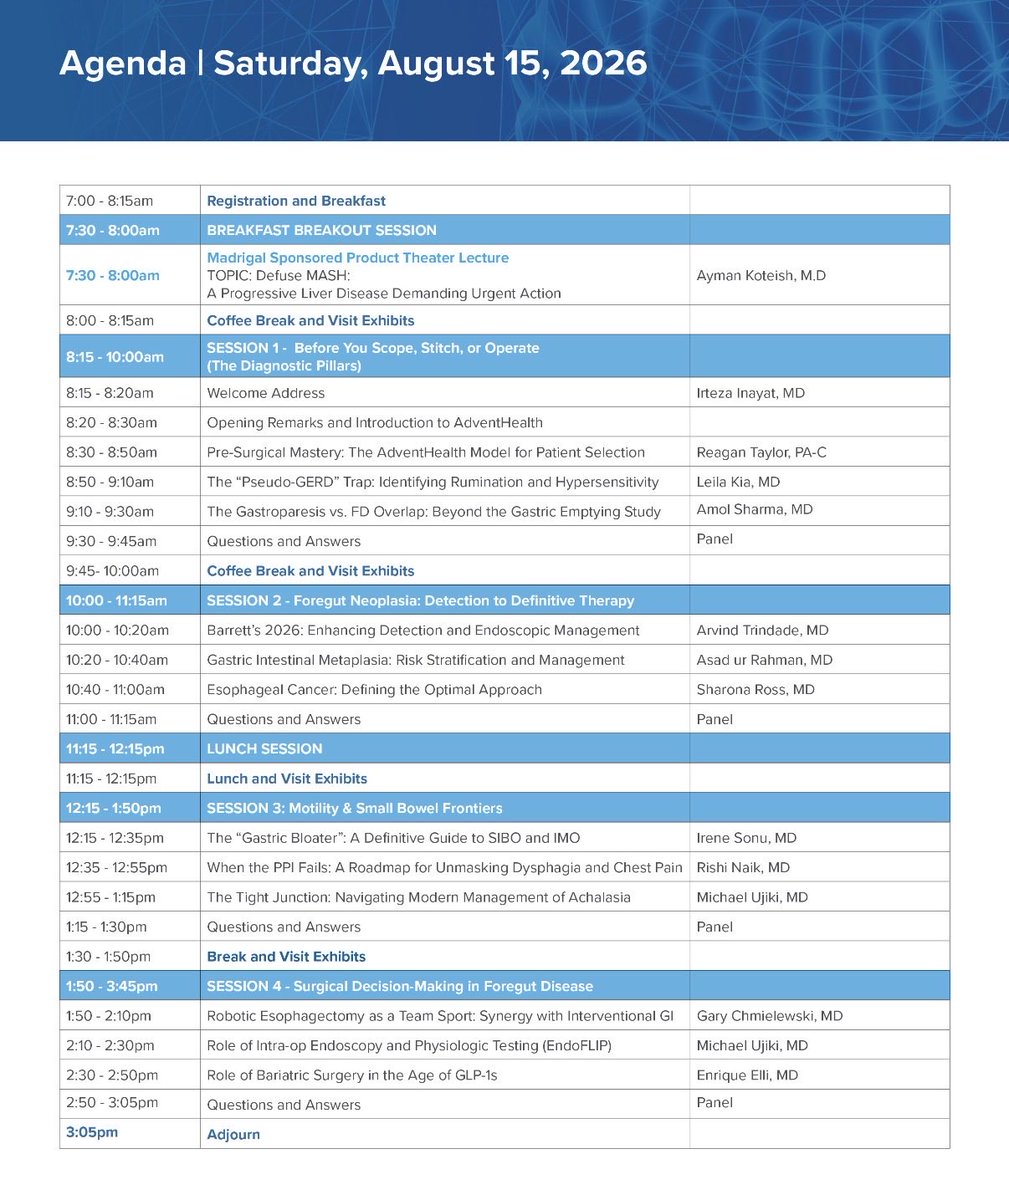
Looking forward to @AdventHealthCFL
“Updates in Foregut 2026” as we tackle some of the most challenging cases in foregut disease.
📍 JW Marriott Orlando
📅 August 15
Fellows & Residents Free Registration
#Gastroenterology #MedEd #Foregut