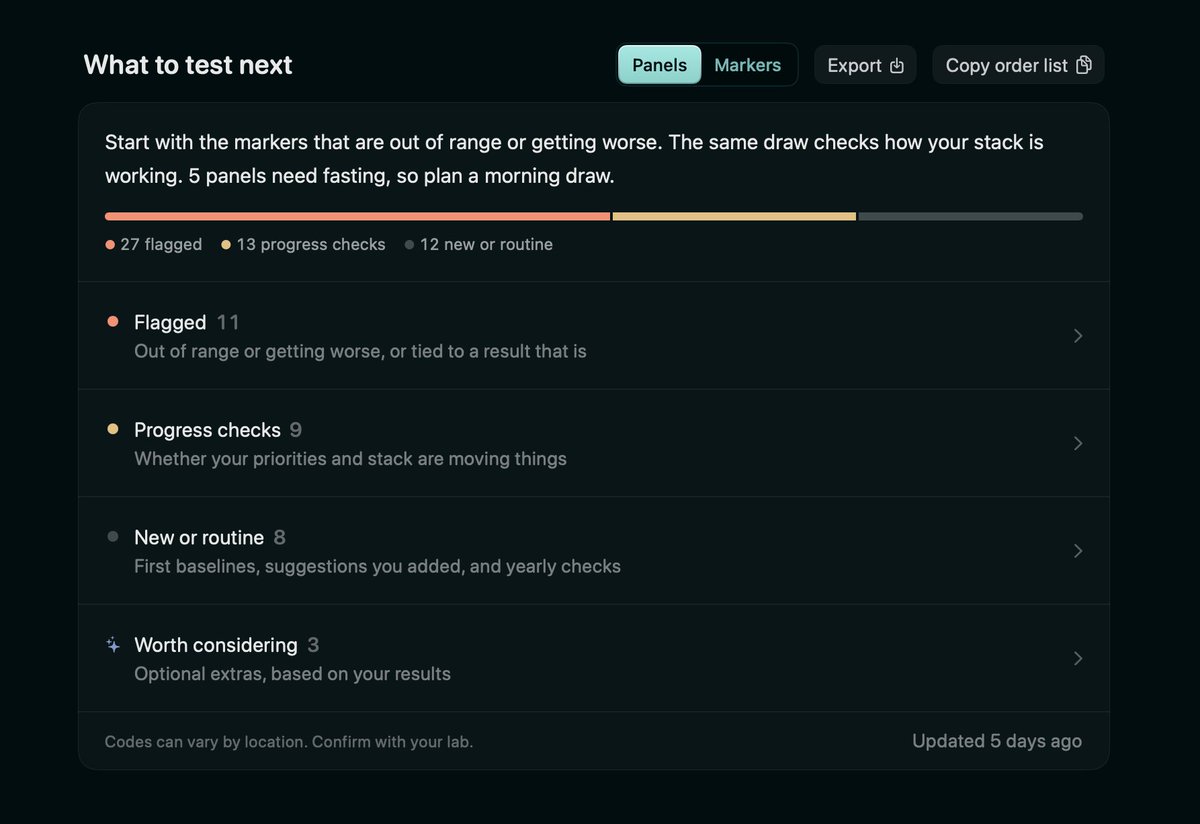
Hemo’s Action Plan, reimagined.
Your labs → a few clear priorities → small steps you can actually take.
Add one to your stack in a click. Hemo checks it against your results and sharpens the plan as new labs come in.
When it’s time for your next blood draw, Hemo shows you what to test next.
We’ve also redesigned the navigation and Stack UI to make it more usable.
Out now.
Interesting development in biological age tracking.
Unlike established clocks like GrimAge (DNA methylation) and PhenoAge (blood biomarkers), ClinicalAge uses longitudinal medical records to estimate biological age.
Another reminder that understanding how our health evolves over time can tell us more than any single biological age score.
ClinicalAge, an AI-derived metric from longitudinal electronic health records, varies widely from an individual's chronological age. And it's correlated with risk of many diseases and cancers, as shown below, from 2 huge cohorts @uk_biobank@LancetDigitalH
https://t.co/BzXgLzHdA9
NEW in Hemo: Your testing plan.
Tired of guessing which labs to order next? Hemo keeps track so you don't have to. It can also suggests new ones that match your unique needs.
Your testing plan is generated automatically based on your history. Since Hemo keeps track of all your labwork, it knows when certain markers are out of date, or when concerning measurements are ready for re-testing.
It will even suggest the best panels to order that provide the markers in question, or prefer panels you've ordered in the past.
I think the challenge is just getting in touch with the right person at the radiology dept, but ideally a radiology technician or the department manager. Just let them know you're hoping to find out a bit of information about the equipment before your scan.
But the question I'd ask is "which model CT scanner they use for CAC scans", and "what's the approx radiation dose for the imaging"?
I believe normal is ~1.0-3.0 millisievert (mSv) and low dose is <0.5 mSv (about 5 chest xrays, or just a few weeks of background radiation).
If you can find an ultra low dose Photon-Counting CT scanner (e.g. Siemens NAEOTOM Alpha), those have the lowest at ~0.1-0.2, but it does depend on their exact procedure.
Google "ultra low dose CT scanner machines in [your area]" you'll probably get a list of a few, then you can confirm with the hospital.
@MichaelAlbertMD Define "saving lives".
If disease awareness leads to lifestyle changes and preventative medication, is that not enough for meaningful impact?
NEW: Brad Gerstner (@altcap) & Jason Chang (@yoweichang) are trying to turn a $100 CAC heart scan into the “mammogram for the heart.”
At the All-In Summit, Brad brought his mobile coronary artery calcium CT scanner to screen attendees & make the case for preventing heart attacks at scale.
Heart disease kills ~800,000 Americans annually. Brad believes scaling CAC scans to 40M people a year could save 50,000 lives & $20B in government healthcare costs annually.
Rob Goldberg joined us to explain why the mission is deeply personal.
His brother Dave Goldberg, married to Sheryl Sandberg, died suddenly at 47 from undiagnosed heart disease, leaving behind their two young children. Just five months earlier, he had passed a running EKG.
“My brother had passed a running EKG five months before he dropped dead from heart disease, from undiagnosed heart disease.”
Dave’s death became the foundation for Sandberg’s book Option B, co-written with Adam Grant, about grief, resilience & rebuilding life after devastating loss.
Now Brad Gerstner, Rob Goldberg, Jason Chang & the rest of the besties, & the team behind the Center for Heart Attack Prevention want to prevent more families from experiencing the same thing, pushing for earlier detection, broader access to CAC scans & changes to the standard of care.
We go inside the mobile scanner & discuss:
› Why Brad calls CAC scanning the “mammogram for the heart”
› The Goldberg family’s experience with undiagnosed heart disease
› Why cholesterol & traditional testing can miss cardiovascular risk
› What CAC scores actually tell you
› Difference between a calcium CT scan & an angiogram
› Why Brad bought his own mobile scanner
› The “buy one, give one” model for expanding access
› Brad’s push to bring CAC screening to 40 million Americans a year
› How a roughly $100 scan could potentially prevent thousands of premature deaths
› Why Brad believes health data gives people the power to take action
𝐓𝐈𝐌𝐄𝐒𝐓𝐀𝐌𝐏𝐒
00:00 Brad Gerstner & Rob Goldberg
00:10 CAC Scanner Moonshot
01:53 Rob’s Family Tragedy
04:39 Center Missions and Prevention
05:37 Why Cholesterol Became Standard
10:07 Overcoming Fear and Insurance
12:29 CAC vs Angiogram Guidance
14:43 Where the Trailer Goes Next
16:40 Inside the Scanner Demo
20:48 Why Labs Miss Risk
23:27 Final Call to Action
Incremental Predictive Value of Deep Learning–Quantified Coronary Atherosclerotic Volume: A SCAPIS Cohort Analysis
Published: 28 August 2026
Conclusion:
Automated deep learning–quantified Total Plaque Volume improved prediction of first coronary events beyond SCORE2, coronary artery calcium score, and manually derived coronary CTA measurements, and identified even small plaque volumes associated with increased risk in a general population without established atherosclerotic cardiovascular disease.
https://t.co/fWktdxXZq5
We may be thinking about coronary artery disease the wrong way.
Traditionally, a lot of attention has gone toward stenosis: (how blocked is a particular artery?)
But a new study of more than 23,000 adults suggests the total amount of plaque throughout your coronary arteries may tell us more about future heart attack risk than whether you have one major blockage.
Researchers followed participants for nearly 8 years and used software to quantify total plaque volume from coronary CT angiograms.
Risk rose steadily as total plaque burden increased. People in the highest plaque-volume group had more than 6x the risk of heart attack or coronary death compared with those with no detected plaque.
And this is where it gets really interesting.
The automated analysis quantified plaque in roughly twice as many people as conventional readings by radiologists and cardiologists identified.
Even among people whose scans were manually read as showing no atherosclerosis, small amounts of plaque picked up by the software were associated with significantly higher future risk.
Adding that quantified plaque burden improved risk prediction beyond traditional risk scores, calcium scores, and the standard CTA interpretation.
And having one major blockage wasn’t necessarily the most important signal. Once researchers knew how much plaque was present overall, knowing whether someone had a ≥50% blockage added very little.
That points toward an interesting future for heart imaging:
Not just asking, “Do I have a blockage?”
But, “How much atherosclerosis do I actually have?”
This gets even more interesting as newer photon-counting CT scanners come online, making it possible to get detailed coronary CTA (CCTA) imaging at much lower radiation doses.
If you’re already discussing coronary imaging with your cardiologist, it may be worth asking whether quantitative plaque analysis is available.
We may be moving toward a world where we don’t just detect coronary disease.
We measure how much of it you actually have.