Elwood P. Dowd :
Years ago my mother used to say to me, she'd say, "In this world, Elwood, you must be" - she always called me Elwood - "In this world, Elwood, you must be oh so smart or oh so pleasant."
Well, for years I was smart. I recommend pleasant. You may quote me.
When some asshole sneers at a nun in Israel, this is trending news on Twitter for days, but when Arabs mow down half a dozen Christians with machine guns inside a Church in Jordan, the usual suspects remain totally silent. Curious, don't you find?
Today is a mathematical date we won't see again for 78 years.
10/24/26
10² + 24² = 26²
It's called a Pythagorean Triple Day. There are infinitely many Pythagorean triples, but only 12 dates this century satisfy the https://t.co/I0lvmau52v is the last.
Next one: March 4, 2105.
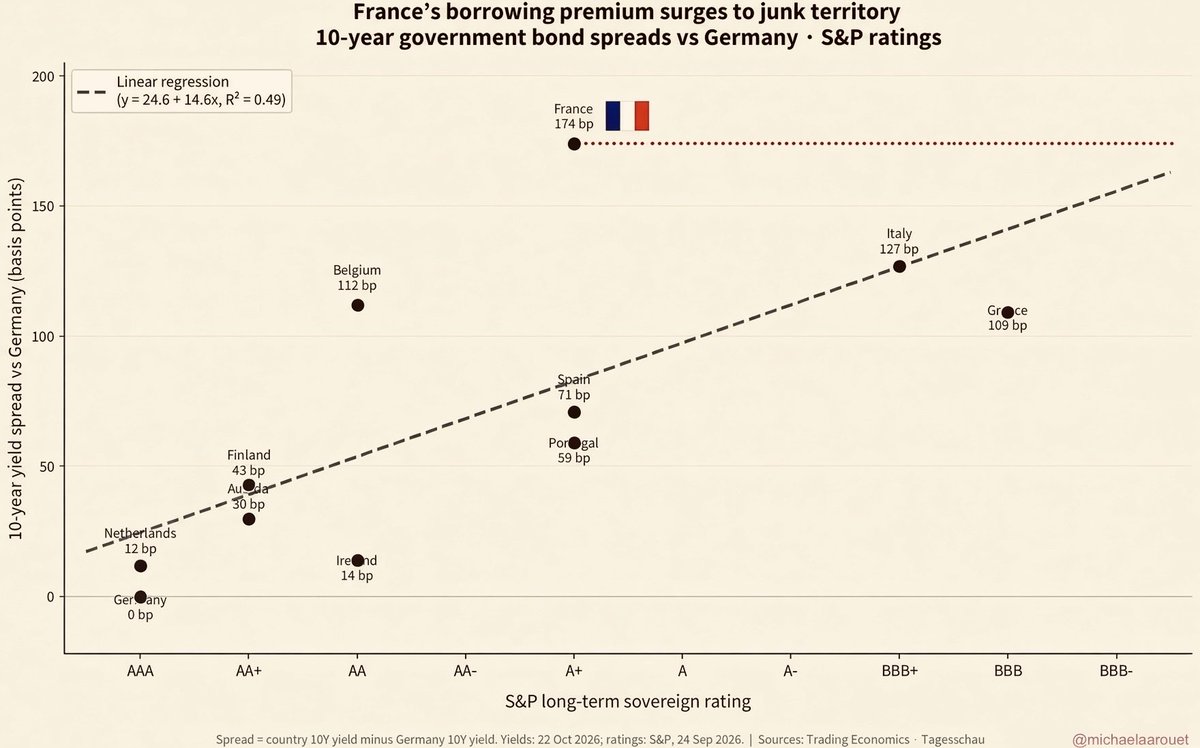
Many don’t yet grasp the seriousness of the French crisis. Markets have priced French debt as junk. The 10-year spread over German bunds has blown out to 174 bp, wider than Italy, Greece or Portugal, despite France’s AA-range S&P rating. The market concludes France’s fiscal arithmetic is broken and politically unfixable.
Public spending remains among the highest in the developed world (57% of GDP), an absurd tax burden already crushes growth potential, and the political system is paralyzed. Meaningful reforms have been impossible for years. When governments try, the unions and street response is rapid and often violent. Recent riots made the constraint explicit, any serious attempt to cut spending or raise the retirement age risks further unrest that damages business confidence, tourism and tax revenues. The short-term fiscal hit is already visible, the longer-term confidence channel is worse.
Higher borrowing costs compound the problem. Interest spending is set to exceed €90 billion next year, more than the defence or education budgets, and will keep rising as debt is refinanced at these spreads. That interest bill more than offsets any modest consolidation that might be legislated, widening the deficit and accelerating the debt-to-GDP ratio already near 120%. A ratings downgrade, which markets clearly anticipate, would raise funding costs for French banks, tightening credit, slowing growth and eroding tax revenues even further. That is the classic doom loop: higher yields → larger deficit → weaker growth and banks → even higher yields.
Rating agencies lag markets but will eventually follow the pricing. France lacks a governing majority capable of sustained fiscal adjustment without triggering further social paralysis and unrest. Until that changes, the market correctly treats French sovereign debt as much higher risk than its official rating implies. It is really difficult to imagine a scenario where France gets its act together and avoids a debt crisis taking down the entire eurozone with it. Please correct me if I’m wrong.
Duh! He's right.
They hate you, they hate Christians, they hate the West.
Egypt actively supported the Gazan's importing weapons and building the tunnel system. They lied about the eminent invasion, telling Israeli intelligence they were not aware of the threat.
Israel should finish Gaza - push the entire population into Egypt. Egypt supported them, Egypt deserves to share them.
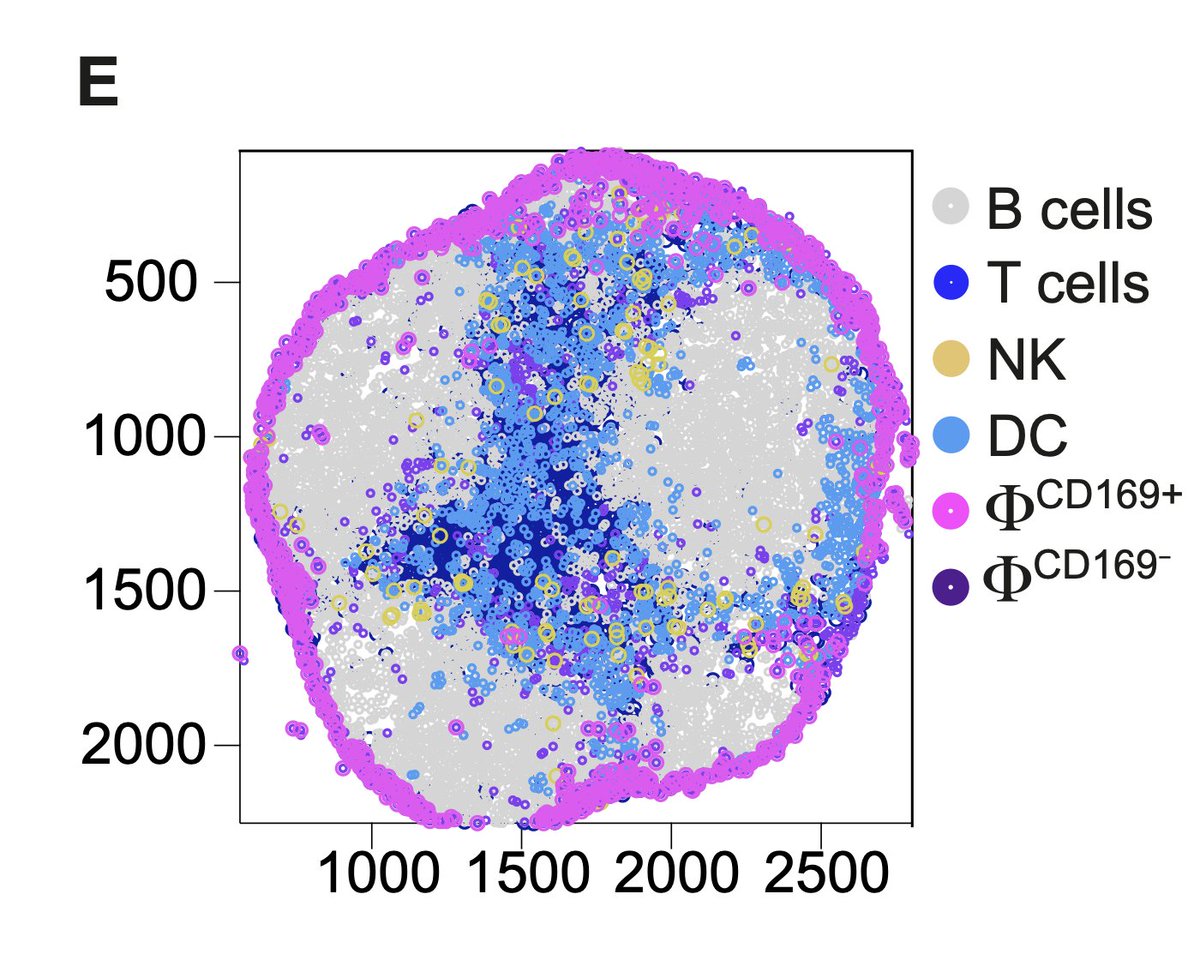
Super interesting paper suggesting lymph node protects plasma cells from ADCP. Might explain why TCEs and CAR-Ts work better in depleting B cells in lymph nodes.
I wish they measured BCMA instead of CD19.
The pink and purple are macrophages.
https://t.co/xwEV7iNzGm
@EliAfriatISR >>What do you think will stop the riots in France?
Nothing short of a radical rethinking of the approach.
There is no reason to believe France or much of the West has the will to resist Islam.
@MAGATexanMBA Interesting thesis.
Then why are so many BP doing poorly or depending on the purchase of biotechs that have done the discovery and approvals?
$TGTX Thank you R.
In PPMS stopping progression would be a huge win, but reduced EDSS scores is a home run.
Looks like TGTX has another winner. But unless they can shorten the time line to approval, there is still little or no PV.
A big and gutsy move would be to design and roll out a pivotal trial sufficient for approval.
One trial of stat-sig size could get approval in this underserved disease.
@boardyai $LQDA That 70 was Claude. I am agnostic on price predictions.
I do think the stock should move higher. But I am much more comfortable predicting financials. Those predictions will be iterative, moving as more data comes in.
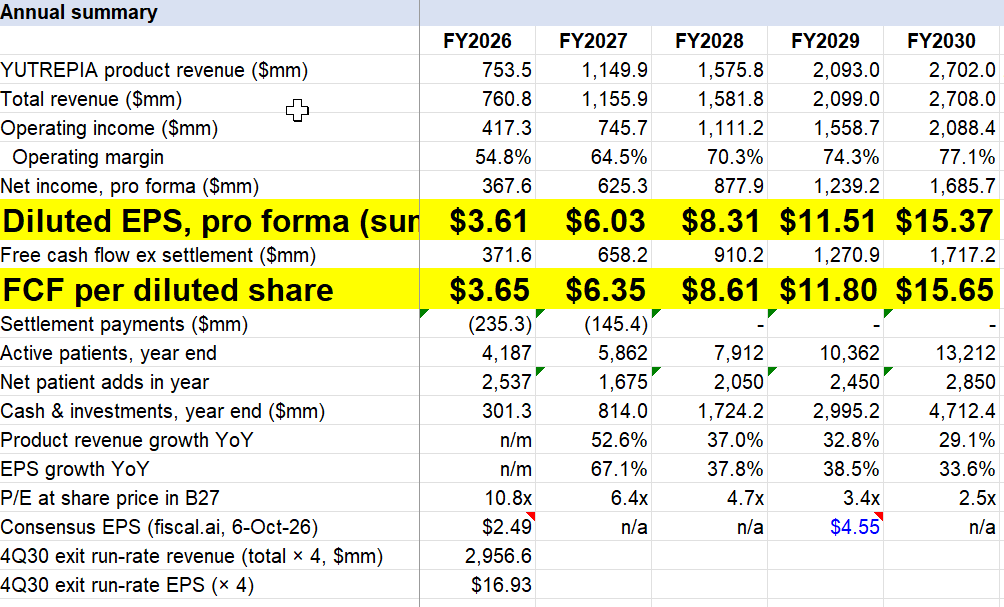
These are my model's projections:
$LQDA
LIQUIDIA (LQDA): SCIENCE, COMPETITION, VALUATION
------------------------------------------------
Written 2026-10-24 at $42.40. Fair value about $70 (range $60–80), roughly 65% upside, bear case near $28. YUTREPIA has taken ~28% of a $2.5B inhaled-treprostinil market in five quarters on a real pharmacologic edge (dose), and the settlement removed the existential risk; what is now being priced is how much of the business was PH-ILD, which the label no longer carries. Q4 2026 (reported February 2027) is the first quarter that answers it.
PREMISE CHECK
-------------
The '327 case is over: Judge Andrews held claims 1 and 14 valid and infringed on 2026-09-30, and the 2026-10-13 global settlement costs $380.7M ($175.0M net within 30 business days, two $72.7M installments by 2027-01-31 and 2027-04-30, $60.3M to antitrust-case participants) and removes PH-ILD from the label. Preliminary Q3 YUTREPIA sales were $222.7M (+30% QoQ) with $396.1M of cash at 2026-09-30, so the payments are fundable from operations, as management says. The dashboard's Drug Commercialization test reads 99.4 A STRONG, but note what it is scored on: your own FY26–FY30 model (EPS 3.61 / 6.03 / 8.31 / 11.51 / 15.37, pro forma ex-settlement), not consensus, which sits at 2.04 / 2.11 / 3.30.
THE SCIENCE
-----------
YUTREPIA's edge is engineering, not a new molecule: it delivers more treprostinil to the lung per session than Tyvaso DPI can, and PAH is a dose-responsive disease.
The disease. Pulmonary arterial hypertension (WHO Group 1, ~45,000 treated US patients) is progressive remodeling of the small pulmonary arteries; prostacyclin-pathway agents are the most effective class and the only one with a dose-response that clinicians titrate against symptoms. PH-ILD (Group 3) is pulmonary hypertension secondary to fibrotic lung disease, where inhaled treprostinil is the only therapy with a positive trial (UTHR's INCREASE, 2021); the '327 patent covers that use.
The mechanism. Treprostinil, a stable prostacyclin analogue, formulated by PRINT (particle replication in non-wetting templates) into uniform dry-powder particles sized for deep-lung deposition, delivered four times daily from a low-resistance capsule inhaler. Capsule strengths are 26.5, 53, 79.5 and 106 mcg, titrated upward as tolerated. Tyvaso DPI (Technosphere, MannKind) tops out at a 64 mcg cartridge; nebulized Tyvaso takes 2–3 minutes per session. Higher deliverable dose per breath, in a device patients prefer to a nebulizer, is the whole proposition.
The evidence, in order of rigor
Study: INSPIRE (PAH)
Design: Open-label Phase 3, ~120 patients: prostacyclin-naive starts and transitions from nebulized Tyvaso
Result: Safety and tolerability consistent with inhaled treprostinil (cough, throat irritation, headache); patients titrated to doses above Tyvaso DPI's ceiling; 6MWD gains larger at higher doses. Basis of the May 2025 approval
Study: ASCENT (PH-ILD)
Design: Open-label Phase 3
Result: Supported the PH-ILD indication now being withdrawn from the label
Study: Bioequivalence to Tyvaso
Design: PK bridging
Result: Approval rests on treprostinil's established efficacy (505(b)(2)); no new placebo-controlled outcomes trial
Study: Real-world (launch)
Design: ~5,900 unique prescriptions, >5,000 patient starts, >1,100 prescribers through 2026-07-31; ~30% of prescribers have written 5+ patients
Result: Adoption by both switchers and naive starts; payer access at parity with Tyvaso
Caveats a skeptic will raise. There is no randomized efficacy trial of YUTREPIA itself; the dose argument rests on an open-label study and on treprostinil's class pharmacology. Four-times-daily dosing is a real adherence burden against the once-daily products in development. The PH-ILD evidence is now academic: without the label the company cannot promote it, and payers may require a Group 1 diagnosis.
Pipeline. YUTREPIA in systemic sclerosis with Raynaud's (RE-WARM, 75 patients, Fast Track) and PH-COPD, both unserved. L606, a liposomal treprostinil nebulized twice daily (licensed from Pharmosa), is in the Phase 3 RE-SPIRE trial in PH-ILD, with a PPF/IPF study planned 1H27. The settlement explicitly does not cover indications other than PAH or new treprostinil products, so UTHR can assert against L606; that is the next legal front, not a closed one.
WHERE THE LAUNCH IS
-------------------
YUTREPIA is approaching 30% of a US inhaled-treprostinil market that grew ~6% quarter on quarter in Q2; the question for the next two quarters is how much of its own book was PH-ILD.
Metric: YUTREPIA net sales Q1 / Q2 / Q3 (prelim) 2026
Value: $130M / $170.4M / $222.7M
Metric: Run-rate revenue (Q3 x 4)
Value: $890.8M
Metric: TTM revenue (to Sep '26)
Value: $619.3M
Metric: Gross margin
Value: 93%
Metric: Operating margin TTM
Value: 37%; Q2 operating income $85.5M, net income $74.7M ($0.74)
Metric: Free cash flow, last 4 reported quarters
Value: −$10.7M, $42.2M, $50.2M, $69.0M
Metric: Cash / debt (Jun '26)
Value: $284.2M / $176.2M; cash $396.1M at Sep 30 before the settlement payments
Metric: Inhaled treprostinil category Q2 2026
Value: ~$607–623M (Tyvaso DPI $326.6M +4% YoY, nebulized Tyvaso $126.0M −18%, YUTREPIA $170.4M)
Metric: Management's stated aim
Value: "well on our way" to >$1B net revenue in 2027 (pre-settlement remark, August)
Growth is coming out of nebulized Tyvaso first (−18% YoY on volume) and from category expansion; Tyvaso DPI is still growing on price. UTHR says competition hurt all three of its treprostinil lines.
Consensus vs your model. Consensus (https://t.co/jiTIqPhoBj mean) revenue $717M / $762M / $886M for FY26–28 and EPS 2.04 / 2.11 / 3.30 — numbers that imply the business stops growing at the Q3 run-rate. https://t.co/jiTIqPhoBj's in-house estimate is $758M / $1,250M / $1,600M. Your model is $761M / $1,156M / $1,582M with EPS 3.61 / 6.03 / 8.31. The Street mean looks stale and PH-ILD-shocked at once; the gap between it and the run-rate is the opportunity and the risk.
COMPETITIVE THREATS, RANKED BY CONSEQUENCE
------------------------------------------
The near-term threat is regulatory and commercial (the PH-ILD carve-out and UTHR's IPF label), the long-term one is dosing convenience (once-daily inhaled and oral prostacyclins).
Rank: 1
Threat: PH-ILD label removal
What it is: Supplement filed to strike PH-ILD; no promotion; '327 claims held valid
Status: In force since 2026-10-13
Why it matters: Tyvaso's post-2021 growth was predominantly PH-ILD; if YUTREPIA's mix is similar, new starts in a third to a half of its addressable pool stop. Your view that physicians code PH-ILD as Group 1 to stay on drug is the swing variable, and payers are the check on it
Rank: 2
Threat: UTHR nebulized Tyvaso in IPF, then Tyvaso DPI in IPF/PPF
What it is: TETON program; sNDA under review
Status: Decision expected late April 2027
Why it matters: Opens the ILD community to UTHR alone and reinforces nebulized Tyvaso in exactly the patients YUTREPIA can no longer court
Rank: 3
Threat: Insmed TPIP
What it is: Once-daily dry-powder treprostinil prodrug; Phase 3 PALM-PAH and PALM-ILD enrolling; positive 12-month OLE data in PAH
Status: Readouts 2027–28, launch 2028+
Why it matters: The direct successor product: same molecule, once daily vs four times; the first thing a YUTREPIA patient would switch for
Rank: 4
Threat: UTHR ralinepag
What it is: Once-daily oral IP receptor agonist
Status: NDA accepted; PDUFA 2027-06-24
Why it matters: An oral alternative for patients escalating from PDE5/ERA who would otherwise go inhaled; UTHR also plans a ralinepag DPI
Rank: 5
Threat: Tyvaso DPI itself
What it is: Incumbent dry powder, record starts and patients in Q2 per UTHR
Status: Now
Why it matters: Still growing on price; UTHR's field force and hub are the default; a 64 mcg ceiling is its weakness
Rank: 6
Threat: Merck Winrevair (sotatercept)
What it is: Activin signaling inhibitor, add-on
Status: Approved; outcomes trials positive
Why it matters: Slows disease and may delay escalation to prostacyclins; a headwind to category growth, not a substitute
Rank: 7
Threat: UTHR patents vs L606 and new indications
What it is: Settlement covers YUTREPIA in PAH only
Status: Open
Why it matters: The litigation risk did not end; it moved to the pipeline
Not a threat: Gossamer's seralutinib missed its PROSERA primary endpoint (+13.3 m 6MWD, p=0.032 vs alpha 0.025, Feb 2026). Generic nebulized treprostinil remains delayed.
BALANCE SHEET
-------------
Liquidia funds the $380.7M settlement from cash and operations without a raise; the cost is roughly one year of free cash flow.
- Cash $396.1M at 2026-09-30 (prelim). Payments: ~$175M by mid-November, $60.3M in October, $72.7M by 2027-01-31 and 2027-04-30. Pro forma cash troughs near $90–130M around year-end before Q4 collections, then rebuilds; management expects no additional financing.
- Debt $176.2M ex-leases at June 30 (HealthCare Royalty facility); net cash +$108M then, roughly net debt of $50–80M at the trough.
- Free cash flow ran $69M in Q2 and should be ~$90–110M a quarter at the Q3 run-rate before settlement outflows; R&D is guided to double in 2H26 and rise again in 2027 for ten studies.
- Book value per share $2.19; 89.1M shares outstanding, ~102–110M diluted.
VALUATION
---------
Probability-weighted value is about $70 a share (30% bear, 50% base, 20% bull) against $42.40.
Assumptions common to all three 2028 scenarios: 93% gross margin, opex rising to $450–520M for the trial program, ~21% tax once NOLs run down, ~108M diluted shares, settlement payments complete in 2027, present values discount year-end 2028 at 12%.
Scenario: Bear
2028 YUTREPIA revenue: ~$850M
What has to be true: PH-ILD was ~45% of the book and new ILD starts stop; growth stalls at the Q3 run-rate in 2027, TPIP looms
EPS: ~$3.0
P/E: 12x
Value YE-2028: $36
PV at 12%: $28
Scenario: Base
2028 YUTREPIA revenue: ~$1.4B
What has to be true: PAH share keeps climbing toward 45% of a growing category; residual off-label PH-ILD persists; SSc-RP not yet contributing
EPS: ~$6.3
P/E: 15x
Value YE-2028: $95
PV at 12%: $74
Scenario: Bull
2028 YUTREPIA revenue: ~$1.6B (your model)
What has to be true: Your FY28 of $1.58B / EPS 8.31: category keeps compounding, PH-ILD leakage small, first expansion data
EPS: ~$8.3
P/E: 18x
Value YE-2028: $150
PV at 12%: $117
Cross-checks:
- At $42.40 the stock is 4.3x the Q3 run-rate and ~14x the Q2 annualized EPS of $2.96, for a business compounding 30% a quarter with a 37% operating margin: the market is pricing a PH-ILD-driven stall.
- Consensus FY28 EPS of $3.30 is the bear case; your model is the bull case; https://t.co/jiTIqPhoBj's own revenue estimate ($1.6B FY28) sits with you.
- https://t.co/jiTIqPhoBj price target $54.38 (+28%), down from $107.75 in August before the ruling. The dashboard's 9% DCF on your EPS prints $257 (+507%); discount it, as it compounds your 2030 EPS at 10% for five more years.
WHAT TO DO AND WHAT TO WATCH
----------------------------
Own it, sized for a stock that will move 20% on the Q4 print either way; the base case alone is +75% and the settlement removed the scenario that went to zero.
- Q3 call (November): PAH vs PH-ILD mix of the patient base, new-start trends since 2026-10-13, Q4 commentary, exact settlement cash timing.
- Q4 2026 print (February 2027): the first full quarter without PH-ILD promotion; sequential YUTREPIA growth above ~10% says the book held.
- FDA action on the PH-ILD label supplement and any payer policy changes requiring a Group 1 diagnosis.
- UTHR: IPF decision (late April 2027), ralinepag PDUFA (2027-06-24), and any new patent assertion against L606 or RE-WARM.
- Insmed PALM-PAH / PALM-ILD readouts (2027–28).
- RE-WARM (SSc-RP) and PH-COPD data: the first indications where YUTREPIA has no UTHR patent overhang.
SOURCES
-------
- Liquidia: global settlement with United Therapeutics, 2026-10-13 (https://t.co/t5M3SpXpwq) — payments, PH-ILD label supplement, Q3 preliminary sales and cash
- Liquidia Q2 2026 earnings call transcript (https://t.co/e80c0NHVmt) — sales, patient and prescriber counts, category size, pipeline
- United Therapeutics Q2 2026 results, 2026-08-05 (https://t.co/XCn07GOh3R) — Tyvaso DPI / nebulized Tyvaso revenue, IPF and ralinepag filings
- Zacks via Yahoo Finance, 2026-09-23 — Tyvaso DPI overlap, UTHR IPF sNDA timing, Insmed TPIP Phase 3 status, ralinepag PDUFA
- HCPLive, 2026-02-23 — PROSERA Phase 3 topline (seralutinib)
- Agent Dashboard: LQDA Drug Commercialization result (scored on Jim's model), https://t.co/jiTIqPhoBj workbook and Free CF report harvested 2026-10-24.
We were trained prior to go to Vietnam to lay down a field of fire so intense, the enemy couldn't poke his head up to fire back.
Democrats are good at that.
Republicans suck at it.
Carville: Dems Will ‘Investigate the Hell Out‘ of Trump‘s ‘Corruption‘ https://t.co/j1Tpj2tV5h
Some do.
I may be wrong, but I do not think FTC would try to block it. Only way to be sure is to try.
I'd argue that whatever anti-competitive effect it is offset by the benefit to patients and given the patent estates, the only company that can completely serve the patient populations is UTHR.
Lyndon Johnson declared war on poverty in January 1964, and poverty promptly won.
The Office of Economic Opportunity launched that same year, spending $800 million in its first year alone. By 1980, the federal government had spent over $3 trillion (in today's dollars) across the constellation of Great Society programs: Medicaid, food stamps, housing subsidies, community action agencies, the whole apparatus. The poverty rate in 1964 sat at 19 percent. By 1973, it had fallen to 11 percent. Impressive, until you notice it was already falling at precisely that rate throughout the 1950s, before Johnson spent a single dollar.
The market was already doing the job.
What Johnson created was a dependency infrastructure. The Aid to Families with Dependent Children program paid higher benefits when no father lived in the household, which subsidized his departure.
Between 1965 and 1980, out-of-wedlock births among black Americans climbed from 25 percent to 56 percent. Charles Murray documented the numbers exhaustively in "Losing Ground" (1984), and the left never refuted the math; instead, they attacked Murray personally.
Bureaucracies administer poverty rather than eliminate it. Every dollar Washington sends to a poor family in Chicago passes through a federal agency, a state agency, a county office, and a caseworker's desk first. The machinery consumes a stunning share before anything reaches you.
Capital formation, voluntary exchange, and sound money pulled more people out of destitution in the 19th century than every federal program combined has since Johnson's cameras rolled in the Rose Garden.
I agree that $UTHR is the natural buyer. Yutrepia and L606 in the hands of UTHR are both far more valuable.
So no third party buyer would make the bid without a substantial breakup fee. Why would $LQDA do that? It just reduces the shareholder buy out price from UTHR?
However, when Yutrepia makes substantial inroads into the UTHR franchise, UTHR will need to buy the company.
Fortunately, Guyana formerly known as Guiana when it was a British colony has chosen to be an oil producing country in stark contrast to the UK.
In the last five years the GDP of Guyana has soared 5 fold.
The UK chose a different path. Tax the oil producers in the North sea into contraction, cutting production by ~80% to 1.1M bpd.
Norway is gratefully pulling out over 4M bpd.