Glomerular crescents 🌙
❓What’s a crescent?
🔬Crescentic GN?
🧩 How are crescents formed?
🔬🗂 Types of crescents? ❗️Pseudo-crescents?
(1/6)
#renalpath#PathResidents#Pathbracket
Atypical necroinflammatory interstitial nephritis can be seen in SLE patients. This lesion is similar to lesion seen lymph nodes of KFD patients https://t.co/cxK1eqhAvN
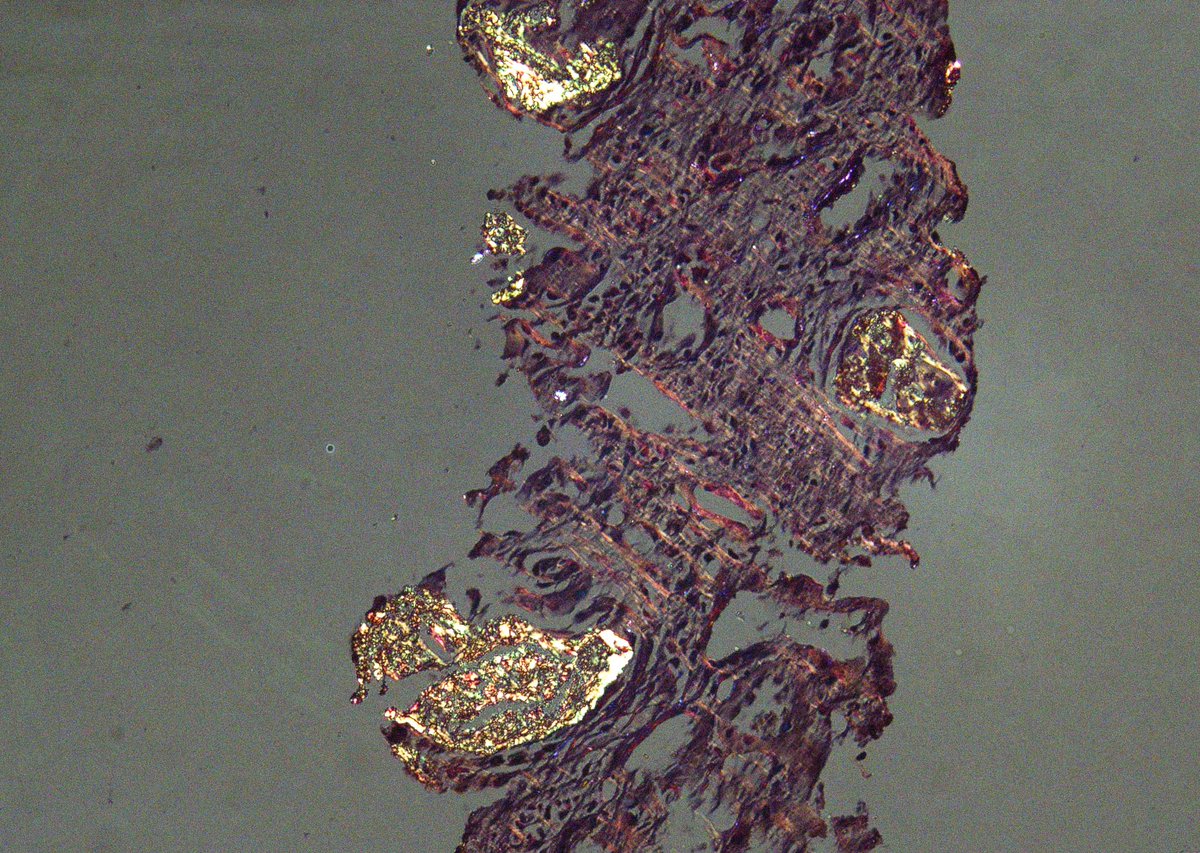
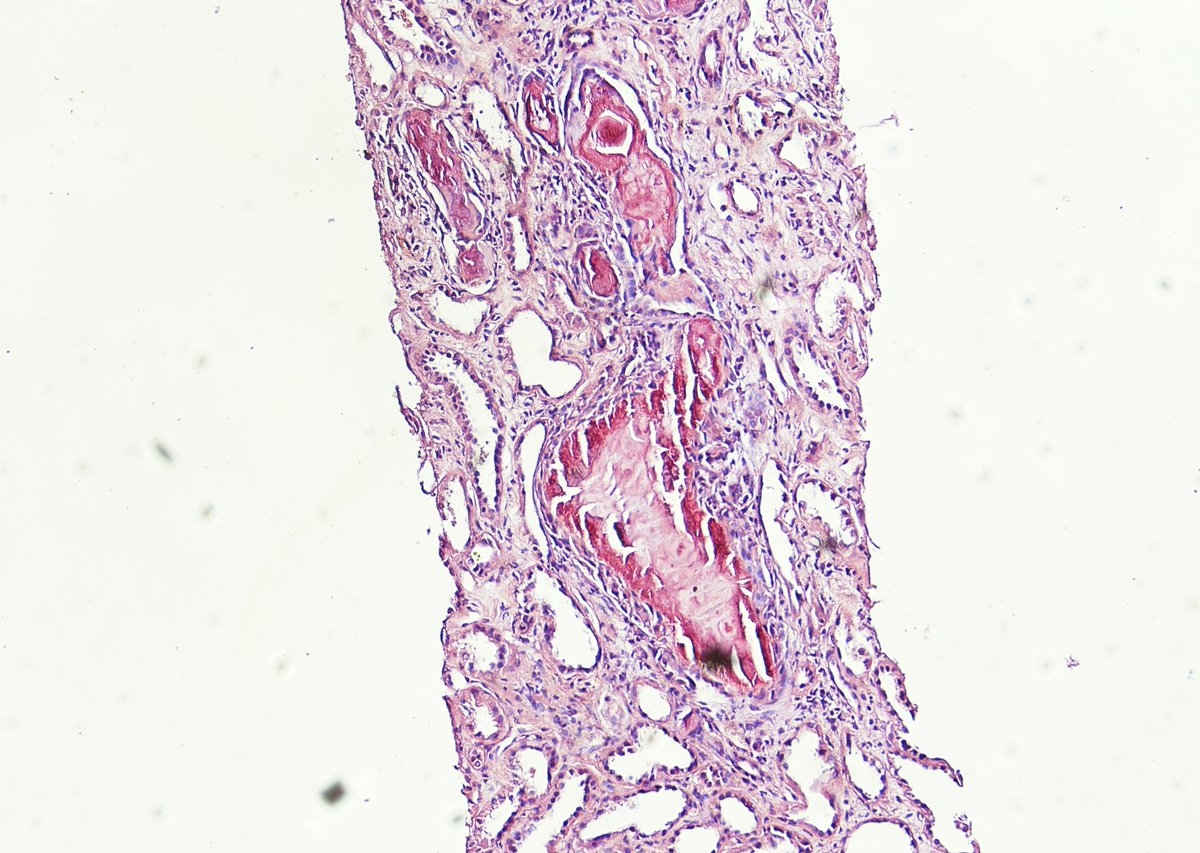
An interesting case of Amyloid cast nephropathy with Lambda restriction in 62 yr, male with AKI. Diffuse congophilic casts with Apple green birefringence on polarising light.
73y,M,proteinuria for 40yrs(start with sudden NS, treat with ARB and TW, UP fluctuate+~++,no steroid use). Recent 24hUP12g,ALB15g/L, FSGS lesion with IgA++ deposits, diffuse FPE and mesangium EDD. Would you consider secondary FSGS due to IgAN, or primary FSGS with IgA deposits?
Can you access the WHO Blue Books when you need them? Pathologists, trainees and researchers worldwide: share your experience in our survey. All levels of access welcome.
https://t.co/1ClvGTAEUM
#Pathology
Kidney biopsy findings in a patient treated with complement inhibitor-pegcetacoplan. First one for me.
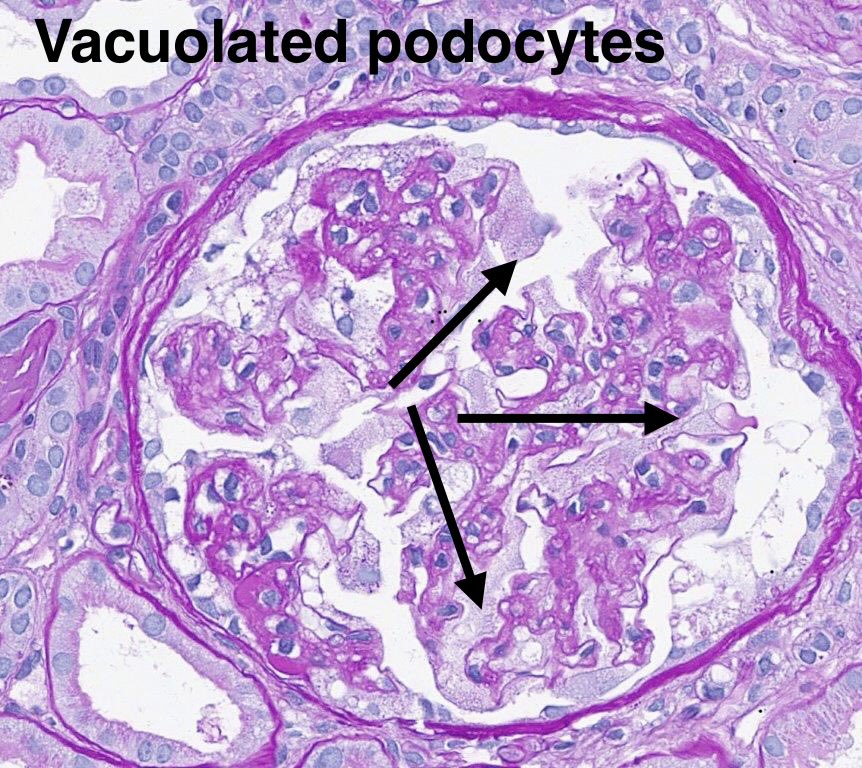
Glomeruli appear and vacuolated and washed out. The vacuoles are most prominent in the podocytes.
The interstitium also contains vacuolated cells.
Glomeruli appear non proliferative and were negative for Ig and C3 on Immunofluorescence.
However, there was extensive global glomerulosclerosis and tubular atrophy and interstitial fibrosis.
Some of the best hump-like deposits are seen with cases of C3 GN. This case in a 50's y/o pt with monoclonal gammopathy https://t.co/gRy4WcaU0v. #renalpath#pathtwitter
Clinicopathological Features of NELL1-Associated Membranous Nephropathy with Tubular Basement Membrane Deposits - Kidney International Reports https://t.co/9wmA5W5aF5
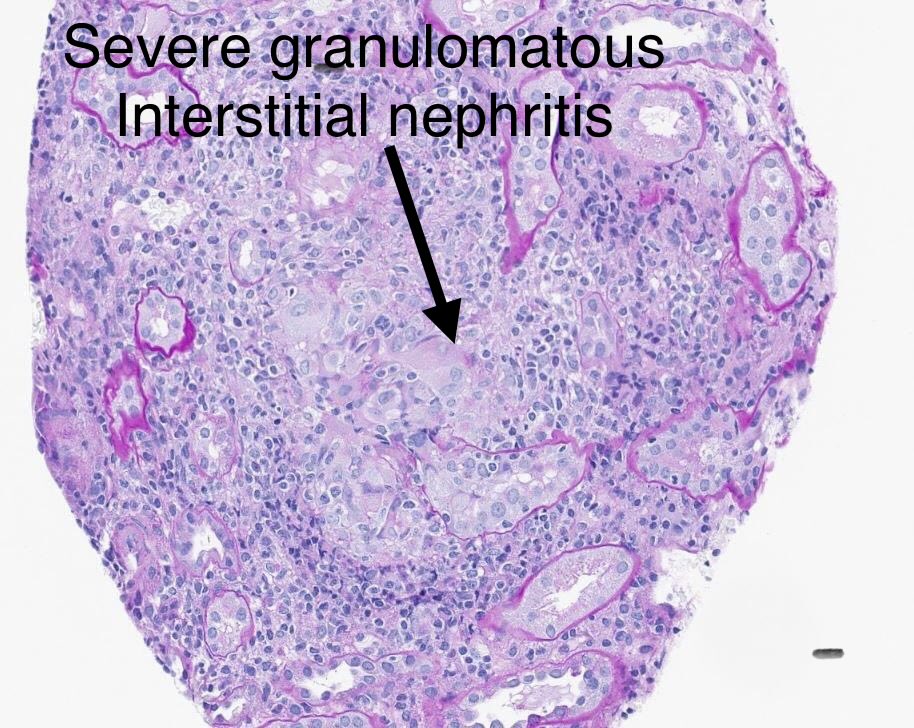
Tough case.
LM: granulomatous interstitial nephritis, extensive.
IF: negative.
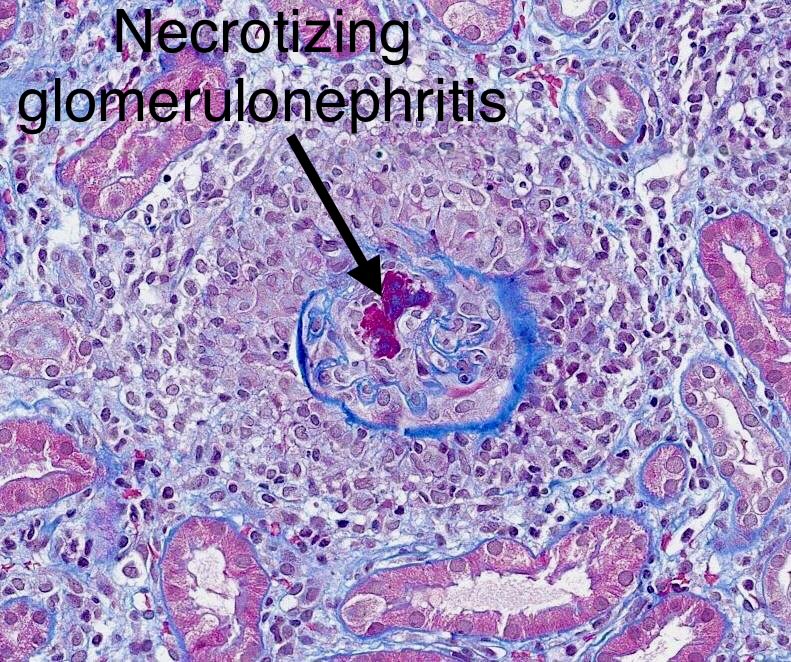
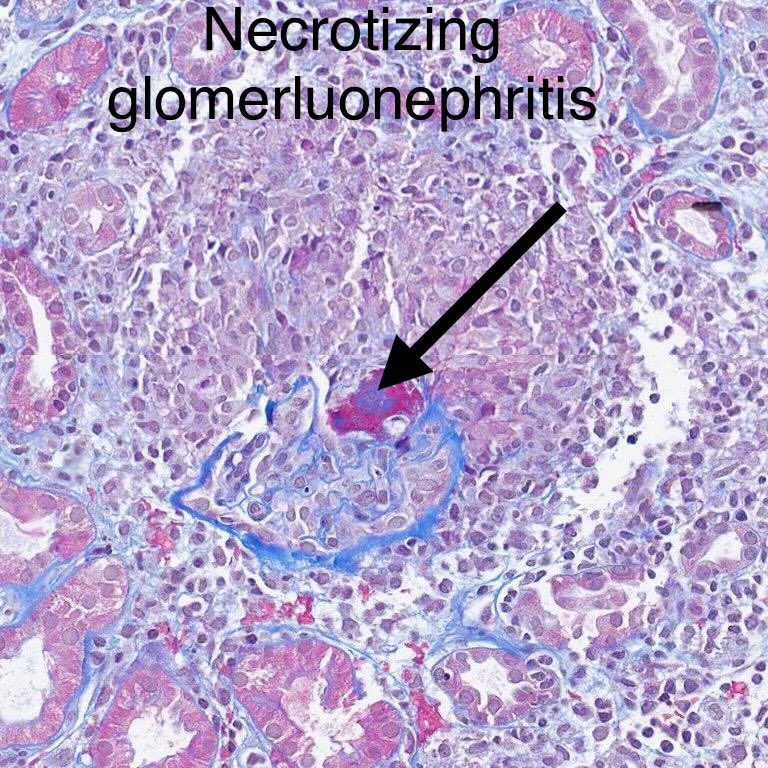
Look carefully and you start seeing small foci of necrosis in glomeruli, surrounded by inflammation/rupture of Bowman’s capsule.
Dx: 1. Granulomatous interstitial nephritis. 2. Necrotizing glomerulonephritis, pauci-immune. (both possibly drug related).
30-yr woman with rash, serum creatinine 10, bipolar disorder-just started treatment. ANCA, other serology negative.
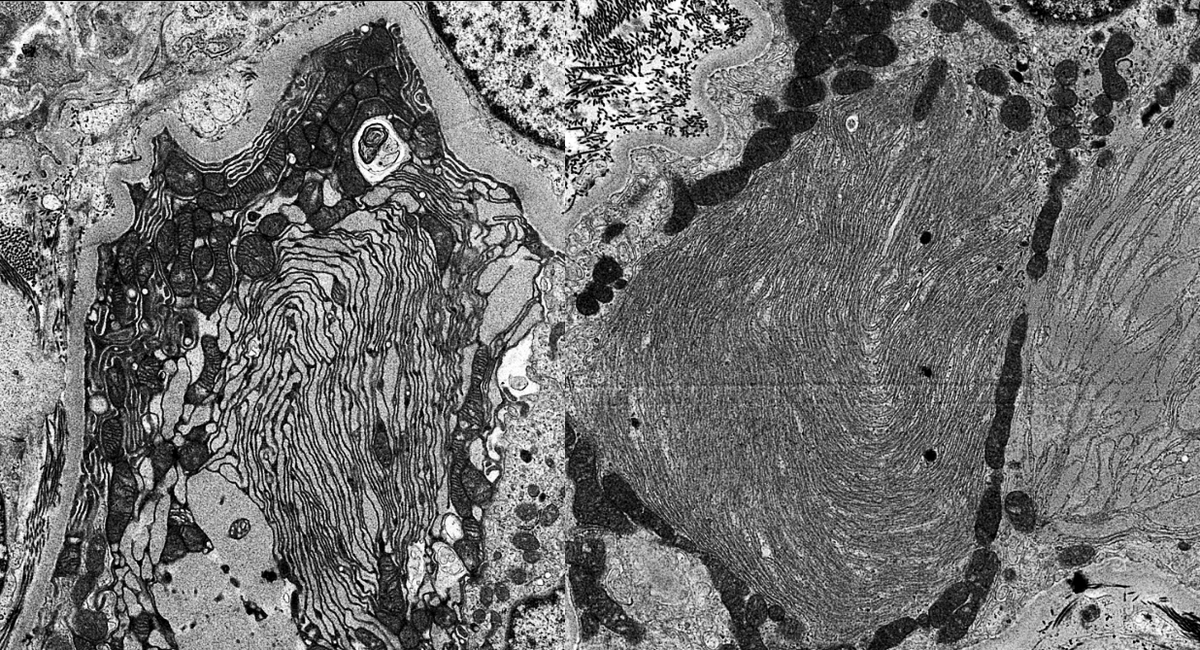
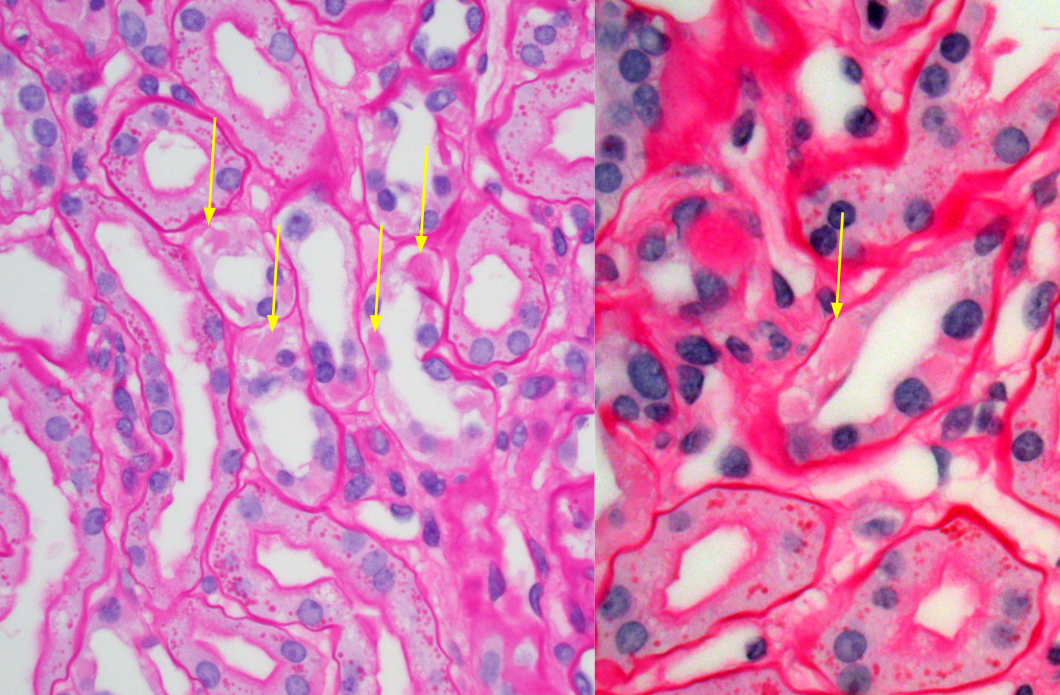
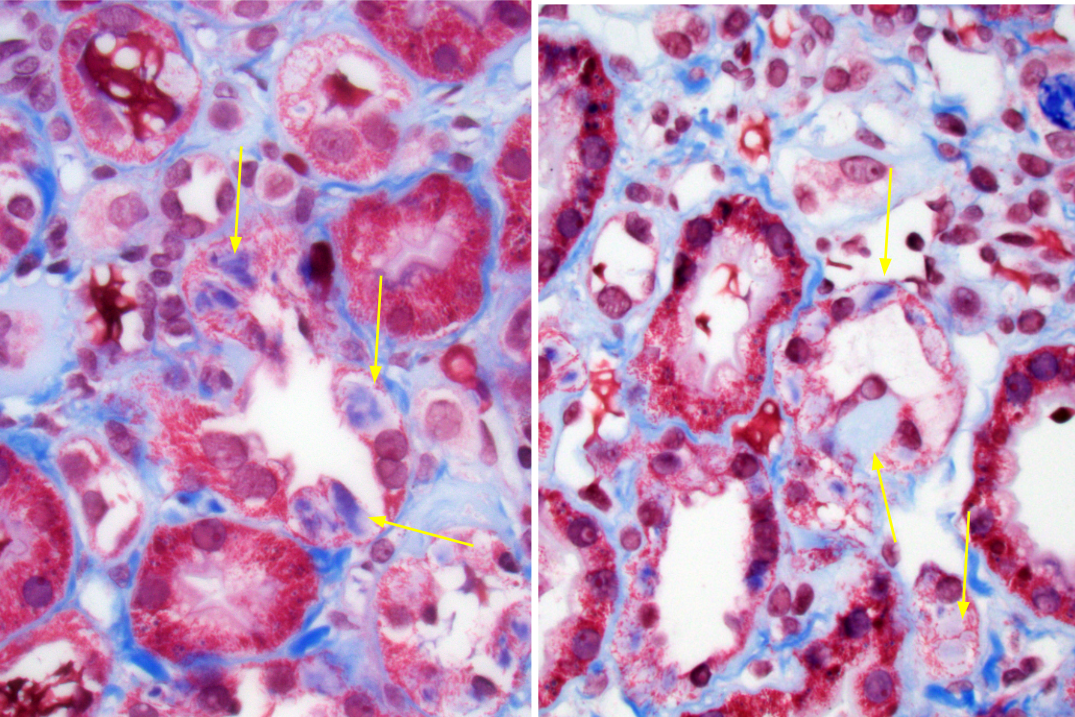
Young pt with family history of CKD, hyperuricemia, increased Cr. Fluffly thick ascending limb inclusions; blue on trichrome stain. Hyperplastic ER with dilated cisternae and stacked lamellar structure by EM. Characteristic for Uromodulin-related kidney disease. #renalpath
The ultrastructure of a cast: the art and science of renal tubular pathology: Ultrastructural Pathology: Vol 50 , No 3 - Get Access
#EM#ultrastucture#renalpath
https://t.co/QkgLwQNx5t
To confirm the interstitial amyloid was ALECT2 amyloid.
The patient was Hispanic. ALECT2 was likely an incidental finding.
Check out this very timely publication ⬇️
Co-occurrence of systemic anti-neutrophil cytoplasmic antibody-associa… https://t.co/nml5RspEUc
Well developed example of medullary angiitis (https://t.co/oqTXYTE2Fx) in a case of MPO-ANCA associated GN. Neutrophils and hemorrhage in the medulla. Also plenty of active crescents in this case. #renalpath#pathwitter#nephrology