https://t.co/GcdSi6PQ0r
Spent the last 2 months editing this video. Learned a lot making it.
This one is for all the Residents and Med Students who need a clear, step-by-step refresher on Above-Knee Fem-Pop Bypass with PTFE.
Things I covered:
1-Longitudinal vs transverse incision for femoral artery Exposure.
2- Dissecting the CFA in a fibrotic field
3-Popliteal artery segments.
4- Medial vs lateral exposure of the "P1" popliteal artery.
5-How to tunnel. Superficial vs deep tunneling.
6- How to bevel a graft.
7-Optimal arteriotomy size....
and much more.
If this can help even a handful of trainees, it was worth every hour 😁. #VascularSurgery #MedEd
@docpark When the in-situ vein splits, we follow the segment where the valvulotome has passed (usually the larger, straighter one) and ligate the other.
We’d like to thank Pr. Franco Grego and the organizing committee of the #VIPConference for an amazing meeting.
Meeting vascular surgeons from Italy, Europe, the US, and beyond, in historic #Padua, was extraordinary.
The quality of the topics and discussions was truly stimulating.
The congress wrapped up fittingly on Saint Anthony of Padua’s Feast Day.
A beautiful ending to an inspiring few days where history, medicine, and community came together.
Ever looked at a carotid angiogram and thought:
“Which one’s the ICA, which one’s the ECA?”
Quick rule of thumb:
ECA -> early branches in the neck-> looks like a tree.
ICA -> no branches until it’s inside the skull
#MedEd#Radiology
If the clot persists or TIAs continue, CEA is the treatment of choice; not observation.
Hold heparin for 4–6 hours, then proceed urgently.
🧠 You’re not watching the clock, you’re racing it.
#VascularSurgery#StrokeCare#FOAMed
A 70yo man presents to ER with 3 TIAs in 12 hours. Duplex US shows a snake-like clot flapping in the carotid bulb. CTA shows no brain bleed.
That’s a crescendo TIA with a free-floating thrombus (FFT).
🚨 1 in 5 will stroke within 48h. #MedTwitter#NeuroTwitter
🧠 Playbook:
– Start IV heparin + DAPT + high-intensity statin.
– No thrombolytics (you’ll just spray the clot into the MCA)
– BP 120–140
– Repeat CTA in 24h → if clot remains, stenosis ≥50%, or persistant TIAs-> OR
#Stroke#NeuroTwitter
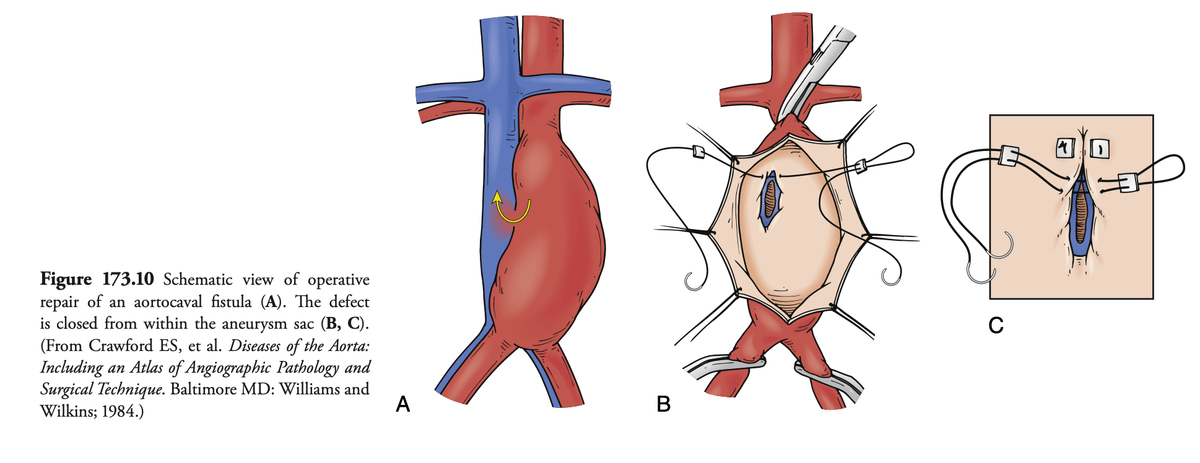
📸 From Rutherford: Pledgeted sutures for robust closure of the fistula.
The aortic & IVC walls are often fused: take both in transaortic bites.
🧭 If feasible:
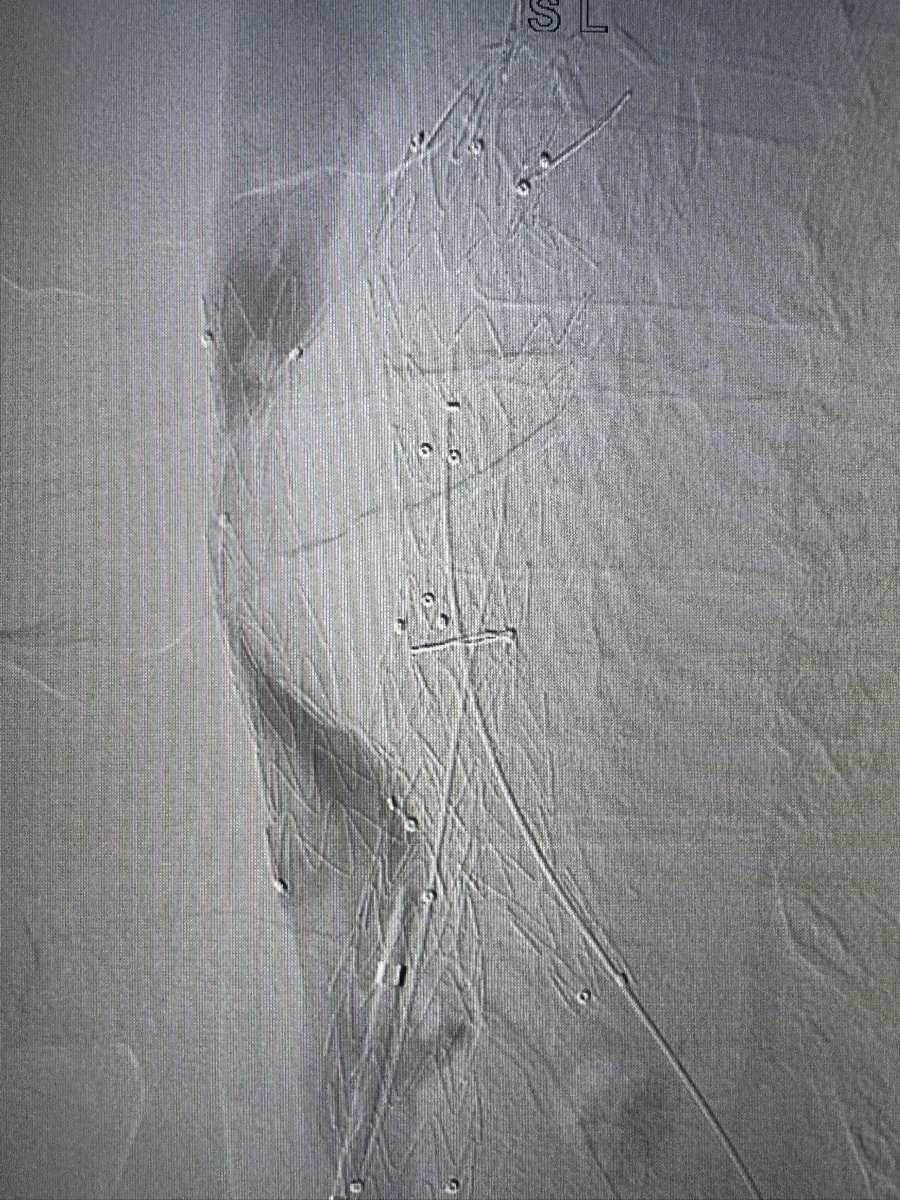
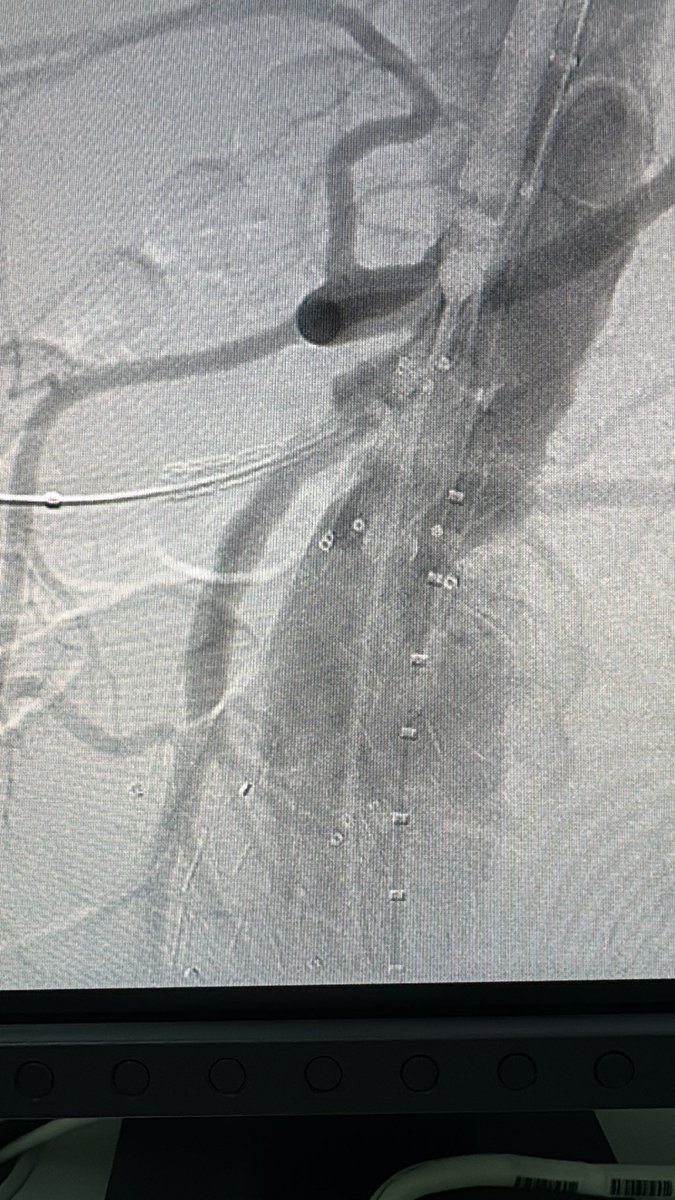
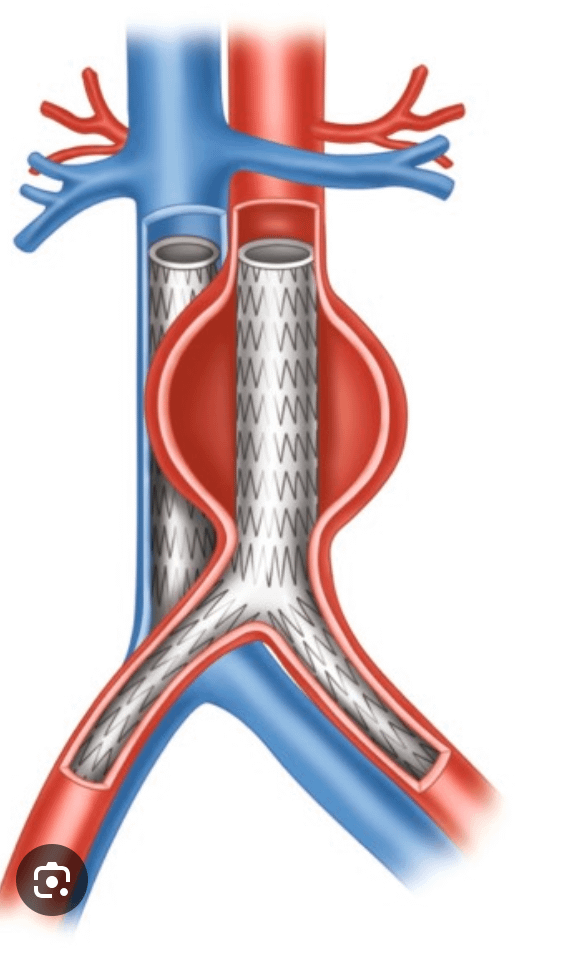
#EndoFirst → EVAR ± covered IVC stent (fearing IVC thrombus).
📍Monitor closely for endoleaks.
#VascSurg#MedEd#AAA
🚨 Clinical Vignette:
Patient with known AAA. Presents hypotensive with flank pain. Rushed to OR for open repair. Aorta & iliacs clamped. On opening the sac—massive gush of blackish blood.
What’s the diagnosis? What’s your next step?
#VascularSurgery.#SurgicalEducation
🛠️ Management pearls:
1️⃣ Apply immediate digital pressure or packing on bleeding source within the sac.
2️⃣ Identify the fistula (likely posterior aortic wall to IVC).
3️⃣ Prioritize Fistula/IVC control: it’s usually more life-threatening than lumbar retrograde bleed.
4️⃣ Perform transaortic repair: suture IVC defect from within sac using non-absorbable sutures.
5️⃣ Once stable, oversew lumbar arteries and proceed with graft placement.
Teamwork, suction, and rapid decision-making are key.
#OpenSurgery #SurgicalEducation #VascSurg