Okay ladies (and gents) with time on their hands: here’s a concrete way to help. Make masks! Some fabric kits at Treadle in St. Paul, otherwise can buy 100% cotton tightly woven fabric and flannel. Put those home ec and crafty skills to use - there’s no better time.
In the US, because of the opaque and unfair ways in which the system says no, health care deepens our political divisions, as the system’s current winners fear that reform could make them tomorrow’s losers.
And that makes reform harder.
This is the irony of comparing health politics in the UK and the US.
In part because of the public and fair ways the UK says no, its health system has generated a form of social solidarity that cuts across political lines.
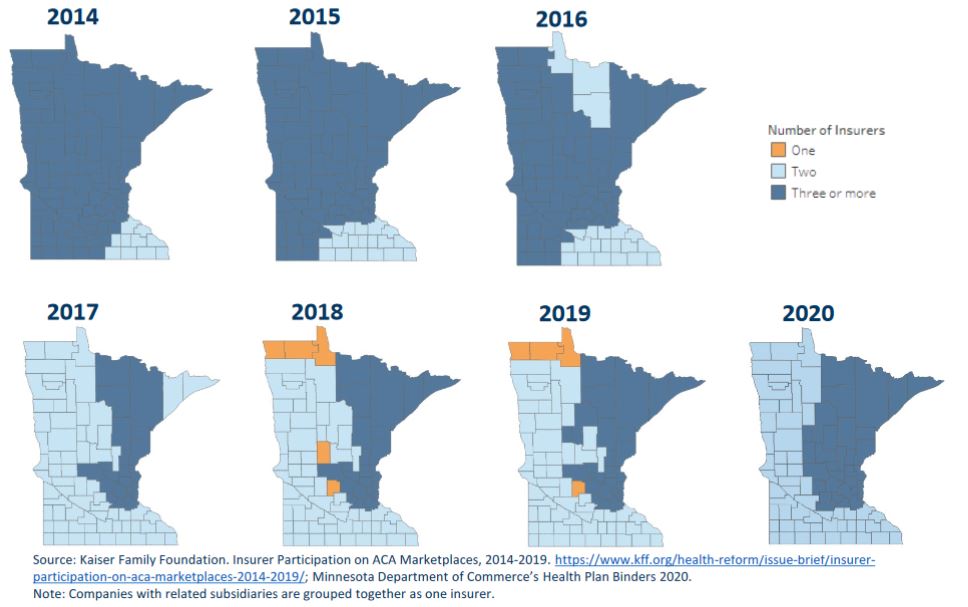
While you are considering the last few open enrollment days through @Mnsure, remember that Minnesotans are seeing more options for insurers & plans in the individual insurance market. We @mnhealth just put out a "data short take" to help assess trends. https://t.co/hGbSqmcxKV
Come work for us! @alisha_mnhealth, who leads HEP's policy research team, is looking for a mid-level analyst. Support what we know about MN's #healthcare market by looking at hospital, surgical center, & diagnostic imaging providers + more https://t.co/HC0mpIyLS8 @mnhealth
Busy day for the #MNAPCD: @mink_pam is presenting on the nearly complete MN Atlas of Children's Health Use at #NAHDO2019, a women's-only panel. I got to talk about our episode grouping work .
Stay tuned, as we bring this work across the finish line.
"The researchers said the biggest reason for the scheduling differences by race was not because of factors like education or which jobs workers chose, but because managers gave worse shifts to employees who weren’t white." https://t.co/ZbjnA0XIJ0
Want an exciting, fast-moving, intellectually stimulating job dvlping & tracking policies on HMOs/CBPs, coverage, network adequacy, surprise billing & consumer protection? Come work at @mnhealth! Job in Health Policy/Managed Care Systems, open thru 10/18: https://t.co/kV1hvhgTsT
Leaving the MN AG Advisory Task Force on Lowering Pharmaceutical Drug Prices, this message rose to the surface several times during public discussion w/r/t patents and market exclusivity
I came across a study on Twitter that made the claim that a pharma patient support program reduces healthcare costs. I like lower healthcare costs so I click through. Instead of coming across intriguing research, I found the worst of industry sponsored propaganda. 1/12
Pelosi senior adviser Wendell Primus says during a @BrookingsInst event a drug pricing package is coming in September
He added that Dems were almost ready to roll out the package but decided to wait til after August to prep new members for PhRMA's opposition and get a CBO score
Important, timely work from the @mnhealth Health Economics Program. When we talk about the state we want to live in, we must think broadly about access to high quality, affordable, respectful, pt-centered, culturally appropriate care, & how it intersects w/poverty & race/racism.
"Location, location, location" isn't just about real estate. It's also about health & access to care. And if we don't also talk about the impact of structural racism & unequal distribution of social determinants of health, we won't improve. GREAT work from @mnhealth researchers.
High-pvrty areas w/high rates of racial/ethnic diversity had 2x the rate of high-pvrty areas & nearly 3x the rate of state;
Avrg age of premature death: 50, 54, 57;
Add'l econ cost to these communities: $114.8M;
Where you live & what lives you experience matters to health
2/2
Seen our @mnhealth's new work on health care amenable mortality in #MN and the interaction w/concentration in poverty & racial/ethnic mortality? https://t.co/LEbVQGRlmT https://t.co/MoFgradEpX
1/2