I fully agree with this take. Let me add that I feel really sorry @ImmunityBio decided to share this trial outcome on the same day they released ungrown QoQ revs. This is a comm weakness that needs to be fixed. Asap. @DrPatrick@bullishbruk
$IBRX In plain English, \bm{p = .0455} means there is a 95.45% chance that the result was real, and a 4.55% chance it was a total fluke or random luck.
Here is how to break down what that specific number means.
Gold Standard Threshold (\bm{p < .05}): In clinical trials, the FDA and medical scientists set the standard cutoff for "statistical significance" at \bm{p = .05} (a 5% chance of luck). Anything below \bm{.05} is officially considered a proven success rather than a coincidence.
Because \bm{.0455} is smaller than \bm{.05}, it means the combination of ANKTIVA + BCG was officially proven to be superior to BCG alone in keeping patients disease-free at 9 months, satisfying the FDA's strict requirement for statistical significance.
The Clinical Meaning: It proves that adding ANKTIVA doesn't just give patients a temporary initial bump—it keeps the cancer away significantly longer compared to standard treatment, giving the drug a strong, scientifically backed case for label expansion.
Progress in research happens one study at a time.
We're committed to transparency in our clinical development programs. Stay informed about where our investigational candidates stand.
Check our latest pipeline updates: https://t.co/jzMALyOFKN
Journal of Urology publication of our updated 100 patients with long-term data in BCG unresponsive non muscle invasive bladder cancer. Responses extending beyond 53 months! 84% cystectomy free survival at 36 months.
NK cells matters. Chemotherapy reduces lymphocytes.
Next, BCG naive in non muscle invasive bladder cancer.
https://t.co/CbJqYFrANL
We are pleased to announce that the U.S. Food and Drug Administration (@FDA) has expanded the indication for ANKTIVA® (nogapendekin alfa inbakicept‑pmln) + BCG to include patients with BCG‑unresponsive non‑muscle‑invasive bladder cancer (NMIBC) with papillary‑only tumors.
This milestone makes ANKTIVA + BCG the first FDA‑approved therapy for both CIS and papillary‑only disease in the BCG‑unresponsive NMIBC setting. Because papillary tumors represent approximately 85 % of NMIBC diagnoses, this approval significantly broadens access to a bladder‑sparing option for patients who face high risk of recurrence and progression.
Read more: https://t.co/prIgphlGKf
Thanks to FDA for approving the platform that stimulates NK and Killer T cells. Memory T cells and durable responses is the next evolution of immunotherapy.
Thank you to @FDADrugs for making ANKTIVA accessible to all patients in non muscle invasive bladder cancer who failed BCG therapy. @ImmunityBio - The first treatment approved for this group of patients.
An important step for cancer immunotherapy 2.0.
FDA is transforming rare disease drug approvals. The new Rare Disease Framework Initiative will work to give patients more voice, give developers more clarity, and eliminate surprises in the regulatory process. https://t.co/dN9mby7MPN
$IBRX Congratulations to the @FDA and @FDA_KyleD on expanding the approval of ANKTIVA for BCG-unresponsive, high-grade papillary-only NMIBC — the first FDA-approved option for these patients who previously had no alternatives. Credit where credit is due. Thank you for prioritizing patients. @DrPatrick@LoriMills4CA42@MichaelRCaputo
Big news for bladder cancer patients! FDA just expanded approval of Anktiva with BCG for adults with BCG-unresponsive, high-grade papillary-only NMIBC — the first treatment approved for this group. This is a first, and that matters. Evidence from a closely related form of bladder cancer supported the approval.
https://t.co/azWUTpNxjm
Billionaire cancer doctor Patrick Soon-Shiong told Tucker Carlson that almost every oncologist ignores the one number in your blood test that kills cancer:
“Pick up the phone, call any random oncologist, not to shame them, and say, ‘You do a CBC, correct?’ A complete blood count. You take blood and check whether you’re anemic or not.”
“And you give chemotherapy and radiation, and you ask, ‘What do you look for?’ Well, we look to see if you’re anemic, so we can give you this drug Amgen makes called Epogen. We look to see whether your platelets have gone down, so we can give you a platelet transfusion. We look to see whether your neutrophils have gone down so you don’t get an infection, so we give you Neupogen.”
“Well, the problem is, do red blood cells kill cancer? No. Do platelets kill cancer? No. Do neutrophils kill cancer? No.”
“What kills cancer? The natural killer cells and T cells. So in that CBC, there’s a thing called the lymphocytes. Do you look at that? No.”
“The only cell that is important, that kills cancer, and 99.9% of oncologists will say, ‘We don’t pay any attention to that.’”
Even Tucker couldn’t believe it: “Why, if you’re fighting cancer, would you ignore the one cell that fights cancer?”
“That’s the missing link. That is the key element in your body.”
PS. We post daily breakdowns on health and longevity, so if that’s you, follow us @LxngevityLab for more.
Like and repost if you found value in this post:
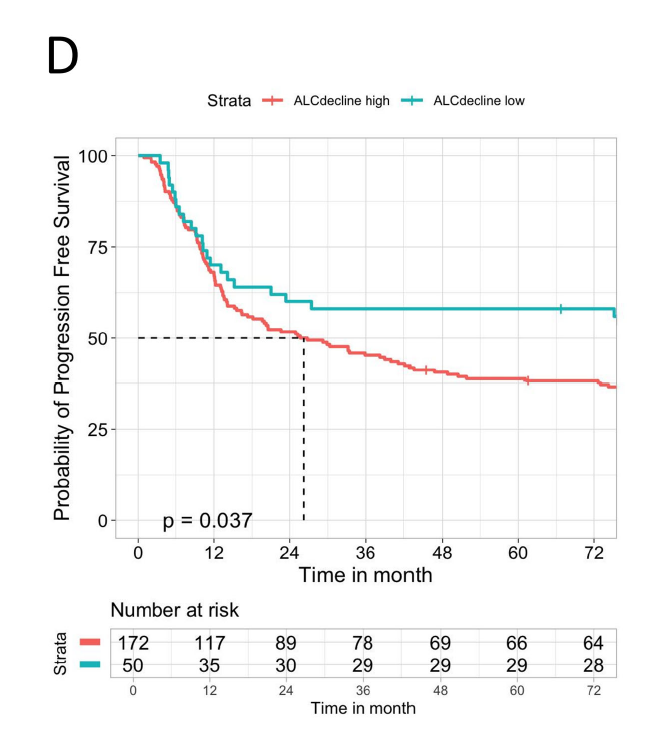
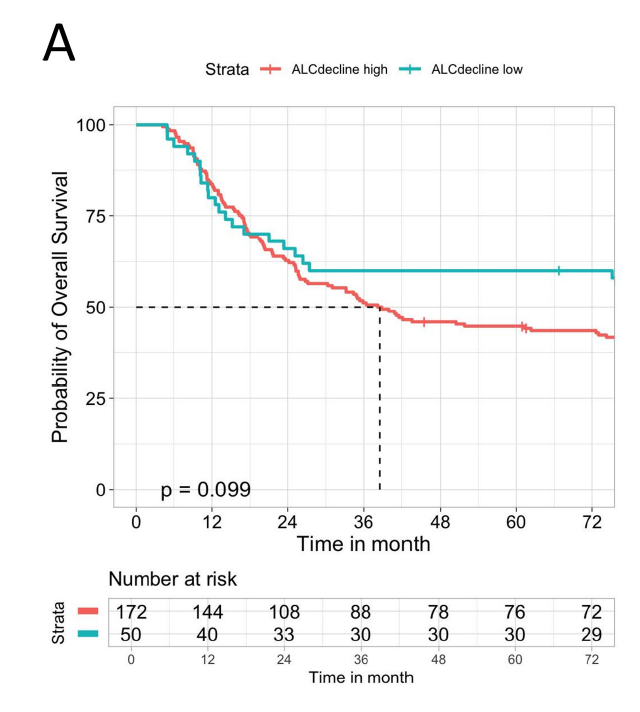
Lymphocytes matter. ALC count matters. Yet another paper in 2026 showing that when ALC levels fall from radiation, recurrence of cancer occurs. This progression free survival of ALC high vs ALC low is self explanatory. NK cells and T cells protect
https://t.co/4lAVD8UM65
Best of wishes Michael and Congratulations .
There are millions of patients with cancer worldwide who are in complete remission. The next frontier is to develop therapies strengthening the immune system to prevent recurrence in these over 15 million patients in the USA alone, and drive long term durable freedom from cancer to win the war. Incremental short term duration of response should no longer be an acceptable outcome.
The therapies to address and maintain cancer free status are now here……..the orchestration of the immune system, the identification of tumor DNA in the peripheral blood, the easy measurement of the NK and T cell levels in the peripheral blood count, the sophistication of next gen PET/ MRI/ CT scans, the ability to grow and store activated NK cells, the ability to identify tumor educated T cells, the new knowledge of camelid derived heavy chain single domain antibodies and the ability to precisely target radioactive ligands, to precisely target CART and CarNK and CAR-iNKT cells. These immunotherapy advances are all here today and in various stages of clinical trials. The oncology community will enter this next generation of paradigm change. The need to establish these diagnostic and therapeutic combinations as IMMUNOTHERAPY 2.0 is both urgent and exhilarating.
This was the subject of my one hour talk with NIH and NCI and the decade of collaboration with Jeffrey Schlom and James Gulley to develop a cancer vaccine. Hope to release the talk once I receive the video recording and obtain clearance to make it public. We are closer than ever.