Algunas fotos del programa de prehabilitación de trasplante hepático del @incmnszmx
Preparando a los pacientes para el trasplante 💪🏼💪🏼 Anestesio perioperatoria, Nutrición, Fisioterapia y Medicina del deporte
Feliz con este equipazo 🫶🏻 @kary_vaznar2@PereaOrnelas@E1Miranda
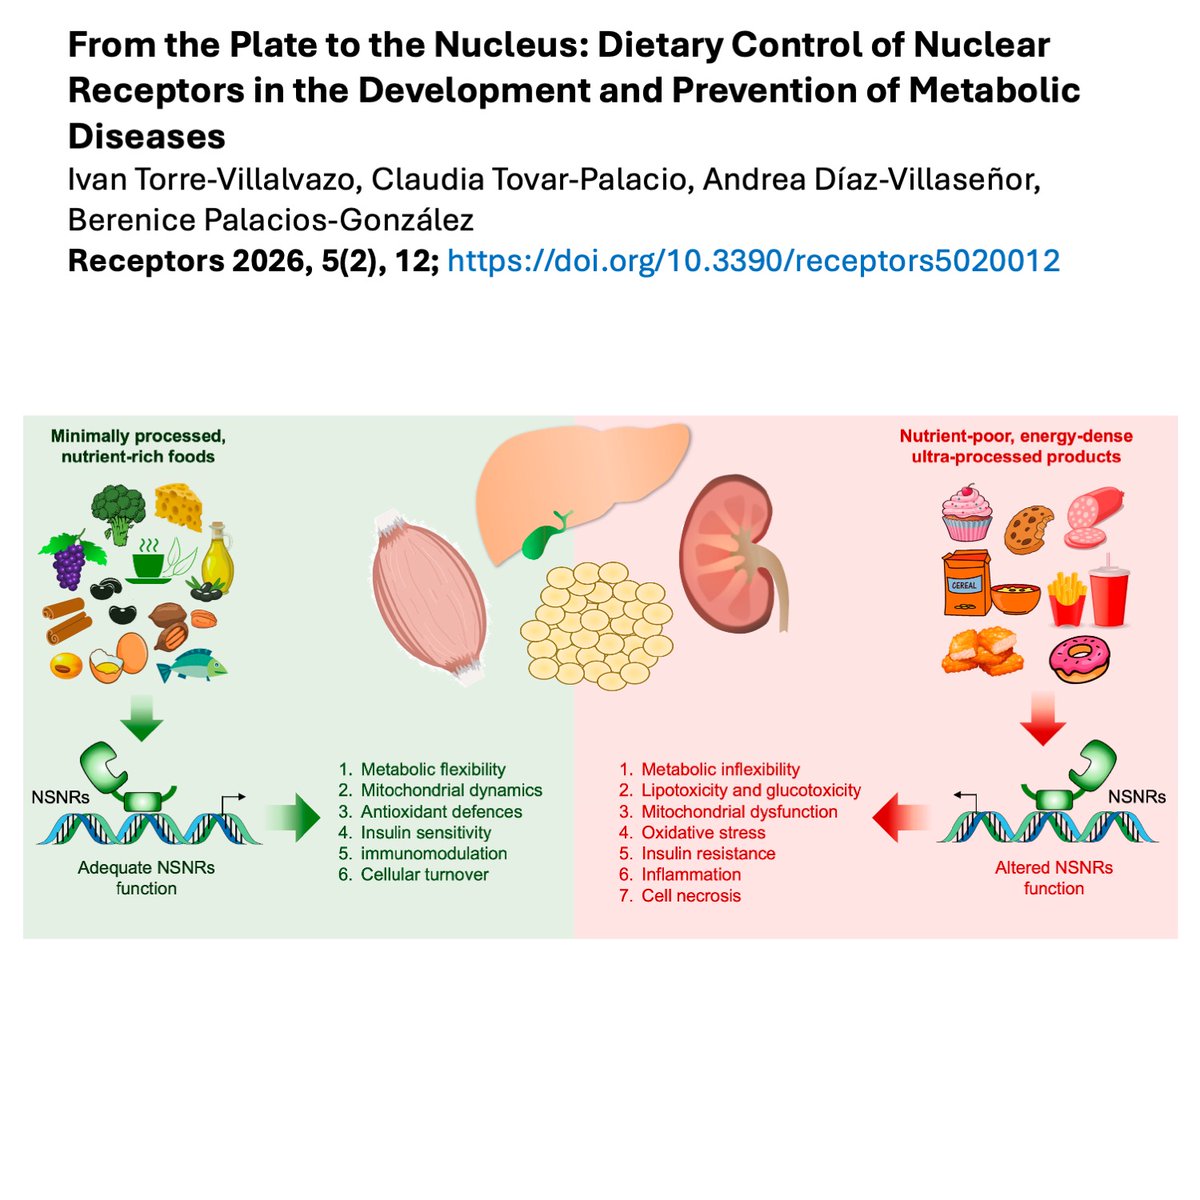
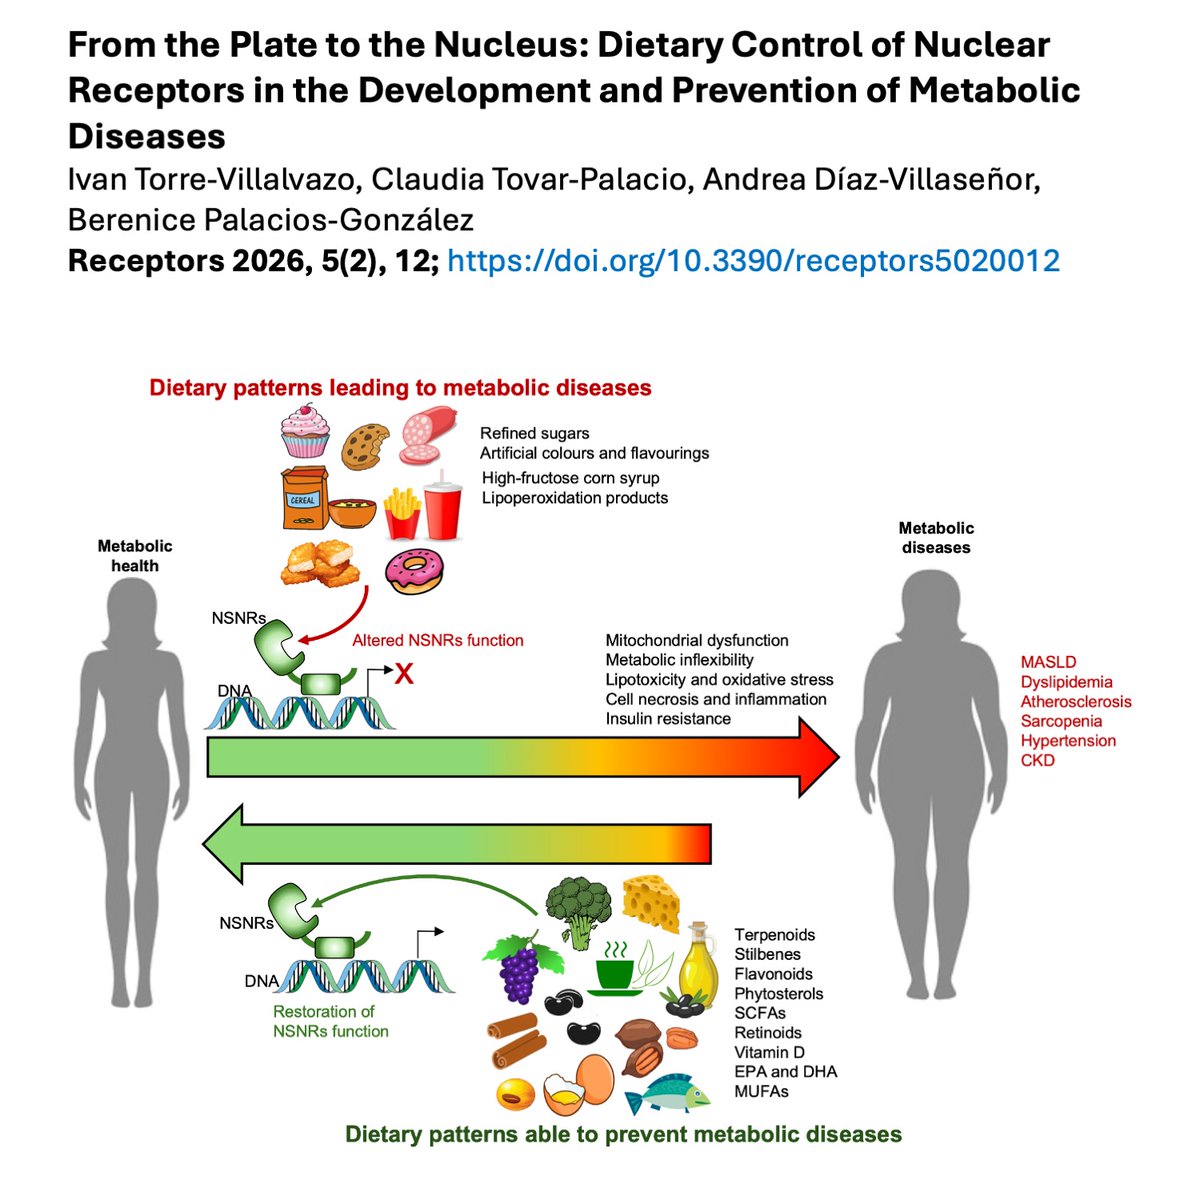
Los alimentos modulan el metabolismo de cada uno de nuestros órganos al activar receptores nucleares que actúan como sensores de la calidad de los alimentos. Buena comida=buena salud, mala comida.....
¿Buscas hacer tu residencia médica e iniciar en marzo de 2027?
Ya está abierta la convocatoria del INCMNSZ para el registro y participación en el proceso de selección.
Consulta las bases aquí:
https://t.co/KOPb94JOnR
¡Compártela con quien esté por dar este gran paso!
🗣️
@CCINSHAE_mx@SSalud_DGCES@FacMedicinaUNAM@SSalud_mx
#ResidenciasMédicas #INCMNSZ #ENARM #EducaciónMédica
Compartimos nuestra convocatoria para el REGISTRO Y PARTICIPACIÓN EN EL PROCESO DE SELECCIÓN DE PERSONAS INTERESADAS EN CURSAR ALGUNA RESIDENCIA MÉDICA PARA INICIAR EN MARZO 2027.
🗣️ ¡Pasen la voz!
https://t.co/KOPb94Kmdp
@CCINSHAE_mx@SSalud_DGCES@FacMedicinaUNAM@SSalud_mx
NT-proBNP
🧠 Core physiology
NT-proBNP is released from LV myocardium due to:
• Increased wall stress from volume or pressure overload
• Hypoxia and ischemia
• Neurohormonal activation like Angiotensin II and Endothelin
👉 It reflects hemodynamic stress, not just heart failure
⚙️ Biochemical pathway
Pre-proBNP (134 AA) → proBNP (108 AA) → cleaved into:
• BNP (32 AA) → biologically active, causes natriuresis and vasodilation
• NT-proBNP (76 AA) → inactive but clinically measurable
👉 NT-proBNP is more useful because of stability
⏱️ Kinetics and clearance
• BNP half-life ~20 minutes
• NT-proBNP half-life 90–120 minutes
• BNP cleared by receptors and enzymes
• NT-proBNP cleared exclusively by kidneys
👉 NT-proBNP reflects sustained cardiac stress over ~12 hours
📊 BNP vs NT-proBNP clinical relevance
• BNP affected by neprilysin inhibition
• NT-proBNP unaffected
• BNP less stable in vitro
• NT-proBNP highly stable
👉 In modern practice, NT-proBNP is preferred
🚨 Acute dyspnea: Rule OUT HF
NT-proBNP < 300 pg/mL
• Negative predictive value ~99%
• Effectively excludes acute decompensated HF
👉 Shift focus to pulmonary or systemic causes
2: Rule IN HF using age-adjusted cutoffs
“45-90-18 rule”
• Age <50 → >450 pg/mL
• Age 50–75 → >900 pg/mL
• Age >75 → >1800 pg/mL
👉 Aging myocardium and declining GFR increase baseline levels
🏥 Chronic outpatient setting
NT-proBNP < 125 pg/mL
• Rules out chronic HF in stable patients with mild symptoms
⚠️ Critical concept
NT-proBNP is NOT HF specific
👉 It is a marker of myocardial strain
👉 Always interpret with clinical context, echo, volume status
🚩 Causes of falsely elevated NT-proBNP
Think CARSS
• CKD → reduced renal clearance
• Age → baseline elevation
• Rhythm → AF and tachyarrhythmias
• Sepsis → cytokine-mediated myocardial depression
• Strain → RV strain like PE, PAH
Also seen in:
• Acute coronary syndrome
• Critical illness
👉 Elevated value ≠ always LV failure
📉 Causes of falsely low NT-proBNP
• Obesity → increased peptide clearance
• Flash pulmonary edema → delay in release 2–4 hours
• HFpEF → less wall stretch compared to dilated ventricles
• Constrictive pericarditis or tamponade → restricted stretch
• Severe mitral stenosis → LV underfilled
👉 Normal value does not completely exclude HF
💡 High-yield bedside pearl
Obesity halving rule
• Reduce diagnostic cutoffs by ~50%
• Example: 450 becomes ~225
👉 Prevents missing HF in obese patients
💊 ARNI paradigm shift
Sacubitril inhibits neprilysin
→ BNP breakdown blocked → falsely elevated BNP
👉 BNP becomes unreliable
✅ NT-proBNP must be used for diagnosis and monitoring
💊 Sacubitril/Valsartan dosing
• Starting dose: 24/26 mg or 49/51 mg PO BD
• Target dose: 97/103 mg PO BD
⚠️ Absolute rule
• 36-hour washout after ACE inhibitor
Monitoring
• Hypotension most common
• Hyperkalemia risk
• Creatinine rise up to 30% acceptable
📉 Prognostic and discharge utility
Track admission to discharge change
👉 Target ≥30% reduction
If not achieved
• Persistent subclinical congestion
• High 30-day readmission and mortality
👉 Action
• Continue IV diuresis
• Plan early follow-up within 72 hours
👉 Always correlate with clinical exam, echo, IVC, response to diuretics
🔚 Final takeaways
• <300 pg/mL rules OUT acute HF
• Always apply age-adjusted rule-IN
• Interpret in clinical context, not isolation
• Use NT-proBNP in ARNI patients
• Aim ≥30% reduction before discharge
This is not just a lab value.
It is a dynamic tool for diagnosis, monitoring, and prognosis
❤️ Like + Repost
👉 Follow @DrNikhilMD for more
Todo listo!!
📢No se pierdan el 2do Congreso de Mayo Clinic & INCMNSZ
Los esperamos en el @incmnszmx o en la modalidad virtual!
Programa y registro en: https://t.co/FKrIeirjDO
@Merayo_Dr@NayelliCointa@Abraham_RMI
No es la especialidad. Es la maquinaria neuropsicológica de cada uno. Lo importante es conocerla, saber sus limitaciones y no avorazarse más allá de lo que puedas tolerar y necesitar. Hay mucha gente inteligente con psicopatología, te amortigua que te apasione tu especialidad.