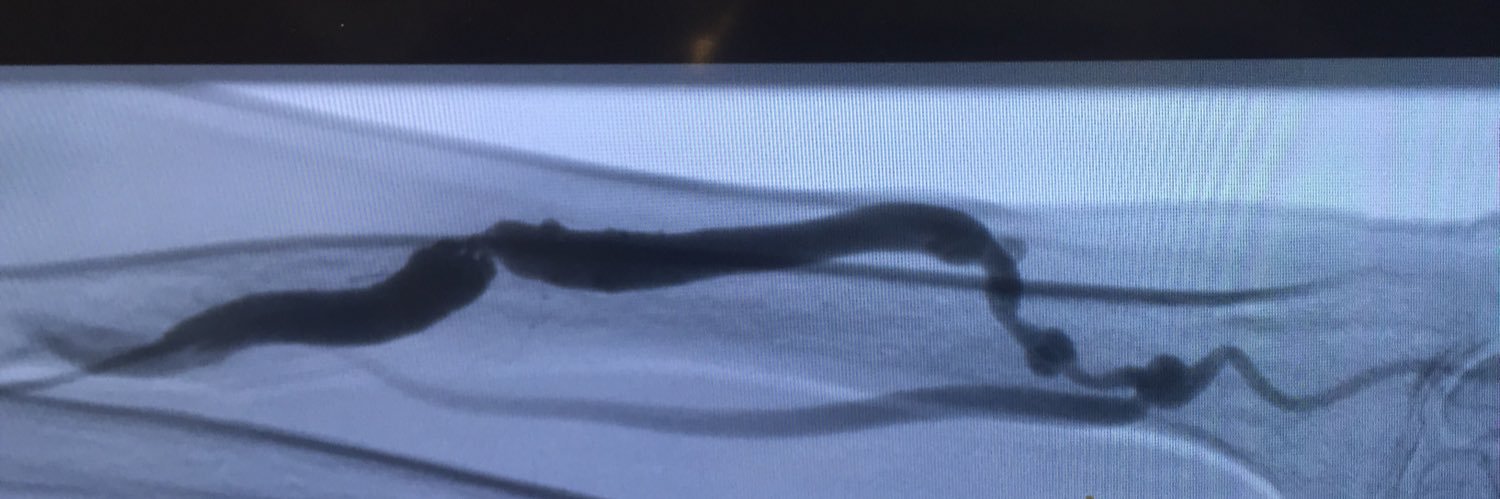
25 yo ESKD pt referred for eval for HD access after 9 yrs of PD & eventual sclerosing peritonitis. No previous AV access.
- broke L arm at age 13
- not on tx list, so you want to start distal
- you find a great cephalic vein
- you see these:
#orthotwitter@RenalFellowNtwk
Endo approach to the stuck tunneled dialysis CVC. No 🔪 needed.
• Amplatz safety guidewire through venous port & parked in IVC
• Guidewire through arterial port w/ serial PTA using 5 x 4 Sterling from first rib/clav to venotomy
• 🥁…..CVC out!
Favorite part of #kidneyweek: visiting posters and talking to trainees! Even better when bringing along a friend @NMawlaMD
Excellent poster and great discussion with med student Jasper Sim of @EinsteinMed! 🙌🏾🙌🏾 @ASNKidney
A big thanks to special guests Drs. Alejandro Alvarez and Robert Shahverdyan for making the 11th Chicago Dialysis Access Dinner Club meeting dynamic, interactive and educational!
Thanks to our sponsors for their support. 🙏🏾
📸 Cole Warner
Access surgeons:
This is a prox radial-cephalic AVF that was superficialized and now the AVF lies under/just adjacent to the incisional scar.
Please show me how you perform these to avoid this problem. 🤷🏽♀️
Pt with a 4 mo radial-cephalic AVF referred for difficult cannulation & “very small vein”.
AVF (in red) is 4mm. There’s a 4 mm competing collateral vein.
How do you manage it? 🪡🧰🛠️
Ligate? Coil? Plug?
Pt presents for difficult cannulation of his mature aneurysmal AVF.
This is in the cannulation segment. It’s 12 mm and there are two of them.
The prior US from 4 mo ago shows it, but now it’s bigger.
How do you treat it?
@ASDINNews Help me win an argument with IR. Our IR dept routinely uses a 2-3 hr TPA infusion for dysfxn tdc arguing it has better patency rate than fibrin sheath pta or stripping with an exchange. I strongly doubt this is true/trying to find true h2h studies. @NMawlaMD@wasse_m
ESRD HD pt with a brachial-cephalic AVF referred for decreased surveillance blood flow of 381 ml/min on Fresenius machine.
Pump speed 450 ml/min, normal Kt/V & arterial pressure is 220 w/15 g needle. No other stenotic lesions.
Proud to have co-chaired the #VEITH2023 dialysis access symposium w/Drs Scher and Sidawy, and even prouder to have kicked off the morning with this stellar panel of dialysis access experts!! 💃🏽
Dialysis access surgeons:
-Patient w/BMI of 43 is preparing for first AV access. Not on tx list.
- RIJ CVC x 1 year
- No veins for L forearm AVF
Do you create a:
- left forearm AVG
- left BC-AVF
- left prox-radial cephalic AVF
- left upper arm AVG
An ESRD patient is referred for a pulsatile proximal radial-cephalic AVF with high VP’s.
The patient has been going to an access center q3 months. You have no records.
On angio, you see this: