Out today in @JAMASurgery we provide updated benchmarks for the cost per minute of OR time and, for the first time, estimates of charges and revenues per minute as well:
https://t.co/dcc5WbJZdw
tl;dr -
cost per minute: $57
charges: $295
revenues: $66
@SyedAAhmad5 2 recent articles relevant:
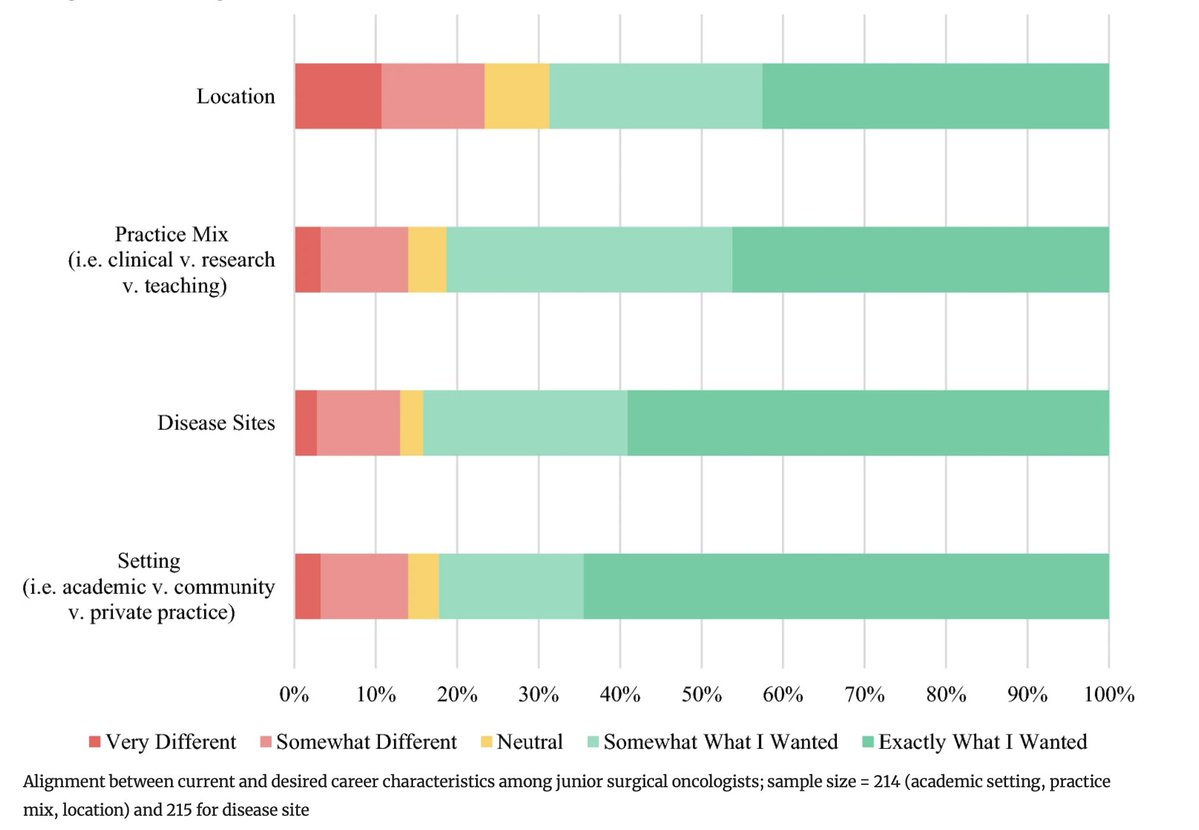
1. junior SSO faculty confirm most have clinical jobs, sig research time unlikely (https://t.co/txAeNyPiIx)
2. the opportunity cost of training is substantial... we estimated upwards of $13M for these prolonged pathways (https://t.co/8kloOOsfKu)
A new @TIME article highlights a JACS analysis of geographic disparity in surgeon supply across the US.
The study found that 38% of US counties have no general surgeon, affecting more than 15 million Americans.
Read the @TIME article at: https://t.co/aNgMGl06td
Find the JACS study at: https://t.co/1qb8gt0U4T
In @acsJACS, we looked at the evolution of the Medicare fee schedule 2018 - 2024
tl;dr: payment rates (wRVU/min) are now the same across specialties, and any differences in comp across specialty are unlikely to be materially impacted by the fee schedule https://t.co/FAoc78w9nl
A message from our President, @DrLolaFayanju of @queensu and @KingstonHSC: “Surgical Outcomes Club is my intellectual safe space.”
We couldn’t agree more.
Join us on September 26 in Washington, DC: https://t.co/VK6BT2AfB4
@jnahmias1@JAMASurgery Well...
CPI-U went up by ~ 24%, MEI by ~ 13%
And OR revenue went up by 37%
So... depends how you define "good" but costs are rising faster than any reasonable inflation measure and faster than revenue growth...
Open operation looks different in the minimally invasive era.
Among 105,085 operations, conversions accounted for nearly half of open appendectomies and cholecystectomies. Conversion was associated with 147% and 116% longer operative times and 7.07 and 7.60 times higher odds of complication, respectively, vs minimally invasive surgery.
Read the full study by @cchildersmd and colleagues at: https://t.co/f7YHtQymlp
In Part 2, we show hypocrisy in the @CMSGov mod 25 policy. They think only procedures get more efficient when they overlap, what about the rest of the fee schedule? https://t.co/799CNMUEJK
@AmCollSurgeons@DonJSelzer@Thomasctsai
@rbarbosa91@GloriousPCMD@EricKnauerMD Why?
We asked for an obesity modifier from CPT and were told no, in part because they said modifier 22 already existed. It wouldn't apply to bariatric operations, but for any operation where there's a spectrum of patients...
https://t.co/C66My85Nof