@ASCOGU. Re: renaming GG1. imo, real pattern 3 is cancer for reasons stated. BUT, perhaps (a middle ground?) we can educate pathologists to stop overdiagnosing cancer when there’s only 1-2 parts with <1mm GG1 in the absence of def infiltration. These should really be ASAPs…
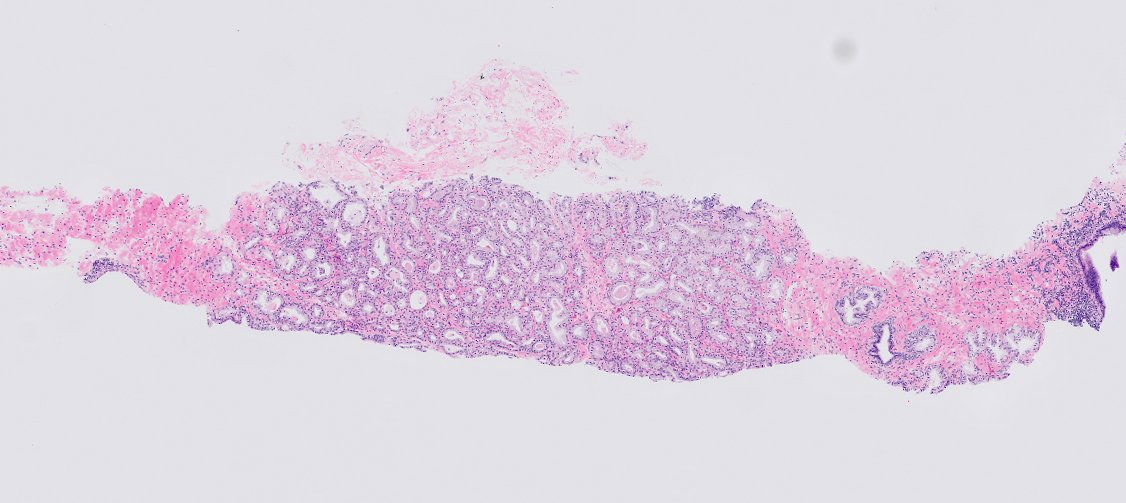
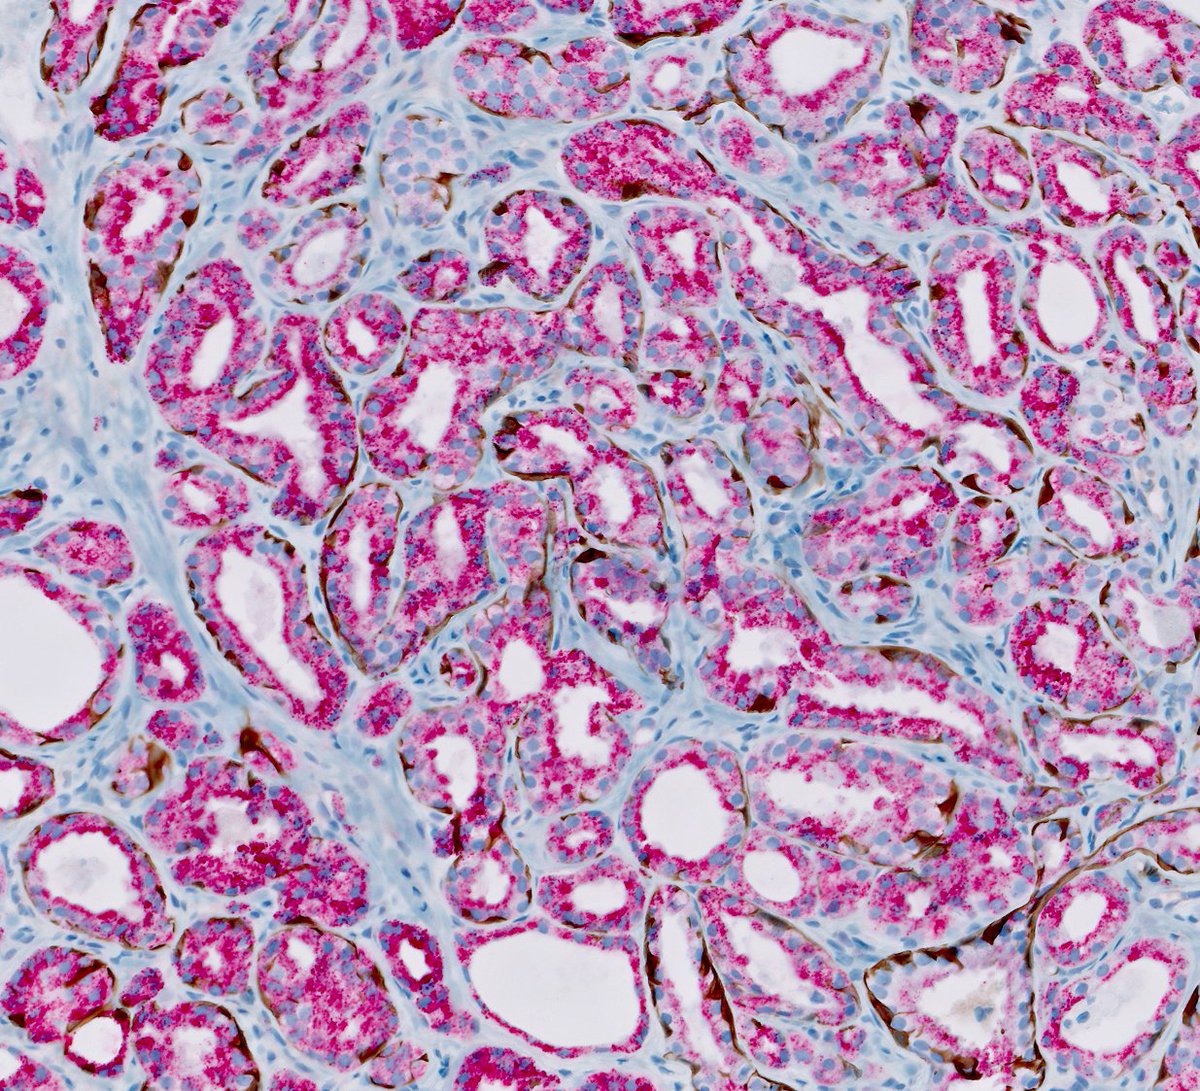
In a complete 360 from yesterday's case... I thought for sure this was benign (or small focus of ASAP/3+3), BUT it all stains like cancer. 😱 I even told the lab they forgot my basal cell stains but there's some internal +control. aren't those corpora?? #realitycheck#gupath
Almost reflexively called this 3+3 (there was high-grade PCa in every other part of this case). We don't often see adenosis on bx (more often seen in transition zone/TURP), but clues here are: no significant cytologic atypia and basal cells appreciated at higher power #gupath
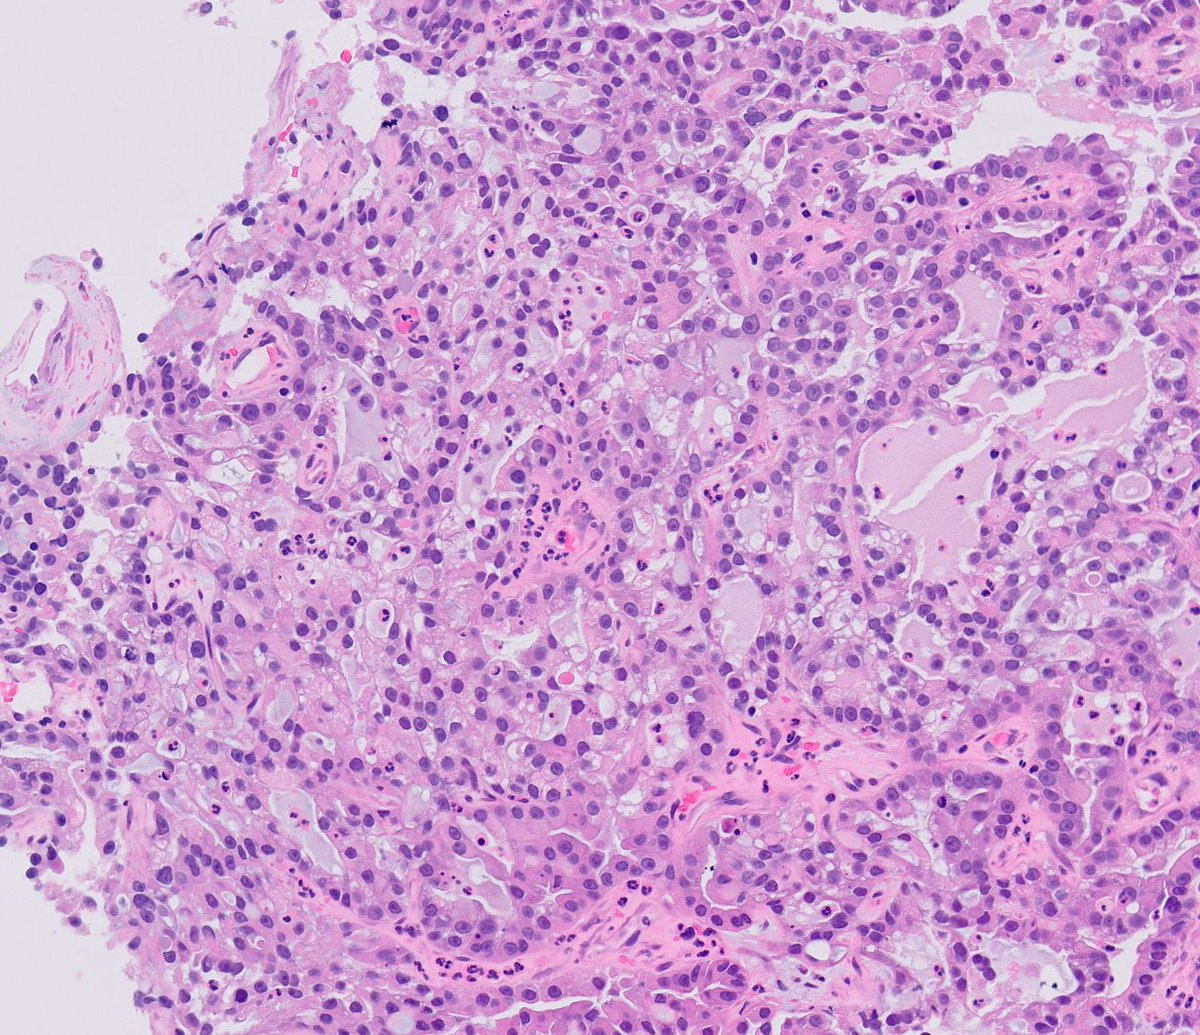
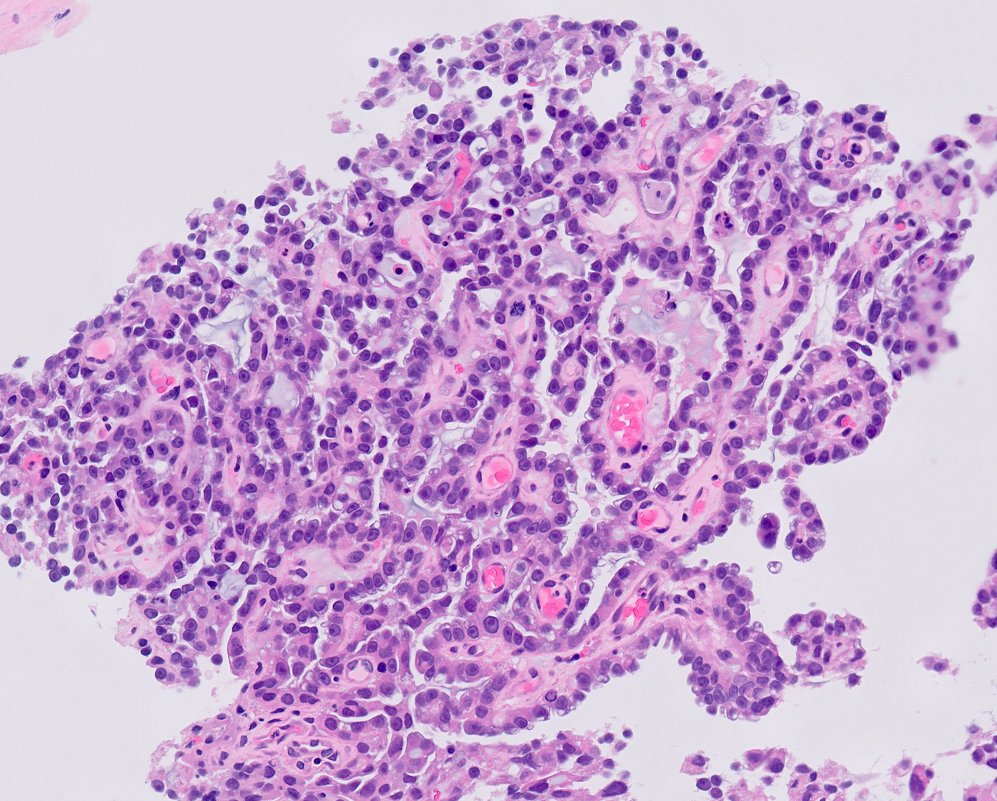
beautiful clear cell adenocarcinoma of the urinary tract (male patient)! essentially equivalent to CCC in gyn world. may mimic nephrogenic adenoma by morphology and IHC but solid areas, cytologic atypia, mites and necrosis are clues. #gupath
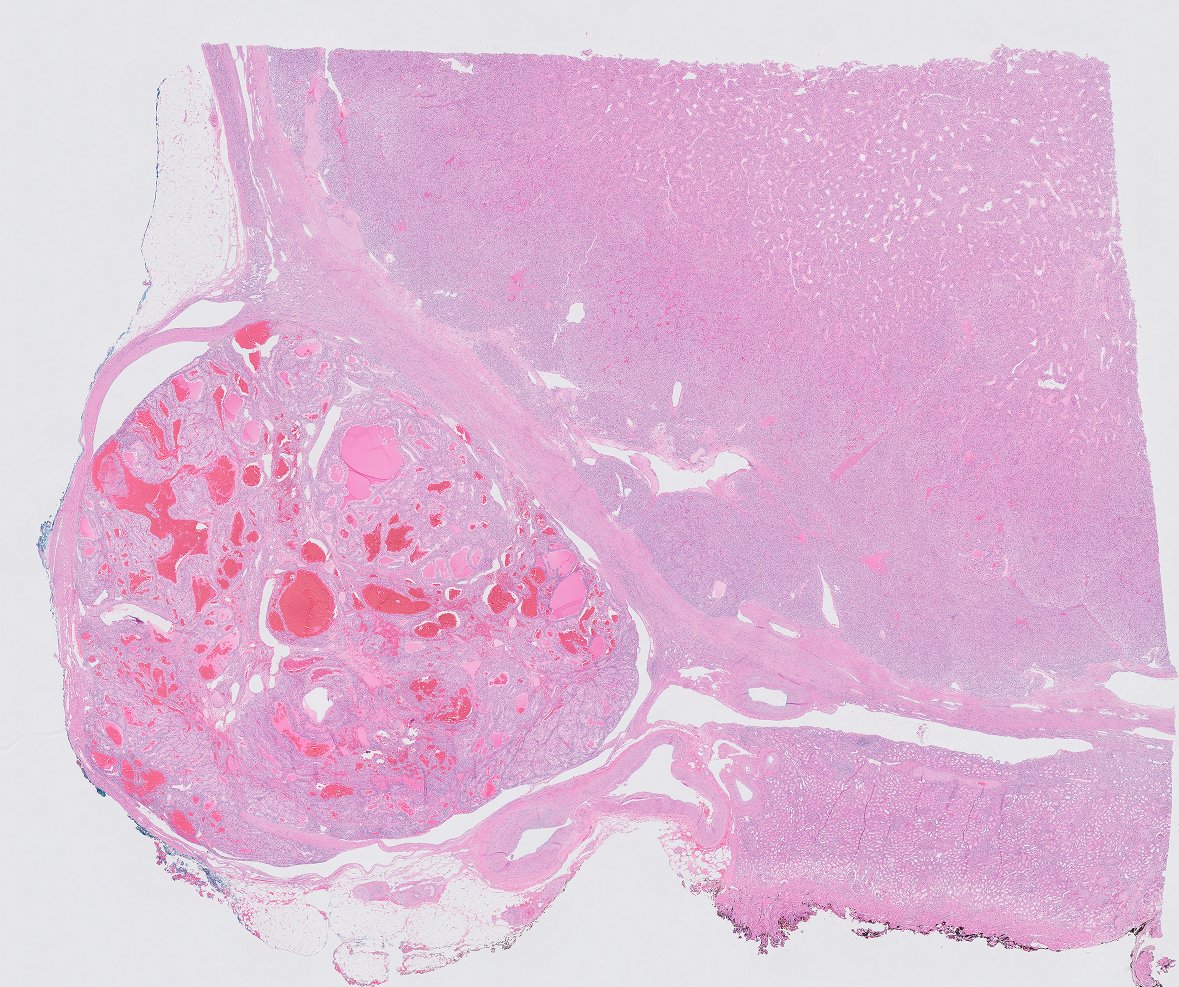
Remember to look for vein invasion in your partial nephrectomies! What was thought to be a multinodular tumor (left) clearly showed tumor in a major (segmental) vein on b2b (right). Likely call-able w/o b2b but wanted to teach trainee to look for vessel margins on gross #gupath
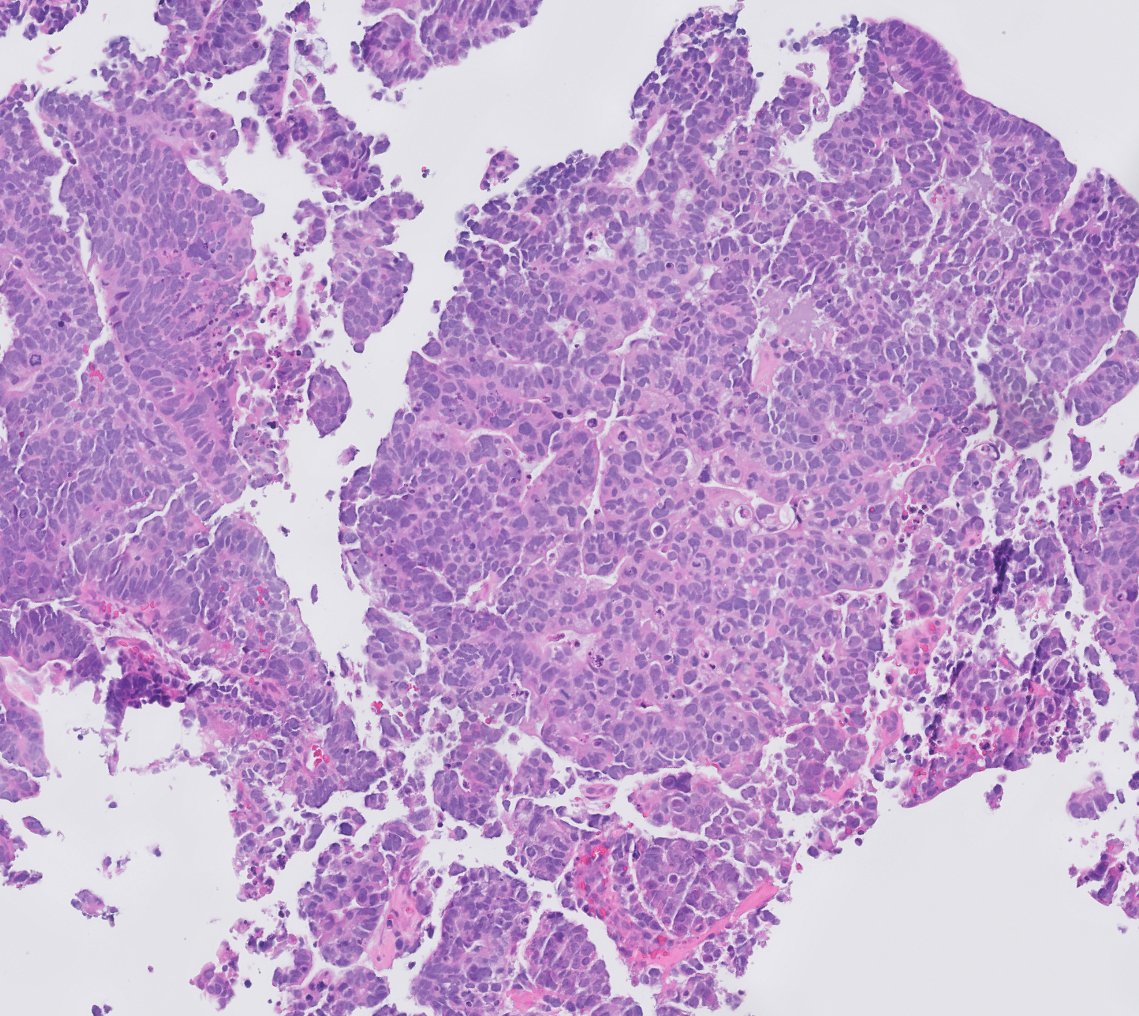
Final impressions: enteric looking yes! but important NOT to topline adenocarcinoma as this could be urothelial ca with glandular diff. primary adeno of bladder will get GI-type chemos vs UCa chemo for UCa. This tumor had TERTp, TP53 and KMT2D alterations, supporting UCa
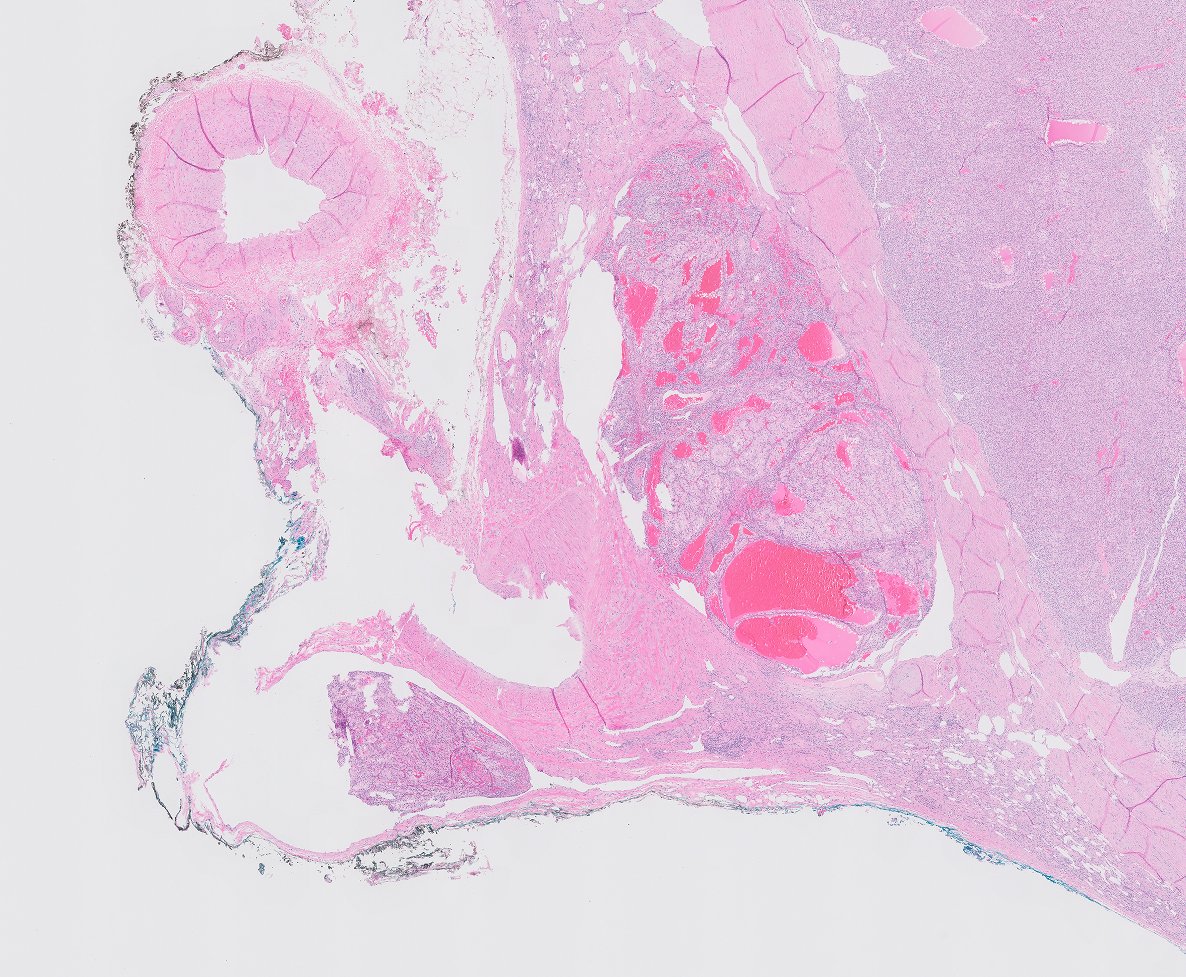
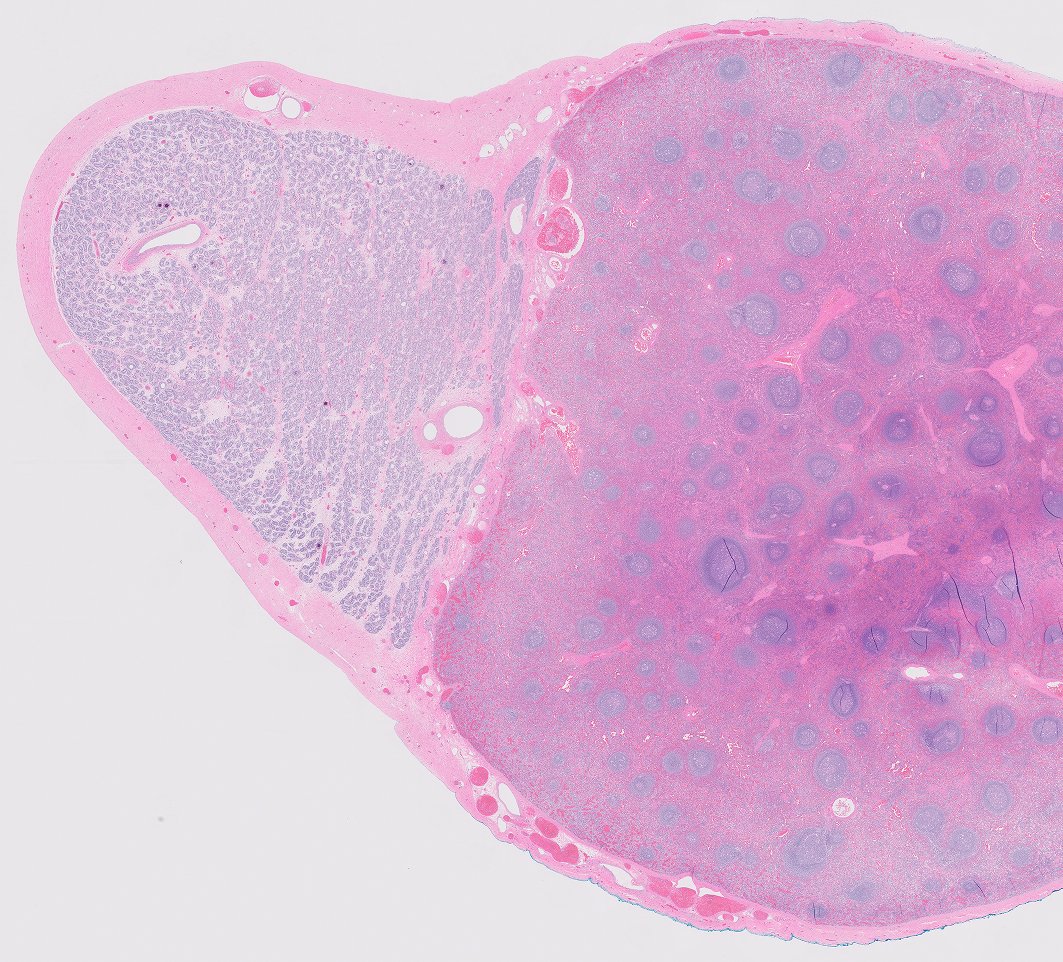
almost forgot to update.. it's a rare case of splenogonadal fusion. cut surfaces may have been more helpful but I thought a giveaway; AND our surgeon actually recognized this as spleen intraoperatively which I found quite impressive! but then again, we have great surgeons! :D
@rovingatuscap We do neuroendocrine markers/ki-67/AR if asked or if certain features present (sometimes for research protocol, sometimes just because of the way tumor is behaving in patient). We do pten if debating between IDC/AIP/HGPIN in otherwise low-intermediate grade case.