Evaluation and Treatment of Iron Deficiency for the Practicing Oncologist | JCO Oncology Practice https://t.co/OlPqUor0xf @JCOOP_ASCO@ASCO@OncoAlert one of the most common consults in General HemOnc Clinics
This is the treatment algorithm we have used to drive our 🗣️ with @lungoncdoc on targeted options in 1L for metastatic NSCLC!
✅ Zongertinib recently added
✅ Data around front line when you have multiple options
✅ Role of Re-testing
#lcsm#OncTwitter@OncoAlert@OncUpdates
Algorithm for Systemic Therapy in Early HR+/HER2- Breast Cancer
(Recommendations in gray areas reflect my own clinical judgment— eg. olaparib and CDK4/6 sequence)
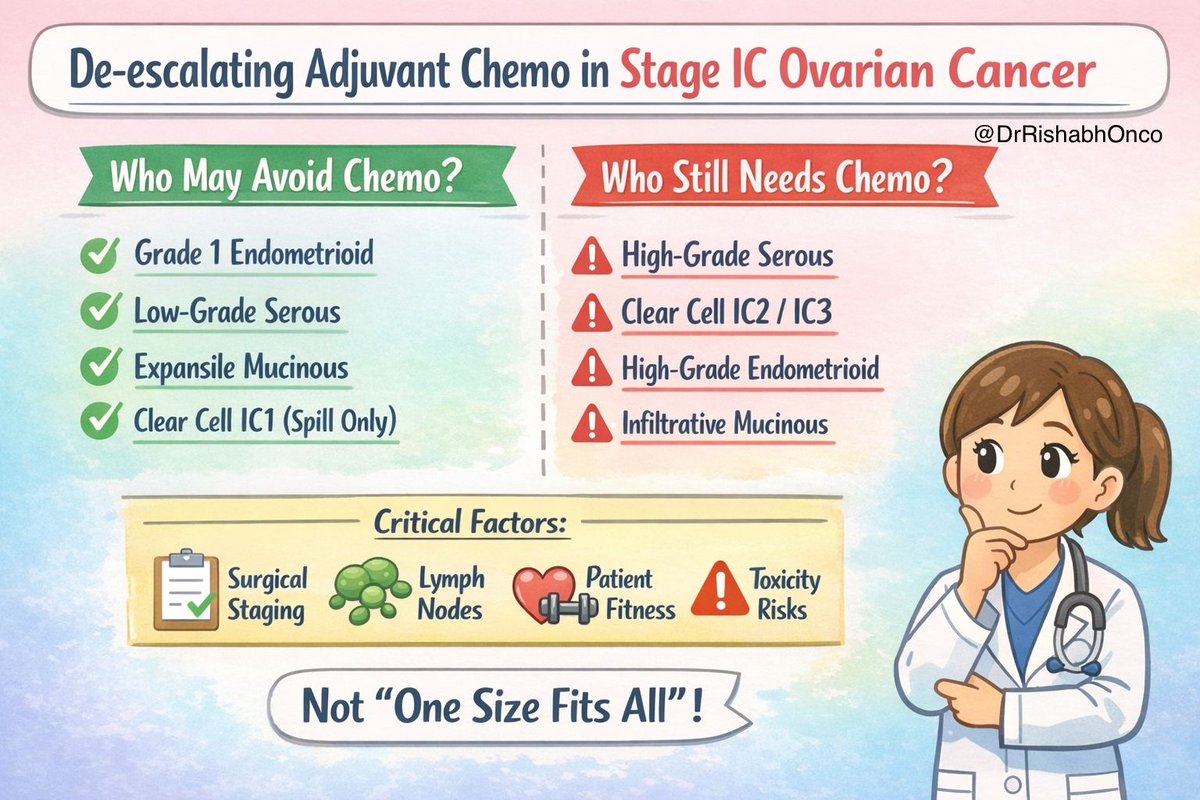
Not all stage IC ovarian cancers need chemo.
This IJGC review supports selective de-escalation 👇 
🟢 Consider NO chemo
Low-grade serous
Grade 1 endometrioid
Expansile mucinous
Clear cell IC1
🔴 Chemo still needed
High-grade serous
Clear cell IC2/3
High-grade endometrioid
Infiltrative mucinous
🧠 Takeaway
Stage IC ≠ one disease
👉 Treat by histology + staging, not habit
🔖 Save this
📖 Full paper in comment ⬇️
#OncoTwitter #MedTwitter #GynOnc #OvarianCancer
@OncoAlert@myesmo@esmo_open@asco
🧬 Can we skip Oncotype DX… and still decide chemotherapy?
A Lancet Oncology AI study tackles this head-on in HR+ / HER2− early breast cancer by predicting recurrence score directly from H&E slides + clinicopath data.
Study backbone:
•🧪 Training/validation: TAILORx (n=8284)
•🌍 External validation: 6 cohorts (n=5497) 
Performance 📊
•🎯 High genomic risk (RS ≥26): AUC 0.898
•Risk split (TAILORx test):
•🟢 Low: 45.6%
•🟡 Intermediate: 42.4%
•🔴 High: 12.0% 
Where it gets clinically interesting 👇
👩🦰 Premenopausal
•🔴 AI high-risk → chemo benefit (HR 0.63)
👩 Postmenopausal
•🟢 AI low-risk → no chemo benefit (HR 0.94)
•⚠️ 31.3% clinically high-risk → reclassified as low AI risk (no chemo signal)
Why this matters 💡
•Bridges digital pathology → treatment decisions
•Potentially reduces dependence on costly genomic assays
•Especially relevant for resource-limited settings
But ⚠️
•Retrospective model
•Needs prospective validation before practice change
👉 Pathology slides might soon guide chemo decisions. Are we ready?
📖 Full paper in comment ⬇️
#OncoTwitter #MedTwitter #BreastCancer #AIinOncology
@oncoalert
NORTHSTAR: Who really benefits from LCT?
Not everyone with EGFR NSCLC.
✔ No thoracic LN
✔ No pleural effusion
✔ Curative RT feasible
👉 It’s not oligometastasis… it’s oligobiology
#ELCC2026#ESMO#MVOnco#LungCancer
NorthStar trial 🌟
Osimertinib + LCT vs osimertinib alone
PFS: 25.4 vs 17.0 mo
HR 0.60 (p=0.02)
Not just oligometastatic—benefit seen even beyond
👉 Target residual disease, delay resistance
#MVOnco#Oncology#LungCancer#EGFR
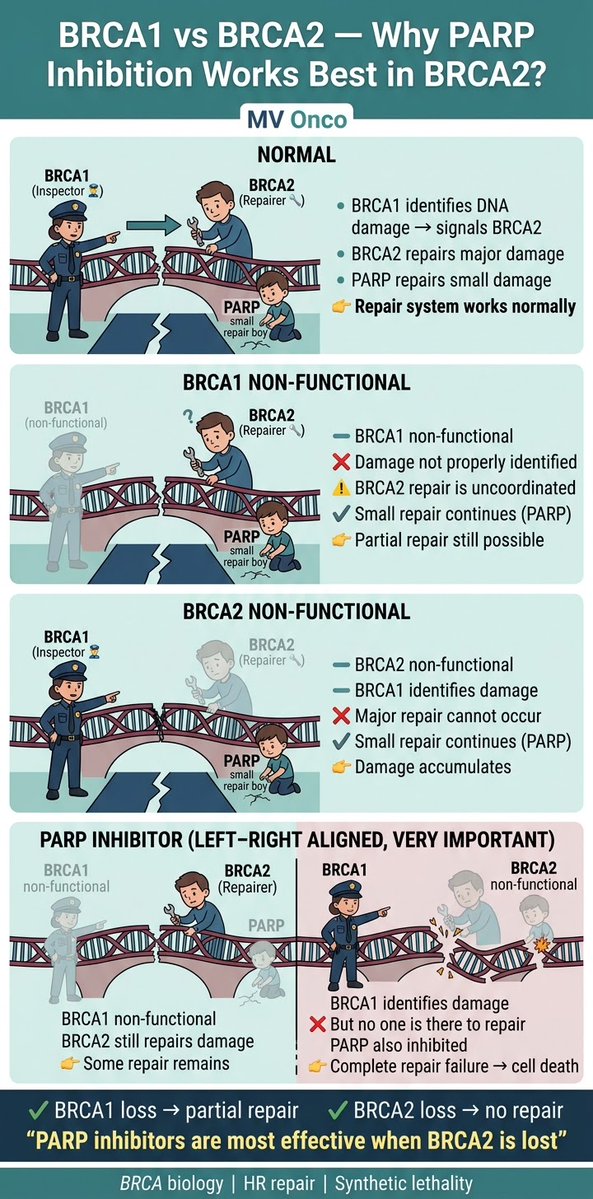
If you remember only one thing from BRCA biology, remember this👇
• BRCA1 → detects DNA damage
• BRCA2 → repairs DNA
• PARP → fixes small damage
Block PARP + lose BRCA2 → no repair left → cell dies
👉 That’s why PARP works best in BRCA2
#MVOnco#Oncology#MedOnc
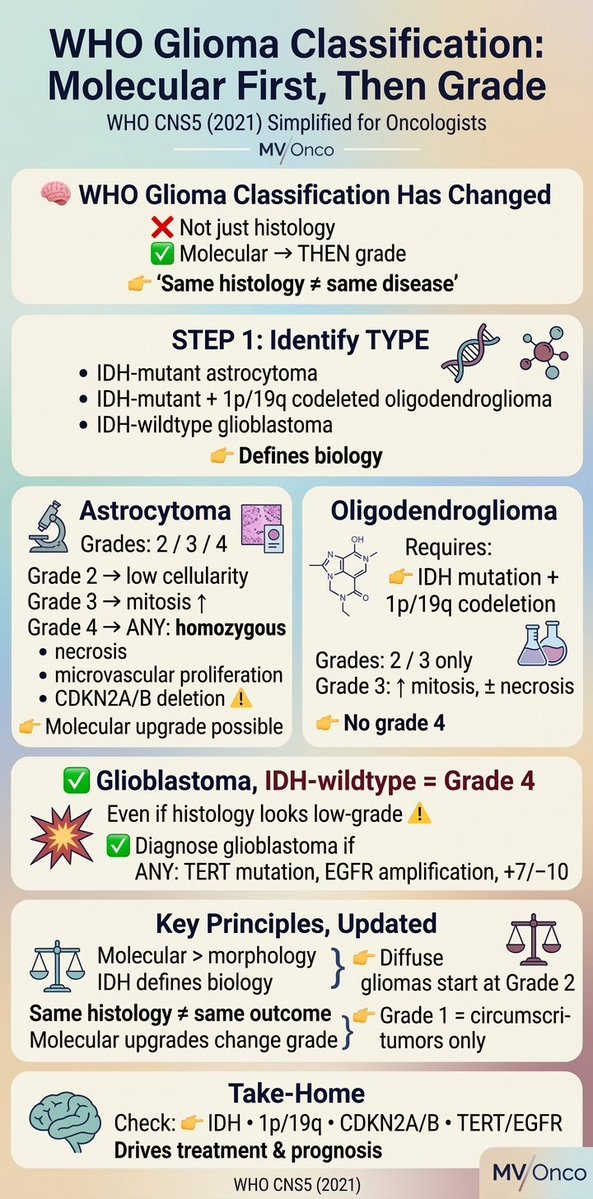
INDIGO Trial 👇
• PFS: 27.7 vs 11.1 mo
• Delays RT/chemo (TTNI NR vs 17.8)
• Seizures ↓
• QoL preserved
👉 Best in early mIDH grade 2 glioma
👉 Hit IDH early or miss the window
#MVOnco#Glioma#NeuroOncology#Oncology
Adjuvant therapy in resected NSCLC — who benefits?
• Stage IA → No chemotherapy
• Stage IB → Consider if high-risk
• Stage II–IIIA → Standard
Cisplatin doublets improve OS (~5%).
Modern era: targeted therapy & immunotherapy.
#MVOnco#LungCancer#Oncology#MedOnc
Rectal cancer treatment is moving toward DE-ESCALATION.
• dMMR → Immunotherapy first
• Upper/Mid rectum → Radiation may be omitted
• Lower rectum → Organ preservation (OPRA watch-and-wait)
Biology + anatomy now guide therapy.
#MVOnco#RectalCancer#Oncology