Dr. Ken Anderson (center) woke up at 3 am to catch a 5 am flight to attend Dr. Kyle’s memorial service yesterday. It was Ken’s 75th birthday yesterday, and we didn’t know about it till later. That’s the level of respect he had for Bob. He chose to spend the day honoring him.
We grabbed a pic together. Also in the pic are @szusmani who flew in from New York to be at the service, and @myelomaMD and @MyelomaDrKapoor
The myeloma field is special in how we work together. This is not by chance. It started with Bob Kyle and how he interacted with his peers and mentees and how they in turn did to their peers and mentees and so on.
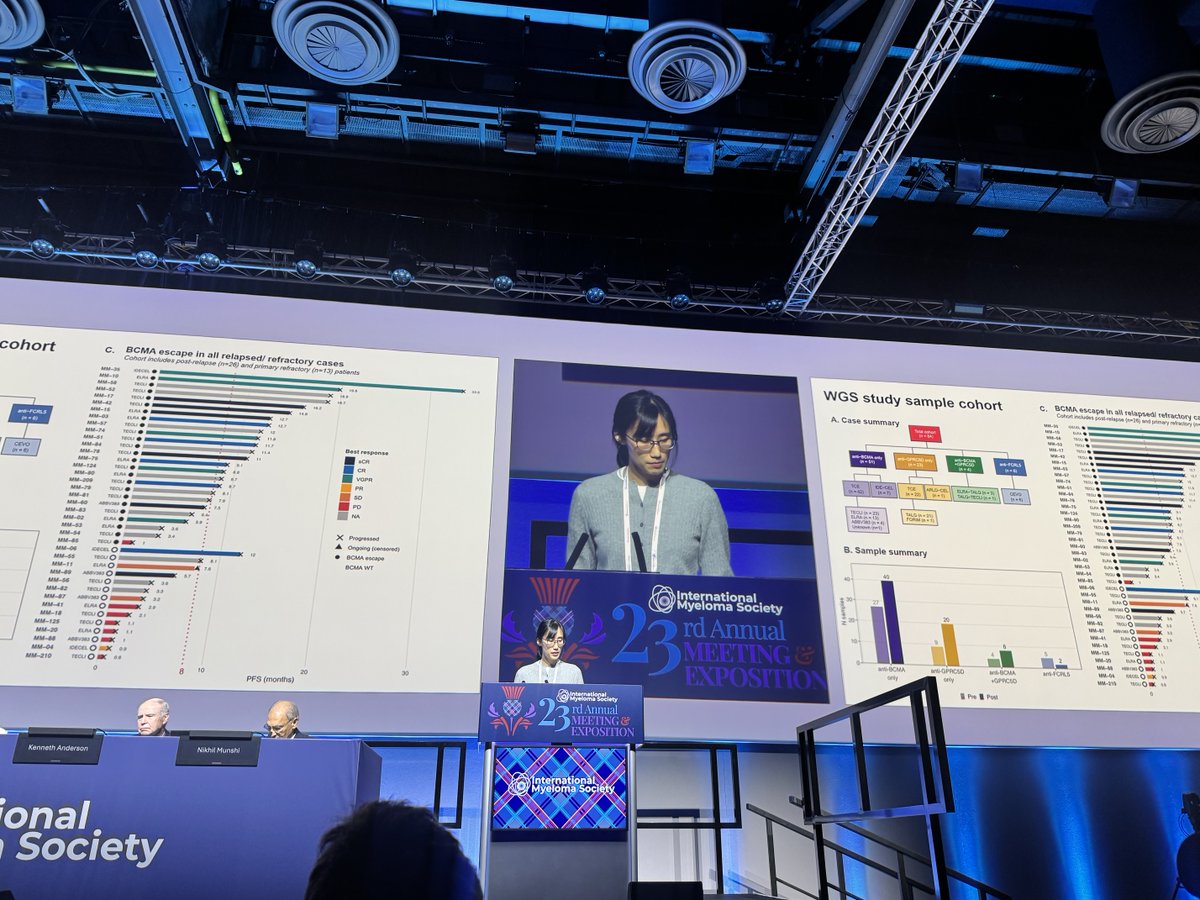
Dr Holly Lee @hollyleeYJ presenting at #IMS23 updated data and novel mechanisms on TNFRSF17 mutations and resistance to anti-BCMA redirecting therapies
If you are in Glasgow #IMS26 stopby 12-1 pm poster- Mezigdomide post ide-cel in RRMM. We demonstrate in likited number that mezigdomide is safe as time limited maintenance for 1 yr at 0.6 mg.
https://t.co/6fsIu606BO
Three things I recommend for using Bispecific antibodies in myeloma:
1) Prophylactic tocilizumab with first dose
2) Monthly IVIG regardless of the IgG level
3) Consider reducing frequency/stopping after excellent response.
This applies to all the approved bispecifics: teclistamab, elranatamab, linvoseltamab, and talquetamab.
Academic centers with expertise and close monitoring capabilities may skip the prophylactic tocilizumab but in general I do not see community adoption without it.
The data on routine IVIG and early use before the IgG levels drop or infections occur is good and sufficient to move forward. It’s recommended in NCCN and mSMART. Bispecifics are better at controlling myeloma than standard triplets and quads, but pose a much higher risk of serious life threatening infections without prophylaxis and careful adjustment of dosing schedule based on response and patient characteristics.
#IMS26
Best myeloma study I've ever put patients on 🤩
⭐️ Commercial lead-in allowed
⭐️ MRD neg: ASCT deferral vs not
⭐️ MRD pos: tec-dara (à la TEC-4) vs standard dara-len
⭐️ Sustained MRD-neg? Stop all treatment!
Thanks @End_myeloma for leading us all - looking forward to results!
We are a mighty myeloma group! What an incredible day, thank you to the over 400 ppl who came out, 120K plus in donations for myeloma research in Canada, thank you for supporting and believing in research @HamHealthSci@McMasterU@HamiltonMyeloma@MyelomaCanada
Rituximab Maintenance Added to Ibrutinib-Containing Therapy in Patients With Mantle Cell Lymphoma: Update from TRIANGLE Trial | @JCO_ASCO
https://t.co/TNU2Itlypm
This weekend, we bid farewell to Hartmut Goldschmidt, who will retire from his academic positions at the end of the month. To celebrate 35 years of @HDMyeloma, 30 years of #GMMG, a large crowd joined us for a dedicated symposium with long-standing partners and friends. #mmsm
Excited to see the ImmunoPRISM trial published with Omar Nadeem and @IrenemGhobrial!
Teclistamab induced deep responses in high-risk smoldering multiple myeloma.
Next: understanding these responses in depth through ongoing translational studies.
https://t.co/1N9RdGoPSu
Very happy to be back to Houston for SOHO 2026 and privileged to join tomorrow at noon Drs Raje and Orlowski at a Research To Practice Satellite Symposium on Optimal Management of RR multiple myeloma
Infection burden among patients with triple-class–exposed RRMM receiving non–T-cell–redirecting therapies: a US claims study @BloodCancerJnl#mmsm@utswcancer
✅More than 60% of heavily pretreated patients with triple class exposed RRMM experience infections, with nearly half experiencing severe infections that require hospitalization or emergency care
✅ 63.5% of patients experienced any infection:
➡️58.2% bacterial infections (most common)
➡️27.4% viral infections
➡️8.2% fungal infections
✅Infections are common in RRMM patients even in patients who don’t receive BCMA based therapies, important to do proactive infection prophylaxis, antimicrobial prevention strategies, and supportive care in this vulnerable population, regardless of treatment type used.
➡️ https://t.co/ZhPnXzQxxx
Drs. Tarek H. Mouhieddine and Kenneth C. Anderson summarize treatment for multiple myeloma, highlighting four-drug induction therapy, evolving transplantation strategies, tailored maintenance therapy, and in relapse, earlier use of BCMA-directed immunotherapy.
Read the Review Article “Treatment Decisions in Multiple Myeloma”: https://t.co/rtFssp5gYf
And at #IMFIMWG26, Mr. New York takes on ���Hotel California”…
And not just crushes it, he knocks it to MRD neg at 10^-8 in 30 seconds 👏
Bravo @JoshuaRichterMD for 🎸 performance of the year!
Kudos to @MyMKaiser et al!
HR myeloma is a marathon, not a sprint. With extended MUKnine course, median PFS will be over SIX YEARS (!) in ultra-HR MM without BsAbs or CAR-T 👏
But evidently, GEP will need to be the way of the future. Not all ultra-HR MM is created equal…