A high fiber diet outperforms metformin, without the iatrogenics, of course.
This is somewhat statistically OK, so could be big, very big, because it must necessarily directionally apply to GLP-1 --though the latter has a stronger effect than metformin.
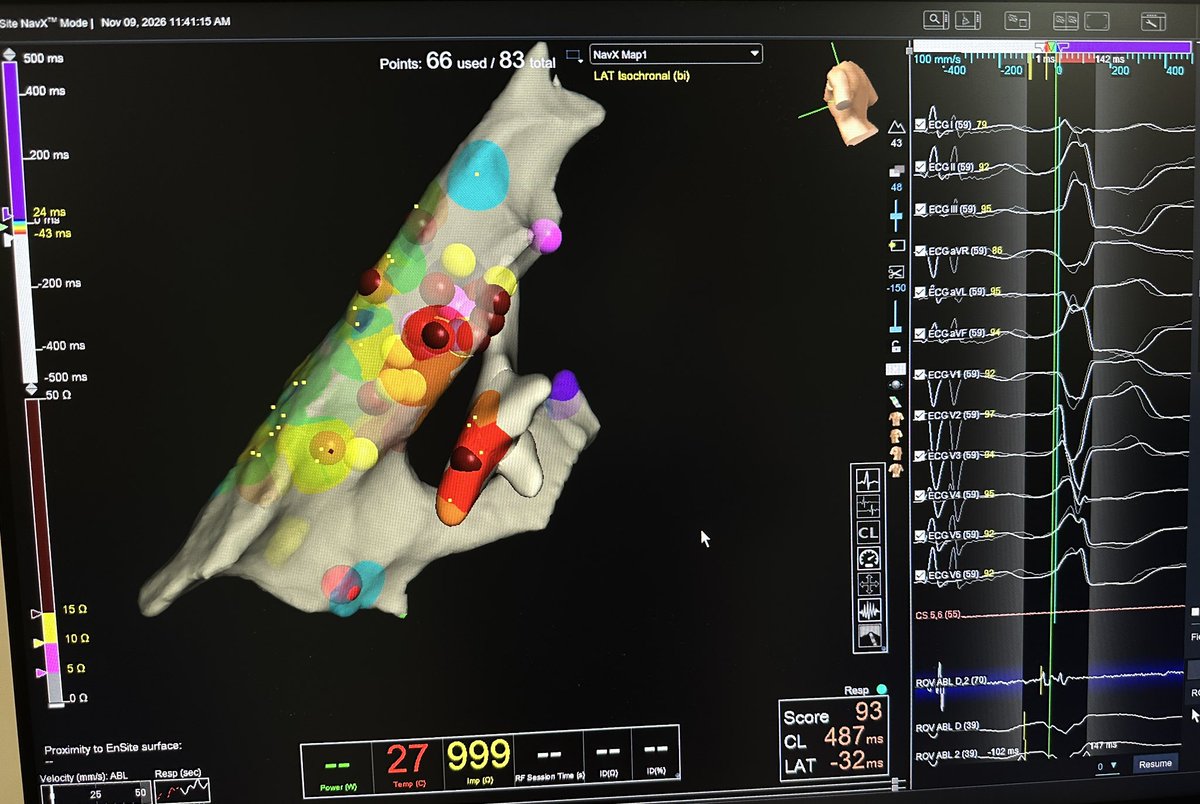
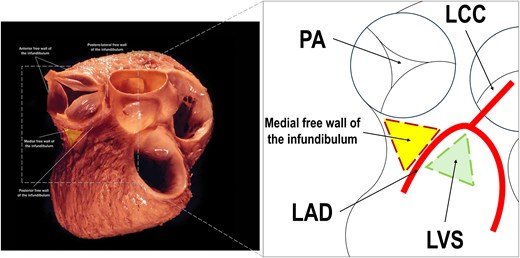
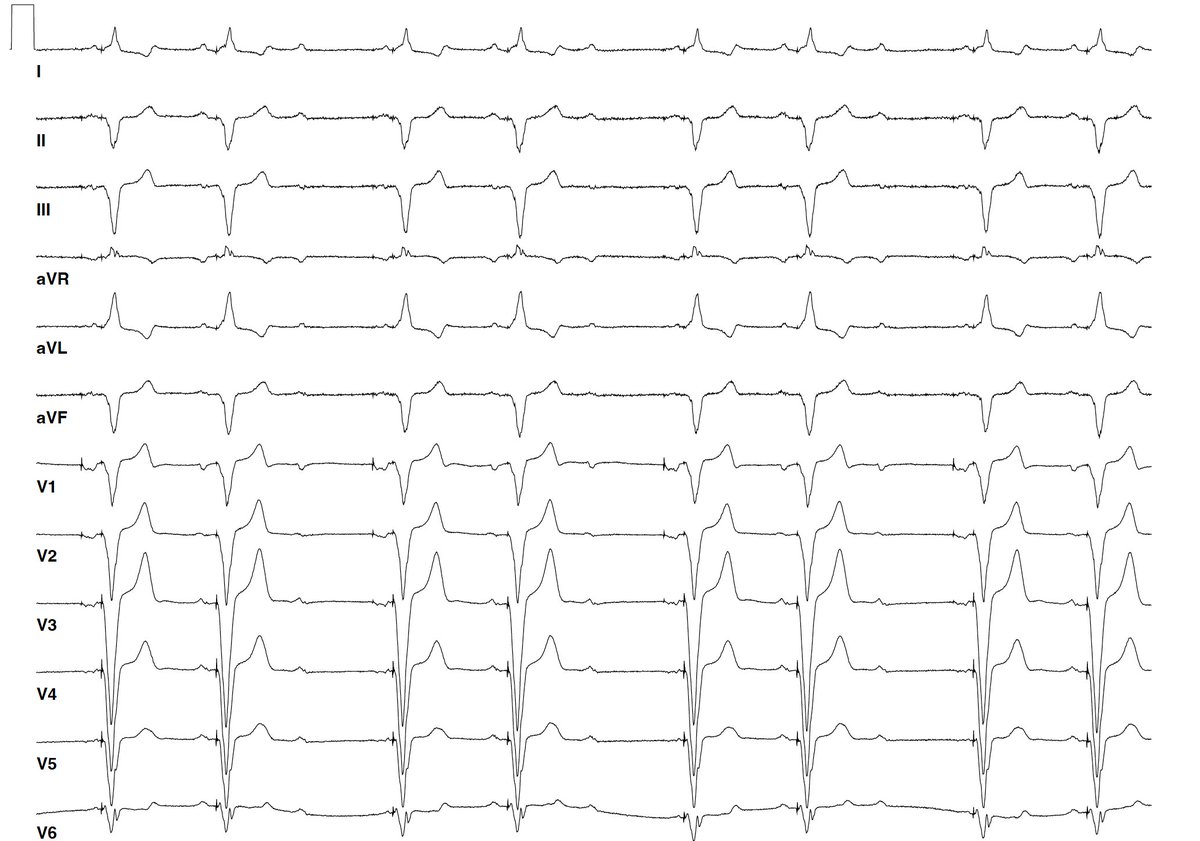
#EPeeps, how many of you would suspect the RCC when seeing this PVC?
Despite early activation at the RVOT free wall, multiple RVOT lesions failed. Ablation at this signal in the RCC finally eliminated the PVC immediately!!!#Epeeps
Wśród bohaterów, którzy pomagali rannym w Krakowie, było dwóch Słowaków. Linda i Mário, studenci medycyny, bez wahania odłączyli się od grupy turystów zwiedzających miasto aby nieść pomoc 🙏🏻💪🏻🤝 Informację pochodzącą od przewodniczki podają słowackie media.
Interesting responses to @drjohnm post of our study. Agree PF PWI is easier BUT 1) is it more durable than RF 2) does it improve outcomes? Every study to date says NO inc PIFPAF RCT with PF! What is this obsession of EPs with PWI?
Peri-mitral flutter in a patient with prior PVI and PW isolation. Mitral block (even with PFA) still suboptimal (https://t.co/g8D6EicX6Z). Will PF + RF using STSF DE be the answer? Block easy to achieve in this case. Need durability data. Excellent mapping by @mahummaps
Another sobering study in AF ablation. Melbourne group reports on 121 patients who have recurrent AF despite durable PVI. All have posterior wall isolation. [Because we can.]
The results are similar to the trials. Not good.
https://t.co/FtckPQI6zT
@peterkistler3
Credit to the EP team in Bern for this excellent remapping study after either RF or PFA. Mandated remapping is much better than remapping for symptoms https://t.co/CrxPRG2Ed5
A) PFA no better than RF for durable PVI
B) Recapitulates GAP study showing that AF still occurs in one-third of durably isolated PVs and 72% of those with reconnected veins DID NOT have AF at one year
This is the crux of our problem in EP: we don't understand the pathophysiology of the condition. PVs get isolated because we can. @TobiasReichlin
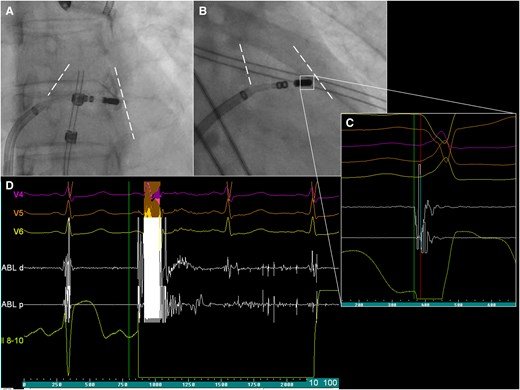
Can RVOT PVCs with transition at V4 still be ablated from the left side? Despite local EGMs being much better on the right, RF resulted only in very late and brief suppression. RF from the left, opposite to the RV lesions immediately eliminated the ectopy.
Kudos to Martin Ruwald et al. for the detailed remapping data. Worth noting though that these numbers come exclusively from:
1️⃣patients with clinical recurrence who returned for redo (not entire initial cohort) and
2️⃣after initial focal-monopolar PFA
This subset doesn’t fully represent durability in total monopolar-PFA population or the (more commonly used for PVI) bipolar PFA systems
🚩How durable is PVI after PFA when patients return for repeat ablation?
In @HRS_O2Journal , Ruwald et al. found:
• 48% complete durable PVI
• 79% of individual PVs remained isolated
• 76% of gaps clustered at the carina
• Organized AT was the main recurrence
The carina may be an important target for improving long-term PFA durability. #EPeeps
Multivessel Coronary Microvascular Vasospasm Following Redo Pulmonary Vein Isolation with Left Atrial Roof Linear Ablation Using Pulsed Field Ablation for Persistent Atrial Fibrillation
https://t.co/gmBkj2cmHV
Bipolar ablation of VT during APHRS 2026 in Busan:
• Magdi Saba – Bipolar RF Ablation in NICM-VT: A Pre-recorded Case from Cleveland Clinic London
Thu 22 Oct, 14:10–14:25
• Takumi Yamada – Bipolar Ablation and Alternative Energy Delivery Strategies for Refractory Intramural VT
Sat 24 Oct, 08:30–08:45
• Ayaka Takeo – Bipolar and Needle Ablation: How to and When to Use? Sat 24 Oct, 15:00–15:15
@ftrae@lukaszzarebski1 I agree….
It mainly goes about precision and reproducibility… and this does not just concern lesion depth, but also lesion width.
Why? Because it allows precise and safe ablation close to the His bundle area. Our study using standard ablation catheters for focal PFA will be presented at #APHRS2026 by @lukaszzarebski1
Why rely on standard focal ablation catheters when you can count on the stability of the Sphere-9 ™ catheter lattice tip? Video from x vivo pre-clinical model at the visible heart lab.
Learn more: https://t.co/PkdaI5lZyP
See risk info: https://t.co/PPGmtZWMnF
Amen:
“The EP community at-large, and other relevant stakeholders, have to be the arbiters of whether the right questions are being asked and whether the right studies are being done. This is why it is critical to ensure that we refocus training programs with this goal in mind.”
Cardiac Electrophysiology at a Crossroads: Building on Dr. Josephson's 20 years of observations. Is EP science, procedure or both? What is the future of EP science?
https://t.co/qQ33wCvekc
#EPeeps#CardioX@ACCinTouch@HRSonline