

Top Tweets for #TapBlock

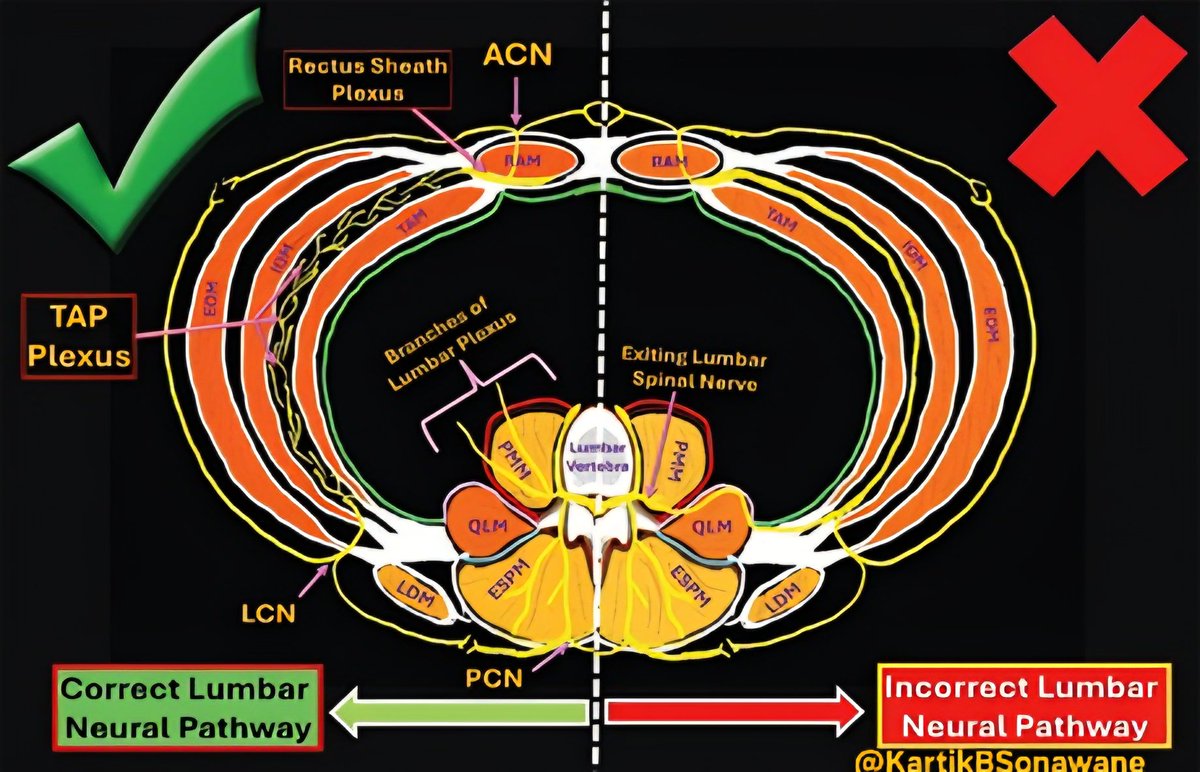
TAP or Trap? - Rethinking the True Territory of the Transversus Abdominis Plane Block
#BeyondTAP #AbdominalAnalgesia #RegionalAnesthesia #TAPBlock #QuadratusLumborum #QLBlock #EOIP #FascialPlaneBlocks #PainManagement #UGRA #AcutePain #AnatomyMatters #BlockSmart #SomaticVsVisceral #KnowBeforeYouBlock
#MyRATips #TipOfTheDay
Tip of the Day:
✨ The Transversus Abdominis Plane (TAP) block is often perceived as a comprehensive abdominal wall block.
✨ Anatomically and clinically, however, its coverage is selective, variable, and frequently incomplete. Let’s decode it logically.
🧠 Segmental - Not Complete Dermatomal Coverage
🔹 Targets anterior rami of T6–L1 within the fascial plane
🔹 Spread is plane-dependent and inconsistent
🔹 Neural branching forms a TAP plexus → dermatomal predictability drops
🔹 Upper abdominal coverage (T6–T9) is unreliable
➡️ Reality: Partial somatic sensory block - not uniform dermatomal anesthesia.
🧩 Medial Sparing - The Rectus Sheath Gap
🔹 Anterior Cutaneous Nerves (ACNs) pierce the posterior rectus sheath
🔹 TAP does not reliably block ACNs
🔹 Midline analgesia requires Rectus Sheath Block
🔹 “Medial escape zone” phenomenon
➡️ Reality : Without RSB, central abdominal wall remains inadequately covered.
⚡ Lateral Cutaneous Nerve Escape
🔹 Lateral cutaneous branches exit early from the neurovascular plane
🔹 Standard lateral TAP frequently spares them
🔹 Posterior TAP improves but does not guarantee coverage
➡️ Reality : Lateral abdominal wall analgesia may be incomplete.
💪 Muscle Innervation Overlap - No True Motor Promise
🔹 Abdominal wall muscles have overlapping segmental innervation
🔹 Blocking selected segments ≠ muscle paralysis
🔹 TAP is primarily sensory
➡️ Reality: It is not a muscle relaxation technique.
🔥 No Visceral Analgesia
🔹 Blocks somatic afferents only
🔹 Visceral pain travels via sympathetic & splanchnic pathways
🔹 Peritoneal stretch & bowel manipulation remain untouched
➡️ Reality: Not adequate as a standalone block for intra-abdominal surgery.
🤔 So Why Consider TAP at All?
Because it still has value, when chosen rationally.
✅ Superficial abdominal wall procedures
✅ Part of multimodal analgesia
✅ When neuraxial is contraindicated
✅ To reduce opioid requirement
✅ When combined strategically (RSB + posterior TAP)
🎯 Decision Lens
🔹 Lower abdominal superficial → TAP acceptable
🔹 Upper abdominal → EOIP preferred
🔹 Mixed somatic + visceral → QL more rational
🔹 Major open abdominal → Epidural still gold standard
🔑 Take-Home
✨ TAP is not wrong - it is simply limited.
✨ It is a plane block, not a pan-abdominal solution.
✨ Choose based on pain source: somatic vs visceral vs mixed.

🚀 “Fascial Highways, Not Magic Shots” - Take-Home Messages from Decoding QL Blocks
#RegionalAnesthesia #PainMedicine #UltrasoundGuided #FascialPlaneBlocks #QuadratusLumborumBlock #QLB #ThoracolumbarFascia #TLF #TransmuscularQLB #AnteriorQLB #PosteriorQLB #TAPBlock #AbdominalWallAnalgesia
🧭 QLB is TAP’s evolved cousin:
TAP mainly stays in the TAP plane (somatic abdominal wall), while QLB tries to “borrow” deeper fascial continuities to extend coverage.
🕸️ The thoracolumbar fascia (TLF) is the real engine:
QLB success is governed more by fascial architecture than by “which nerve you think you’re blocking.”
🛣️ Anterior TLF = the main ‘fascial highway’:
It connects laterally to transversalis fascia, medially to psoas fascia, and cranially toward endothoracic fascia- explaining why deeper approaches can sometimes go broader (and occasionally visceral).
🎯 If you want broader + more predictable spread, think “anterior/transmuscular”:
The review highlights why anterior approaches more consistently access paravertebral/lumbar plexus corridors than superficial/lateral techniques.
🧱 Lateral & posterior QLB = reliable somatic analgesia (mostly):
Great for flank/lateral wall pain, but don’t expect consistent visceral cover.
🔬 T12→L1 transition is the clinical ‘game-changer’:
At/after L1, the psoas is more evident and the lumbar plexus starts forming- helping explain why anterior QLB at/below L1 can be more extensive.
🧠 Stop teaching the wrong nerve story:
Lumbar plexus nerves don’t just “enter the TAP.” That common schematic error leads to unrealistic expectations from TAP/lateral QLB.
🧩 Anterior QLB isn’t one block-it’s multiple sub-compartments: Small needle-tip shifts can redirect spread cranial/medial/posterior and change what you get clinically.
🔼 Want upper abdominal + possible visceral component?
Aim for the plane that favors cranial tracking along endothoracic continuity (subcostal/anterior variants are built for this logic).
🧷 Technique selection should be indication-driven:
Lateral/posterior for somatic flank; anterior/CPPB when you need deeper/lumbar plexus or broader abdominal–pelvic coverage.
⚠️ Safety isn’t optional - anterior is closer to neuraxis/lumbar plexus:
Higher risk of unintended neuraxial spread if volume/plane is wrong; lateral variants risk peritoneal/retroperitoneal breach, so dynamic US, incremental injection, and vigilance matter.
📌 Bottom line:
QLB outcomes vary because anatomy + fascial compliance + injection dynamics vary - so reproducibility comes from precise plane selection, not from “QLB label” alone.
Read in details:
Indian Journal of Anaesthesia https://t.co/CHRCwW6HR0



New research finds ultrasound-guided TAP blocks can safely reduce pain, opioid use, and hospital stays for acute pancreatitis patients in the ER. Breathe easy with this groundbreaking treatment! #TAPBlock #PainManagement #MedicalInnovation https://t.co/NrmkdHsR2v


ظهرت تقنيات جديدة للحد من الشعور بالأ��م بعد العمليات الجراحية مثل تقنية #تاب_بلوك، تعرف عليها من هنا:
#dailymedicalinfo #TAPBlock
https://t.co/PGqssdXZHN
🔥🫁 "Pain at the Core: On-Arrival Blocks for Chest and Abdomen" 🧍♂️🛡️
#PainAtTheCore #OnArrivalBlock
#TruncalAnalgesia #ChestWallBlock #AbdominalBlock
#RegionalAnesthesia #ESPBlock #TAPBlock
#SAPBlock #UltrasoundGuidedRA
#PointOfCareBlocks #OnArrivalRA #TipoftheDay #MyRATips
Tip of the Day:
🟦 Why FOCUS on Truncal Pain Early?
🫁 Chest and abdominal injuries often compromise vital functions - especially breathing, coughing, and cooperation.
🔥 Pain in these regions is often deep, diffuse, and distressing, and opioids alone may not suffice or may cause respiratory depression.
🛠️ Regional blocks offer site-specific, opioid-sparing relief that improves immediate care and downstream outcomes.
🟨 CLINICAL GOALS of Truncal On-Arrival Blocks
🫁 Restore respiratory efficiency (chest trauma, rib fractures)
🚑 Facilitate imaging, positioning, and transport
🧘 Relax abdominal guarding (peritonitis, pancreatitis)
📉 Reduce sympathetic overdrive in trauma
🫱 Enhance cooperation for procedures or airway planning
🟫 COMMON INDICATIONS
🟦 Chest Wall:
Rib fractures (especially multiple)
Flail chest
Post-thoracostomy or chest tube placement
Chest wall contusions in blunt trauma
🟨 Upper Abdomen:
Blunt abdominal trauma
Acute pancreatitis
Upper GI perforation or distension
Postoperative laparotomy or laparoscopy pain
🟧 Lower Abdomen:
Inguinal hernia (painful or strangulated)
Appendicitis with guarding
Abdominal wall hematomas or incisional pain
🟪 BEST CHOICES
🫁 For Chest Wall Injuries:
ESPB, SAPB, or ICNB.
Provide broad dermatomal coverage.
Safe to perform away from critical structures like the pleura.
Ideal for rib fractures, flail chest, and chest tube insertion pain.
🧼 For Upper Abdominal Pain:
ESPB at T6–T9 levels or TAP Block.
Relieve guarding and improve respiratory effort in conditions like pancreatitis or blunt abdominal trauma.
🧩 For Lower Abdominal Conditions:
TAP Block, RSB, IIN/IHN Block.
Provide localized anterior abdominal wall analgesia. Suitable for inguinal hernia, appendicitis, or post-incisional pain.
🟥 ESPB: CHAMPION?
✅ Superficial and safe (away from pleura/major vessels)
✅ Wide craniocaudal spread
✅ Suitable for non-sterile or semi-sterile environments
✅ Excellent for rib fractures and abdominal wall pain
✅ Can be done quickly with or without USG
🟧 KEY PEARLS
🧼 Basic aseptic precautions suffice in emergency use
🩻 USG is ideal but can be landmark-based if skilled
🧾 Document block site, volume, drug, and response
⏱️ Reassess for conversion to longer-acting block or catheter if needed
🟫 CHEST WALL BLOCKS: RULE
“Hit the Rib, Deposit the Drug”
🔹Deep SAP Block – Needle hits the rib, inject deep to serratus
🔹External Oblique Intercostal Plane Block – Target rib at anterior/mid-axillary line, inject above EO
🔹Parasternal Block – Identify rib near sternum, inject in intercostal plane
🎯A safe, reproducible approach - perfect for emergency or limited-resource settings.
🟨 ABDOMINAL WALL BLOCKS: RULE
“Follow the Muscle, Find the Plane”
🔹TAP Block – Feel or visualize the abdominal wall → insert between internal oblique & transversus abdominis
🔹Rectus Sheath Block – Palpate the rectus muscle → inject posterior to it, above posterior sheath
🔹Ilioinguinal/Iliohypogastric Block – Palpate ASIS → inject in plane between internal oblique and transversus abdominis near the iliac crest
🎯Key Tip: Identify the muscle → follow its plane → deposit where spread flows freely.
✅Reliable, reproducible, and effective for anterior abdominal wall analgesia.
"When pain impairs breathing or masks diagnosis, a timely On-Arrival Block for the trunk may be your best intervention - not just for comfort, but for survival."

“🦴 From Skin to Capsule: Smart Blocks for Every Hip Cut!”
#THR #RegionalAnesthesia #PENGblock #FICB #QLblock #TAPblock #LFCNblock #SmartAnalgesia #PostOpPain #OrthoAnesthesia
#TipoftheDay
#MyRATips
Tip of the Day:
The key to Post-op analgesia after Total Hip Replacement?
Block what matters—based on Surgical approach & Innervation.
▶️ Anterior Approach
🔹 Joint Capsule (Anterior)
– Use PENG block (targets FN, ON, AON)
🔹 Skin – Upper Incision
– Subcostal (T12), Iliohypogastric (L1)
– Add TAP (subcostal/lateral) or QL block (Type 1/2)
🔹 Skin – Mid/Lower Incision
– IIN, GFN, LFCN → Block with FICB, TFP, or LFCN block
▶️ Anterolateral Approach
🔹 Joint Capsule (Anterior & Lateral)
– Covered well by PENG block
🔹 Skin
– Mostly LFCN, ± IIN/GFN
– Use FICB or LFCN block
– If upper extension → add TAP/QL
▶️ Posterolateral Approach
🔹 Joint Capsule (Posterior)
– Minimally nociceptive → No sciatic block needed
– Use PENG for anterior capsule
🔹 Skin – Upper Incision
– T12, L1 (Subcostal, IHG) → TAP/QL block
🔹 Skin – Lower Incision
– LFCN → Use LFCN block or high-volume FICB
▶️ Local Anesthetic Strategy
🧪 Type:
Ropivacaine 0.2–0.25%, Bupivacaine 0.125–0.25%
💉 Volumes:
– PENG: 20 mL
– FICB: 30–40 mL
– TAP/QL: 20–30 mL
– LFCN: 5–10 mL
My go-to hierarchy for THR analgesia:
QLB > FICB > PENG + LFCN
"Block smart.
Incision-specific.
Capsule-aware.
Approach-adapted."


🧪 What does epinephrine do to ropivacaine during a TAP block?
In this RCT, Rozier et al. found:
✔️ No change in Cmax
⏱️ Delayed Tmax
📉 Lower Cmean
❤️ No toxicity
🔗 Read all about this study here: https://t.co/9zxxZlNlHE
#RAPM #TAPBlock #Anesthesia #Epinephrine

مع التقدم الطبي المذهل، ظهرت تقنيات ج��يدة للحد من الشعور بالألم بعد العمليات الجراحية مثل تقنية #تاب_بلوك ..
تعرف على هذه التقنية بالتفصيل من هنا:
#dailymedicalinfo
#TapBlock
https://t.co/7gP2qxtloh
مع التقدم الطبي المذهل، ظهرت تقنيات جديدة للحد من الشعور بالألم بعد العمليات الجراحية مثل تقنية #تاب_بلوك، وسنتعرف عليها في هذا المقال
#dailymedicalinfo #TAPBlock
https://t.co/PGqssdXrSf

Pro vs Con #ERAS debates 🥊 with @BonaldoGiulio and @Pan_Teresa_MD #carbload #TAPblock #drains @ErasSociety @pedroramirezMD


Administering TAP blocks significantly decrease opioid requirements and shorten hospital stays for patients undergoing minimally invasive hysterectomy @AAGLJMIG
#jmigjc #PainManagement #TAPBlock
مع التقدم الطبي المذهل، ظهرت تقنيات جديدة للحد من الشعور بالألم بعد العمليات الجراحية مثل تقنية #تاب_بلوك ..
تعرف على هذه التقنية بالتفصيل من هنا:
#dailymedicalinfo
#TapBlock
https://t.co/7gP2qxtTdP
مع التقدم الطبي المذهل، ظهرت تقنيات جديدة للحد من الشعور بالألم بعد العمليات الجراحية مث�� تقنية #تاب_بلوك ..
تعرف على هذه التقنية بالتفصيل من هنا:
#dailymedicalinfo
#TapBlock
https://t.co/7gP2qxtTdP

@dr_tgro @beckimarshRA @ajrmacfarlane @DrRobbieErskine @PeterMerjavy @womackjonathan @amit_pawa @AminaBenyoucef5 @davidleegumd @UCI_Urology @IntuitiveSurg @pennsurgery @AR_Jarrar More evidence for Laparoscopic assisted transversus abdominis plane #TAPblock (vs ultrasound guided) in laparoscopic #BariatricSurgery
Ping @AR_Jarrar @AdeleBudiansky
HT:
Algyar MF, Abdelsamee KS. BMC Anesthesiol 2024
https://t.co/rz428Yhd9s
مع التقدم الطبي المذهل، ظهرت تقنيات جديدة للحد من الشعور بالألم بعد العمليات الجراحية مثل تقنية #تاب_بلوك ..
تعرف على هذه التقنية بالتفصيل من هنا:
#dailymedicalinfo
#TapBlock
https://t.co/7gP2qxtloh
تعد الأيام الأولى بعد الخضوع لأي عملية جراحية من أصعب الأيام التي تمر ببطء على صاحبها.. ولأن التكنولوجيا تأتينا بكل جديد تعرف على حقنة #تاب_بلوك للتخدير بعد جراحات البطن: #dailymedicalinfo #tapblock
https://t.co/7gP2qxtTdP
ظهرت تقنيات جديدة للحد من الشعور بالألم بعد العمليات الجراحية مثل تقنية #تاب_بلوك، وسنتعرف عليها في المقال التالي بشيء من التفصي�� #dailymedicalinfo #TAPBlock https://t.co/PGqssdXrSf

Pre-operative vs. postoperative TAP block ⚡️
👇🏻👇🏻👇🏻👇🏻👇🏻👇🏻👇🏻👇🏻👇🏻
#regionalanesthesia #tapblock #cholecystectomy #pain #metaanalysis
@SerkanTulgarMD @DecassaiMD @BMC_series @SpringerNature
https://t.co/EAY0AL1qtO

مع التقدم الطبي المذهل، ظهرت تقنيات جديدة للحد من الشعور بالألم بعد العمليات الجراحية مثل تقنية #تاب_بلوك .. تعرف على هذه التقنية بالتفصيل من هنا: #dailymedicalinfo #TapBlock
https://t.co/7gP2qxtloh
يتزا��د الشعور ب #الألم في موضع الجرح والشعور بالتعب العام
بعد الخضوع لأي عملية جراحية بصفة عامة..
تعرف على تقنية #تاب_بلوك للتخدير بعد جراحات البطن بالتفصيل من هنا:
#dailymedicalinfo
#TapBlock
https://t.co/7gP2qxtloh
Last Seen Hashtags on Sotwe
Nyúlcipőbolt
Seen from Canada
รับงานลพบุรี
Seen from Thailand
qosslut
Seen from United States
Memphisisauniontown
Seen from Thailand
พะเยานัดเย็ด
Seen from Thailand
ควยพม่า
Seen from Thailand
mms
Seen from India
rishtaCulture
Seen from Ukraine
KidneyTumors
Seen from United States
repbrklyn
Seen from France
Most Popular Users

Elon Musk 
@elonmusk
241.7M followers

Barack Obama
@barackobama
118.9M followers

Cristiano Ronaldo
@cristiano
114.6M followers

Donald J. Trump
@realdonaldtrump
111.9M followers

Narendra Modi
@narendramodi
107.2M followers

Rihanna
@rihanna
98.7M followers

NASA
@nasa
92.4M followers

Justin Bieber
@justinbieber
91.8M followers

KATY PERRY
@katyperry
90.1M followers

Taylor Swift
@taylorswift13
84M followers

Lady Gaga
@ladygaga
75.5M followers

Virat Kohli
@imvkohli
73.5M followers

Kim Kardashian
@kimkardashian
70.9M followers

YouTube
@youtube
68.8M followers

Neymar Jr
@neymarjr
66.5M followers

Bill Gates
@billgates
65.2M followers

Selena Gomez
@selenagomez
63.1M followers

The Ellen Show
@theellenshow
62.3M followers

CNN
@cnn
61.8M followers

X
@x
60.7M followers