

Top Tweets for #rezpeg

I have made several posts on $CRVS #Tregs could be beneficial in atherosclerosis
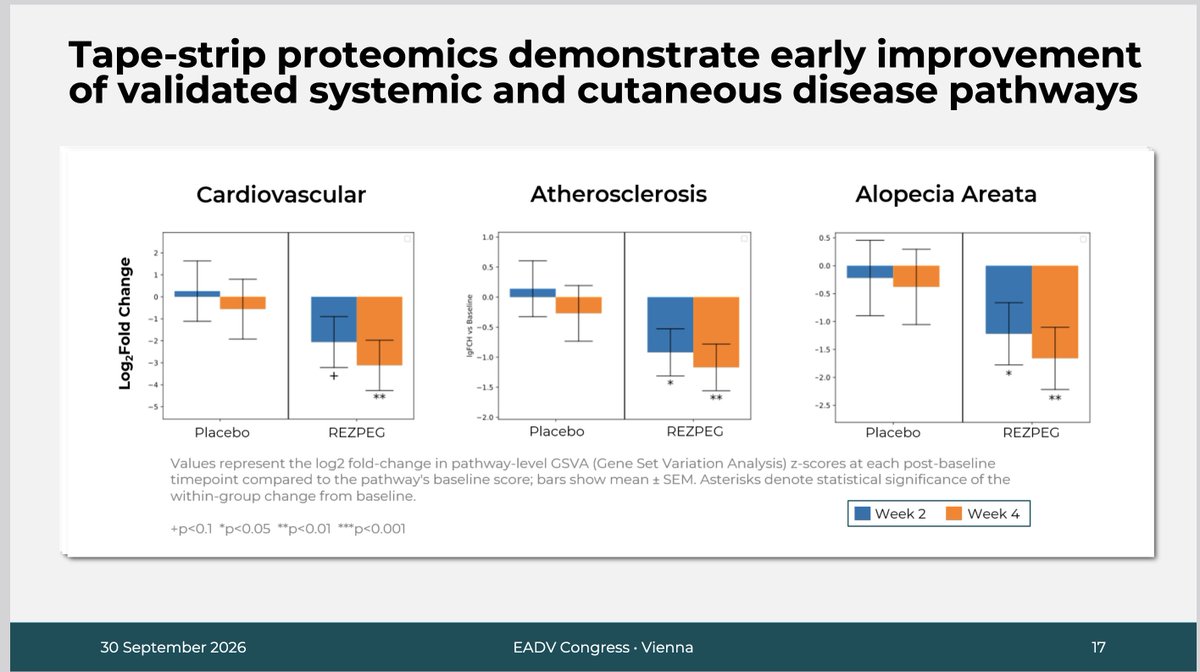
$NKTR new slides show cardiovascular and atherosclerotic benefit for #Rezpeg #Tregs furthering the potential of Tregs in this disease
Good news for Treg therapies + read thru for #soquelitinib
Nektar slides, see Slide 17
https://t.co/sg6ov151QY
Prior posts on Tregs potential in removing atherosclerotic plaques:
https://t.co/hPXPqbr061
https://t.co/D338Z1gR2G
Rationale 1 of 2: #NRP1 negative #iTregs are ESSENTIAL for #atherosclerosis plaque regression.
Tregs inhibit #Th1 cells and re-educate #macrophages to M2-like variant w/ tissue repair functions, clears apoptic cells. Very promising treatment if we could make these Tregs $CRVS

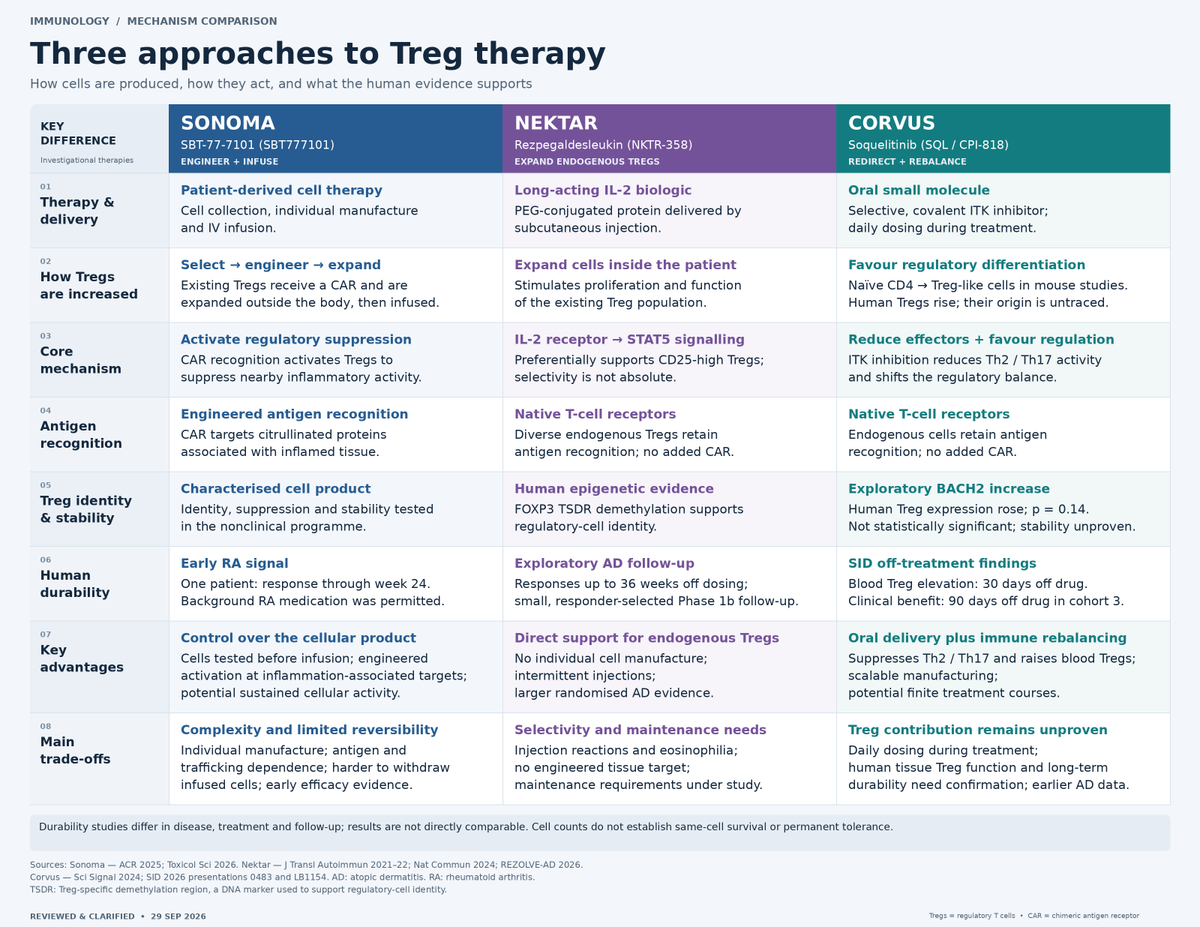
#Tregs in Autoimmune, 3 Approaches:
🔹 Sonoma SBT-77-7101: engineer & infuse CAR Tregs
🔹 $NKTR #Rezpeg: expand existing Tregs w/ PEG-IL-2
🔹 $CRVS #soquelitinib: oral ITK inhibition reduces #Th2/#Th17 activity, increases Tregs
Different routes toward durable immune control
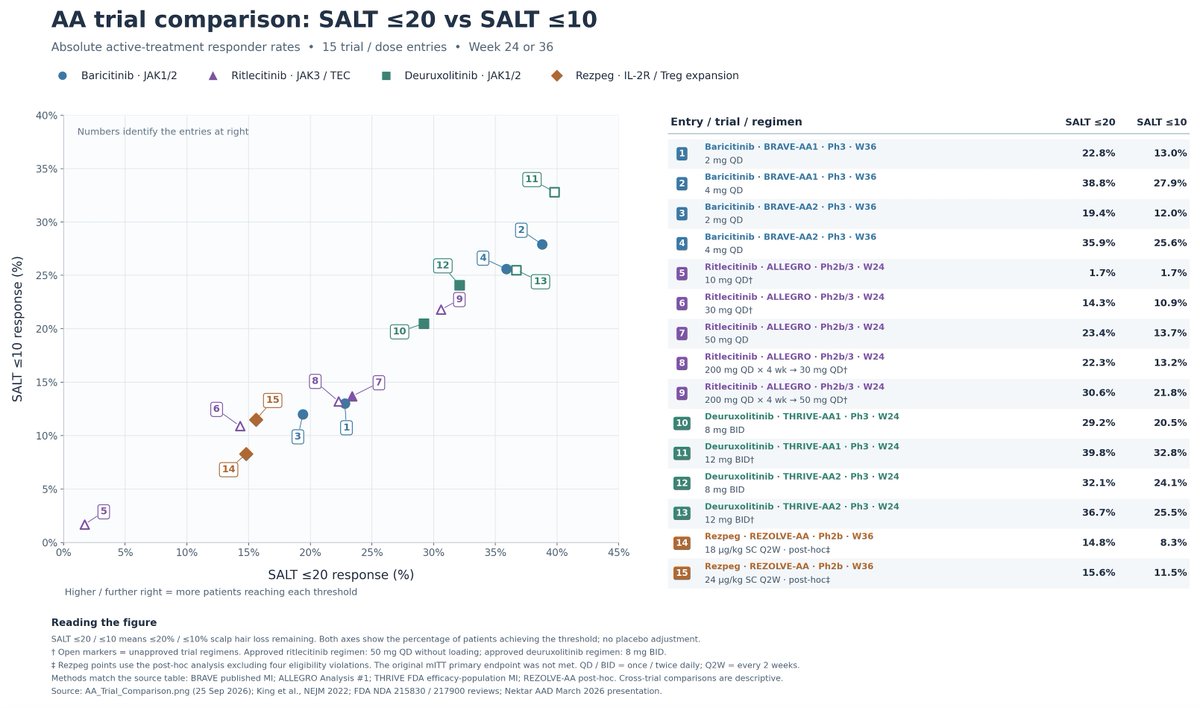
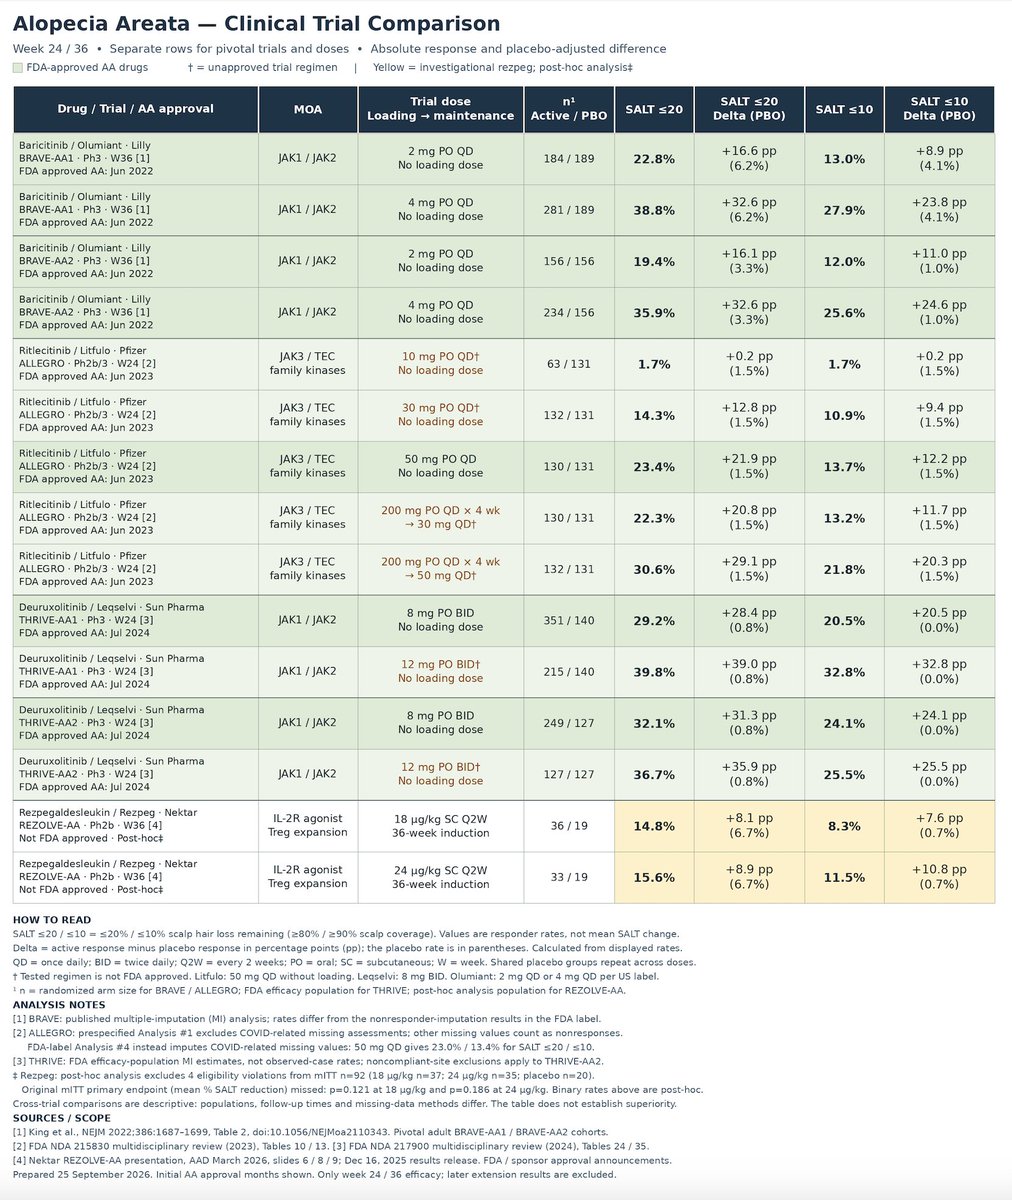
Alopecia areata #AA trial results for benchmark:
Table (3) FDA approved drugs (Ph3 data):
$LLY #baricitinib JAK1/2
$PFE #ritlecitinib JAK3, TEC
Sun #deuruxolitinib JAK1/2
also added Ph2 data from
$NKTR #rezpeg IL-2 Treg
Scatter plot of SALT≤20 v SALT≤10 (no PBO-adj)
@plainyogurt21 One more post where I made a table looking at these alternate pathways upstream of STAT6 part of prevalent Q576R polymorphism showing how $KYMR STAT6 degrader KT-621 may struggle compared to $NKTR #Rezpeg $SNY $REGN #Dupilumab $CRVS #Soquelitinib
https://t.co/5JyVLQ2Ejp
Table of different MOA control of inflammation for polymorphism in AD:
1. $REGN $SNY #Dupilumab comprehensive
2. $CRVS oral #soquelitinib comprehensive
3. $KYMR oral #STAT6 degrader KT-621 likely to struggle
4. $NKTR #Treg promoter #Rezpeg may have #Th17 challenges


$ABBV #Upadacitinib AA data weakens case for $NKTR to spend on conventional Ph 3 AA program
May delay Ph 3 until Q426 #Rezpeg off-treatment data. Durability readout become much more important after upadacitinib data.
Rezpeg advantage likely durability + safety, not efficacy
Newly published:
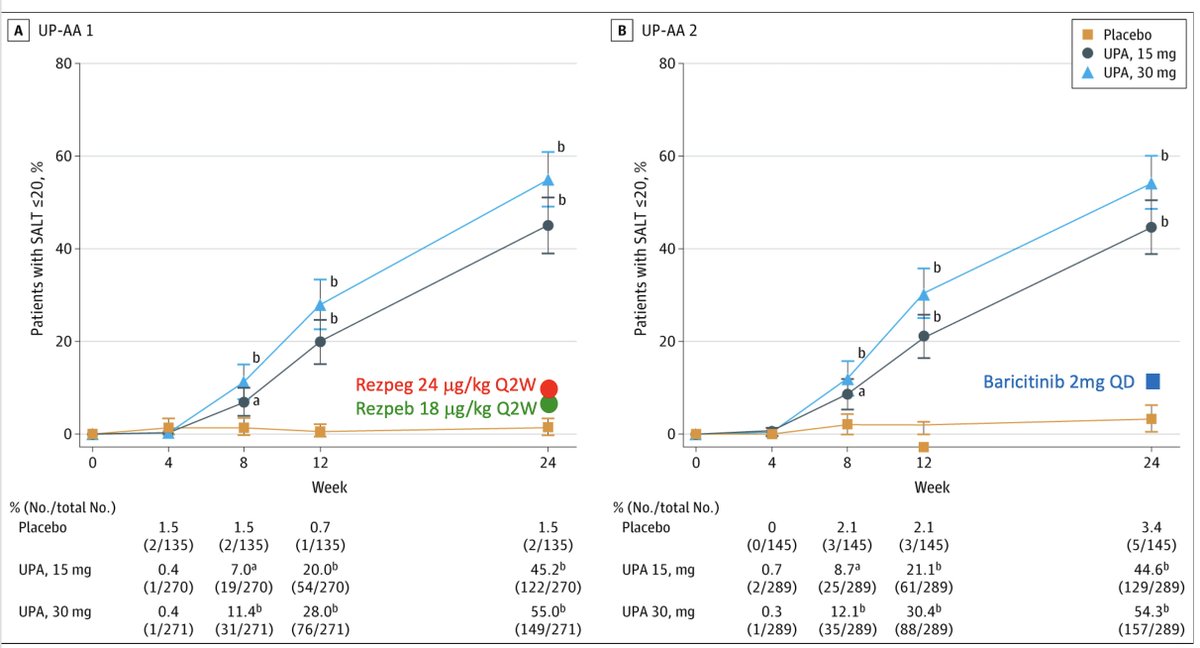
$ABBV #Upadacitinib (selective JAK1) Ph3 Alopecia Areata (AA) Results at 24 weeks
Comparing SALT ≤20 with:
$NKTR #Rezpeg (#Treg)
$LLY #Baricitinib (JAK1/3)
Added Rezpeg and Baricitinib data for visual on chart
Nektar data
https://t.co/eUg6gRBZNN

Newly published:
$ABBV #Upadacitinib (selective JAK1) Ph3 Alopecia Areata (AA) Results at 24 weeks
Comparing SALT ≤20 with:
$NKTR #Rezpeg (#Treg)
$LLY #Baricitinib (JAK1/3)
Added Rezpeg and Baricitinib data for visual on chart
Nektar data
https://t.co/eUg6gRBZNN

In severe #AlopeciaAreata, upadacitinib improved scalp, eyebrow, and eyelash hair outcomes and alopecia areata–specific quality of life vs placebo, with no new safety findings through 24 weeks. https://t.co/ZlOaWTXkJh

Updated Atopic Dermatitis Dev Timelines:
Following 2Q reports + recent trial starts, new timelines of current status and plans for each:
$NKTR - #Rezpeg Ph3
$APGE / $ABBV - #Zumilokibart Ph3 ready
$EVMN - Ph2 x 2
$KYMR - KT-621 Ph2
$CRVS - #soquelitinib Ph2

Atopic Dermatitis Space Heating Up?
Plausible $KYMR accelerating oral #STAT6 degrader KT-621 timeline increased competitive urgency around $APGE for $ABBV buyout this week
Today's news compresses lead $APGE and $NKTR biologics had over orals in development behind them

Fast-Track Timelines for Some Atopic Dermatitis Drugs
$NKTR #Rezpeg - Fast Track (FT), 16 mo after Ph2b start
$KYMR KT-621 - FT, 4.5 mo into Ph 2b
$CRVS #Soquelitinib - If applied for, FT if follows KT-621 timeline 3Q-4Q26 or plausible coincide/follow Angel AD data in 4Q26-1Q27


Treg protect against lung disease through amphiregulin....
https://t.co/g03RuoxB7D

Atopic Dermatitis Landscape
Oral drugs in Ph2b for AD ~1 phase behind (6-15 months) Ph3 ready $APGE #zumilokibart ($11B buyout $ABBV) and $NKTR #Rezpeg:
$EVMN EVO756 #MRGPRX2 antag, data 3Q26
$KYMR KT-621 #STAT6 degrader, data mid-27
$CRVS #soquelitinib #ITK inhib, same mid-27

$CRVS SID data akin to maintenance:
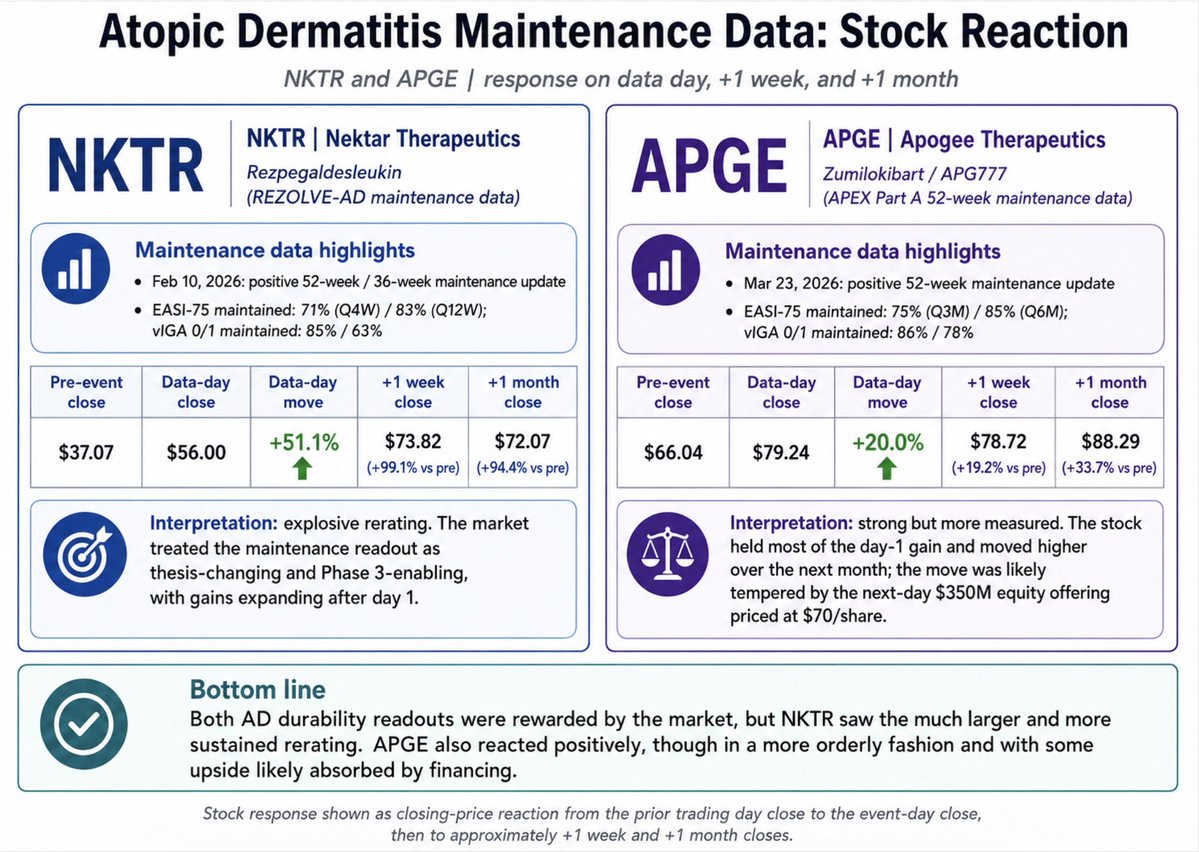
AD Maintenance Data: Stock Reactions for $APGE #zumilokibart + $NKTR #Rezpeg = Large 1-day, 1-wk, 1-mo gains ⤵️
For $CRVS, a convincing soquelitinib maintenance/remission dataset at SID + biomarker data supporting strong mechanistic rational ITK inhibition in other autoimmune indications could be more NKTR-like (i.e., $24-$31/sh) than APGE-like ($19-$22/sh) as story increasingly becomes “oral Signal 1 immune reprogramming w/ off-drug durability”
Both scenarios are biased to higher prices, just vary by degree. The math shorting 18.4M shares into SID doesn't make sense to me.
$CRVS #soquelitinib SID Data + Investor Call, May 14
Potentially Market Moving
High-Impact Points To Watch:
1. Lasting 90-day off-drug durability confirmed Cohort 4
2. Biomarkers support durability mechanistically
3. Strong efficacy in prior-treated / harder AD patients
4. Supports broad application in HS, asthma + other I&I
* Adjust probabilities and values as see fit. These are personal estimates for myself based on Cohort 1-3 data and literature

Atopic Dermatitis Trials Exclusion/Inclusion Critera ⤵️
Patient Disease Severity from lowest to highest, refractory hardest to treat
$NKTR #Rezpeg, IL-2
$KYMR KT-621, STAT6
$APGE APG777, IL-13
$SNY $REGN #Dupilumab, IL-4
$AMGN #Rocatinlimab, OX40L
$CRVS #Soquelitinib, ITKi

Atopic Dermatitis Landscape:
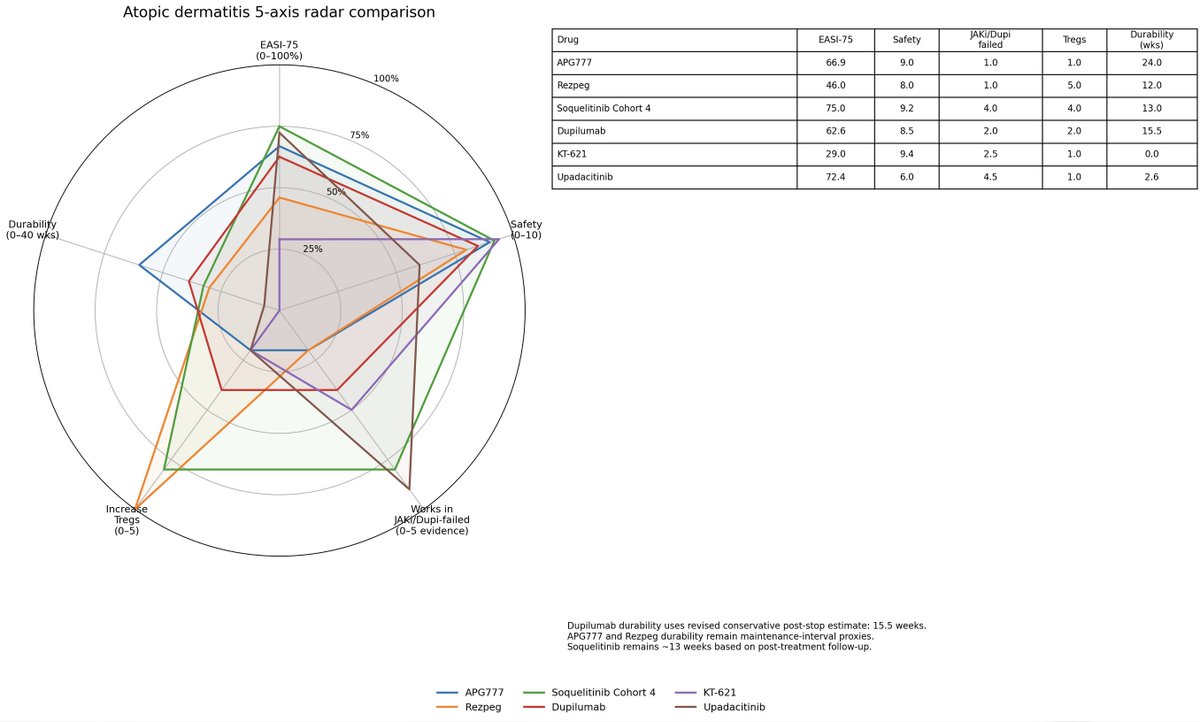
Updated earlier 5-axis radar graph w/ actual data for: EASI-75, Safety, Durability, Treg, Failed Patients ⤵️
$SNY $REGN #Dupilumab,IL-4
$ABBV #Upadacitinib, JAKi
$APGE APG777, IL-13
$NKTR #Rezpeg, IL-2
$KYMR KT-621, STAT6
$CRVS #Soquelitinib, ITKi
Atopic Dermatitis Landscape:
Updated earlier 5-axis radar graph w/ actual data for: EASI-75, Safety, Durability, Treg, Failed Patients ⤵️
$SNY $REGN #Dupilumab,IL-4
$ABBV #Upadacitinib, JAKi
$APGE APG777, IL-13
$NKTR #Rezpeg, IL-2
$KYMR KT-621, STAT6
$CRVS #Soquelitinib, ITKi
Summary graphic of atopic dermatitis drugs/targets by benefit/treatment profile:
SOC benchmarks: #Dupilumab $SNY $REGN and #Upadacitinib $ABBV
Compare to:
Injectables in Ph2b trials
#APG777 $APGE
#Rezpeg $NKTR
Oral drugs in Ph2b trials
#soquelitinib $CRVS
KT-621 $KYMR


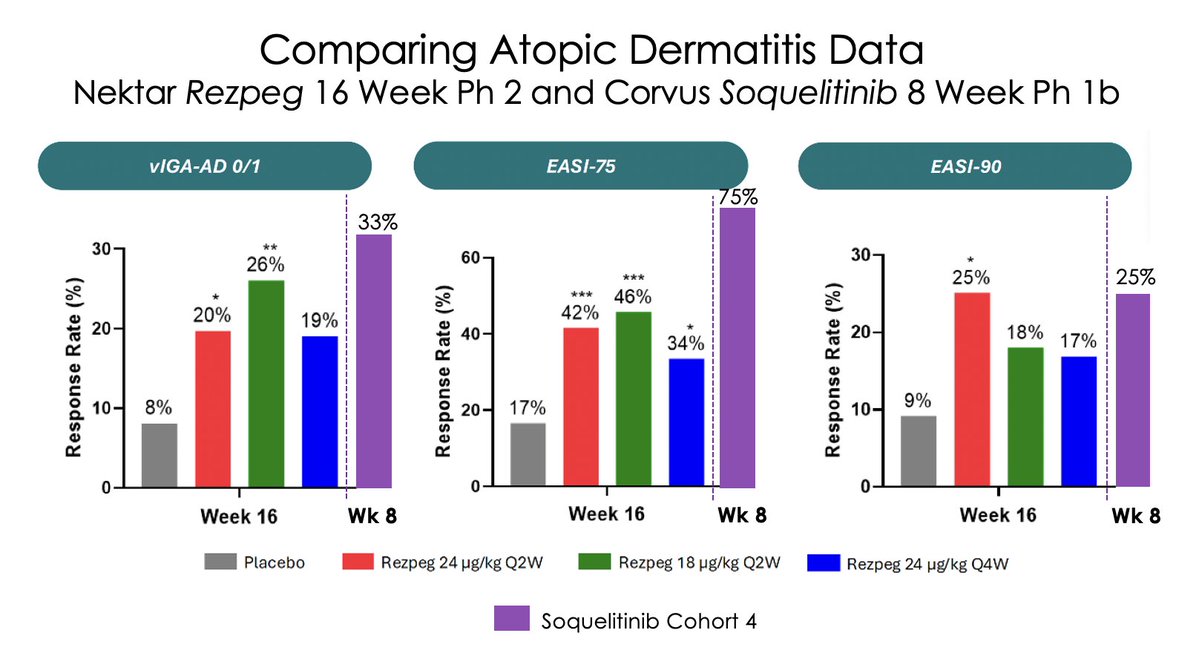
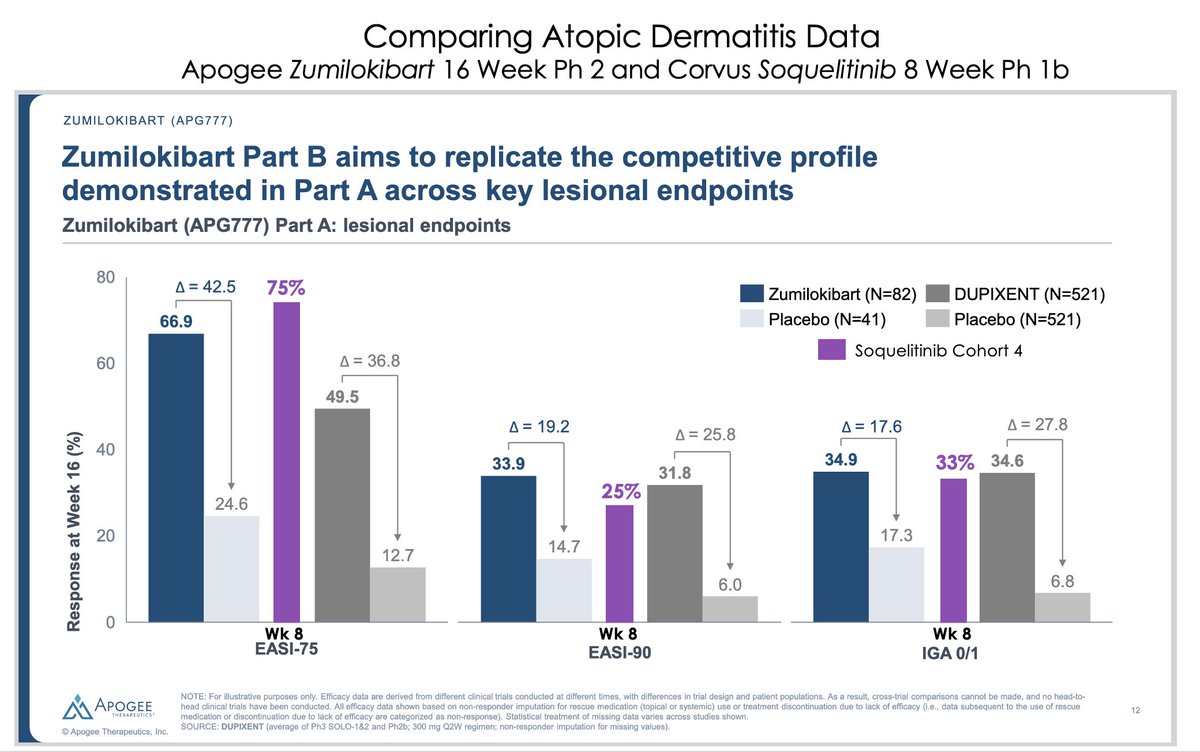
Visual $CRVS early 8wk Ph1b data w/ oral ITKi #soquelitinib compared to recent 16wk Ph2 AD data:
$APGE #Zumilokibart
$NKTR #Rezpeg
Caveats:
Cross-trial comparison
Trials had very different inclusion/exclusion criteria
Just visual summary as SQL now in Ph2b
Not picking winners
🚨 $CRVS Ph 2 atopic dermatitis trial design sets up #soquelitinib to be first line therapy in AtD and used in relapsed patients.
$CRVS requiring enrolled patients in upcoming Ph 2 to have failed either topical or systemic therapy i.e., #Dupixent or #JAK inhibitor. Very strong indication of what $CRVS likely seeing in Cohort 4, data in Jan.
No other atopic dermatitis trial has ever been designed in this way taking on the toughest patients w/ the most severe disease that failed other therapies. Trials typically require biologic naive patients, very very different trials.
https://t.co/fozgC10Bfv
Summary graphic of atopic dermatitis drugs/targets by benefit/treatment profile:
SOC benchmarks: #Dupilumab $SNY $REGN and #Upadacitinib $ABBV
Compare to:
Injectables in Ph2b trials
#APG777 $APGE
#Rezpeg $NKTR
Oral drugs in Ph2b trials
#soquelitinib $CRVS
KT-621 $KYMR

It's a smart bet
I have a slightly different perspective on it:
Dupi's 2031 LOE will be unique in a way where they will still be a Best in Disease gold standard product. When dupi biosimilars come into the market they will be widely used bc of this gold standard efficacy and safety combined with the discounted price (40-70% discount)
This creates a dynamic where payers will need to evaluate whether the premium they're paying for your drug is more value than a dupi biosimilar. This also increases the amount of dupi failures and dupi experienced AD in the market
So the question every drug program should be asking is:
1. How much do they differentiate (efficacy, safety, administration route, dosing frequency, durability) to a dupi? And is that enough to justify the pricing premium of your drug?
2. If I can't beat dupi on a price adjusted basis, can I work on dupi experienced and/or failure AD pts?
(There's also the ability capture that AD pt population that has a Asthma comorbidity but you still need to beat dupi here.)
Any drug program creating me-too drugs or dodging dupi-experienced and dupi failures pts in their phase 2 and 3 trials are essentially shooting themselves in the foot.
This is my view on these names: $KYMR's KT-621: MOA-wise they won't be beating dupi since they only target one source of that Th2 inflammation whereas dupi could hit the others. They will struggle on mixed Th2/Th17 diseases so if they have any asian sites or more African American patients, I'd be scared of being positioned in those readouts. It is an oral so I think they can capture pts that have needle phobia at 1L. After that, I'm not sure where they would fit especially if efficacy and safety doesn't hold up. Also $SNY dropped $KYMR's IRAK4 program so that partnership is not safe if efficacy doesn't hold up.
$NKTR should be able to work on dupi experienced and failures hence, why I'm confused why they had to filter for a biologic naive pt pop in their phase 2bs so now they have nothing to guide their phase 3 design. Their durability is real though. It looks like you have to dose for a longer period to balance the Treg/teff ratio to get more efficscy that's why phase 3 has a 24wk induction period.
IL-13s have some data on being able to work on dupi experienced and failures so they will have a place in this market and I believe $APGE (APG-777) dosing frequency can set itself apart
Ox-40s are essentially dead but if amli still sells, I'd say that's a good sign that the market is still looking for options
JAK inhibitors will still have a place in severe-very severe patients. I can actually envision a treatment landscape where JAK inhibitors are used in short course to quickly control disease and then Treg inducers $NKTR, $CRVS to maintain the response.
Need to look at $EVMN's programs but new MOAs and orals will carve a market share
Bispecifics will be interesting but it's all about whether they can best dupi and can work on dupi failures (especially IL17A/F x IL13, not sure about IL13xTSLP)
$CRVS program to me is the best suited to survive in this post-dupi LOE world. It's an oral and a new MOA. Works on dupi and JAK failures. Can work on th2/th17 diseases and CTCL pts that present themselves like AD (which allows it to be used 1L for some patients). It can work on Asthma comorbidity with it's effects on ILC2s and reduction of IL-5 and it can even work on the neutrophilic asthma pts where dupi is ineffective. Durability is similar to $NKTR's durability and good to know that longer dosing (more tregs) can lead to extended effects (increased EASI-100s). There's an unknown on safety though Ritlecitinib (hits ITK and JAK3 can provide some read-through as it is viewed as the safest JAK. It's early tho but mgt clinical development design, planning, and execution are top notch. It's hard not to be bullish when looking at it this way.
@tradingsssss Key point: $NKTR #Rezpeg maintenance data and $CRVS #soquelitinib duration benefit data validate each other mechanistically
Increasing Tregs = Lasting Disease Control
Both increase Tregs, see charts
#Rezpeg injections every 2 weeks
#Soquelitinib oral pill taken over 4 weeks


$CRVS oral ITK inhibitor #soquelitinib AD profile:
Works fast as JAKi + EASI-75 benefit months off-treatment
Oral therapy in just 4-8 wks offers $ABBV JAKi disease control but better safety + $NKTR #Rezpeg duration
Also works in patients that fail #Dupilumab or #Upadacitinib


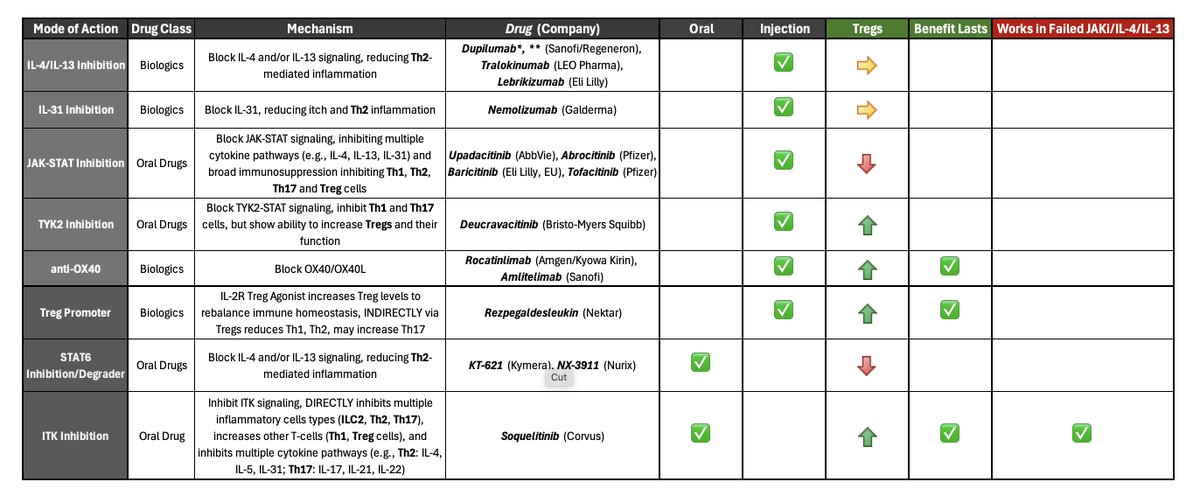
🚨 Table of Drug Profiles for Different Treatments/Targets in Atopic Dermatitis, FDA-approved and In-Development ⤵️
$ABBV $AMGN $APGE $BMY $CRVS $KYMR $LLY $NKTR $PFE $REGN $SNY
$NKTR looking forward to maintenance data to see potential duration benefit that may be possible w/ increased #Treg population.
Comparison of Ph2b atopic dermatitis data
Nektar v #OX40 class:
$NKTR #Rezpeg IL-2Ra agonist
$SNY #Amlitelimab OX40L
$AMGN #Rocatinlimab OX40

$NKTR #Rezpeg INCREASES CD56 bright NK cell population, no data on CD16 mentioned, but may be worth looking at for HIV?
https://t.co/2i2B04k5dO
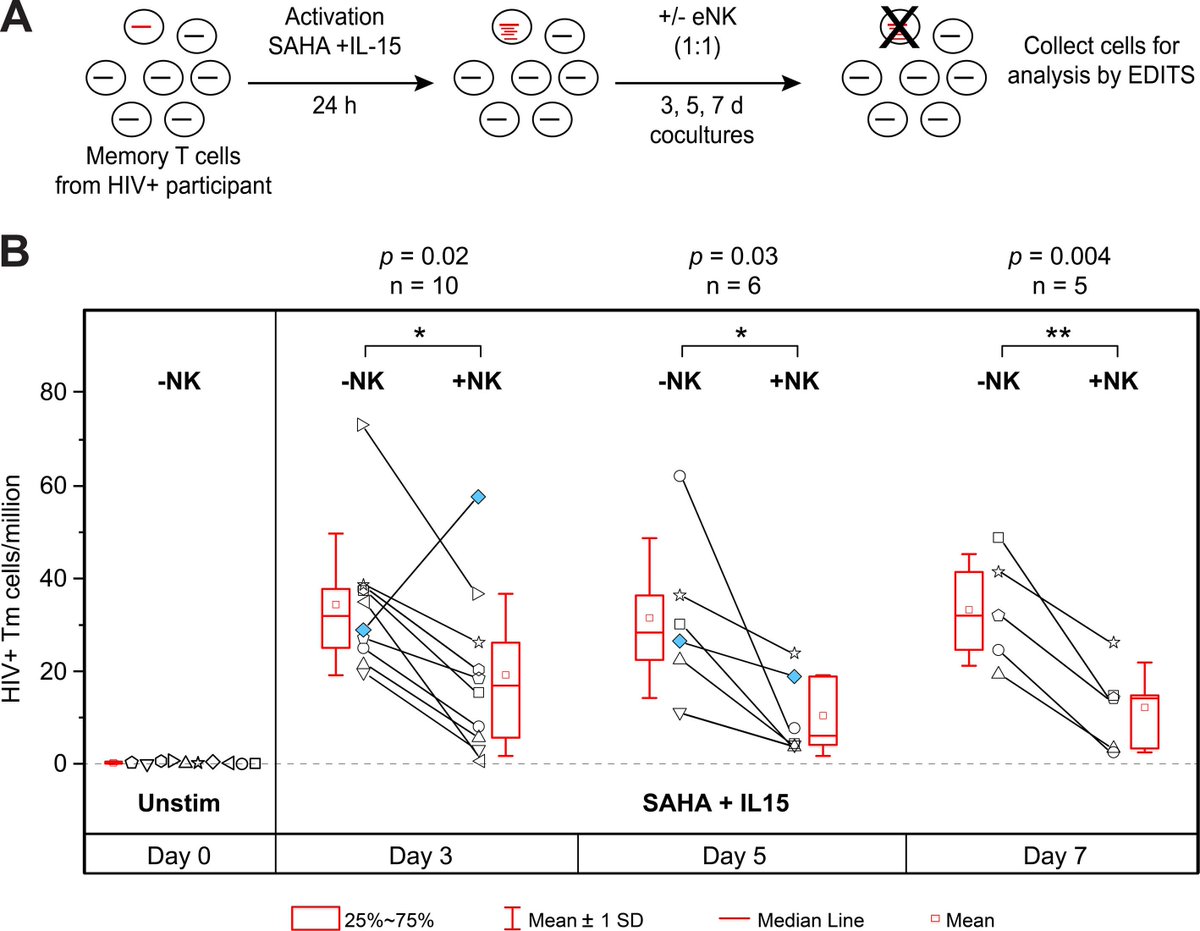
🚨 New Paper: Expanding CD56 bright CD16+ NK cells can reduce latent HIV-1 reservoir


Adoptive immunotherapy with in vitro expanded CD56bright CD16+ NK cells combined with LRA treatment can reduce the latent HIV-1 reservoir @mbiojournal @cwru
https://t.co/EnWE9BJ2T8
Wow! On back of #amlitelimab OX40L disappointing and $SNY de-prioritising, now $AMGN handing theirs back to Kyowa.
Bios with new I&I targets just went up in value ⬆️
$CRVS ITKi #soquelitinib (oral)
$KYMR #STAT6 degrader KT-621 (oral)
$NKTR #Treg promotor #Rezpeg (inj)

$AMGN hands back ox40 rocat back to kyowa https://t.co/BR6AwYU4iF $SNY
Last Seen Hashtags on Sotwe
Trends for you
Most Popular Users

Elon Musk 
@elonmusk
241.5M followers

Barack Obama
@barackobama
118.8M followers

Cristiano Ronaldo
@cristiano
114.5M followers

Donald J. Trump
@realdonaldtrump
111.8M followers

Narendra Modi
@narendramodi
107.1M followers

Rihanna
@rihanna
98.7M followers

NASA
@nasa
92.3M followers

Justin Bieber
@justinbieber
91.8M followers

KATY PERRY
@katyperry
90M followers

Taylor Swift
@taylorswift13
84M followers

Lady Gaga
@ladygaga
75.5M followers

Virat Kohli
@imvkohli
73.5M followers

Kim Kardashian
@kimkardashian
70.9M followers

YouTube
@youtube
68.8M followers

Neymar Jr
@neymarjr
66.5M followers

Bill Gates
@billgates
65.3M followers

Selena Gomez
@selenagomez
63.1M followers

The Ellen Show
@theellenshow
62.2M followers

CNN
@cnn
61.7M followers

X
@x
60.7M followers