@BBCNewsNI Amalgamate Trusts. Implement Bengoa. Compulsory health education/prevention in schools. Supertax alcohol/cigs/harmful foods & remove VAT on healthy foods. Make private health insurance tax deductible. Remove nhs healthcare litigation. Legislate for healthcare volunteers.
@cahillbooks Sad and depressed to read of your experience. Healthcare staff are overwhelmed, demoralised and burnt out. Everyone affected by failed services needs to give it to their politicians in the ear ad nauseum and hold them to account.
📢 NEW REPORT:
A year-long analysis of BBC coverage of Israel’s war on Gaza reveals a pattern of bias, double standards & silencing of Palestinian voices.
Despite 34x more Palestinian deaths, Israeli fatalities received 33x more coverage per death.
DOWNLOAD FULL REPORT HERE
📄 https://t.co/JlZX4uSpB1
#BBCBias #Gaza @BBCNews
@GH99953797@newsoncool Capacity insufficient to meet demand. Massive hospital waiting lists multiples of those in Britain increasing Gp workload. Diminishing GP workforce unable to recruit due to pressures. Inadequate resourcing for GP staff & services a fraction of that provided in Britain
⚠️🗣GP HITS OUT: 'There’s a narrative that GPs are lazy and play golf in the afternoon. It’s not true. The wheels are falling off.'
❗️Belfast GP Dr Michael McKenna warns Northern Ireland risks losing the next generation of GPs due to mounting pressure on services.
🎤He sat down with Chief Reporter @jamesgould23.
⁉️He says doctors are now “looking at what action they can take” to secure more funding.
✅️It comes after Health Minister Mike Nesbitt confirmed he will impose the 2025/26 General Medical Services (GMS) contract, despite it being rejected in a ballot by @BMA_NI GPs.
🙌Dr McKenna says being a doctor in his community is the “honour” of his life, but warns the situation is deteriorating.
He acknowledges public frustrations around access and phone delays, and says he wants things to improve.
@BMA_NI@healthdpt Have destabilised the majority of practices which do not have full mdts and are at a recruitment/retention disadvantage to the chosen few. Healthcare apartheid.
@No2Inequality@MyFermanagh@FermanaghJulian So disheartening to the people who go to work there and try to deliver some sort of service in a broken system. It will make it even harder to retain staff. Protest at the Department of Health and the politicians offices.
Informative data-led graphs @PeterShirlow that show how erroneous the anti-immigrant narrative is.
NI is 96% white and no other ethnic group exceeds 1% of the population. We are 90% Christian with just 1.5% all other religions. Total annual immigration (most recent figures) is 2,300 people including from EU and America - that’s just 0.1% of the NI population.
NI is not being flooded with immigrants, our culture & identity is not threatened by immigrants but rather is enhanced and enriched, and immigrants are not stealing our jobs or houses. In fact NI employment and wages are the best they have ever been, while problems with housing are because we do not build enough homes for an indigenous population that is growing naturally.
It is understandable that some communities feel frustrated and let down by problems in society that have not been solved. But there is nothing legitimate about blaming immigrants for these problems or taking part in protests that are erroneous in their diagnosis and are only serving to spread fear and disorder on our streets.
Seems like a good time to re-post my older (now edited) post about athletes with XY DSDs (Disorder, or Difference of Sex Development). Lots of graphs and detail about the relevant biology at the end.
* * *
First: People living with DSDs should be treated with compassion and understanding, and receive any heath care they need. These can be challenging conditions for individuals and their families. But when male athletes have DSDs that give them an advantage over females, and they compete in the female category, this raises concerns about safety and fairness, and forces discussion of the relevant physical traits.
Athletes with XY DSDs who have testes (usually internal), XY sex chromosomes, male-typical levels of testosterone, and functional androgen receptors are often described as females with "hyperandrogenism," i.e., abnormally high levels of testosterone. They experience physical benefits of this high testosterone during puberty, which translate into athletic advantages over females. The issue for sports is that athletes with the XY DSD 5-alpha reductase deficiency (5-ARD), may be socialized as female, may be legally female, and may live and identify as female; but they are male.
These individuals are usually born with female-appearing genitalia, which can lead to being sexed as female. Here's why. 5-ARD is caused by a mutation in the gene that codes for the enzyme 5-alpha reductase, which converts testosterone into a more potent androgen, DHT. This androgen interacts with the androgen receptor, like testosterone, and is necessary for the typical development of male external genitalia (penis and scrotum) and the prostate. Without DHT, female-typical external genitalia develop. At the end of this monster post is a graphic of the relevant steroid production pathway, from my book T: The story of Testosterone.
DHT is also responsible for male-pattern baldness and dark, coarse facial hair, which is why people with the condition have smooth skin that can give a feminine appearance.
The “decision makers” are aware that athletes with 5-ARD are male, and that they experience the benefits of male puberty. The requirement to reduce their testosterone to typical female levels isn’t discriminatory, since these are males who are asking to compete in the female category. But more significantly, all the relevant scientific evidence shows that reducing male T in adulthood does not undo the physical benefits of male puberty.
Here's more detail about T, DHT, and male advantage in strength and speed.
I've been asked if men with the DSD 5-ARD (in which ppl cannot convert testosterone into the more potent androgen DHT) experience the typical benefits of male puberty, that would give them an advantage in strength and speed relative to women. This is relevant to questions about whether male athletes with 5-ARD should be allowed to compete in the female category. This is an excellent question, because it could be the case that DHT is necessary for the development and maintenance of male-typical muscle, lean body mass and strength. If that were the case, then people with 5-ARD might not have a typical male advantage, because the lack of DHT would perhaps lead to a more feminine pattern of fat, lean body mass and strength. I've wondered about this myself and have looked into the evidence.
Perhaps the top researcher in this area, Shalendar Bhasin, who is scrupulous in his methods, has examined this very question. The answer appears to be: no, testosterone does not need to be converted to DHT to exert its typical anabolic effects. These findings are reported in his 2012 study, "Effect of Testosterone Supplementation With and Without a Dual 5α-Reductase Inhibitor on Fat-Free Mass in Men With Suppressed Testosterone Production, A Randomized Controlled Trial." (It is linked to below—and since it's paywalled, I've included the graphs that show comparisons between the placebo and DHT— inhibited conditions, with no difference on the various outcomes.)
For more detail, the investigators wanted to examine the effects of suppressing DHT on muscle mass, strength, and sexual function. This important because one of the treatments for benign prostatic hyperplasia and male-pattern baldness is to suppress DHT, but clinicians have been concerned about effects on other outcomes that affect health and quality of life. Participants (healthy men, 18 to 50, with normal T levels) had their T blocked, and were given graded doses of T, along with either placebo or a drug that blocked the conversion of T to DHT. So both groups had T, but only one, the placebo group, also had DHT. After 20 weeks of treatment, changes in lean body mass, muscle, and strength were assessed. There were no significant difference between the placebo and DHT-blocked groups in these outcomes.
For LOTS more detail, here's the relevant text from the results. Please don't ask me questions about the study. Just look at the abstract and results which you can find by Googling. The main point is that while there are predicted effects of the different doses of T received, there were no differences in the outcomes according to whether they had DHT blocked (with dutasteride) or not (placebo). "Fat-Free Mass Fat-free mass and lean body mass increased in a dose-dependent manner in the placebo and dutasteride [THIS IS THE DRUG THAT BLOCKS CONVERSION OF T TO DHT] groups (Figure 2).
The changes in fat-free mass were related to testosterone dose and changes in testosterone concentrations in the placebo and dutasteride groups but did not differ between groups; the dose-adjusted mean difference (placebo minus dutasteride) in fat-free mass was 0.50 kg (95% CI, −0.22 to 1.22 kg; P = .18). There was no significant interaction between testosterone dose and randomization to dutasteride or placebo, indicating a lack of evidence that the relationship of testosterone dose to change in fat-free mass differed between the dutasteride and placebo groups.
The model-based smoothed regression lines, obtained by generalized additive models, describing the relationship between changes in testosterone concentrations and changes in fat-free mass and lean body mass were similar in the placebo and dutasteride groups. Changes in fat mass were negatively related to testosterone dose and concentrations, but the relationship between change in fat mass and dose did not differ significantly between the placebo and dutasteride groups (P = .41; Figure 2)."
"Muscle strength Leg-press and chest-press strength increased dependently by dose in the placebo and dutasteride groups. Increases in leg-press and chest-press strength were greater with larger doses and higher concentrations of testosterone. These relationships did not differ between the placebo and dutasteride groups (Figure 2)."
Really interesting commentary from the authors on the role of DHT in adult men: "Why then did the steroid 5α-reductase system evolve for androgens? Forty-six XY males with steroid 5α-reductase deficiency exhibited ambiguous or female external genitalia at birth and poor prostate development, but underwent normal muscle and bone development during pubertal transition. The phenotype of these patients suggests that steroid 5α-reductase plays an essential role in the development of prostate and phallus by providing local amplification of an androgenic signal without systemic hyperandrogenemia during critical periods of sexual differentiation, illustrating nature's extraordinary ingenuity in creating mechanisms for tissue-selective amplification during development.
We speculate that in adult men, in whom this tissue-specific amplification is not essential because the circulating testosterone concentrations are substantially higher than those in the fetus, testosterone and DHT can interchangeably subserve many androgenic functions. When circulating testosterone concentrations are low, intraprostatic DHT formation may become important in maintaining prostate growth, thus buffering the effects of decreasing testosterone levels, which has been suggested by Marks et al.
Our data are consistent with studies that have reported no effects of 5α-reductase inhibitors on muscle or bone mass. Inferences from these trials are limited by the fact that administration of 5α-reductase inhibitors increases testosterone levels, rendering it difficult to ascribe the outcomes to differences in DHT levels alone. In our trial, inhibition of endogenous testosterone by administration of a gonadotropin-releasing hormone agonist eliminated this problem. Additionally, the high-dose dutasteride regimen effectively inhibited both steroid 5α-reductase isoenzymes."
Can an anti-inflammatory diet reduce knee pain? 🤔
This single-arm feasibility study investigated the effects of a 9-week anti-inflammatory diet on knee pain in 28 individuals with symptomatic knee osteoarthritis🦵💥
The anti-inflammatory diet consisted of…
High amounts of fish, fruit, vegetables, nuts & seeds 🥗
Moderate amounts of lean meats, eggs & dairy 🥛
Focus on monounsaturated fats from fish, seeds & olive oil 🥑
Limit highly processed & refined foods such as pasta, breads, rice, confectionary & processed meats ❌
Results.
Self-report knee pain & quality of life measures were significantly improved after the intervention ✅
Participants also lost on average 3kg in bodyweight ✅
And 32% reported using much less pain relief medication at the end of the study ✅
More research and RCTs required, but this study does show positive evidence that an anti-inflammatory diet could be a useful applied intervention to help manage pain 👈
The 10 biggest cancer papers of the last 10 years (in my opinion)
1. Blocking PD1 activates the immune response against cancer - especially if the cancer has more mutations
https://t.co/rBCVRcDfvo
If you reduce the skillset in primary care (GPs) and ED and replace the clinical reasoning and ability to go back to core principles and determine risk then what happens is:
1) referrals to specialties increases
2) extra investigations and imaging is done
3) protocolised medicine works on simple pathways leading to the above two
4) increased activity leads to increased costs
This is why healthcare cost in the U.K. is going to go up by 3x in the next 10 years.
How our lives, our planet and our mental health got trashed by something we scarcely understand: a doctrine that changed everything. Neoliberalism.
This week's column.
https://t.co/YUIOlD1beD
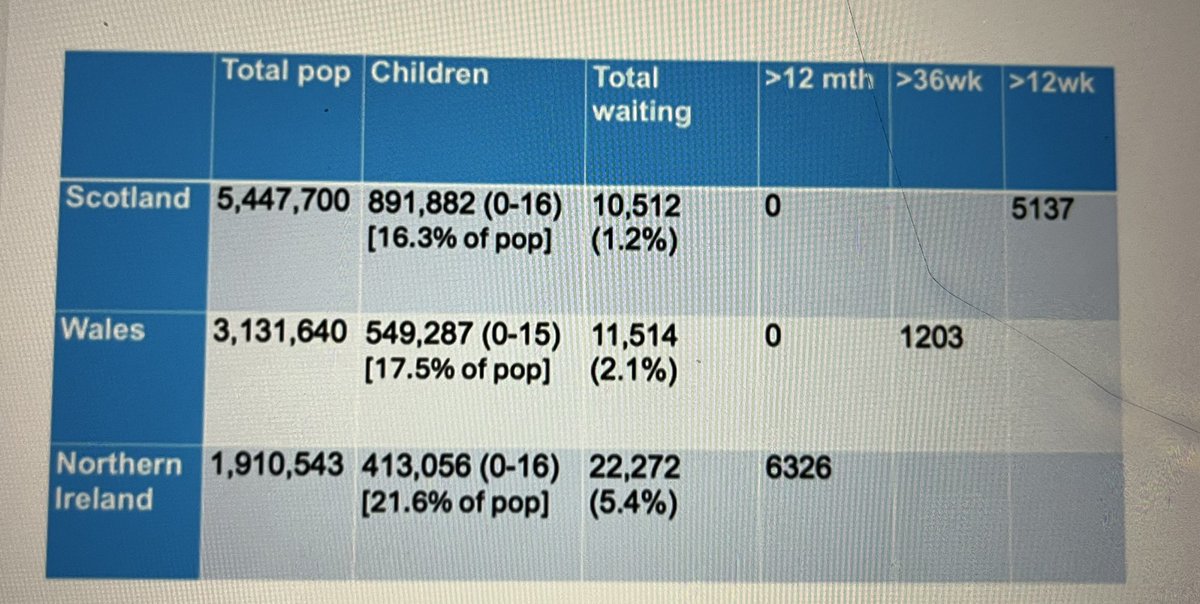
New report from RCPCH on Waiting Lists for children in NI paints a damning picture.
Number of children waiting more than 12 months:
Scotland 0
Wales 0
NI 6,326
Haven’t we have tolerated this appalling performance for far too long?
@NIAuditOffice Insufficient assessment of impact of disparity of funding support (eg for mdts & premises) on gp capacity/recruitment & retention/practice sustainability & also impact of reduced secondary care access (eg in rural areas) on primary care demand.
The conspiracy theories around Kate are absolutely absurd!
We see W&K most days and in the last couple days too!
It beggars belief that people would be so ridiculous and cruel in writing BULLSHIT on this platform that are out and out lies!
W&K are the most wonderful parents and as normal/humble as they come. Let K who is recovering from an operation recover.
Leave her and her beautiful family alone!!!!
cc @KensingtonRoyal
@HollyerMarcus ‘Junior’ dr is a misnomer which the profession must amend. All striking tomorrow are highly trained, skilled clinicians intentionally undervalued by both government and employers. Those in NI deliver higher workload & responsibility for less pay. Solidarity.