Absolute iron deficiency affects approximately 2 billion people worldwide.
This narrative review examines the screening, diagnosis, and treatment of adults with absolute iron deficiency without anemia and iron-deficiency anemia. https://t.co/JRDMdhXJjT
Immune thrombotic thrombocytopenic purpura (iTTP) is an immune-mediated disorder characterized by thrombocytopenia and microangiopathic hemolytic anemia.
Learn more in this Review. https://t.co/YQF7gIkUu8
🧵 1/9
📢 Just published!
"Advances in the Treatment of AML: Implications for Low- and Middle-Income Countries"
🔓 Open access: https://t.co/3dQONA8BEx
🧬 This thread breaks down key insights—and how they can help improve AML care in resource-limited settings.
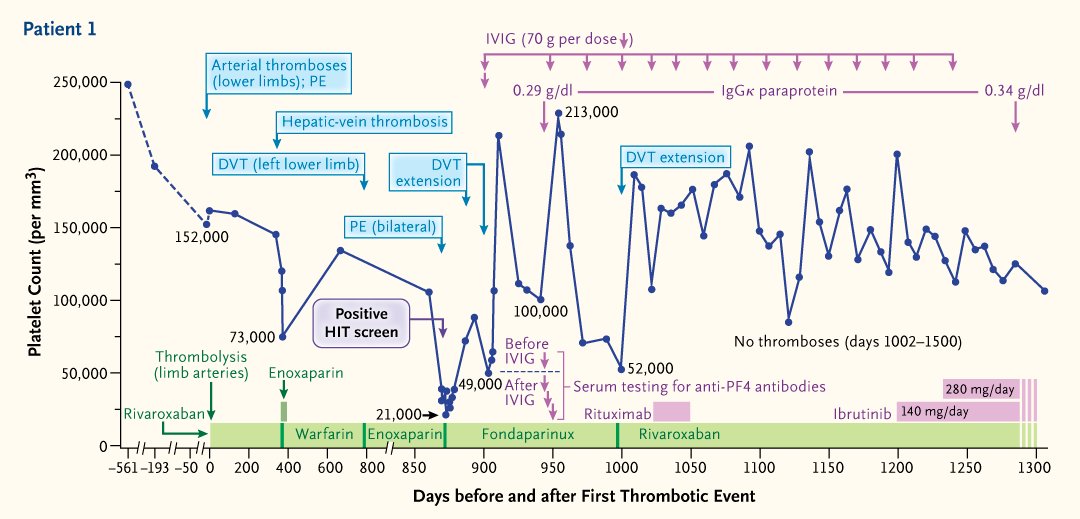
Patients with a prothrombotic clinical course often associated with thrombocytopenia may have a monoclonal paraprotein, even at low levels, that activates platelets by binding to platelet factor 4. Learn more in a Brief Report: https://t.co/te1RtMJ17B
#Hematology
📢 Guide to Switching Anticoagulants 📢
Clinicians often face the challenge of transitioning between anticoagulants. Here’s a simplified breakdown with clinical pearls! 🧵👇
🔄 Warfarin to NOACs (Rivaroxaban, Apixaban, Dabigatran)
✅ Stop warfarin & start:
🔹 Rivaroxaban when INR <3.0
🔹 Apixaban when INR <2.0
🔹 Dabigatran when INR <2.0
💡 Pearl: Warfarin has a long half-life, so overlap may be needed in high-risk cases!
🔄 Warfarin to LMWH
✅ Start LMWH when INR <2.0 for DVT/PE treatment
✅ For stroke prevention, wait until INR <2.5
💡 Exam Tip: If renal impairment exists, plasma concentrations may be higher than expected—monitor closely! 📉
🔄 LMWH to NOACs
✅ Discontinue LMWH & start:
🔹 Rivaroxaban 0–2 hrs before next LMWH dose
🔹 Apixaban/Dabigatran at next scheduled LMWH dose
💡 Pearl: Timing matters—prevent thrombosis by ensuring minimal interruption! ⏳
🔄 NOACs to Warfarin
✅ Overlap required 📊
🔹 Rivaroxaban: Stop when INR is in range
🔹 Apixaban: Continue for 2 days, stop when INR ≥2.0
🔹 Dabigatran: Based on CrCl—stop 2-3 days before
💡 Clinical Tip: Dabigatran increases INR! Measure INR 2 days after stopping to avoid false elevation! 🚨
🔄 Switching Between NOACs
✅ Direct Switch ⏩
🔹 Discontinue Rivaroxaban/Apixaban/Dabigatran & start new NOAC at the next scheduled dose
💡 Pearl: NOACs have fast onset—no need for overlap! 🚀
🔎 Key Takeaways
🔹 Warfarin needs INR monitoring when switching
🔹 LMWH requires careful timing
🔹 NOACs allow direct switch at next dose
🔹 Dabigatran + INR = tricky—be cautious!
💡 Clinical Pearl: Always assess renal function before switching! 🩺
#MedEd #Anticoagulation #NOACs #Warfarin #Hematology
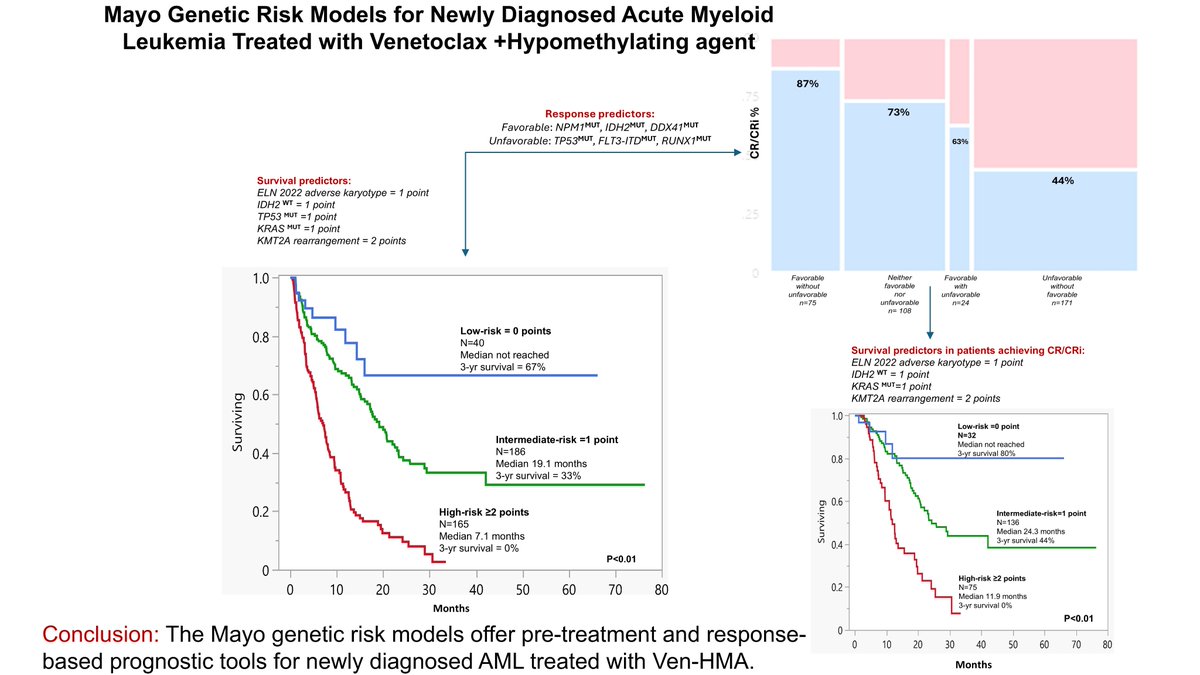
The Mayo genetic risk models offer pre-treatment and response-based prognostic tools for newly diagnosed #AML treated with Ven-HMA
Open access: https://t.co/bQMQbJCacm
#LeuSM@AntoineNSaliba
Drinking more than 3 cups of coffee, especially in the mornings rather than throughout the day, may be one of the easiest ways to increase survival! Hurray for coffee…in the mornings 🤪☕️
https://t.co/7q0jludeHv