#100DaysOfRheum Day 40 🧪
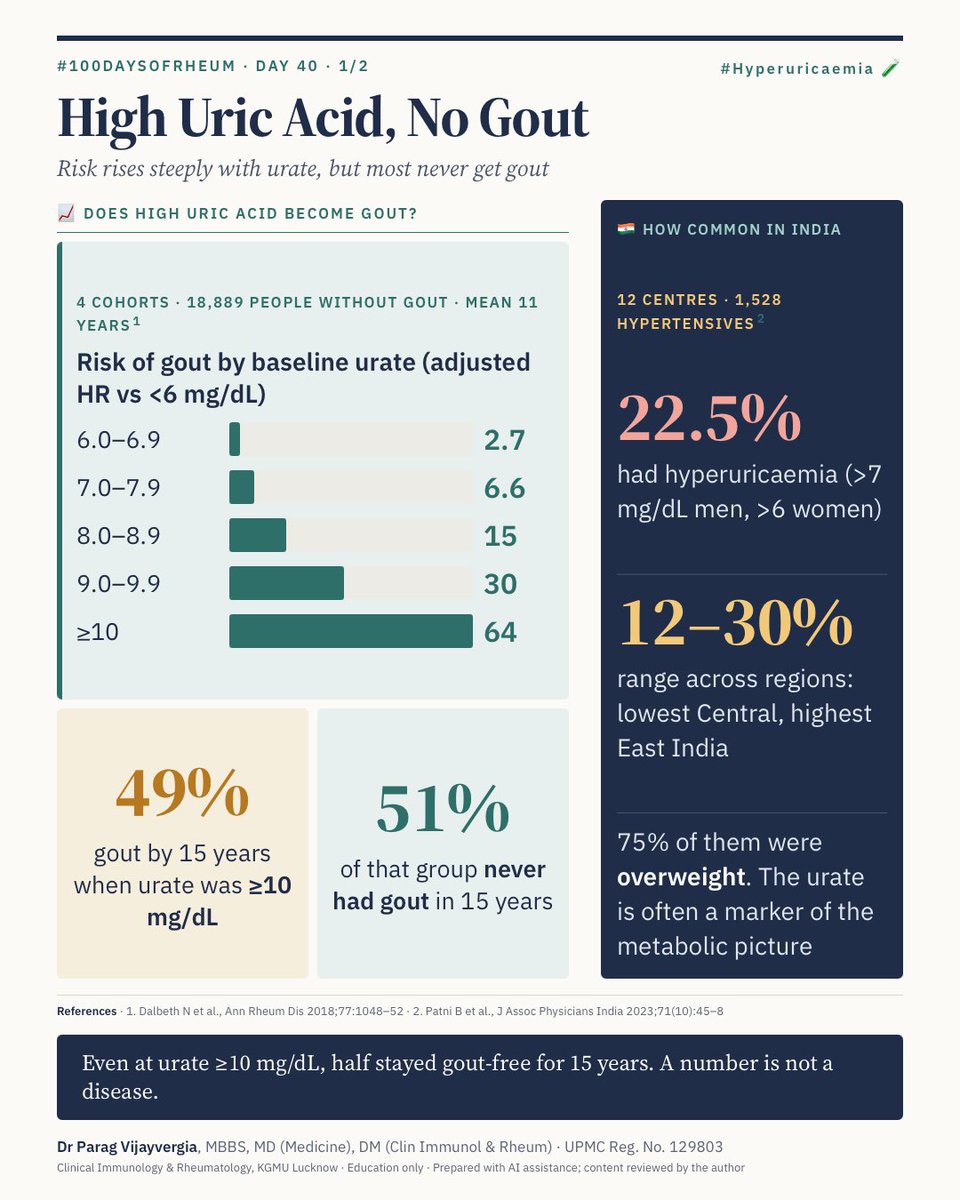
High uric acid, no gout. Start febuxostat?
18,889 people: even at urate ≥10 mg/dL, 51% stayed gout-free for 15 yrs
CKD-FIX, PERL: no kidney benefit
ALL-HEART: no heart benefit
ACR 2020: conditionally against drugs
Treat gout, not a lab value.
🔥Hot off the press for #ACR26 🔥
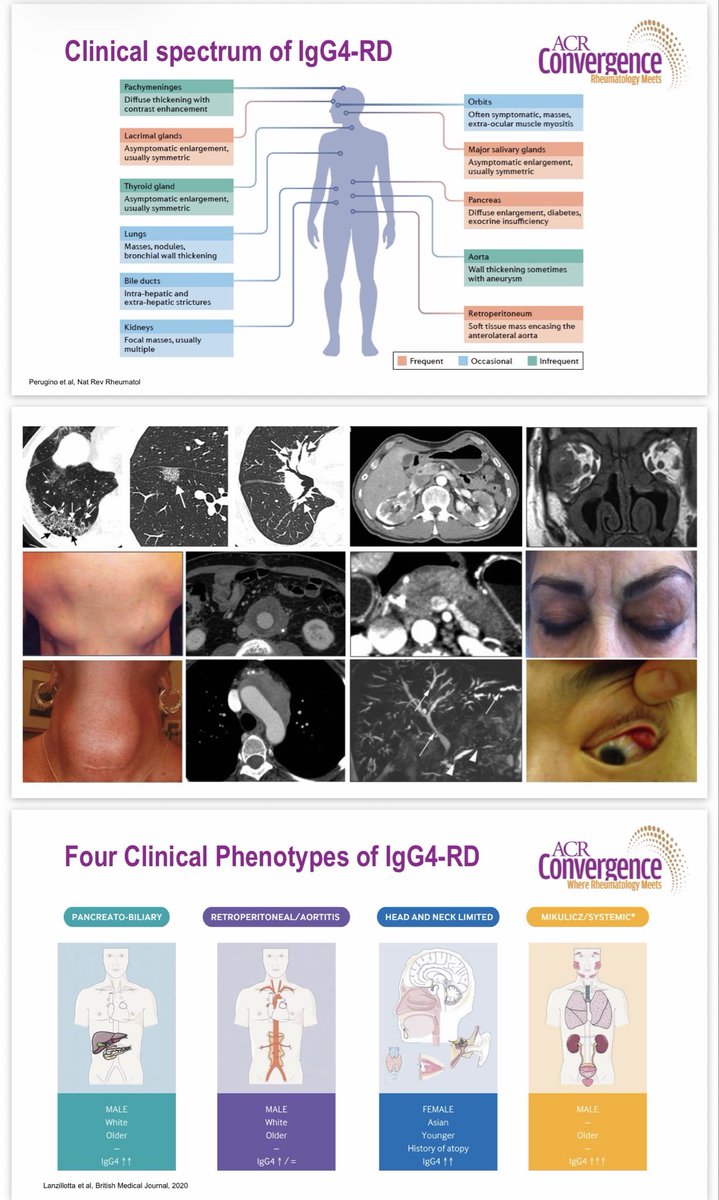
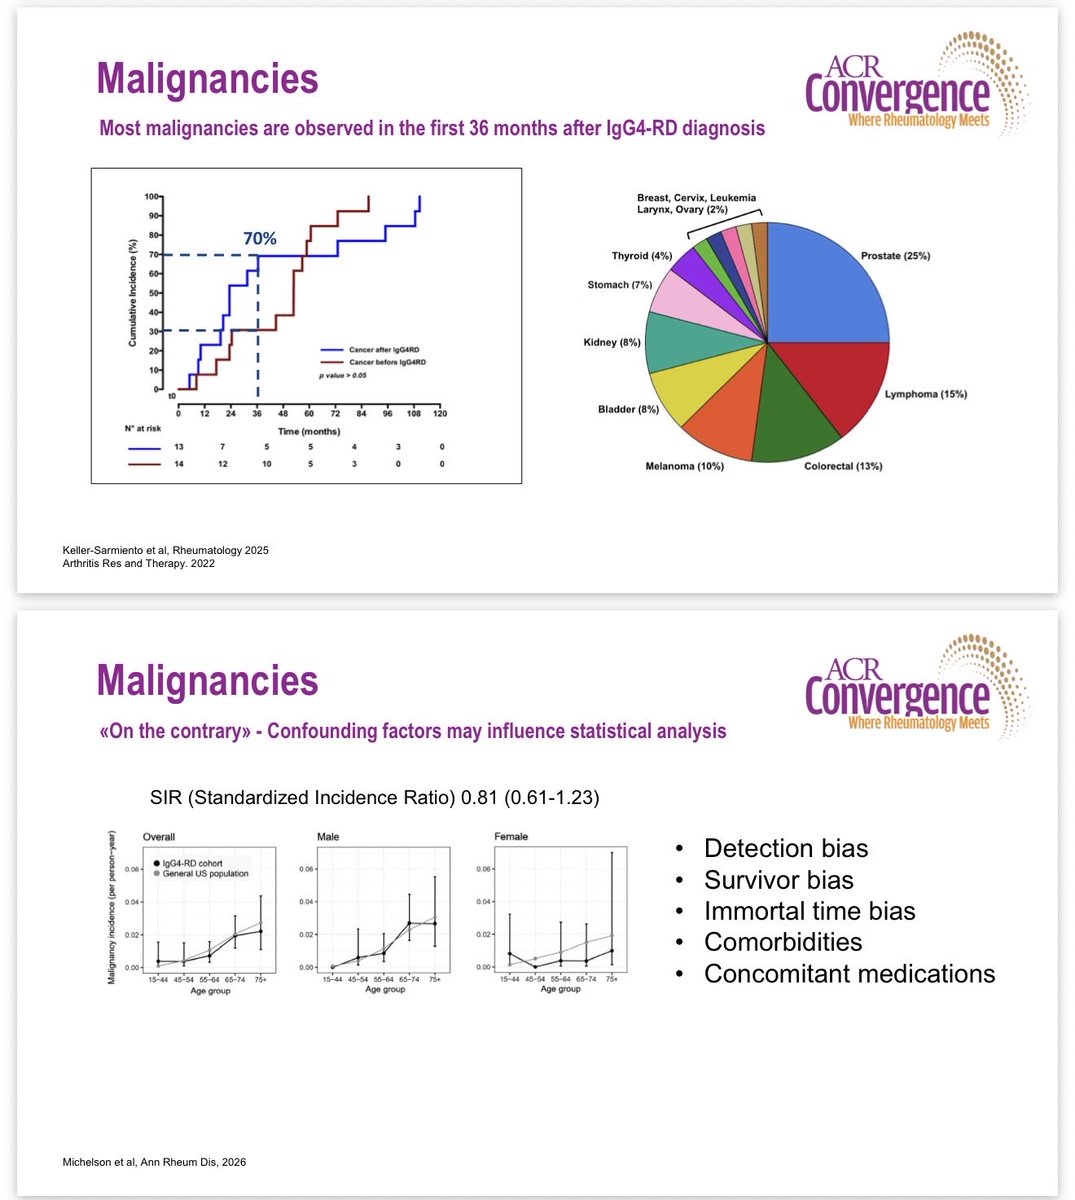
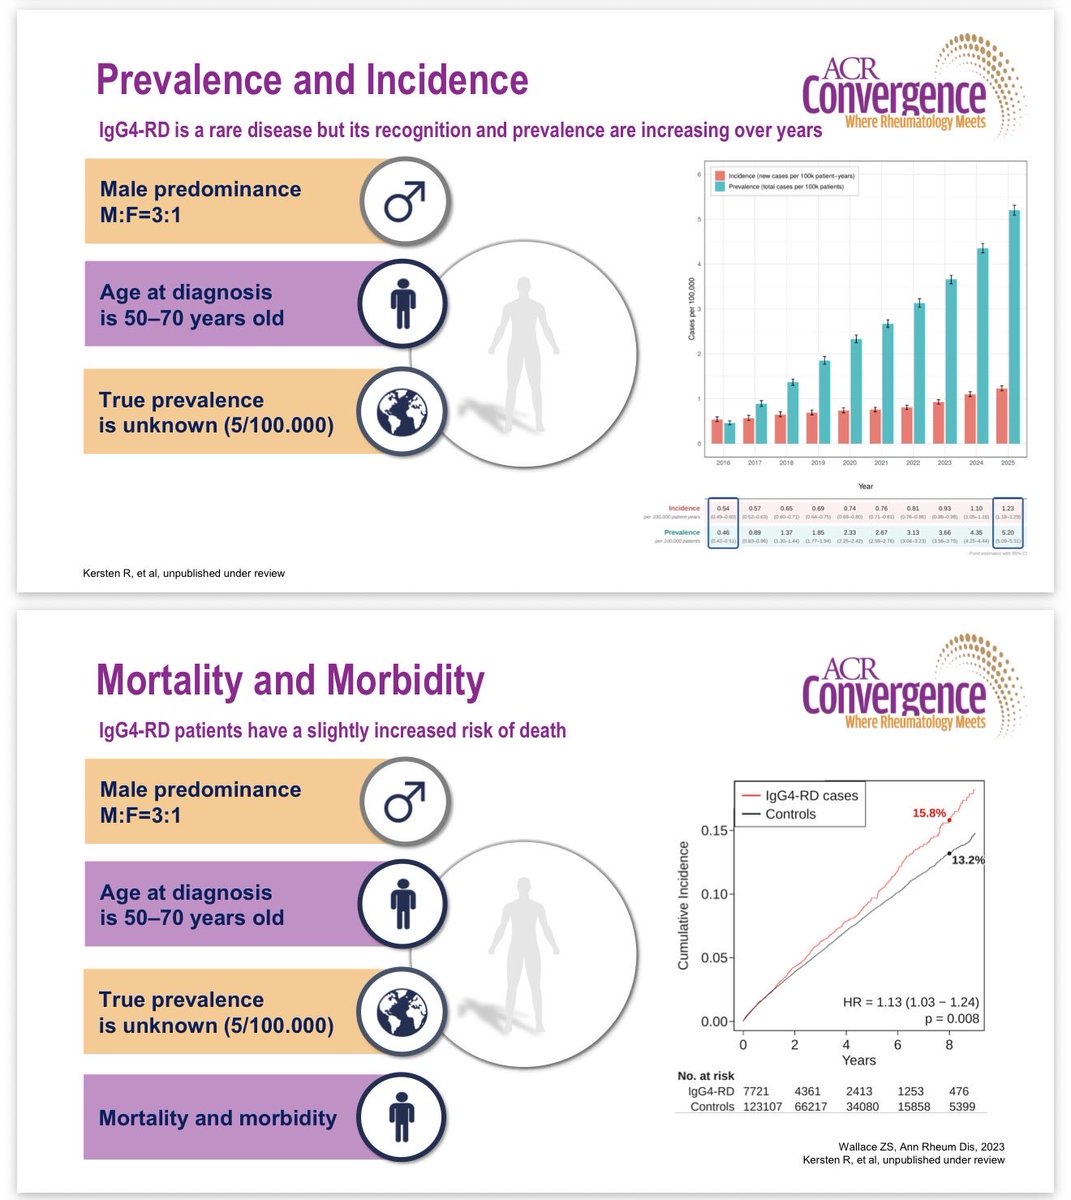
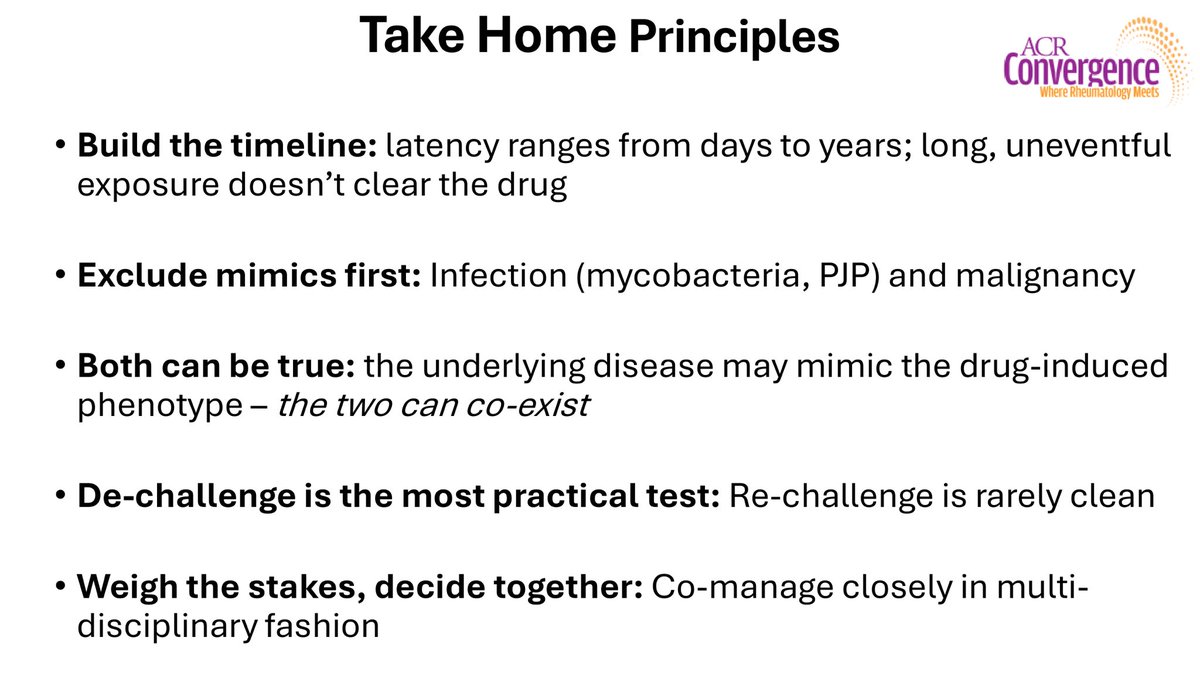
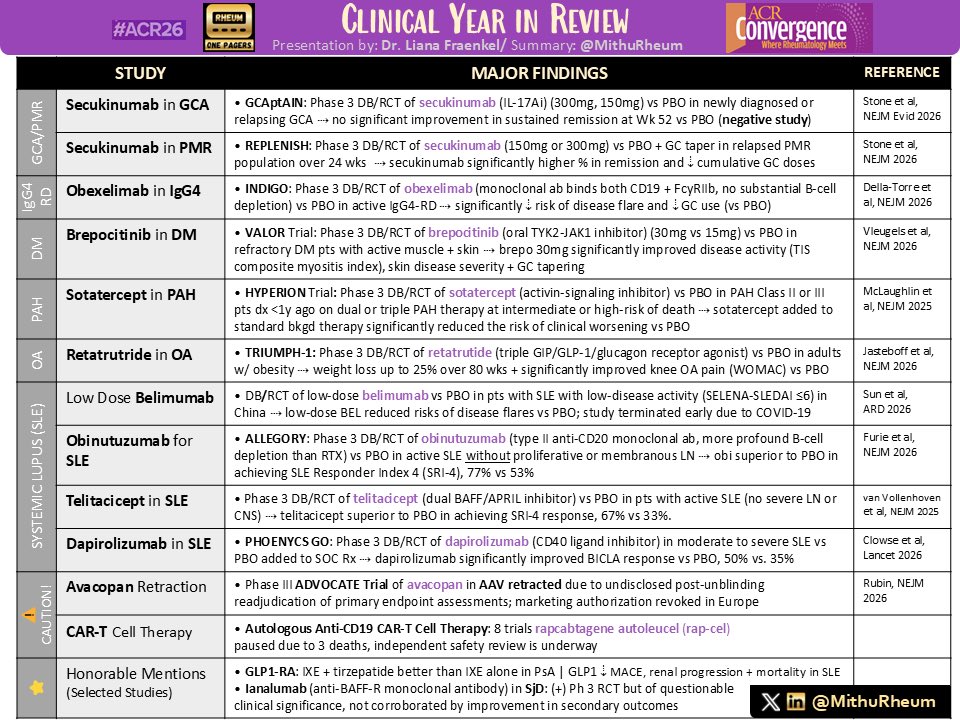
The @IgG4ward foundation guidelines on the treatment of IgG4-related disease
https://t.co/B3NKHxDKzK
Free to read on https://t.co/gt6JPgLHUG
Menopause can mimic a flare. Ask before escalating.
#ACR26 | Hormone therapy in SARDs:
• Stable, aPL-negative SLE: consider for severe vasomotor symptoms after assessing contraindications.
• SELENA: mild–moderate flares ↑34%; no significant rise in severe flares. High-risk aPL/prior thrombosis excluded.
• APS: avoid systemic estrogen—even anticoagulation does not establish safety.
• Vaginal estrogen: may relieve dryness/dyspareunia after lubricant failure; minimal systemic absorption, limited SARD-specific data.
• RA: menopausal symptom and bone benefits; no proven disease-modifying effect.
• Systemic HT contraindicated? Consider nonhormonal options.
Match treatment to symptoms, disease stability and thrombotic risk.
Credit: Prof Karen H. Costenbader
#ACRambassador #Menopause #Lupus #Rheumatology
Erosions do not always mean inflammation. Sometimes, the clue is hormonal.
Hyperparathyroidism—the metabolic mimic worth remembering at #ACR26.
Six imaging pearls:
• Radial middle-phalangeal subperiosteal resorption: the classic giveaway.
• SI-joint resorption with pseudo-widening: a sacroiliitis mimic.
• Acro-osteolysis: look beyond systemic sclerosis.
• Brown tumours: bone lesions that can masquerade as neoplasia.
• Rugger jersey spine: think renal osteodystrophy and secondary hyperparathyroidism.
• Chondrocalcinosis: remember the association with CPPD.
A bone-health pearl: lumbar-spine DXA may miss the full picture in primary hyperparathyroidism. Remember the distal radius.
Read the image. Check the biochemistry. Reconsider the diagnosis.
Credit: Dr John A. Carrino, HSS.
#ACRAmbassador #Rheumatology #MSKImaging #Hyperparathyroidism
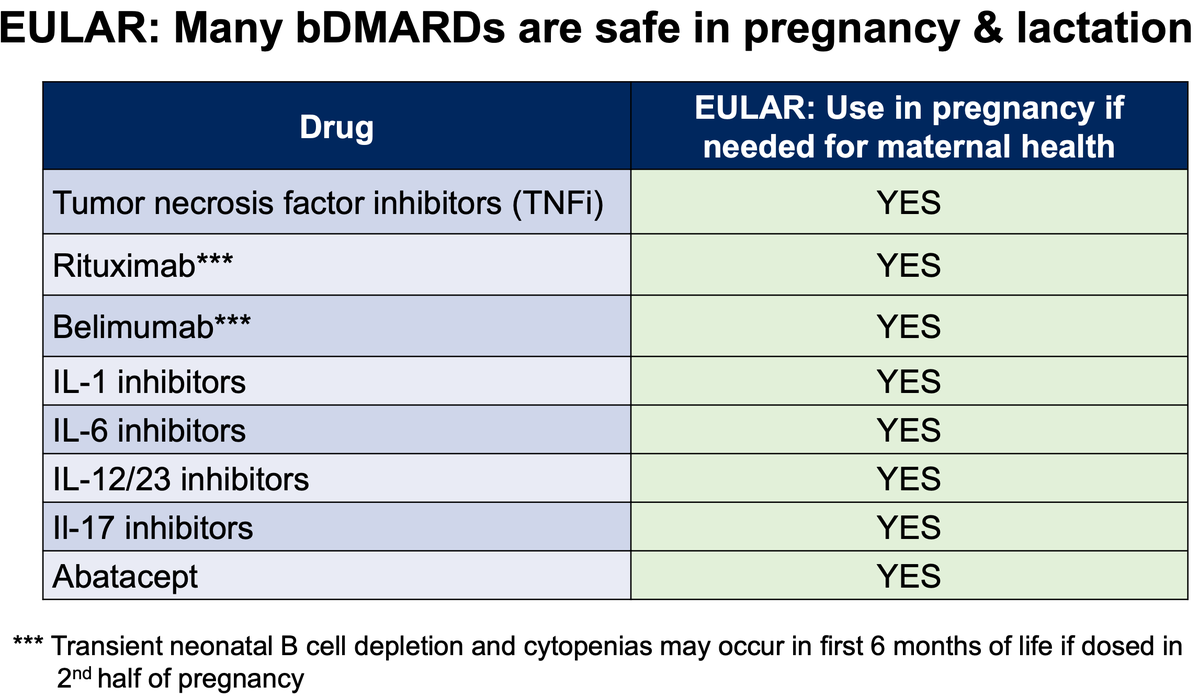
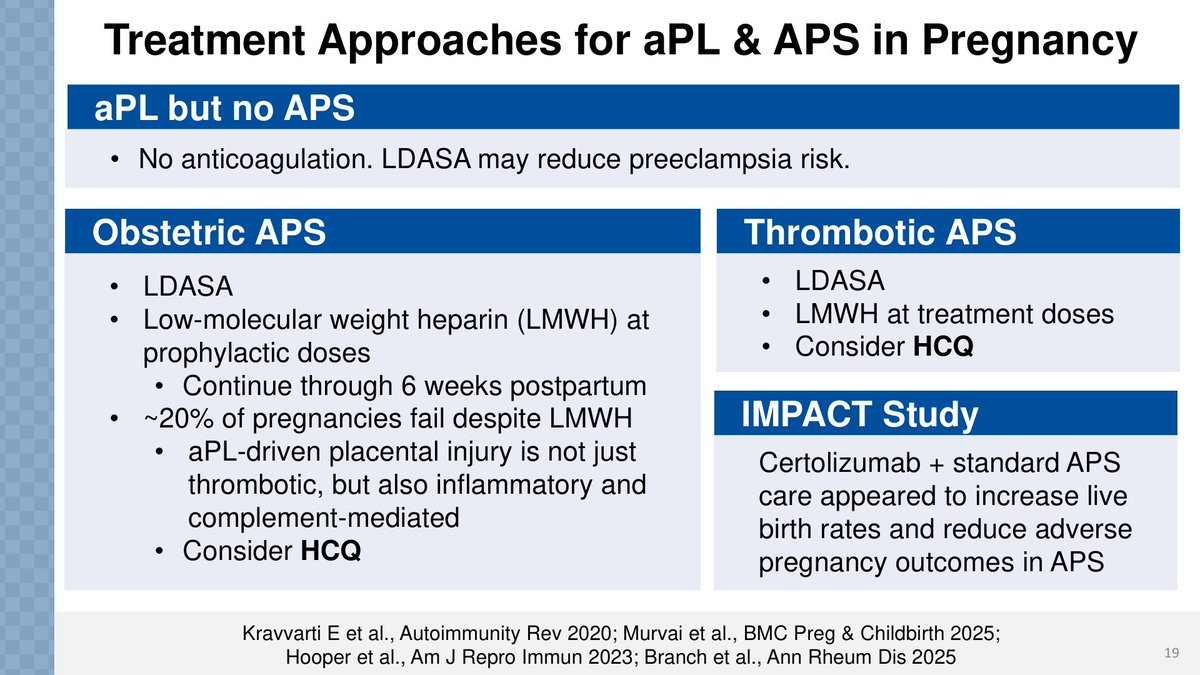
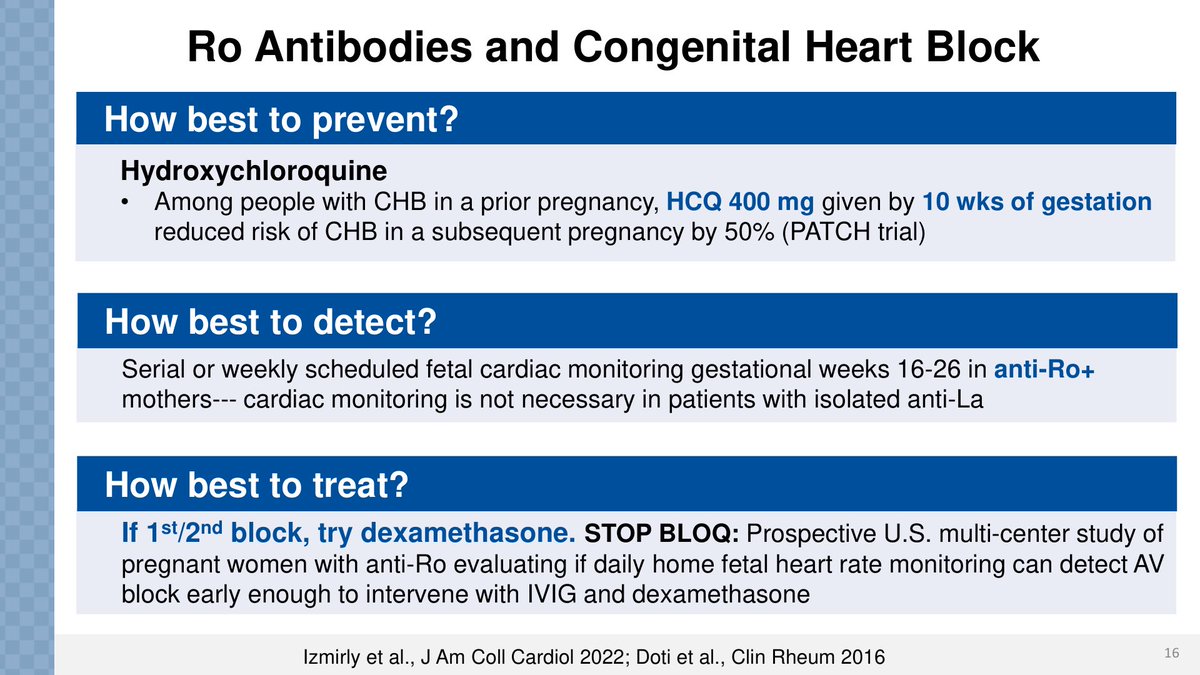
-Biologic DMARDs are generally safe for pregnancy: ETA and CZP safer compared to others.
-B cell depletion can be used in pregnancy but caution about neonatal cytopenias for first 6m if dosed in 2nd half og pregnancy.
-Counsel on vaccination for biologic exposed babies.
#ACR26@RheumNow
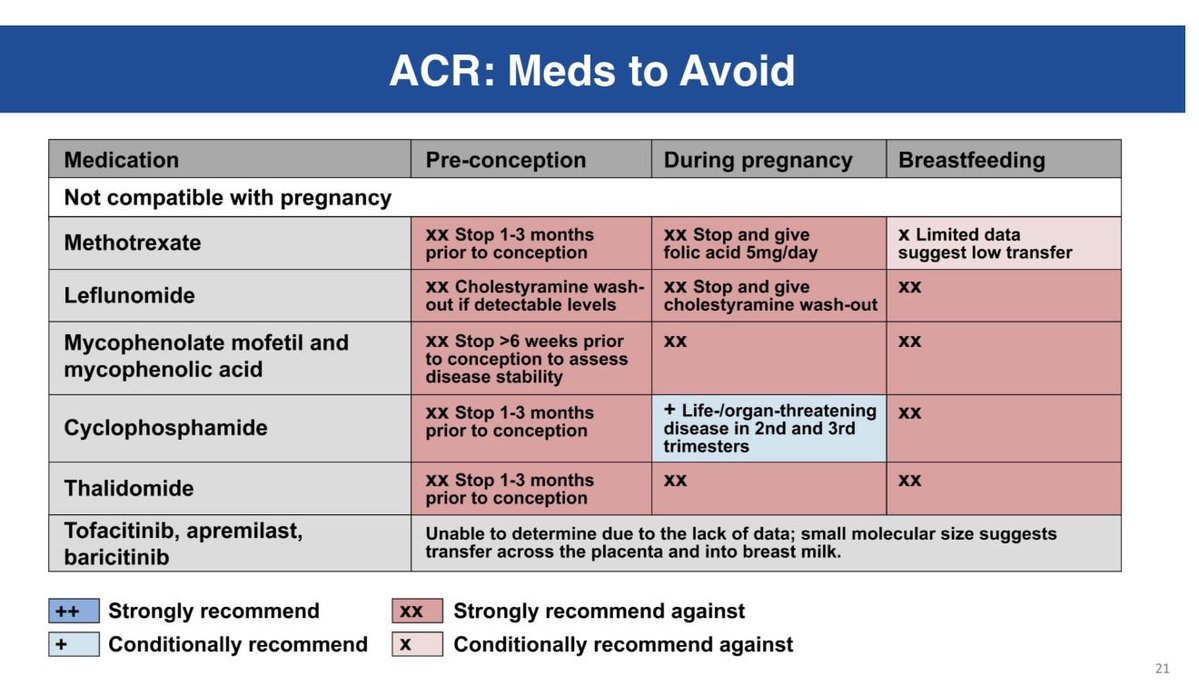
#ReviewCourse ACR: Drugs & Pregnancy ➡️ Avoid MTX, leflunomide and mycophenolate. HCQ, sulfasalazine, colchicine and AZA: compatible in pregnancy/lactation.
👁️ AZA Compatible with pregnancy, but linked to cholestasis. Check bile acids if itching; stop if confirmed. #ACR26
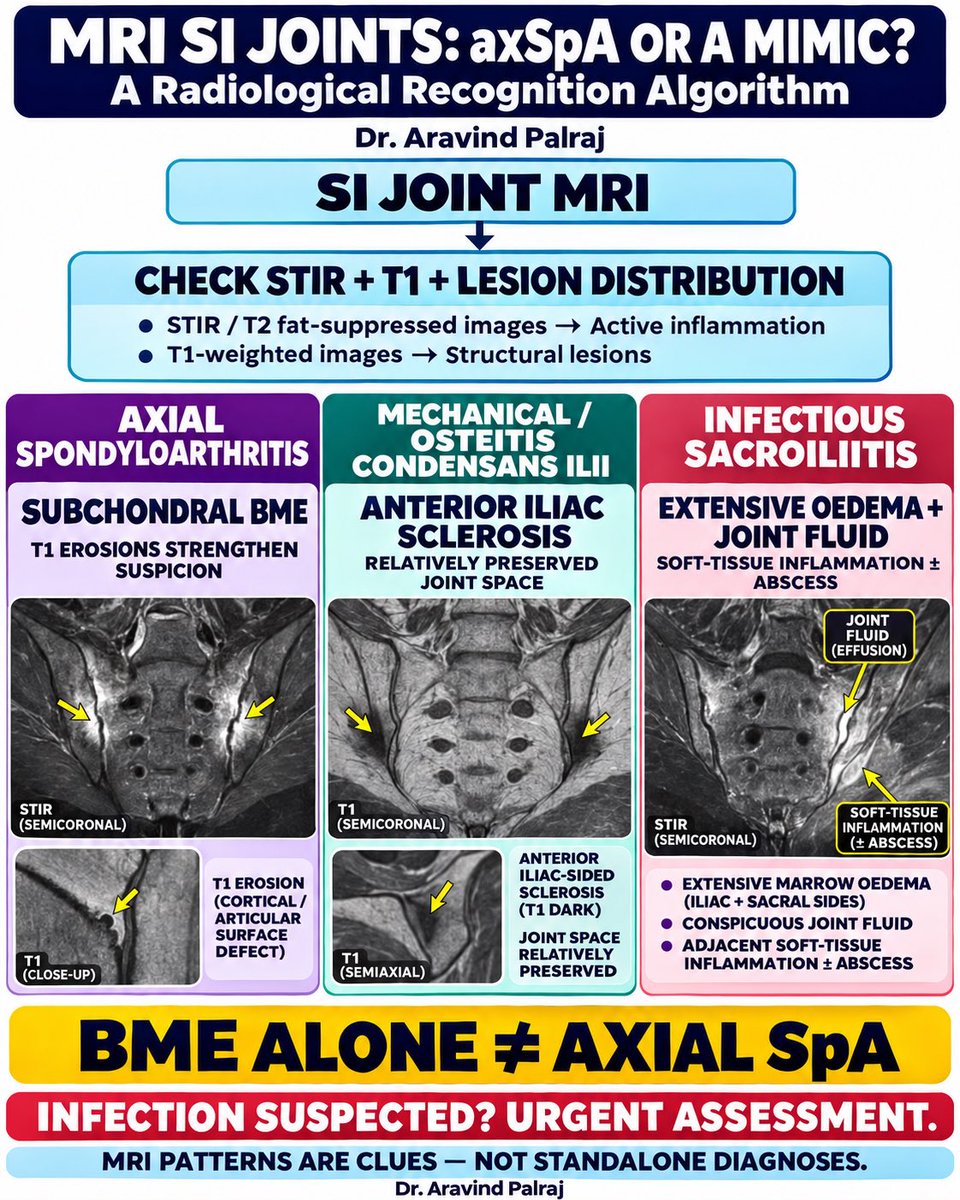
An abnormal MRI is a finding. The diagnosis still needs context.
Six diagnostic pearls from “Rare Rheumatology Findings” at #ACR26:
• Postpartum SI-joint marrow oedema can mimic inflammatory sacroiliitis. MRI positivity alone does not establish axial SpA.
• SAPHO: anterior chest-wall involvement + contiguous thoracic vertebral osteitis, often with disc sparing.
• Sarcoid dactylitis: lace-like phalangeal osteolysis, typically without periosteal reaction.
• Acute neck pain + odynophagia: calcification anterior to C1–C2 with prevertebral oedema suggests longus colli calcific tendinitis. Around/behind the dens? Consider crowned dens syndrome.
• A huge knee effusion with surprisingly little pain, a Baker’s cyst and popliteal nodes: consider Lyme arthritis when exposure and geography fit.
• “Tophaceous pseudogout” at the TMJ may represent an FN1-fusion–associated calcified chondroid mesenchymal neoplasm.
The most useful imaging clue may be the one that makes you reconsider your first diagnosis.
Which mimic have you encountered?
Credit: Dr Mohamed Jarraya, MGH/Harvard.
#ACRAmbassador #Rheumatology #MSKImaging
@adir_13@ifra772 مادري شلون اشرح لك بس فعليا اللي راكب وضعية سكوات مع شد الكور مستمرة مو مستسلم و جالس بالعكس رافع نفسه ! لا تقارنه بالجلوس والمشي لانه فعليا كانك تقارن wall sit بالجلسة علي كرسي و تقول نفس الشي
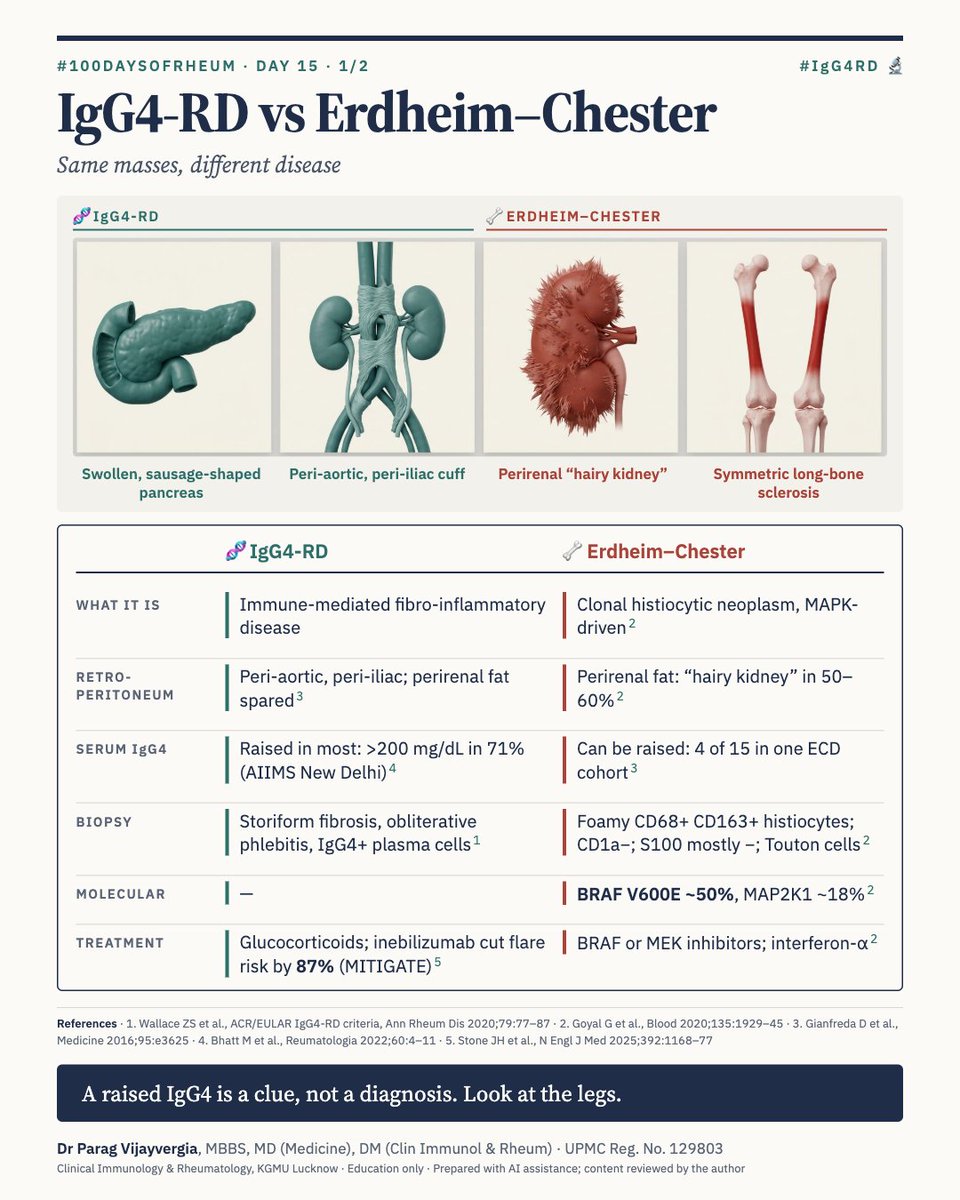
Day 15 #100DaysOfRheum 🔬
IgG4-RD or Erdheim–Chester? Both can involve the orbit and retroperitoneum.
🇮🇳 Indian IgG4-RD series (n=70): orbit 53%
🦴 ECD: long bones >95%, BRAF V600E ~50%
🧪 IgG4 can be high in ECD too.
No steroid response? Image the legs.
#IgG4RD#Rheumatology